

The DOI matches its Crossref record; 15 of the 17 references it cites were found in a registry or an index.
Assessment of Doxorubicin and Pembrolizumab in Patients With Advanced Anthracycline-Naive Sarcoma: A Phase 1/2 Nonrandomized Clinical Trial
Open accessAbstract
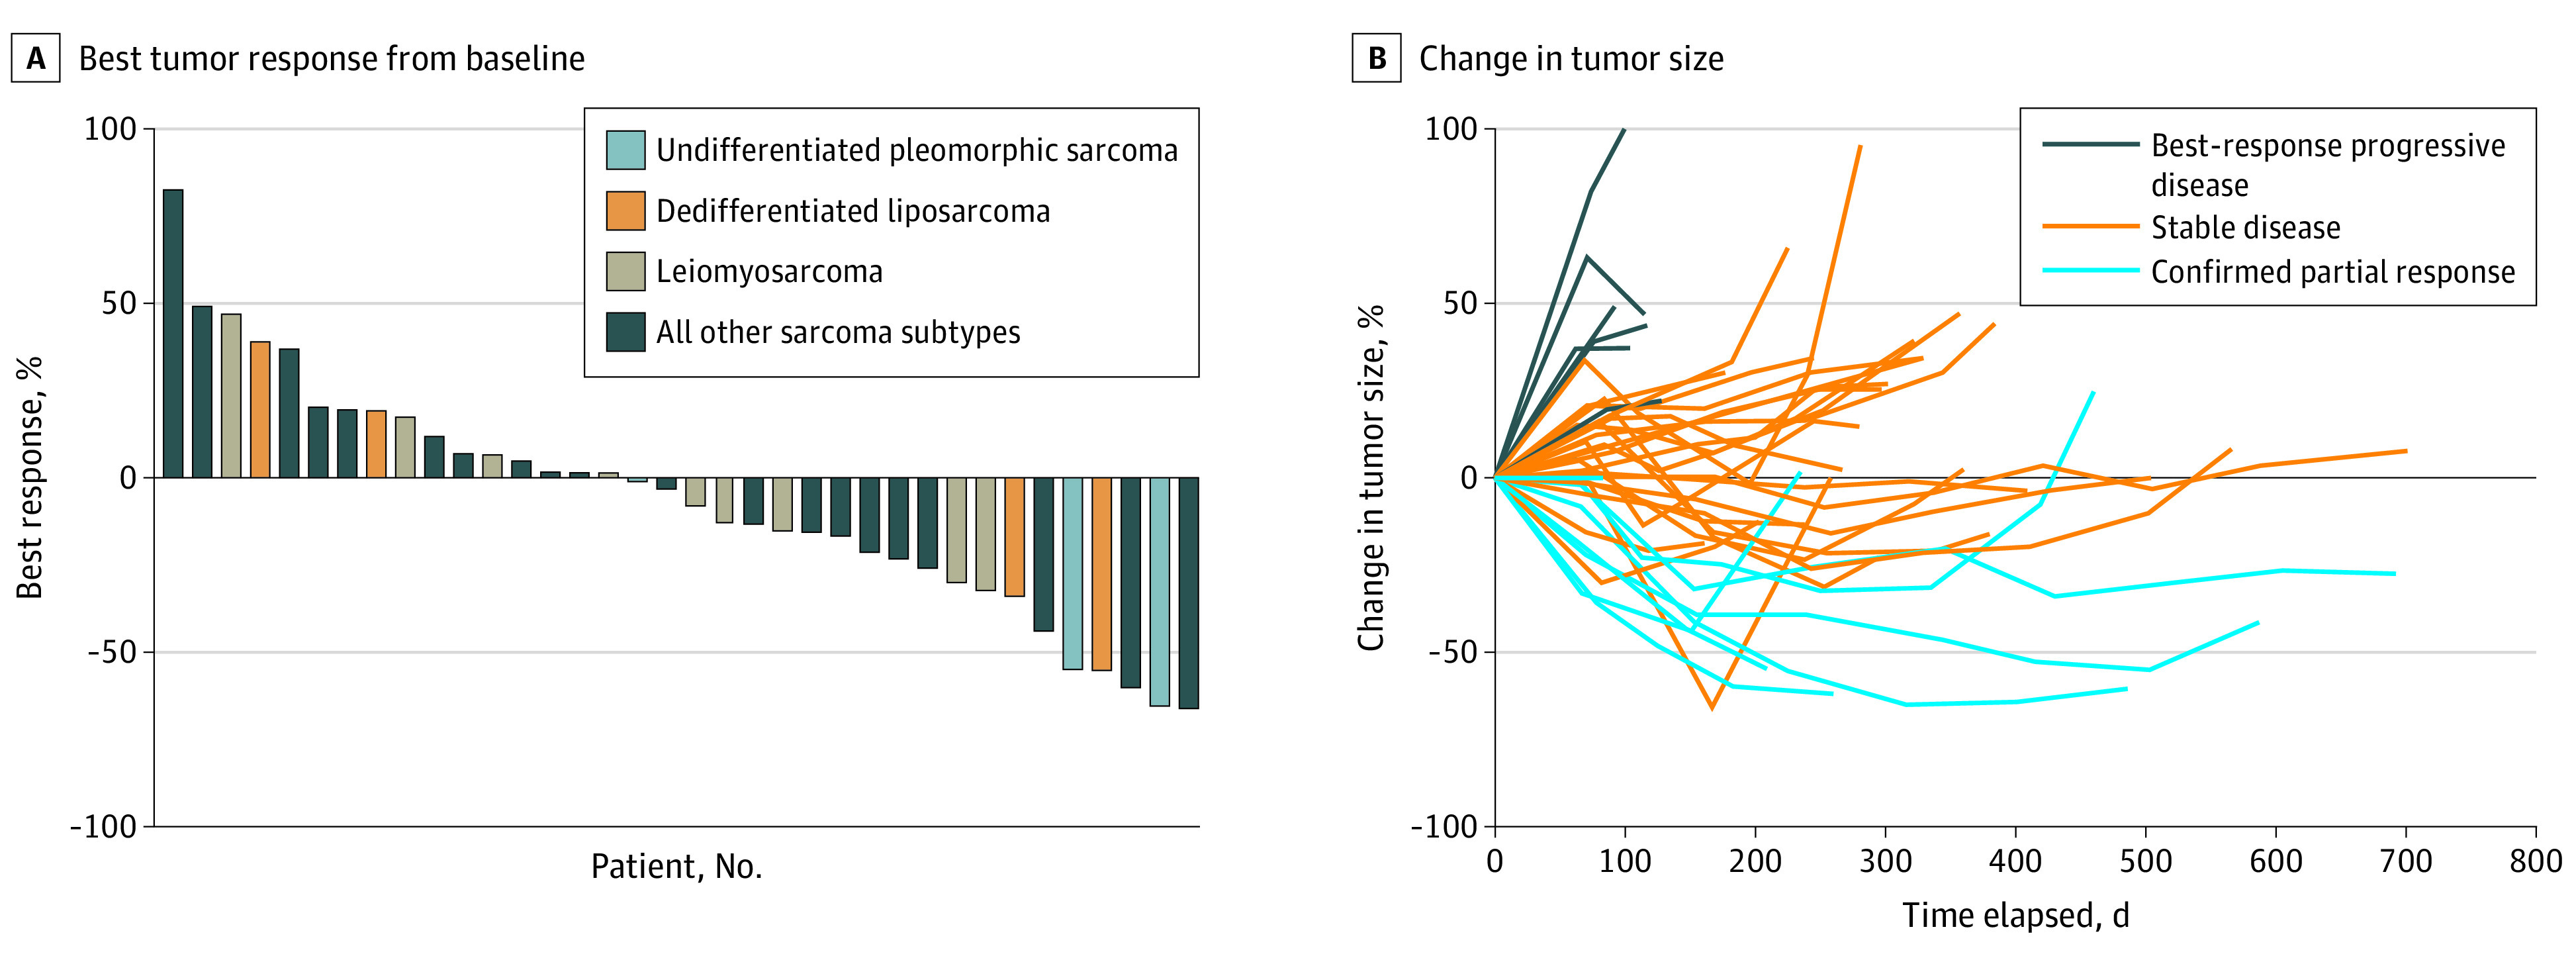
IMPORTANCE: Anthracycline-based therapy is standard first-line treatment for most patients with advanced and metastatic sarcomas. Although multiple trials have attempted to show improved outcomes in patients with soft-tissue sarcoma over doxorubicin monotherapy, each has fallen short of demonstrating improved outcomes. OBJECTIVE: To evaluate the safety and efficacy of doxorubicin in combination with pembrolizumab in patients with advanced, anthracycline-naive sarcomas. DESIGN, SETTING, AND PARTICIPANTS: This nonrandomized clinical trial used a 2-stage phase 2 design and was performed at a single, academic sarcoma specialty center. Patients were adults with good performance status and end-organ function. Patients with all sarcoma subtypes were allowed to enroll with the exception of osteosarcoma, Ewing sarcoma, and alveolar and embryonal rhabdomyosarcoma. INTERVENTIONS: Two dose levels of doxorubicin (45 and 75 mg/m2) were tested for safety in combination with pembrolizumab. MAIN OUTCOMES AND MEASURES: Objective response rate (ORR) was the primary end point. Overall survival (OS) and progression-free survival (PFS) were secondary end points. Correlative studies included immunohistochemistry, gene expression, and serum cytokines. RESULTS: A total of 37 patients (22 men; 15 women) were treated in the combined phase 1/2 trial. The median (range) patient age was 58.4 (25-80) years. The most common histologic subtype was leiomyosarcoma (11 patients). Doxorubicin plus pembrolizumab was well tolerated without significant unexpected toxic effects. The ORR was 13% for phase 2 patients and 19% overall. Median PFS was 8.1 (95% CI, 7.6-10.8) months. Median OS was 27.6 (95% CI, 18.7-not reached) months at the time of this analysis. Two of 3 patients with undifferentiated pleomorphic sarcoma and 2 of 4 patients with dedifferentiated liposarcoma had durable partial responses. Tumor-infiltrating lymphocytes were present in 21% of evaluable tumors and associated with inferior PFS (log-rank P = .03). No dose-limiting toxic effects were observed. CONCLUSIONS AND RELEVANCE: In this nonrandomized clinical trial, doxorubicin plus pembrolizumab was well tolerated. Although the primary end point for ORR was not reached, the PFS and OS observed compared favorably with prior published studies. Further studies are warranted, especially those focusing on undifferentiated pleomorphic sarcoma and dedifferentiated liposarcoma. TRIAL REGISTRATION: ClinicalTrials.gov Identifier: NCT02888665.
Overview
The claims and statistics of this paper haven’t been checked yet.
Run the check — free, no account needed. It reads the open-access text and checks the sources it cites.
Integrity signals
Registry
Cites
Statistics
Figures
Verification
Claims the paper makes
The claims and statistics of this paper haven’t been checked yet.
Run the check — free, no account needed. It reads the open-access text and checks the sources it cites.
Claims other papers make about this one
Each is checked against this paper’s own text: does it say what the citing paper says it does?
The cited source doesn’t support the claim as written.
In the citing paper
“This trial included three cases with conventional chondrosarcoma, with no dimensional responses observed.”
From Nivolumab and sunitinib in patients with advanced bone sarcomas: A multicenter, single‐arm, phase 2 trial (2025) · cites this paper as [55]
Checked by a reasoning model — may be wrong.
Experimental — accuracy not yet measured
Self-check
Percentages, sums and reported differences re-computed from the paper’s own numbers.
The self-check needs the paper’s full text.
Citations
Cites
New response evaluation criteria in solid tumours: revised RECIST guideline (version 1.1)
Eisenhauer, E. A., Therasse, P., Bogaerts, J., Schwartz, L. H., Sargent, D., Ford, R., Dancey, J., Arbuck, S., Gwyther, S., Mooney, M., et al. (2009) · European Journal of Cancer · doi:10.1016/j.ejca.2008.10.026 · Cited by 29,534
Tawbi, H. A., Burgess, M., Bolejack, V., Van Tine, B. A., Schuetze, S. M., Hu, J., D'Angelo, S., Attia, S., Riedel, R. F., Priebat, D. A., et al. (2017) · The Lancet Oncology · doi:10.1016/s1470-2045(17)30624-1 · Cited by 1,452
Judson, I. R., Verweij, J., Gelderblom, H. A. J., Hartmann, J. T., Schöffski, P., Blay, J., Kerst, J. M., Šufliarský, J., Whelan, J. S., Hohenberger, P., et al. (2014) · The Lancet Oncology · doi:10.1016/s1470-2045(14)70063-4 · Cited by 1,185
Tap, W. D., Jones, R. L., Tine, B. A. V., Chmielowski, B., ELIAS, A. D., Adkins, D., Agulnik, M., Cooney, M. M., Livingston, M. B., Pennock, G. K., et al. (2016) · The Lancet · doi:10.1016/s0140-6736(16)30587-6 · Cited by 584
Self-citationSeddon, B. M., Strauss, S. J., Whelan, J. S., Leahy, M. G., Woll, P. J., Cowie, F. J., Rothermundt, C. A., Wood, Z., Benson, C., Ali, N., et al. (2017) · The Lancet Oncology · doi:10.1016/s1470-2045(17)30622-8 · Cited by 529
Use of PD-1 Targeting, Macrophage Infiltration, and IDO Pathway Activation in Sarcomas
Toulmonde, M., Penel, N., Adam, J., Chevreau, C., Blay, J., Cesne, A. L., Bompas, E., Piperno-Neumann, S., Cousin, S., Grellety, T., et al. (2017) · JAMA Oncology · doi:10.1001/jamaoncol.2017.1617 · Cited by 420
Wilky, B. A., Trucco, M. M., Subhawong, T. K., Florou, V., Park, W., Kwon, D., Wieder, E., Kolonias, D. S., Rosenberg, A. E., Kerr, D. A., et al. (2019) · The Lancet Oncology · doi:10.1016/s1470-2045(19)30153-6 · Cited by 404
Tap, W. D., Wagner, A. J., Schöffski, P., Martín‐Broto, J., Krarup‐Hansen, A., Ganjoo, K. N., Yen, C., Razak, A. R. A., Spira, A. I., Kawai, A., et al. (2020) · JAMA · doi:10.1001/jama.2020.1707 · Cited by 310
Self-citationD’Angelo, S. P., Shoushtari, A. N., Agaram, N. P., Kuk, D., Qin, L., Carvajal, R. D., Dickson, M. A., Gounder, M. M., Keohan, M. L., Schwartz, G. K., et al. (2014) · Human Pathology · doi:10.1016/j.humpath.2014.11.001 · Cited by 305
Tap, W. D., Pápai, Z., Tine, B. A. V., Attia, S., Ganjoo, K. N., Jones, R. L., Schuetze, S. M., Reed, D. R., Chawla, S. P., Riedel, R. F., et al. (2017) · The Lancet Oncology · doi:10.1016/s1470-2045(17)30381-9 · Cited by 304
Self-citation
Cited by
Sorted by citations
Panez-Toro, I., Muñoz-García, J., Vargas-Franco, J. W., Renodon‐Cornière, A., Heymann, M., Lézot, F., & Heymann, D. (2023) · Current Osteoporosis Reports · doi:10.1007/s11914-023-00803-9 · Cited by 133
Arrieta, V. A., Gould, A., Kim, K.-S., Habashy, K. J., Dmello, C., Vazquez-Cervantes, G. I., Palacín-Aliana, I., McManus, G., Amidei, C., Gomez, C., et al. (2024) · Nature Communications · doi:10.1038/s41467-024-48326-w · Cited by 116
Saerens, M., Brusselaers, N., Rottey, S., Decruyenaere, A., Creytens, D., & Lapeire, L. (2021) · European Journal of Cancer · doi:10.1016/j.ejca.2021.04.034 · Cited by 118
Dugage, M. R., Nassif, E. F., Italiano, A., & Bahleda, R. (2021) · Frontiers in Immunology · doi:10.3389/fimmu.2021.775761 · Cited by 100
Livingston, M. B., Jagosky, M. H., Robinson, M. M., Ahrens, W. A., Benbow, J. H., Farhangfar, C. J., Foureau, D., Maxwell, D. M., Baldrige, E. A., Begic, X., et al. (2021) · Clinical Cancer Research · doi:10.1158/1078-0432.ccr-21-2001 · Cited by 75
Metadata
- Authors
- Pollack, S. M., Redman, M. W., Baker, K. K., Wagner, M. J., Schroeder, B. A., Loggers, E. T., Trieselmann, K., Copeland, V. C., Zhang, S., Black, G., McDonnell, S., Gregory, J., Johnson, R., Moore, R., Jones, R. L., & Cranmer, L. D.
- Affiliations
- University of Washington (US)
- Fred Hutch Cancer Center (US)
- Virginia Mason Medical Center (US)
- Institute of Cancer Research (GB)
- Corresponding author
- Pollack, Seth M.
- ORCID
- Venue
- JAMA Oncology
- Publisher
- American Medical Association (AMA)
- Published
- 2020-11-01
- Volume
- 6
- Issue
- 11
- Pages
- 1778
- ISSN
- 2374-2437 (ISSN-L)
- PMC
- PMC7489365
- OpenAlex
- W3083776688
- Cited by
- 142
- References
- 17
- Citations by year
- 2026: 16 · 2025: 31 · 2024: 29 · 2023: 25 · 2022: 25 · 2021: 15 · 2020: 1
- FWCI
- 9.72
- Type
- journal article
- Language
- en
- Open access
- hybrid
- doi.org
- Licence
- cc-by-nc-nd
- Locations
- JAMA Oncology (publishedVersion, cc-by-nc-nd)
- PubMed Central (publishedVersion, cc-by-nc-nd)
- PubMed (publishedVersion)
- Topics
- Health Sciences › Medicine › Oncology › Sarcoma Diagnosis and Treatment
- Health Sciences › Medicine › Oncology › Cancer Immunotherapy and Biomarkers
- Health Sciences › Medicine › Pathology and Forensic Medicine › Lymphoma Diagnosis and Treatment
- Keywords
- doxorubicin, pembrolizumab, soft tissue sarcoma, immune checkpoint inhibitors, combination chemotherapy, objective response rate, progression-free survival, overall survival, tumor-infiltrating lymphocytes, leiomyosarcoma, malignant fibrous histiocytoma, dedifferentiated liposarcoma, drug safety and tolerability
- MeSH terms
- Adult, Aged, Aged, 80 and over, Doxorubicin, Female, Humans, Male, Middle Aged, Sarcoma, Anthracyclines, Antibodies, Monoclonal, Humanized
About these checks
Registry, retraction, Cites and statistics results are computed, not judged, with one exception: a printed reference that no index lists is read once by a model before it counts as a citation error. Claims are extracted by a model and kept only when their quote appears verbatim in the text; each cited source is then checked, with a model’s help, for whether it says what the claim relies on. Those verdicts can be wrong — read the claim’s quote and the cited source before relying on one.
Statistics and arithmetic are recomputed, not judged.
Confidence bands are shown only for fields calibrated on our annotated test set. None is calibrated yet, so no band is shown.
What counts as a claim ›How we measure confidence ›How we check this ›
Are you an author, or do you see a problem with this page? Request a review
