

The DOI matches its Crossref record; 17 of the 17 references it cites were found in a registry or an index; 2 of the 21 sources its claims cite were checked for support.
The Cochrane risk of bias assessment tool 2 (RoB 2) versus the original RoB: A perspective on the pros and cons
Open accessAbstract
Background and Aims: Critical appraisal or risk of bias assessment is a fundamental part of systematic reviews that clarifies the degree to which included research articles are qualified and reliable. Version 2 of the Cochrane tool for assessing the risk of bias in randomized trials (RoB 2), the updated version of the first tool, was released in 2019. Here, we have compared these two versions of Cochrane risk of bias assessment tools and highlighted the pros and cons of RoB 2. Methods: Statistical analysis and methodology is not applicable to this article as no new data were created or analyzed in this study. Results: The overall approach in RoB 2 is that by answering some signaling questions after the specification of results, effects of interest, and sources of information, an overall judgment for the quality of each study is reached. Accordingly, in the original version of the Cochrane RoB tool, the judgment can be in three different conclusions, including low, unclear, and high risk of bias. The most prominent difference in bias domains is the removal of “other bias” domain being replaced by “overall bias” judgment. Also, the most common presentation types of Cochrane risk of bias assessments are the “summary” and “graph” which are generated by Review Manager, web‐based applications, or packages in R software. Conclusion: The RoB 2 tool, compared to the original RoB, has improved and is the recommended version by the Cochrane Collaboration for quality assessment of randomized controlled trials. It is recommended to consider funding source, duration of follow‐up, declaration of data availability, the status of baseline characteristics between groups, and sample size calculation methods in further revisions of the Cochrane risk of bias assessment tools.
Overview
AI snapshot
Written from the paper’s full text.
TL;DR
This perspective article compares the Cochrane risk of bias tool version 2 (RoB 2, released 2019) with the original RoB 1 for randomized trials, arguing RoB 2 is improved and Cochrane-recommended but more complex and time-consuming. The authors recommend that future revisions consider funding source, follow-up duration, data availability, baseline characteristics, and sample size calculation methods.
Key findings
- RoB 2 assesses five bias domains (randomization process, deviations from intended interventions, missing outcome data, measurement of outcomes, selection of the reported result) plus an "overall bias" judgment, whereas RoB 1 had six domains including "other bias"; the removal of "other bias" is described as the most prominent domain difference and as improving clarity.
- RoB 2 uses structured signaling questions answered at five levels (yes, probably yes, no, probably no, no information) leading to judgments of low risk, some concerns, or high risk, replacing RoB 1's low/unclear/high judgments; RoB 2 focuses on results rather than outcomes.
- RoB 2 is more resource-intensive: a systematic review of 113 studies reported an average of 358 min per article, versus 10–60 min per article for the original RoB tool; two studies found no significant inter-rater reliability (IRR: −0.15) and slightly higher IRR (IRR: 0.16) for overall judgment, while use of RoB 2 was significantly associated with improved methodological quality of systematic reviews (p = 0.007).
- Drawing on Babic et al.'s survey of 768 Cochrane reviews including 11,369 RCTs, 87% of reviews reported the "other bias" domain with 5762 explanations categorized into 31 groups; the five most frequent categories were baseline characteristics (21.4%), funding (15.6%), sample size (8.1%), reporting (7.6%), and conflicts of interest (5.8%). A Cochrane review of 75 articles found industry-funded studies more often had favorable efficacy results (RR: 1.27; 95% CI: 1.17–1.37), suggesting an "industry bias" not assessed by RoB 2.
Methods
- Perspective article; the authors state that statistical analysis and methodology are not applicable because no new data were created or analyzed.
- The comparison focuses on RoB 2 for parallel study design versus RoB 1, drawing on previously published studies and the Cochrane Handbook to support the discussion.
- No primary data were collected; results from prior studies are cited as supporting evidence, and suggestions for future tools are based on previous findings and the authors' opinions.
Limitations
- Stated by the authors: it is a perspective article that only critiques the pros and cons of RoB 2 versus RoB 1 and offers factors for future iterations; it did not collect or report primary original data; it assessed only Cochrane RoB 2 with a focus on the parallel study design version and did not evaluate other quality assessment tools for clinical trials or observational studies; the suggestions are based on previous findings and authors' opinions, and further research, pilot studies, and expert consensus may be needed to evaluate their implementation.
- Evident from the text: RoB 2 lacks supplements for some trial types (e.g., trials without a control arm, factorial-design RCTs), and some domains remain subjective, with signaling-question answers (e.g., on deviations from intended intervention) often being "no information" or "probably no" due to unavailable protocols, potentially leading to discrepant judgments.
Model-written summary. Check it against the paper before relying on it.
Integrity signals
Registry
Cites
Statistics
Figures
Verification
Claims the paper makes
16 Not checked yet · 14 Own interpretation · 2 Supported · 1 Sources not found · 1 No basis given
Every source the paper cites for this claim was checked and supports it.
In the paper
“While this time for the original RoB tool was between 10 and 60 min per article.”
§ The Cochrane risk of bias assessment tool 2 (RoB 2) versus the original RoB: A perspective on the pros and cons > LIMITATIONS AND IMPROVEMENTS OF ROB 2
What the sources say
- Supportedcites [9] Savović J, Weeks L, Sterne JAC, et al. Evaluation of the Cochrane collaboration's tool for assessing the risk of bias in randomized trials: focus groups, online survey, proposed recommendations and their implementation. Syst Rev. 2014; 3(1): 37. 24731537 PMC4022341 source
The Abstract (Results) reports that respondents took an average of between 10 and 60 minutes per study to complete RoB assessments. The Results (Survey, Table 3) likewise show that most respondents reported times in that interval, though some reported shorter or longer times. (LLM, conf=0.92)
plain- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
- Supported
None of the sources cited for this claim have been checked yet.
In the paper
“One of the limitations of the RoB2 is that it takes more time to complete each study.”
§ The Cochrane risk of bias assessment tool 2 (RoB 2) versus the original RoB: A perspective on the pros and cons > LIMITATIONS AND IMPROVEMENTS OF ROB 2
What the sources say
- Not checked yetcites [8] Crocker TF, Lam N, Jordão M, et al. Risk‐of‐bias assessment using RoB2 was useful but challenging and resource‐intensive: observations from a systematic review. J Clin Epidemiol. 2023; 161: 39‐ 45. 37364620 source
Checked before — its earlier verdict is held back until a new check runs.
- Not checked yetcites [9] Savović J, Weeks L, Sterne JAC, et al. Evaluation of the Cochrane collaboration's tool for assessing the risk of bias in randomized trials: focus groups, online survey, proposed recommendations and their implementation. Syst Rev. 2014; 3(1): 37. 24731537 PMC4022341 source
plaindirect- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
- Not checked yet
None of the sources cited for this claim have been checked yet.
In the paper
“Nevertheless, there was a significant association between the use of RoB 2 and the improved methodological quality of the systematic reviews (p = 0.007).”
§ The Cochrane risk of bias assessment tool 2 (RoB 2) versus the original RoB: A perspective on the pros and cons > LIMITATIONS AND IMPROVEMENTS OF ROB 2
What the sources say
- Not checked yetcites [12] Minozzi S, Gonzalez‐Lorenzo M, Cinquini M, et al. Adherence of systematic reviews to Cochrane RoB2 guidance was frequently poor: a meta epidemiological study. J Clin Epidemiol. 2022; 152: 47‐ 55. 36156301 source
Checked before — its earlier verdict is held back until a new check runs.
plaincorrelational- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: unclear — It is unclear whether the paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
- Not checked yet
A conclusion the paper draws from its own results — it cites no other source for it, so there is none to check. The quote shows it is in the paper.
In the paper
“The RoB 2 improved the quality assessment of randomized clinical trials in several ways.”
§ The Cochrane risk of bias assessment tool 2 (RoB 2) versus the original RoB: A perspective on the pros and cons > LIMITATIONS AND IMPROVEMENTS OF ROB 2
plaindirect- Asserted: passes — The authors put it forward as true.
- Checkable: unclear — It is unclear whether it could be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
- Rests on an assumption: The RoB 2 includes supplements for parallel, cluster-randomized, and cross-over designs of RCTs, whereas RoB 1 has one guidance and iteration.
A conclusion the paper draws from its own results — it cites no other source for it, so there is none to check. The quote shows it is in the paper.
In the paper
“The most prominent difference in bias domains is that the “other bias” domain is removed in RoB 2 and instead, an “overall bias” judgment has been added based on the status of the five bias domains.”
§ The Cochrane risk of bias assessment tool 2 (RoB 2) versus the original RoB: A perspective on the pros and cons > HOW ROB2 IS DIFFERENT FROM ROB1 > Included domains
plain- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
None of the sources cited for this claim have been checked yet.
In the paper
“A systematic review of 113 studies showed an average time of 358 min per article.”
§ The Cochrane risk of bias assessment tool 2 (RoB 2) versus the original RoB: A perspective on the pros and cons > LIMITATIONS AND IMPROVEMENTS OF ROB 2
What the sources say
- Not checked yetcites [8] Crocker TF, Lam N, Jordão M, et al. Risk‐of‐bias assessment using RoB2 was useful but challenging and resource‐intensive: observations from a systematic review. J Clin Epidemiol. 2023; 161: 39‐ 45. 37364620 source
Checked before — its earlier verdict is held back until a new check runs.
plain- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
- Not checked yet
A conclusion the paper draws from its own results — it cites no other source for it, so there is none to check. The quote shows it is in the paper.
In the paper
“Some of the items listed in this domain such as outcome measures, attrition, blinding, selection and randomization, reporting, and publication biases were assessed in other domains of this tool as well, or they were evaluated by other methods.”
§ The Cochrane risk of bias assessment tool 2 (RoB 2) versus the original RoB: A perspective on the pros and cons > HOW ROB2 IS DIFFERENT FROM ROB1 > Included domains
plain- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
In the paper
“It showed that the results are in favor of better efficacy findings in industry‐funded studies than other sources of funding (risk ratio [RR]: 1.27; 95% confidence interval [CI]: 1.17–1.37).”
§ The Cochrane risk of bias assessment tool 2 (RoB 2) versus the original RoB: A perspective on the pros and cons > DISCUSSION
What the sources say
- Not checked yetcites [16] Lundh A, Lexchin J, Mintzes B, Schroll JB, Bero L. Industry sponsorship and research outcome. Cochrane Database Syst Rev. 2017;(2). PMC8132492 28207928 source
plaincorrelational- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
None of the sources cited for this claim have been checked yet.
In the paper
“The study by Babic et al. on 768 Cochrane reviews showed that baseline characteristics of participants (21.4%), funding (15.6%), sample size (8.1%), reporting (7.6%), and conflicts of interest (5.8%) are the five most frequent categories reported for “other bias” domain in systematic reviews.”
§ The Cochrane risk of bias assessment tool 2 (RoB 2) versus the original RoB: A perspective on the pros and cons > DISCUSSION
What the sources say
- Not checked yetcites [6] Babic A, Pijuk A, Brázdilová L, et al. The judgement of biases included in the category “other bias” in Cochrane systematic reviews of interventions: a systematic survey. BMC Med Res Methodol. 2019; 19(1): 77. 30971219 PMC6458756 source
Checked before — its earlier verdict is held back until a new check runs.
plain- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
- Not checked yet
In the paper
“In this regard, a Cochrane review that included 75 articles compared favorable outcomes between industry‐funded studies and studies using other funding sources.”
§ The Cochrane risk of bias assessment tool 2 (RoB 2) versus the original RoB: A perspective on the pros and cons > DISCUSSION
What the sources say
- Not checked yetcites [16] Lundh A, Lexchin J, Mintzes B, Schroll JB, Bero L. Industry sponsorship and research outcome. Cochrane Database Syst Rev. 2017;(2). PMC8132492 28207928 source
plaincorrelational- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
- It may state two separate claims as one. 11
- Probably not a substantial claim. 15
Every source the paper cites for this claim was checked and supports it.
In the paper
“Protocol registration and deviation from registered protocol were reported in 0.3% and 2.5% of the “other bias” domain in the RoB1, respectively.”
§ The Cochrane risk of bias assessment tool 2 (RoB 2) versus the original RoB: A perspective on the pros and cons > DISCUSSION
What the sources say
- Supportedcites [6] Babic A, Pijuk A, Brázdilová L, et al. The judgement of biases included in the category “other bias” in Cochrane systematic reviews of interventions: a systematic survey. BMC Med Res Methodol. 2019; 19(1): 77. 30971219 PMC6458756 source
Table 1 in Results > Primary analysis lists protocol registration as 16 (0.3%) and deviations from the protocol as 123 (2.5%) among 4,991 explanations categorized as other bias. The percentages match the claim; they refer to explanations within that domain, not percentages of reviews. (LLM, conf=0.93)
plain- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: unclear — It is unclear whether the paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
- Supported
The paper states this without a source or data behind it here, so there is nothing to check it against. The quote shows it is in the paper.
In the paper
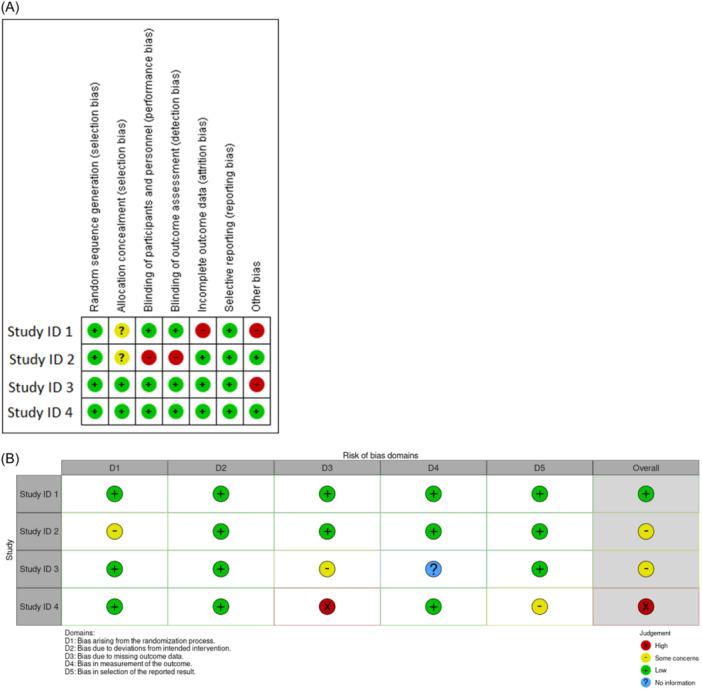
“There were no remarkable changes in presenting the results between RoB 2 (Figure 1A) and the original version of the RoB assessment tool (Figure 1B).”
§ The Cochrane risk of bias assessment tool 2 (RoB 2) versus the original RoB: A perspective on the pros and cons > HOW ROB2 IS DIFFERENT FROM ROB1 > Presentation of results
plainn = 4- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: fails — The paper’s conclusions may not depend on it.
- Based: passes — The paper gives a reason why it holds.
Probably not a substantial claim. The paper’s conclusions may not depend on it.
- Rests on an assumption: The most common presentation types of Cochrane risk of bias assessments are the 'summary' and 'graph' generated by Review Manager, web-based applications, or R packages.
In the paper
“Also, the RoB 2 is focused on the results instead of outcomes.”
§ The Cochrane risk of bias assessment tool 2 (RoB 2) versus the original RoB: A perspective on the pros and cons > LIMITATIONS AND IMPROVEMENTS OF ROB 2
What the sources say
- Not checked yetcites [5] Ella F, Theresa HM, Isabelle B, et al. Using risk of bias 2 to assess results from randomised controlled trials: guidance from Cochrane. BMJ Evid Based Med. 2023; 28(4): 260. 36693715
plain- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: fails — The paper’s conclusions may not depend on it.
- Based: passes — The paper gives a reason why it holds.
Probably not a substantial claim. The paper’s conclusions may not depend on it.
A conclusion the paper draws from its own results — it cites no other source for it, so there is none to check. The quote shows it is in the paper.
In the paper
“Meanwhile, omitting the “other bias” domain has improved the clarity of RoB 2.”
§ The Cochrane risk of bias assessment tool 2 (RoB 2) versus the original RoB: A perspective on the pros and cons > CONCLUSIONS
plaindirect- Asserted: passes — The authors put it forward as true.
- Checkable: fails — It may be too vague to check against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: fails — The paper may give no reason why it holds.
Probably not a substantial claim. It may be too vague to check against evidence. The paper may give no reason why it holds.
In the paper
“However, in the original version of the Cochrane RoB tool, the judgment can be in three different groups, including low, unclear, and high risk based on provided support for judgment.”
§ The Cochrane risk of bias assessment tool 2 (RoB 2) versus the original RoB: A perspective on the pros and cons > HOW ROB2 IS DIFFERENT FROM ROB1 > Overall risk of bias judgment
What the sources say
- Not checked yetcites [3] Higgins JPT, Altman DG, Gøtzsche PC, et al. The Cochrane collaboration's tool for assessing risk of bias in randomised trials. BMJ. 2011; 343: d5928. 22008217 PMC3196245
plain- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
Probably not a substantial claim.
A conclusion the paper draws from its own results — it cites no other source for it, so there is none to check. The quote shows it is in the paper.
In the paper
“The judgment process and the conclusion of each study's risk of bias have been changed, while the presentation of the assessment is almost similar.”
§ The Cochrane risk of bias assessment tool 2 (RoB 2) versus the original RoB: A perspective on the pros and cons > CONCLUSIONS
plain- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: fails — The paper may give no reason why it holds.
Probably not a substantial claim. The paper may give no reason why it holds. It may state two separate claims as one.
- Rests on an assumption: Both versions of the Cochrane RoB assessment tools use an option for RoB that cannot be categorized into low or high RoB; the original uses 'unclear' and RoB 2 uses 'some concerns'.
In the paper
“In the RoB 2 tool, there are five bias domains, including (1) bias due to the randomization process, (2) deviation from intended intervention, (3) missing outcome data, (4) measurement of outcomes, (5) selection of the reported result, and “overall risk of bias” judgment.”
§ The Cochrane risk of bias assessment tool 2 (RoB 2) versus the original RoB: A perspective on the pros and cons > HOW ROB2 IS DIFFERENT FROM ROB1 > Included domains
What the sources say
- Not checked yetcites [4] Sterne JAC, Savović J, Page MJ, et al. RoB 2: a revised tool for assessing risk of bias in randomised trials. BMJ. 2019; 366: l4898. 31462531
plain- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
Probably not a substantial claim.
A conclusion the paper draws from its own results — it cites no other source for it, so there is none to check. The quote shows it is in the paper.
In the paper
“The presence of signaling questions in RoB2, in five levels, including yes, probably yes, no, probably no, and no information, which leads to high risk, low risk, and some concerns for each domain can increase the precision of this revised version compared to the original version of RoB tool.”
§ The Cochrane risk of bias assessment tool 2 (RoB 2) versus the original RoB: A perspective on the pros and cons > HOW ROB2 IS DIFFERENT FROM ROB1 > Overall risk of bias judgment
plaindirect- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: fails — The paper may give no reason why it holds.
Probably not a substantial claim. The paper may give no reason why it holds.
In the paper
“The RoB 2 tool, compared to the original RoB, has been improved and is the recommended version by Cochrane for the quality assessment of RCTs.”
§ The Cochrane risk of bias assessment tool 2 (RoB 2) versus the original RoB: A perspective on the pros and cons > CONCLUSIONS
What the sources say
- Not matchedcites [18] Higgins JPT, Savović J, Page MJ, Elbers RG, Sterne JAC. Chapter 8: Assessing risk of bias in a randomized trial. In: Higgins JPT, Thomas J, Chandler J, Cumpston M, Li T, Page MJ, Welch VA, eds. Cochrane Handbook for Systematic Reviews of Interventions Version 6.2 (Updated February 2021). Cochrane; 2021.
Couldn’t be matched to a paper in Crossref, so it can’t be checked.
plaindirect- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
- Rests on an assumption: The RoB 2 includes supplements for parallel, cluster-randomized, and cross-over designs of RCTs, whereas RoB 1 has one guidance and iteration.
- Not matched
A conclusion the paper draws from its own results — it cites no other source for it, so there is none to check. The quote shows it is in the paper.
In the paper
“Contrary to the original version of the Cochrane RoB tool which was based on the authors' judgments and used quotes from the papers to support the judgments, the RoB 2 used a more comprehensive and structured framework for quality assessment using the signaling questions.”
§ The Cochrane risk of bias assessment tool 2 (RoB 2) versus the original RoB: A perspective on the pros and cons > LIMITATIONS AND IMPROVEMENTS OF ROB 2
plain- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
Probably not a substantial claim. It may state two separate claims as one.
In the paper
“For example, the results of a comparison study between the two versions of the Cochrane RoB assessment tools showed that the responses to “Were there deviations from the intended intervention that arose because of the trial context?” question are usually “no information” or “probably no” due to no available protocol which leads to overall judgments of “some concerns” or low RoB, respectively and”
§ The Cochrane risk of bias assessment tool 2 (RoB 2) versus the original RoB: A perspective on the pros and cons > LIMITATIONS AND IMPROVEMENTS OF ROB 2
What the sources say
- Not checked yetcites [13] Richter B, Hemmingsen B. Comparison of the Cochrane Risk of Bias Tool 1 (RoB 1) with the 517 Updated Cochrane Risk of Bias Tool 2 (RoB 2). 2021. https://communitycochraneorg/sites/default/files/uploads/inline-files/RoB1_2_project_220529_BR%20KK%20formattedpdf
plaindirect- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
A conclusion the paper draws from its own results — it cites no other source for it, so there is none to check. The quote shows it is in the paper.
In the paper
“In spite of the improvement in the assessment methods in the RoB2, there are still domains that are subjective and there might be doubt and disagreement about the answer to the signaling questions.”
§ The Cochrane risk of bias assessment tool 2 (RoB 2) versus the original RoB: A perspective on the pros and cons > LIMITATIONS AND IMPROVEMENTS OF ROB 2
hedged- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
None of the sources cited for this claim have been checked yet.
In the paper
“The study conducted by Babic et al. on 768 Cochrane reviews which included 11,369 randomized controlled trials (RCTs) showed that 87% of reviews reported “other bias” domain and there were 5,‐762 types of explanations which were categorized into 31 groups.”
§ The Cochrane risk of bias assessment tool 2 (RoB 2) versus the original RoB: A perspective on the pros and cons > HOW ROB2 IS DIFFERENT FROM ROB1 > Included domains
What the sources say
- Not checked yetcites [6] Babic A, Pijuk A, Brázdilová L, et al. The judgement of biases included in the category “other bias” in Cochrane systematic reviews of interventions: a systematic survey. BMC Med Res Methodol. 2019; 19(1): 77. 30971219 PMC6458756 source
Checked before — its earlier verdict is held back until a new check runs.
plain- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
- Not checked yet
None of the sources cited for this claim have been checked yet.
In the paper
“Two different studies assessing the RoB 2 showed no significant inter‐rater reliability (IRR: −0.15) and slightly higher IRR (IRR: 0.16) for overall judgment.”
§ The Cochrane risk of bias assessment tool 2 (RoB 2) versus the original RoB: A perspective on the pros and cons > LIMITATIONS AND IMPROVEMENTS OF ROB 2
What the sources say
- Not checked — no full text of the sourcecites [10] Minozzi S, Dwan K, Borrelli F, Filippini G. Reliability of the revised Cochrane risk‐of‐bias tool for randomised trials (RoB2) improved with the use of implementation instruction. J Clin Epidemiol. 2022; 141: 99‐ 105. 34537386 source
- Not matchedcites [11] Minozzi S, Cinquini M, Gianola S, Gonzalez‐Lorenzo M, Banzi R. The revised Cochrane risk of bias tool for randomized trials (RoB 2) showed low interrater reliability and challenges in its application. J Clin Epidemiol. 2020; 126: 37‐ 44. 32562833
Couldn’t be matched to a paper in Crossref, so it can’t be checked.
plain- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
A conclusion the paper draws from its own results — it cites no other source for it, so there is none to check. The quote shows it is in the paper.
In the paper
“Overall, the RoB 2 is comprehensive but complex and difficult to use even for experts.”
§ The Cochrane risk of bias assessment tool 2 (RoB 2) versus the original RoB: A perspective on the pros and cons > LIMITATIONS AND IMPROVEMENTS OF ROB 2
plain- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
In the paper
“The overall approach in RoB2 is that by answering some signaling questions after the specification of results, effects of interest, and sources of information, an overall judgment for the quality of that study is reached.”
§ The Cochrane risk of bias assessment tool 2 (RoB 2) versus the original RoB: A perspective on the pros and cons > HOW ROB2 IS DIFFERENT FROM ROB1 > Overall risk of bias judgment
What the sources say
- Not checked yetcites [4] Sterne JAC, Savović J, Page MJ, et al. RoB 2: a revised tool for assessing risk of bias in randomised trials. BMJ. 2019; 366: l4898. 31462531
plaindirect- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
Probably not a substantial claim.
In the paper
“In the original RoB tool, six bias domains (and source[s] of bias) are assessed, including selection bias, performance bias, detection bias, attrition bias, reporting bias, and “other bias.””
§ The Cochrane risk of bias assessment tool 2 (RoB 2) versus the original RoB: A perspective on the pros and cons > HOW ROB2 IS DIFFERENT FROM ROB1 > Included domains
What the sources say
- Not checked yetcites [3] Higgins JPT, Altman DG, Gøtzsche PC, et al. The Cochrane collaboration's tool for assessing risk of bias in randomised trials. BMJ. 2011; 343: d5928. 22008217 PMC3196245
plain- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
Probably not a substantial claim.
A conclusion the paper draws from its own results — it cites no other source for it, so there is none to check. The quote shows it is in the paper.
In the paper
“On the other hand, one of the main limitations of the RoB 2 is that it is complex and needs trained individuals to use this tool.”
§ The Cochrane risk of bias assessment tool 2 (RoB 2) versus the original RoB: A perspective on the pros and cons > LIMITATIONS AND IMPROVEMENTS OF ROB 2
plaindirect- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
A conclusion the paper draws from its own results — it cites no other source for it, so there is none to check. The quote shows it is in the paper.
In the paper
“Nevertheless, still some improvements need to be implemented such as considering some valuable information addressing the quality of studies.”
§ The Cochrane risk of bias assessment tool 2 (RoB 2) versus the original RoB: A perspective on the pros and cons > CONCLUSIONS
plain- Asserted: passes — The authors put it forward as true.
- Checkable: fails — It may be too vague to check against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: fails — The paper may give no reason why it holds.
Probably not a substantial claim. It may be too vague to check against evidence. The paper may give no reason why it holds.
A conclusion the paper draws from its own results — it cites no other source for it, so there is none to check. The quote shows it is in the paper.
In the paper
“However, there is still a lack of some supplements for other types of clinical trials like clinical trials without a control arm or RCTs with factorial design.”
§ The Cochrane risk of bias assessment tool 2 (RoB 2) versus the original RoB: A perspective on the pros and cons > LIMITATIONS AND IMPROVEMENTS OF ROB 2
plain- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: fails — The paper’s conclusions may not depend on it.
- Based: fails — The paper may give no reason why it holds.
Probably not a substantial claim. The paper’s conclusions may not depend on it. The paper may give no reason why it holds.
A conclusion the paper draws from its own results — it cites no other source for it, so there is none to check. The quote shows it is in the paper.
In the paper
“Nevertheless, the RoB 2 improved the criteria for judgment on how to reach an overall judgment about the RoB using the signaling questions and algorithms.”
§ The Cochrane risk of bias assessment tool 2 (RoB 2) versus the original RoB: A perspective on the pros and cons > LIMITATIONS AND IMPROVEMENTS OF ROB 2
plaindirect- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
Probably not a substantial claim.
In the paper
“In this regard, Weibel and colleagues generated a research integrity assessment tool to identify problematic RCTs which evaluates six criteria, including ethics approval status, study retraction, prospective trial registration, author group, plausibility of methods, and study results.”
§ The Cochrane risk of bias assessment tool 2 (RoB 2) versus the original RoB: A perspective on the pros and cons > DISCUSSION
What the sources say
- Not checked yetcites [17] Weibel S, Popp M, Reis S, Skoetz N, Garner P, Sydenham E. Identifying and managing problematic trials: a research integrity assessment tool for randomized controlled trials in evidence synthesis. Res Synt Methods. 2023; 14(3): 357‐ 369. PMC10551123 36054583 source
plain- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: fails — The paper’s conclusions may not depend on it.
- Based: passes — The paper gives a reason why it holds.
Probably not a substantial claim. The paper’s conclusions may not depend on it.
In the paper
“The AMSTAR 2, which is a tool for quality assessment of systematic reviews, includes two domains related to the source of funding (Domain 10: “Did the review authors report on the sources of funding for the studies included in the review?” and Domain 16: “Did the review authors report any potential sources of conflict of interest, including any funding they received for conducting the review?”).”
§ The Cochrane risk of bias assessment tool 2 (RoB 2) versus the original RoB: A perspective on the pros and cons > DISCUSSION
What the sources say
- Not checked yetcites [14] Shea BJ, Reeves BC, Wells G, et al. AMSTAR 2: a critical appraisal tool for systematic reviews that include randomised or non‐randomised studies of healthcare interventions, or both. BMJ. 2017; 358: j4008. 28935701 PMC5833365 source
plain- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: fails — The paper’s conclusions may not depend on it.
- Based: passes — The paper gives a reason why it holds.
Probably not a substantial claim. The paper’s conclusions may not depend on it.
A conclusion the paper draws from its own results — it cites no other source for it, so there is none to check. The quote shows it is in the paper.
In the paper
“As a result, there can be an “industry bias” that is not assessed in the RoB 2 which might be considered for designing future quality assessment tools.”
§ The Cochrane risk of bias assessment tool 2 (RoB 2) versus the original RoB: A perspective on the pros and cons > DISCUSSION
hedged- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
The paper relies on this without support.
The implications of the results for researchers and methodologists and how the changes can lead to high-quality systematic reviews were not mentioned in previous publications.
“However, the implications of the results for researchers and methodologists and how the changes can lead to the production of high‐quality systematic reviews were not mentioned.”
The paper relies on this without support.
Some domains that were omitted from the original version of RoB assessment were not analyzed in depth in previous publications.
“In addition, some domains that were omitted from the original version of RoB assessment were not analyzed in depth in the previous publications.”
The paper relies on this without support.
The RoB 2 includes supplements for parallel, cluster-randomized, and cross-over designs of RCTs, whereas RoB 1 has one guidance and iteration.
“Despite the RoB 1 that has one guidance and iteration, the RoB 2 includes other supplements for parallel, cluster‐randomized, and cross‐over designs of RCTs.”
The paper relies on this without support.
Both versions of the Cochrane RoB assessment tools use an option for RoB that cannot be categorized into low or high RoB; the original uses 'unclear' and RoB 2 uses 'some concerns'.
“Both versions of the Cochrane RoB assessment tools use another option for RoB that cannot be categorized into low or high RoB. In this regard, the original version uses “unclear” and the RoB 2 uses “some concerns.””
The paper relies on this without support.
The RoB 1 and RoB 2 include the 'reporting bias' domain and 'bias in the selection of the reported result,' respectively, to assess reporting bias.
“The RoB 1 and RoB 2 include the “reporting bias” domain and “bias in the selection of the reported result,” respectively, to assess this outcome.”
The paper relies on this without support.
The most common presentation types of Cochrane risk of bias assessments are the 'summary' and 'graph' generated by Review Manager, web-based applications, or R packages.
“The most common presentation types of Cochrane risk of bias assessments are the “summary” and “graph” which are generated by Review Manager (RevMan) (Copenhagen: The Nordic Cochrane Centre, The Cochrane Collaboration, 2014) or RevMan Web application.”
Self-check
Percentages, sums and reported differences re-computed from the paper’s own numbers.
Each contradiction between two passages listed here was confirmed by an independent check.
Rated minor: it would not touch a result — a value no result rests on, a p-value that stays on the same side of the significance level, or a conflict that is clerical, resolved elsewhere in the paper, or outside its own findings.
In the paper
§ The Cochrane risk of bias assessment tool 2 (RoB 2) versus the original RoB: A perspective on the pros and cons > HOW ROB2 IS DIFFERENT FROM ROB1 > Presentation of results
“There were no remarkable changes in presenting the results between RoB 2 (Figure 1A) and the original version of the RoB assessment tool (Figure 1B).”
§ The Cochrane risk of bias assessment tool 2 (RoB 2) versus the original RoB: A perspective on the pros and cons > HOW ROB2 IS DIFFERENT FROM ROB1 > Presentation of results
“Figure: Figure 1 Summary of risk of bias assessment for four samples included studies using Cochrane risk of bias assessments tool version 1 (A) and version 2 (RoB 2) (B).”
Citations
Cites
RoB 2: a revised tool for assessing risk of bias in randomised trials
Sterne, J. A. C., Savović, J., Page, M. J., Elbers, R. G., Blencowe, N. S., Boutron, I., Cates, C. J., Cheng, H.-Y., Corbett, M. S., Eldridge, S. M., et al. (2019) · BMJ · doi:10.1136/bmj.l4898 · Cited by 34,787
The Cochrane Collaboration's tool for assessing risk of bias in randomised trials
Higgins, J. P. T., Altman, D. G., Gotzsche, P. C., Juni, P., Moher, D., Oxman, A. D., Savovic, J., Schulz, K. F., Weeks, L., Sterne, J. A. C., et al. (2011) · BMJ · doi:10.1136/bmj.d5928 · Cited by 33,817
Dermyshi, E., Wang, Y., Yan, C., Hong, W., Qiu, G., Gong, X., & Zhang, T. (2017) · Neonatology · doi:10.1159/000454668 · Cited by 24,586
Cochrane Handbook for Systematic Reviews of Interventions
(2019) · doi:10.1002/9781119536604 · Cited by 14,828
Shea, B. J., Reeves, B. C., Wells, G., Thuku, M., Hamel, C., Moran, J., Moher, D., Tugwell, P., Welch, V., Kristjansson, E., et al. (2017) · BMJ · doi:10.1136/bmj.j4008 · Cited by 10,636
McGuinness, L. A., & Higgins, J. P. T. (2021) · Research Synthesis Methods · doi:10.1002/jrsm.1411 · Cited by 5,579
Industry sponsorship and research outcome
Lundh, A., Lexchin, J., Mintzes, B., Schroll, J. B., & Bero, L. (2017) · Cochrane Database of Systematic Reviews · doi:10.1002/14651858.mr000033.pub3 · Cited by 1,697
Ma, L.-L., Wang, Y.-Y., Yang, Z.-H., Huang, D., Weng, H., & Zeng, X.-T. (2020) · Military Medical Research · doi:10.1186/s40779-020-00238-8 · Cited by 1,648
Minozzi, S., Cinquini, M., Gianola, S., Gonzalez-Lorenzo, M., & Banzi, R. (2020) · Journal of Clinical Epidemiology · doi:10.1016/j.jclinepi.2020.06.015 · Cited by 471 · cited 1×
“10,11 Nevertheless, there was a significant association between the use of RoB 2 and the improved methodological quality of the systematic reviews ( p = 0.007).”
BackgroundInfluentialSavović, J., Weeks, L., Sterne, J. A., Turner, L., Altman, D. G., Moher, D., & Higgins, J. P. (2014) · Systematic Reviews · doi:10.1186/2046-4053-3-37 · Cited by 340
Research works printed but not linked: 1
- Higgins JPT, 2021, Cochrane Handbook for Systematic Reviews of Interventions Version 6.2 (Updated February 2021)
Cited by
Sorted by citations
Items 101–200 of 274
Zhou, Q., An, H., Gao, J., Zhang, H., Wang, S., Xu, S., & Guo, F. (2026) · Dementia and Geriatric Cognitive Disorders · doi:10.1159/000550308 · Cited by 1
Pratiwi, I. N., Widyawati, I. Y., Dewi, L. C., & chan, C. M. (2026) · International Journal of Africa Nursing Sciences · doi:10.1016/j.ijans.2026.101007 · Cited by 1
Song, W., Jiayi, C., Huang, W., Hu, B., Zhu, K., Zhou, C., & Liu, Y. (2026) · World Journal of Surgical Oncology · doi:10.1186/s12957-026-04219-4 · Cited by 1
Xiang, Y., Liu, J., Zhu, Z., Hu, X., & Li, W. (2026) · Frontiers in Medicine · doi:10.3389/fmed.2026.1740693 · Cited by 1
Ioannidis, D. C., Kapasouri, E. M., Vassiliou, V. S., & Ntatsaki, E. (2026) · Journal of Personalized Medicine · doi:10.3390/jpm16020113 · Cited by 1
Xing, Z. (2026) · European Archives of Psychiatry and Clinical Neuroscience · doi:10.1007/s00406-026-02205-1 · Cited by 1
Vajje, J., Reyaz, N., Gillani, I., Ullah, M., Chaudhari, S. S., Jabeen, S., Wei, C. R., & Amin, A. (2026) · Cureus · doi:10.7759/cureus.105307 · Cited by 1
Vidor, P. R., Casiraghi, Y., de Souza, A. M., & Schmidt, M. I. (2026) · Scientific Reports · doi:10.1038/s41598-026-44303-z · Cited by 1
Alzayed, A. (2026) · Frontiers in Medicine · doi:10.3389/fmed.2026.1722577 · Cited by 1
Jin, Y., Liu, H., Gan, H., He, B., Wang, W., Gan, X., Hong, L., Ramteke, H. D., Luo, L., & Huang, Z. (2026) · Frontiers in Cardiovascular Medicine · doi:10.3389/fcvm.2026.1762634 · Cited by 1
Yadav, A., Maan, A., Gadhe, P., Banga, A., & Heist, E. K. (2026) · Heart Rhythm O2 · doi:10.1016/j.hroo.2026.03.015 · Cited by 1
Li, T., Liu, H., & Zeng, J. (2026) · BMC Endocrine Disorders · doi:10.1186/s12902-026-02238-6 · Cited by 1
Lyons, G., Nogueira, R., Viana, S. W., Andrade, M. F., Neves, V., Galhego, R. F., Pascotini, N. P., & Lima, D. L. (2026) · Hernia · doi:10.1007/s10029-026-03660-4 · Cited by 1
Lian, J., Wang, Y., Feng, G., & Miao, D. (2026) · Annals of General Psychiatry · doi:10.1186/s12991-026-00661-6 · Cited by 1
Almuqad, F. A., Alsaedi, G. T., Alahmadi, T. A., Alalawi, S. I., Mulla, R. M., Almohammadi, R. M., & Abulfaraj, M. M. (2026) · JMIR Pediatrics and Parenting · doi:10.2196/92880 · Cited by 1
Abureesh, O., Qaqish, F., Abu-Shaban, M., Lahoud, C., Habib, T., Sleiman, J., Moussa, E., Douaihy, Y. E., Chalhoub, J. M., & Andrawes, S. (2026) · Journal of Clinical Medicine · doi:10.3390/jcm15093406 · Cited by 1
Elzayyat, A., Al-Taie, M. S., Shoaib, M. I., Elkholi, M. H., Sofia, T., Serag, I., & Osman, N. A. (2026) · BMC Nutrition · doi:10.1186/s40795-026-01342-z · Cited by 1
Bharath Kumar, G., Jain, M., Meher, B. R., Padhy, B. M., Sakale, H. S., & Kumar, S. (2026) · European Journal of Clinical Pharmacology · doi:10.1007/s00228-026-04073-z · Cited by 1
Abureesh, O., Sohail, A., Yousef, Y., Abureesh, A., Abdulraheem, A., Tam, R., Yassine, A. A., Altork, N. A., Vankayala, U. S. A., Chalhoub, J. M., et al. (2026) · Frontiers in Medicine · doi:10.3389/fmed.2026.1852781 · Cited by 1
Yesodharan, D. K., Arulappan, J., Subramanyam, S., & Sridhar, O. T. S. (2026) · Psychiatry International · doi:10.3390/psychiatryint7030108 · Cited by 1
Zou, M., & Liu, C. (2026) · Diabetology & Metabolic Syndrome · doi:10.1186/s13098-026-02179-z · Cited by 1
Rastkar, M., Ghandchi, S., Ghajarzadeh, M., & Ghajarzadeh, M. (2026) · Neurodegenerative Disease Management · doi:10.1080/17582024.2026.2670683 · Cited by 1
Effectiveness of Group Exercise on the Quality of Life in Older Adults: A Systematic Review
Hernán-Santana, G., & Sobrido, M. (2026) · Journal of Geriatric Physical Therapy · doi:10.1519/jpt.0000000000000502 · Cited by 1
Awasthi, Y., Bangar, S. D., Boopalan, D., Karuppiah, M., & Ponnaiah, M. (2026) · Probiotics and Antimicrobial Proteins · doi:10.1007/s12602-026-11026-6 · Cited by 1
Kaur, K., Saini, R. S., Vyas, R., Alarcón‐Sánchez, M. A., Fraile, J. F., & Heboyan, A. (2026) · Journal of Cranio-Maxillofacial Surgery · doi:10.1016/j.jcms.2026.104628 · Cited by 1
Gogna, P., Wang, C., Underwood, D. L., Farid‐Kapadia, M., Dasari, M., Pyne, T., Sinha, N., Stirnadel-Farrant, H. A., & Valerio, S. J. (2026) · Cancers · doi:10.3390/cancers18121985 · Cited by 1
Conservative treatments for chronic non-specific low back pain: time course network meta-analysis
Belavý, D. L., Saueressig, T., Arora, N. K., Balasundaram, A. P., Chen, X., Diwan, A. D., Ford, J. J., Hahne, A. J., Kaczorowski, S., Miller, C. T., et al. (2026) · BMJ Medicine · doi:10.1136/bmjmed-2025-001908 · Cited by 1
Kamrul-Hasan, A. B. M., Chatterjee, S., Ashraf, H., Nagendra, L., Khalil, I., Hasan, M., Ahsan, A., & Dutta, D. (2026) · Diabetes Obesity and Metabolism · doi:10.1111/dom.71058 · Cited by 1
Marchesi, G., Rapelli, G., Semonella, M., Bruzzese, A., Molinaro, M., Andersson, G., Castelnuovo, G., & Pietrabissa, G. (2026) · Current Obesity Reports · doi:10.1007/s13679-026-00735-2 · Cited by 1
Perricone, E., Caldaci, A., Cacciaguerra, G., Nora, A. D., Parano, C., & Pavone, V. (2026) · Frontiers in Medicine · doi:10.3389/fmed.2026.1832930 · Cited by 1
Rodríguez, L., Lyons, J., Maloy, A., & O’Brien, A. (2026) · Campbell Systematic Reviews · doi:10.1177/18911803261469847 · Cited by 1
Systematic evidence review on radiosensitizers and the abscopal effects of radiotherapy
El‐Sehrawy, A. A. M. A., Oudah, D. M., Baig, M. R., Roopashree, R., Kaur, I., Nematov, O. N., Sapaev, I. B., Arora, V., Smerat, A., & Mohapatra, S. S. G. (2026) · International Journal of Radiation Biology · doi:10.1080/09553002.2026.2704757 · Cited by 1
Zhong, Y., Tan, X., Zhang, L., & Wu, C. (2026) · Frontiers in Pharmacology · doi:10.3389/fphar.2026.1916932 · Cited by 1
Niyomugabo, A. P., Ntakirutimana, L., & Alagbonsi, A. I. (2026) · Channels · doi:10.1080/19336950.2026.2731660 · Cited by 1
Romero, J. C. D., & Moposita, Á. P. C. (2024) · Sinergia Académica · doi:10.51736/8y7jqa68 · Cited by 1
Kumar, B. S., Syed, A., Ekta, Raparthi, A., Palaniappan, A., Kakde, S. P., Shreelakshmi, M. N., Biswas, S. K., Ahmed, S. R., Khan, R., et al. (2025) · medRxiv · doi:10.1101/2025.08.31.25334781 · Cited by 1
Kaste, R., Thyagarajan, R., Rahul, C., Sharma, G., Ashrith, G. S., Sahal, M., Patel, D. M., Patel, V., Das, A., Ramteke, H. D., et al. (2025) · medRxiv · doi:10.1101/2025.09.03.25334996 · Cited by 1
Triple Therapy IDP-126 Gel for Acne Treatment: A Systematic Review and Meta-Analysis
Sparling, K., Giri, R., Adams, A. C., Kang, P., & Farley, V. G. (2024) · Cureus · doi:10.7759/cureus.74357
Zheng, Q., Zhou, Y., & Tian, J. (2024) · Journal of Affective Disorders · doi:10.1016/j.jad.2024.12.059
Sattar, S., Papadopoulos, E., Haase, K. R., Bradley, C., Mariano, C. J., Tejero, I., Jin, R., Puts, M. T. E., & Alibhai, S. M. H. (2025) · PLoS ONE · doi:10.1371/journal.pone.0319943
Prajapati, P., Shafi, N., Pachchipulusu, V., Fatima, N., Noorien, S., Biswas, S. K., Narula, A., Aishwarya, K., Prajapati, S. D., Patel, M. K., et al. (2025) · medRxiv · doi:10.1101/2025.09.01.25334855
Pansuriya, J., Sundararajan, P. P., Ahmed, S. R., Baiju, S., Somegowda, Y. M., Merdjana, Y., Wasim, A., Patel, M. K., Prajapati, S. D., Khan, R., et al. (2025) · medRxiv · doi:10.1101/2025.08.31.25334779
Khan, R., Bokka, M., Jilakaraju, B., Baddam, S. R., Biswas, S. K., Merdjana, Y., Purohit, K., Noor-Ain, S. H., Das, A., & Ramteke, H. D. (2025) · medRxiv · doi:10.1101/2025.09.14.25335718
Atla, S. S. R., Gunasekaran, P., Kakde, S. P., Mithun, M., Waghmode, A., Singh, D., Chennupati, M., Mehveen, S., Abhinaya, M., Khan, R., et al. (2025) · medRxiv · doi:10.1101/2025.09.11.25335549
Ramteke, H. D., Sanapala, K., Das, A., Shreya, B., Paul, S., Jilakaraju, B., Vineetha, B., Senthilkumar, V., Ambala, M., Noor-Ain, S. H., et al. (2025) · medRxiv · doi:10.1101/2025.09.16.25335767
Davidson, L., & Barillas, S. R. (2025) · medRxiv · doi:10.1101/2025.09.22.25336351
Kairgeldina, S. A., Absattarova, K. S., Baurzhan, M. B., О., Т. К., Abzaliev, K. B., Abzalieva, S. A. S., Slivkina, N., Sagandykova, N. S., & СҮЙІНДІК, Қ. Б. (2025) · Vestnik · doi:10.53065/kaznmu.2025.74.3.006
Alhomaid, T., Dalgan, H. A. A., Takrouni, S. O., Alharthi, D. I., Aljammaz, A. M., Alhudaib, R. S. H., & Alotaibi, W. N. (2025) · Journal of Carcinogenesis · doi:10.64149/j.carcinog.24.8s.597-607
Alhomaid, T., Albarakati, M. H., Alzahrani, S. D., Julaih, L. A. A., Julaih, F. A. A., Alruwaythi, N. A., Alharbi, W. F., Almatrafi, W. S., & Felemban, S. M. R. (2025) · Journal of Carcinogenesis · doi:10.64149/j.carcinog.24.8s.699-713
Ramírez-Paesano, C. R., Valente-Rivero, A., Novoa, E. R., Vargas, Y. A. C., & Rodiera, J. (2025) · Journal of Opioid Management · doi:10.5055/jom.0952
Frederick, C., Ghafoor, F., & Yang, N. (2025) · Cureus · doi:10.7759/cureus.95655
Lin, C., & Her, Y. (2025) · American Journal of Therapeutics · doi:10.1097/mjt.0000000000001977
Vascular Pain as a Model of Mixed Pain: A Systematic Review and Meta-Analysis ProtocolPreprint
Varrassi, G., Farì, G., Tran, Y. V., Phong, P. V., Ameen, A. A. A., Caruso, A., & Leoni, M. L. G. (2025) · Preprints.org · doi:10.20944/preprints202511.0404.v1
Game-based learning efficiency in nursing education in Iran: a systematic review
Kamali, M., & Mousavi, S. K. (2025) · Journal of Medical Education Development · doi:10.61882/edcj.18.3.130
A methodological review of pragmatic designs in acute stroke trials
Okikiolu, A., Ray, S., Chakravarty, K., Arimoro, O. I., Martens, R., Singh, N., Ganesh, A., Almekhlafi, M., Hill, M. D., Menon, B. K., et al. (2025) · International Journal of Stroke · doi:10.1177/17474930251407852
Garg, J., Panakkal, N. C., Sukumar, S., Kadavigere, R., Thrivikraman, V., Vani Lakshmi, R., & Shanbhag, S. (2025) · Radiography · doi:10.1016/j.radi.2025.103264
Armani, M. N., Mehan, A., Patel, D., Somegowda, Y. M., Gadidesi, K., Nishat, M., Muneer, N., Ananthula, R. R., Bingursain, M. H., Reddy, S. R. K., et al. (2025) · medRxiv · doi:10.1101/2025.09.17.25335973
Khan, S. H., Manzoor, M. Z., & Khan, J. (2025) · Cureus · doi:10.7759/cureus.99868
Effectiveness of Gene Therapies for Hemophilia: A Systematic Review of Clinical Trials
Almowarey, M., Althagafi, T. M., Al-Oufi, B. M., Alsaeed, N. A., Abdulwahed, A. A., & Althagafi, A. M. (2025) · International Journal of Computational and Experimental Science and Engineering · doi:10.22399/ijcesen.4626
Intravenous Vitamin C in Severe Sepsis: A Systematic Review of Evidence From 2020 to 2025
Ahmed, R., Shetty, S., Khan, M. A., Kalsoom, I., Qasim, S. M., Khan, S. B., & Abdullah, S. (2026) · Cureus · doi:10.7759/cureus.100867
Alqarni, A., Algarni, A., & Chhetri, R. (2026) · World Journal of Cardiology · doi:10.4330/wjc.v18.i1.114123
Innovative Drug Combinations for Enhanced Solid Tumor Treatment Efficacy
(2026) · Frontiers research topics · doi:10.3389/978-2-8325-7377-8
Rangare, T., Popli, A., Sharma, S., & Thakur, S. (2026) · Journal of Manual & Manipulative Therapy · doi:10.1080/10669817.2026.2631773
Gillani, I., Ullah, M., Postoev, A., Sharma, A., Abdul, R. H. M., Chaudhary, S., Gunaratne, H., & Allahwala, D. (2026) · Cureus · doi:10.7759/cureus.104139
Rahman, H., Senaratne, M., Loueian, M. A., Madhusuthanan, A. K., Afzal, M., Turuzhbaeva, D., & Yu, A. K. (2026) · Neuro-Oncology Practice · doi:10.1093/nop/npag017
Cabezas-Durán, D., Martínez-Sánchez, A., García, J. P. F., & Villafaina, S. (2026) · Applied Sciences · doi:10.3390/app16052492
Meng, L., Chen, J., Huo, X., Zhang, Y., & Zheng, H. (2026) · Archives of Physical Medicine and Rehabilitation · doi:10.1016/j.apmr.2026.02.493
Patel, V. K., Zameer, R., Kumar, B., & Das, M. (2026) · World Journal of Meta-Analysis · doi:10.13105/wjma.v14.i1.118496
Kuo, C.-C., Wu, B.-H., Chen, M., Yueh, F.-R., & Hu, F. (2026) · Research in Gerontological Nursing · doi:10.3928/19404921-20260303-01
Yamkelani, N., Joseph, J. T., Businge, C. B., & Kamsu, G. T. (2026) · Research Square · doi:10.21203/rs.3.rs-8956740/v1
The effectiveness of dance interventions on sleep quality: a systematic review and meta-analysis
Li, Z., Song, W., Long, Y., Zhou, Y., & Ma, G. (2026) · Frontiers in Public Health · doi:10.3389/fpubh.2026.1776902
Marchesi, G., Rapelli, G., Roselli, G., Spina, G., Semonella, M., Andersson, G., Simpson, S., & Pietrabissa, G. (2026) · doi:10.2196/preprints.95227
Almohammed, H. A., Zoabi, B. M. K. A., Thalib, H. I., Alhajri, L. A., Abujamai, J. Z., Aljuaid, R. W., Alzahrani, J. H., Alsyrwan, J. M., Alwabari, M. F., Alghafli, N. A., et al. (2026) · The Egyptian Journal of Neurology Psychiatry and Neurosurgery · doi:10.1186/s41983-026-01142-z
Osimertinib for Patients With EGFR-Mutated Non-Small Cell Lung Cancer: Current Evidence
Tang, X., Chen, Y., Zhu, Y., Liu, Y., Li, W., Wang, W., & Wang, Z. (2026) · Clinical Medicine Insights Oncology · doi:10.1177/11795549261434260
Jasmi, M. A. A. A., Nazim, R., Naseri, R. N. N., & Rachmawati, R. (2026) · Advanced International Journal of Business Entrepreneurship and SMEs · doi:10.35631/aijbes.827046
Li, Y. C., Zhang, Y.-X., Jiang, F., Xu, X.-N., & Ye, H. (2026) · Langenbeck s Archives of Surgery · doi:10.1007/s00423-026-04039-w
Caserta, S., Martino, E. A., Lofaro, D., Vigna, E., Bruzzese, A., Mendicino, F., Alvaro, M. E., Labanca, C., Lucia, E., Olivito, V., et al. (2026) · European Journal Of Haematology · doi:10.1111/ejh.70191
Baran, J. M., Waszak, Z., Jarzębska, J., Grusiecki, D., Śmigielska, M., Kochman, W., & Dziedzic, E. A. (2026) · International Journal of Molecular Sciences · doi:10.3390/ijms27093805
Chantim, C., Rattanamanee, K., Songsilp, M., Klaytae, S., Khunprom, M., Saila, R., Anantachoke, P., Asawapornchai., P., Saithong, A., Techaboonsermsak., C., et al. (2026) · Dialnet (Universidad de la Rioja)
Devantoro, M. R., Abdillah, D. S., & Gunawan, D. (2026) · Romanian Medical Journal · doi:10.37897/rmj.2026.1.10
Razick, D., Akhtar, M., Wen, J., O'Brien, G., Kou, M., Razick, A. A., Syed, N. M., Razick, S. A., Siddiqui, F. S., & Lum, Z. C. (2026) · Cureus · doi:10.7759/cureus.107734
Humor and its impact on chronic pain
Κωσταμπίτσης, Α. Α. (2025) · University of Thessaly Institutional Repository (University of Thessaly)
Waqas, R., Kaur, K., Sadia, H., & Chidobu, O. N. (2026) · Cureus · doi:10.7759/cureus.108180
Tundealao, S. T., Okunlola, P., Titiloye, T., Ezema, I. G., & Egba, O. (2026) · Discover Public Health · doi:10.1186/s12982-026-01934-x
Rani, V. I., Jha, V. K., Padma, V., Rengaramanujam, K., Mahapatra, A. P. K., & Prabha, K. S. (2026) · Physiotherapy Quarterly · doi:10.5114/pq/211756
Arifin, J., Johan, M. P., Singjie, L. C., Yushan, R. M., & Tandry, M. (2026) · Orthopedic Reviews · doi:10.52965/001c.160605
Enikeev, D. A., Bakhmudov, M. A., Aznabaeva, I. F., Duskaeva, Y. I., Musaev, K. M., Alidibirova, E. K., Magomedova, P. S., Temirkhanova, S. A., Bagamaeva, K. M., & Magomedova, P. M. (2026) · Russian Medicine · doi:10.17816/medjrf704121
Thamran, B., Sihombing, B., & Steven, S. (2026) · Urogynaecologia · doi:10.4081/uij.2026.367
Taqatqa, H., & Ayyoub, A. A. (2026) · iRASD journal of educational research. · doi:10.52131/jer.2025.v7i1.3094
Taylan, S., Çeli̇k, G. K., & Gezer, D. (2026) · Irish Journal of Medical Science (1971 -) · doi:10.1007/s11845-026-04440-w
Hemdev, V., Rani, A., Qadeer, A., Kumar, P. S., Nancy, F., & Zarif, S. (2026) · Cureus · doi:10.7759/cureus.109592
Parol, Z., Żyła, M., Ustaszewska, A., Oszczypała, A., Potempa, A., Petkow, M., Prorok, L., Lipska, K., Szyszkowska, M., & Strojek, Z. (2026) · International Journal of Innovative Technologies in Social Science · doi:10.31435/ijitss.2(50).2026.5680
Parekh, R. S., Inban, P., Thai, A., Agrawal, A., Kudaiarov, D., & Tariq, H. (2026) · Disease-a-Month · doi:10.1016/j.disamonth.2026.102150
Méndez-Domínguez, N., Estrella-Castillo, D., Villarreal-Jimenez, E., & Arcila-Novelo, R. (2026) · Sports · doi:10.3390/sports14060236
Qiao, Y., Song, M., Lu, G., Liu, F., Cao, H., & Yang, M. (2026) · Frontiers in Medicine · doi:10.3389/fmed.2026.1862217
Yang, Z., Zhao, K., Hu, Y., Zhang, Q., & Zhou, Q. (2026) · BMC Psychology · doi:10.1186/s40359-026-04972-x
Marino, M., Tura, S., Rendine, M., Martini, D., Bo’, C. D., & Riso, P. (2026) · Frontiers in Nutrition · doi:10.3389/fnut.2026.1826381
Lee, H., Lim, Y., & Lee, S. H. (2026) · Medicina · doi:10.3390/medicina62061162
Gangadhar, S., Belgaumkar, A. G., & V., P. N. (2026) · International Journal of Current Pharmaceutical Review and Research · doi:10.25258/ijcpr.18.5.57
Metadata
- Authors
- Nejadghaderi, S. A., Balibegloo, M., & Rezaei, N.
- Affiliations
- Kerman University of Medical Sciences (IR)
- Universal Scientific Education and Research Network (IR)
- Corresponding author
- Rezaei, Nima
- Venue
- Health Science Reports
- Publisher
- Wiley
- Published
- 2024-06
- Volume
- 7
- Issue
- 6
- Pages
- e2165-e2165
- ISSN
- 2398-8835 (ISSN-L)
- PMC
- PMC11147813
- OpenAlex
- W4399330391
- Cited by
- 274
- References
- 17
- Citations by year
- 2026: 177 · 2025: 89 · 2024: 8
- FWCI
- 33.33
- Type
- journal article
- Language
- en
- Open access
- gold
- doi.org
- Licence
- Locations
- Health Science Reports (publishedVersion, cc-by)
- PubMed Central (publishedVersion, cc-by)
- PubMed (publishedVersion)
- Topics
- Social Sciences › Decision Sciences › Statistics, Probability and Uncertainty › Meta-analysis and systematic reviews
- Social Sciences › Sociology and Political Science › Delphi Technique in Research
- Physical Sciences › Mathematics › Statistics and Probability › Statistical Methods in Clinical Trials
- Keywords
- risk of bias assessment, critical appraisal, randomized controlled trials, trial quality assessment, systematic review methodology, funding disclosure, sample size determination
About these checks
Registry, retraction, Cites and statistics results are computed, not judged, with one exception: a printed reference that no index lists is read once by a model before it counts as a citation error. Claims are extracted by a model and kept only when their quote appears verbatim in the text; each cited source is then checked, with a model’s help, for whether it says what the claim relies on. Those verdicts can be wrong — read the claim’s quote and the cited source before relying on one.
A language model drew the claims from the paper on 2026-11-10, under version 3 of the claim definition (model deepseek-v4.1-flash, prompt extract-v3).
A second model labelled each claim on 2026-11-10 (model jev-1.13-20260917, definition revision gold-guideline-v0.2).
Cited sources are checked with a language model’s help (gpt-6-sol).
Statistics and arithmetic are recomputed, not judged.
Confidence bands are shown only for fields calibrated on our annotated test set. None is calibrated yet, so no band is shown.
What counts as a claim ›How we measure confidence ›How we check this ›
Are you an author, or do you see a problem with this page? Request a review
