

The DOI matches its Crossref record; the references it cites are not checked yet.
Postoperative glucocorticoid enhances recovery after endovascular aortic repair for chronic type B aortic dissection: a single-center experience
Open accessAbstract
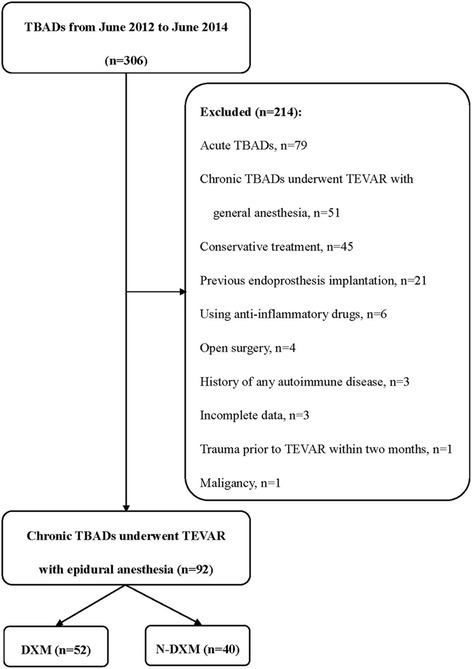
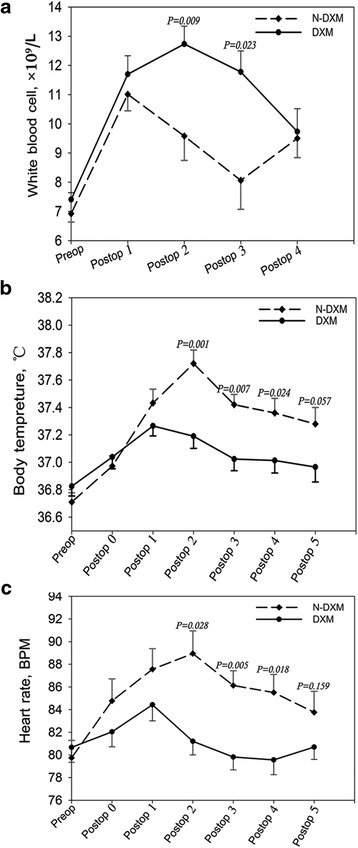
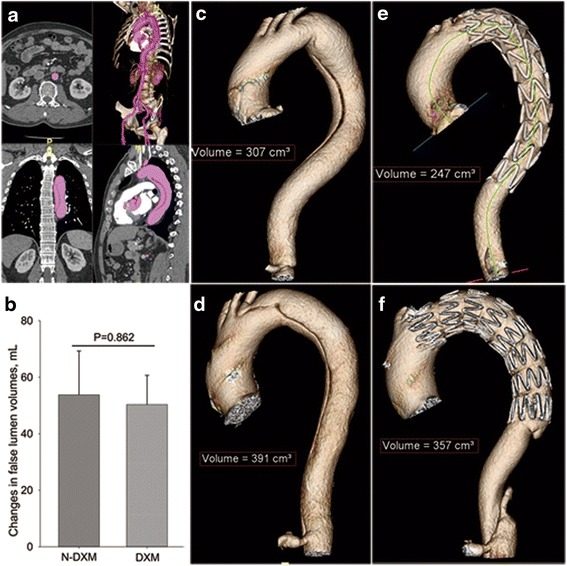
BACKGROUND: Thoracic endovascular aortic repair (TEVAR) has been chosen as a less invasive alternative for type B aortic dissections (TBADs). However, the therapeutic effect of TEVAR has been challenged by postoperative adverse events, which were induced by inflammatory response. Glucocorticoids have been widely used because of the powerful and effective anti-inflammatory properties. Nevertheless, the prognostic effect of glucocorticoids after TBAD patients underwent TEVAR remains unclear. The objective of this study was to assess the potential effect of postoperative glucocorticoids on the prognosis of TEVAR for TBADs. METHODS: A total of 92 chronic TBADs patients underwent TEVAR with epidural anesthesia between June 2012 and June 2014 was retrospectively reviewed. The patients were stratified into dexamethasone (DXM) and non-dexamethasone group (N-DXM). The indications for TEVAR were as following: malperfusion (n = 28); contained or impending rupture (n = 17); persistent intractable chest/back pain (n = 32); refractory hypertension (n = 15). RESULTS: No 30-day mortality and incision infection occurred in each group. The postoperative pain score on the second day was significantly higher in N-DXM group (3.60 ± 0.21 versus 4.83 ± 0.32, P = 0.001). The differences of white blood cell, body temperature and heart rate were pronounced in both groups judged by the peak values (13.01 ± 0.58 × 10(9)/L versus 10.04 ± 0.61 × 10(9)/L, 37.67 ± 0.08 °C versus 37.92 ± 0.09 °C and 89.06 ± 1.21 bpm versus 95.95 ± 1.70 bpm, P = 0.002, 0.04 and 0.001, respectively). The white blood cells in DXM group significantly increased on the second and third postoperative day (P = 0.009 and 0.023), while the body temperature and heart rate showed an apparent decline on the second (P = 0.001 and 0.028), third (P = 0.007 and 0.005) and fourth postoperative days (P = 0.024 and 0.018). However, the changes of false lumen volumes and the endoleak incidence at 3-month follow-up were comparable in the two groups. No significant difference of post-implantation syndrome was observed either. CONCLUSIONS: Although postoperative prophylactic glucocorticoids administration was unable to influence mortality, incision infection or the change of false lumen volumes, it enabled to enhance the recovery of vital signs and alleviate the postoperative pain. A prospective, randomized controlled trial has been registered (NCT02523300), which will be warranted before prophylactic administration of glucocorticoids after TEVAR procedure could be recommended in the clinical work.
Overview
The claims and statistics of this paper haven’t been checked yet.
Run the check — free, no account needed. It reads the open-access text and checks the sources it cites.
Integrity signals
Registry
Cites
Statistics
Figures
Verification
Claims the paper makes
The claims and statistics of this paper haven’t been checked yet.
Run the check — free, no account needed. It reads the open-access text and checks the sources it cites.
Self-check
Percentages, sums and reported differences re-computed from the paper’s own numbers.
The self-check needs the paper’s full text.
Citations
The citation lists haven’t been fetched yet
References 38 · Cited by 9
Research works printed but not linked: 38
- Sachs T, Pomposelli F, Hagberg R, Hamdan A, Wyers M, Giles K, et al. Open and endovascular repair of type b aortic dissection in the nationwide inpatient sample. J Vasc Surg. 2010;52:860–6. · DOI
- Luebke T, Brunkwall J. Outcome of patients with open and endovascular repair in acute complicated type b aortic dissection: a systematic review and meta-analysis of case series and comparative studies. J Cardiovasc Surg (Torino). 2010;51:613–32.
- Hanna JM, Andersen ND, Ganapathi AM, McCann RL, Hughes GC. Five-year results for endovascular repair of acute complicated type b aortic dissection. J Vasc Surg. 2014;59:96–106. · DOI
- Nienaber CA, Rousseau H, Eggebrecht H, Kische S, Fattori R, Rehders TC, et al. Randomized comparison of strategies for type b aortic dissection: the investigation of stent grafts in aortic dissection (instead) trial. Circulation. 2009;120:2519–28. · DOI
- Voûte MT1, Bastos Gonçalves FM, van de Luijtgaarden KM, Klein Nulent CG, Hoeks SE, Stolker RJ, et al. Stent graft composition plays a material role in the postimplantation syndrome. J Vasc Surg. 2012;56:1503–9. · DOI
- Videm V, Ødegård A, Myhre HO. Iohexol-induced neutrophil myeloperoxidase release and activation upon contact with vascular stent-graft material: a mechanism contributing to the postimplantation syndrome? J Endovasc Ther. 2003;10:958–67. · DOI
- Arnaoutoglou E, Papas N, Milionis H, Kouvelos G, Koulouras V, Matsagkas MI. Post-implantation syndrome after endovascular repair of aortic aneurysms: need for postdischarge surveillance. Interac Cardiovasc Thorac Surg. 2010;11:449–54. · DOI
- Rhen T, Cidlowski JA. Antiinflammatory action of glucocorticoids — new mechanisms for old drugs. N Engl J Med. 2005;353:1711–23. · DOI · Paper page
- Owens CD, Gasper WJ, Walker JP, Alley HF, Conte MS, Grenon SM. Safety and feasibility of adjunctive dexamethasone infusion into the adventitia of the femoropopliteal artery following endovascular revascularization. J Vasc Surg. 2014;59:1016–24. · DOI
- Orci LA, Toso C, Mentha G, Morel P, Majno PE. Systematic review and meta-analysis of the effect of perioperative steroids on ischaemia-reperfusion injury and surgical stress response in patients undergoing liver resection. Br J Surg. 2013;100:600–9. · DOI
- Srinivasa S, Kahokehr AA, Yu TC, Hill AG. Preoperative glucocorticoid use in major abdominal surgery: systematic review and meta-analysis of randomized trials. Ann Surg. 2011;254:183–91. · DOI
- Lunn TH, Kehlet H. Perioperative glucocorticoids in hip and knee surgery - benefit vs. Harm? A review of randomized clinical trials. Acta Anaesthesiol Scand. 2013;57:823–34. · DOI
- Schäcke H, Döcke W-D, Asadullah K. Mechanisms involved in the side effects of glucocorticoids. Pharmacol Ther. 2002;96:23–43. · DOI · Paper page
- Morikage N, Esato K, Zenpo N, Fujioka K, Takenaka H. Is endovascular treatment of abdominal aortic aneurysms less invasive regarding the biological responses? Surg Today. 2000;30:142–6. · DOI
- Eggebrecht H, Mehta RH, Metozounve H, Huptas S, Herold U, Jakob HG, et al. Clinical implications of systemic inflammatory response syndrome following thoracic aortic stent-graft placement. J Endovasc Ther. 2008;15:135–43. · DOI
- Ker CR, Ho MC, Huang JW, Hsieh CC, Chen HM. Pyrexia of postimplantation syndrome for patients undergoing (thoracic) endovascular aortic repair. Thorac Cardiovasc Surg. 2015;63:126–33. · DOI
- Erbel R, Aboyans V, Boileau C, Bossone E, Bartolomeo RD, Eggebrecht H, et al. 2014 ESC guidelines on the diagnosis and treatment of aortic diseases: document covering acute and chronic aortic diseases of the thoracic and abdominal aorta of the adult. The Task Force for the Diagnosis and Treatment of Aortic Diseases of the European Society of Cardiology (ESC). Eur Heart J. 2014;35:2873–926. · DOI
- Bijur PE, Silver W, Gallagher EJ. Reliability of the visual analog scale for measurement of acute pain. Acad Emerg Med. 2001;8:1153–7. · DOI
- Chen J, Hillman K, Bellomo R, Flabouris A, Finfer S, Cretikos M. The impact of introducing medical emergency team system on the documentations of vital signs. Resuscitation. 2009;80:35–43. · DOI
- Harrison GA, Jacques T, McLaws M-L, Kilborn G. Combinations of early signs of critical illness predict in-hospital death—the soccer study (signs of critical conditions and emergency responses). Resuscitation. 2006;71:327–34. · DOI
- Rousseau P. Pain as the fifth vital sign. Arch Surg. 2008;143:98.
- Morone NE, Weiner DK. Pain as the fifth vital sign: exposing the vital need for pain education. Clin Ther. 2013;35:1728–32. · DOI
- Oderda G. Challenges in the management of acute postsurgical pain. Pharmacotherapy. 2012;32:6S–11S. · DOI
- Hengge UR, Ruzicka T, Schwartz RA, Cork MJ. Adverse effects of topical glucocorticosteroids. J Am Acad Dermatol. 2006;54:1–15. · DOI
- Dieleman JM, Nierich AP, Rosseel PM, van der Maaten JM, Hofland J, Diephuis JC, et al. Intraoperative high-dose dexamethasone for cardiac surgery: a randomized controlled trial. JAMA. 2012;308:1761–7. · DOI
- Wang AS, Armstrong EJ, Armstrong AW. Corticosteroids and wound healing: clinical considerations in the perioperative period. Am J Surg. 2013;206:410–7. · DOI
- Abdelmalak BB, Bonilla AM, Yang D, Chowdary HT, Gottlieb A, Lyden SP, et al. The hyperglycemic response to major noncardiac surgery and the added effect of steroid administration in patients with and without diabetes. Anesth Analg. 2013;116:1116–22. · DOI
- de la Motte L, Kehlet H, Vogt K, Nielsen CH, Groenvall JB, Nielsen HB, et al. Preoperative methylprednisolone enhances recovery after endovascular aortic repair: a randomized, double-blind, placebo-controlled clinical trial. Ann Surg. 2014;260:540–8. · DOI
- Gerasimidis T, Sfyroeras G, Trellopoulos G, Skoura L, Papazoglou K, Konstantinidis K, et al. Impact of endograft material on the inflammatory response after elective endovascular abdominal aortic aneurysm repair. Angiology. 2005;56:743–53. · DOI
- Gabriel EA, Locali RF, Romano CC, Duarte AJ, Palma JH, Buffolo E. Analysis of the inflammatory response in endovascular treatment of aortic aneurysms. Eur J Cardiothorac Surg. 2007;31:406–12. · DOI
- De La Motte L, Vogt K, Panduro Jensen L, Groenvall J, Kehlet H, Veith Schroeder T, et al. Incidence of systemic inflammatory response syndrome after endovascular aortic repair. J Cardiovasc Surg (Torino). 2011;52:73–9.
- Norwood MG, Bown MJ, Lloyd G, Bell PR, Sayers RD. The clinical value of the systemic inflammatory response syndrome (SIRS) in abdominal aortic aneurysm repair. Eur J Vasc Endovasc Surg. 2004;27:292–8. · DOI
- Weng M, Sun Z, Miao C. Corticosteroid induce leukocytosis during the pain management. Pain Med. 2014;15:1645–6. · DOI
- Brotman DJ, Girod JP, Posch A, Jani JT, Patel JV, Gupta M, et al. Effects of short-term glucocorticoids on hemostatic factors in healthy volunteers. Thromb Res. 2006;118:247–52. · DOI
- Johannesdottir SA, Horváth-Puhó E, Dekkers OM, Cannegieter SC, Jørgensen JO, Ehrenstein V, et al. Use of glucocorticoids and risk of venous thromboembolism: a nationwide population-based case–control study. JAMA Intern Med. 2013;173:743–52. · DOI
- Squizzato A, Gerdes VE, Ageno W, Buller HR. The coagulation system in endocrine disorders: a narrative review. Intern Emerg Med. 2007;2:76–83. · DOI
- van Zaane B, Nur E, Squizzato A, Gerdes VE, Büller HR, Dekkers OM, et al. Systematic review on the effect of glucocorticoid use on procoagulant, anti-coagulant and fibrinolytic factors. J Thromb Haemost. 2010;8:2483–93. · DOI
- Conrad MF, Crawford RS, Kwolek CJ, Brewster DC, Brady TJ, Cambria RP. Aortic remodeling after endovascular repair of acute complicated type b aortic dissection. J Vasc Surg. 2009;50:510–7. · DOI
Metadata
- Authors
- Wu, M., Zhang, L., Bao, J., Zhao, Z., Lu, Q., Feng, R., Song, C., Zhou, J., & Jing, Z.
- Affiliations
- Second Military Medical University (CN)
- Corresponding author
- Zhou, Jian
- Jing, Zaiping
- ORCID
- Venue
- BMC Cardiovascular Disorders
- Published
- 2016-03-25
- Volume
- 16
- Issue
- 1
- Pages
- 59-59
- ISSN
- 1471-2261 (ISSN-L)
- PMC
- PMC4807598
- OpenAlex
- W2306408545
- Cited by
- 9
- References
- 38
- Citations by year
- 2026: 1 · 2025: 1 · 2023: 1 · 2022: 3 · 2021: 2 · 2018: 1
- FWCI
- 0.30
- Type
- journal article
- Language
- en
- Open access
- gold
- doi.org
- Licence
- cc-by
- Locations
- BMC Cardiovascular Disorders (publishedVersion, cc-by)
- PubMed Central (publishedVersion, cc-by)
- PubMed (publishedVersion)
- Funders
- National Natural Science Foundation of China (CN) (81330034, 81273522)
- Key Project of Basic Research in Shanghai (12JC1410802)
- National Natural Science Foundation of China (81173072)
- Topics
- Health Sciences › Medicine › Cardiology and Cardiovascular Medicine › Aortic Disease and Treatment Approaches
- Health Sciences › Medicine › Surgery › Aortic aneurysm repair treatments
- Life Sciences › Biochemistry, Genetics and Molecular Biology › Genetics › Connective tissue disorders research
- Keywords
- type B aortic dissection, thoracic endovascular aortic repair, dexamethasone, anti-inflammatory therapy, postoperative pain, inflammation, white blood cell count, fever, heart rate, postoperative recovery, prognosis, epidural anesthesia, malperfusion, aortic rupture risk, resistant hypertension, incisional infection, 30-day mortality
- MeSH terms
- Computed Tomography Angiography, Aortic Dissection, Aortography, China, Chronic Disease, Dexamethasone, Drug Administration Schedule, Female, Glucocorticoids, Humans, Male, Middle Aged, Pain, Postoperative, Postoperative Pain, Postoperative Care, Retrospective Studies, Time Factors, Treatment Outcome, Aortic Aneurysm, Thoracic, Blood Vessel Prosthesis Implantation, Recovery of Function, Endovascular Procedures, Multidetector Computed Tomography
About these checks
Registry, retraction, Cites and statistics results are computed, not judged, with one exception: a printed reference that no index lists is read once by a model before it counts as a citation error. Claims are extracted by a model and kept only when their quote appears verbatim in the text; each cited source is then checked, with a model’s help, for whether it says what the claim relies on. Those verdicts can be wrong — read the claim’s quote and the cited source before relying on one.
Statistics and arithmetic are recomputed, not judged.
Confidence bands are shown only for fields calibrated on our annotated test set. None is calibrated yet, so no band is shown.
What counts as a claim ›How we measure confidence ›How we check this ›
Are you an author, or do you see a problem with this page? Request a review
How to cite
Cite CoChat for the checks on this page, and the paper for its own findings.
- This page
- CoChat. (2026). Citation check: Postoperative glucocorticoid enhances recovery after endovascular aortic repair for chronic type B aortic dissection: a single-center experience. https://app.cochat.ai/papers/10.1186/s12872-016-0234-2
- The paper
- Wu, M., Zhang, L., Bao, J., Zhao, Z., Lu, Q., Feng, R., Song, C., Zhou, J., & Jing, Z. (2016). Postoperative glucocorticoid enhances recovery after endovascular aortic repair for chronic type B aortic dissection: a single-center experience. BMC Cardiovascular Disorders. https://doi.org/10.1186/s12872-016-0234-2
