

The DOI matches its Crossref record; 20 of the 20 references it cites were found in a registry or an index.
Xpert MTB/RIF assay for the differential diagnosis between sarcoidosis and tuberculosis intrathoracic lymphadenopathy
Open accessAbstract
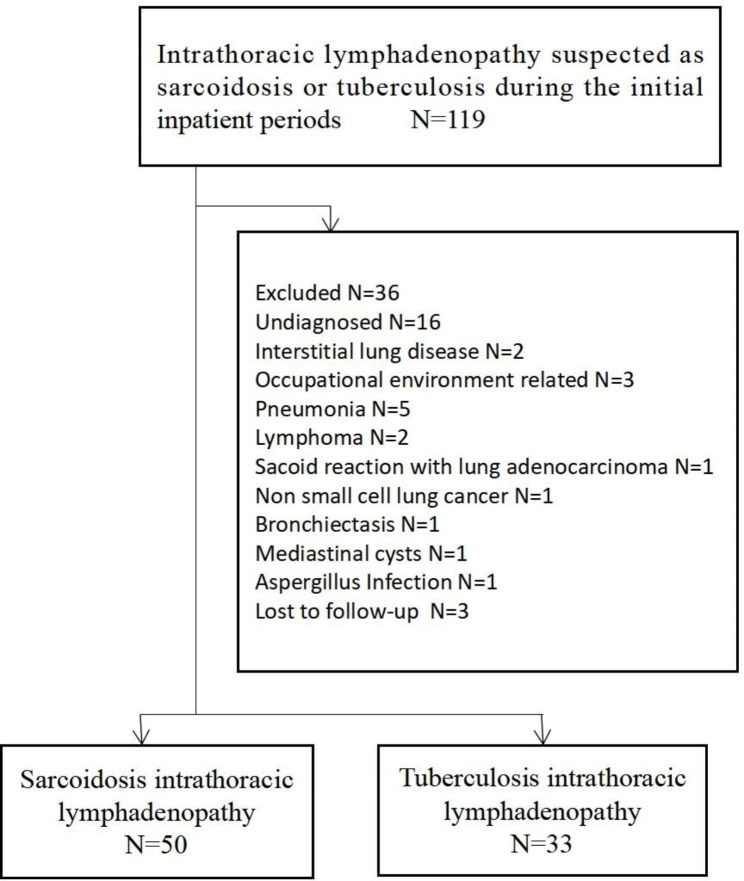
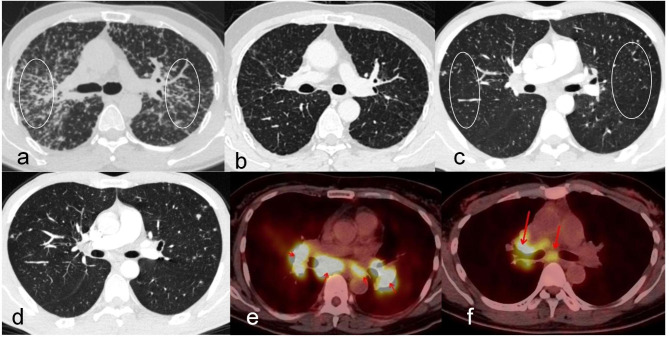
Background: The aim of this study was to evaluate the role of Xpert MTB/RIF assay in the detection of Mycobacterium tuberculosis for differentiating tuberculosis intrathoracic lymphadenopathy from sarcoidosis intrathoracic lymphadenopathy. Methods: The patients who were suspected to having sarcoidosis or tuberculosis intrathoracic lymphadenopathy at the Shanghai Pulmonary Hospital between October 1, 2020 and June 30, 2021 were retrospectively evaluated in this study. All patients underwent endobronchial ultrasound-guided transbronchial needle aspiration (EBUS-TBNA) and Xpert analysis. Differences in clinical and radiological features were recorded. The diagnostic performances of EBUS-TBNA Xpert, acid-fast bacilli, culture, and peripheral blood QuantiFERON-TB Gold (QFT) for differentiating sarcoidosis from tuberculosis intrathoracic lymphadenopathy were analyzed. Results: A total of 119 patients were included in this analysis. Of those, 83 patients were finally diagnosed with sarcoidosis (N = 50) and tuberculosis (N = 33) intrathoracic lymphadenopathy. Young individuals were more likely to have tuberculosis versus sarcoidosis intrathoracic lymphadenopathy (P = 0.006). Markers of inflammation, including fever, leukocytes, and serum ferritin levels, were significantly higher in tuberculosis versus sarcoidosis intrathoracic lymphadenopathy (P < 0.01). Bilateral lung involvement and symmetry intrathoracic lymphadenopathy were more common in sarcoidosis intrathoracic lymphadenopathy (P < 0.01). In addition, the longest diameter of intrathoracic lymphadenopathy (in cm) was significantly larger in sarcoidosis intrathoracic lymphadenopathy (P = 0.001). However, the largest diameter of lung lesions was significantly shorter (P = 0.005). The sensitivity and specificity values of Xpert and QFT for differentiating these two diseases were 69.70% and 100%, and 96.43% and 91.84%, respectively. Conclusion: Xpert MTB/RIF is recommended for the diagnosis of tuberculosis intrathoracic lymphadenopathy using EBUS-TBNA samples. A negative QFT suggests the exclusion of the diagnosis of tuberculosis intrathoracic lymphadenopathy.
Overview
The claims and statistics of this paper haven’t been checked yet.
Run the check — free, no account needed. It reads the open-access text and checks the sources it cites.
Integrity signals
Registry
Cites
Statistics
Figures
Verification
Claims the paper makes
The claims and statistics of this paper haven’t been checked yet.
Run the check — free, no account needed. It reads the open-access text and checks the sources it cites.
Claims other papers make about this one
Each is checked against this paper’s own text: does it say what the citing paper says it does?
The source backs part of the claim, not all of it — or backs it for a different population, condition or comparison.
In the citing paper
“The Xpert MTB/RIF assay and QuantiFERON-TB Gold tests have shown high specificity and sensitivity in distinguishing TB from sarcoidosis. These tests can detect mycobacterial DNA or immune response to TB antigens, which are absent in sarcoidosis [57].”
From Head and Neck Tuberculosis: A Rare Diagnosis and the Role of Surgical Biopsy and Histopathological Evaluation in Extrapulmonary Disease (2025) · cites this paper as [57]
Experimental — accuracy not yet measured
Self-check
Percentages, sums and reported differences re-computed from the paper’s own numbers.
The self-check needs the paper’s full text.
Citations
Cites
Crouser, E. D., Maier, L. A., Wilson, K. C., Bonham, C. A., Morgenthau, A. S., Patterson, K. C., Abston, E. D., Bernstein, R. C., Blankstein, R., Chen, E. S., et al. (2020) · American Journal of Respiratory and Critical Care Medicine · doi:10.1164/rccm.202002-0251st · Cited by 1,099
Epidemiology of Extrapulmonary Tuberculosis in the United States, 1993–2006
Peto, H. M., Pratt, R. H., Harrington, T. A., LoBue, P. A., & Armstrong, L. R. (2009) · Clinical Infectious Diseases · doi:10.1086/605559 · Cited by 741
Denkinger, C. M., Schumacher, S. G., Boehme, C. C., Dendukuri, N., Pai, M., & Steingart, K. R. (2014) · European Respiratory Journal · doi:10.1183/09031936.00007814 · Cited by 527 · cited 1×
“[7].”
Epidemiology of Extrapulmonary Tuberculosis among Inpatients, China, 2008–2017
Pang, Y., An, J., Shu, W., Huo, F., Chu, N., Gao, M., Qin, S., Huang, H., Chen, X., & Xu, S. (2019) · Emerging infectious diseases · doi:10.3201/eid2503.180572 · Cited by 285
Xpert ® MTB/RIF assay for extrapulmonary tuberculosis and rifampicin resistance
Kohli, M., Schiller, I., Dendukuri, N., Dheda, K., Denkinger, C. M., Schumacher, S. G., & Steingart, K. R. (2018) · Cochrane Database of Systematic Reviews · doi:10.1002/14651858.cd012768.pub2 · Cited by 245
Extrapulmonary tuberculosıs: an old but resurgent problem
BAYKAN, A. H., Sayıner, H. S., Aydın, E., Koç, M., İnan, İ., & Ertürk, Ş. M. (2022) · Insights into Imaging · doi:10.1186/s13244-022-01172-0 · Cited by 176
Sarcoidosis: Epidemiology and clinical insights
Rossides, M., Darlington, P., Kullberg, S., & Arkema, E. V. (2023) · Journal of Internal Medicine · doi:10.1111/joim.13629 · Cited by 158
Imaging of pulmonary tuberculosis
Dyck, P. V., Vanhoenacker, F. M. H. M., den Brande, P. V., & de Schepper, A. M. (2002) · European Radiology · doi:10.1007/s00330-002-1612-y · Cited by 145
Zhou, G., Luo, Q., Luo, S., Teng, Z., Ji, Z., Yang, J., Wang, F., Wen, S., Ding, Z., Li, L., et al. (2020) · The Lancet Infectious Diseases · doi:10.1016/s1473-3099(20)30276-0 · Cited by 137
Self-citationLymph nodes—The neglected battlefield in tuberculosis
Ganchua, S. K. C., White, A. G., Klein, E. C., & Flynn, J. L. (2020) · PLoS Pathogens · doi:10.1371/journal.ppat.1008632 · Cited by 127
Research works printed but not linked: 1
- World Health Organization. Xpert MTB/RIF Assay for the diagnosis of pulmonary and extrapulmonary TB in adults and children: policy update. Geneva: WHO; 2013.
Cited by
Sorted by citations
Mogoantă, C. A., Osman, A., Georgescu, A.-M., Mitroi, A. M., Busuioc, C. I., Tănase, I., Cioboată, R., Liliac, I. M., Cimpeanu, O. L., & Ciolofan, M. S. (2025) · Pathogens · doi:10.3390/pathogens14050479 · Cited by 2
“These tests can detect mycobacterial DNA or immune response to TB antigens, which are absent in sarcoidosis [57].”
Maturu, V. N., Pranitha, P., Prasad, V. P., Rachel, R., Garg, V. K., Kotla, S. S., Milap, S., & Prakasham, P. S. (2025) · Journal of Bronchology & Interventional Pulmonology · doi:10.1097/lbr.0000000000001047 · Cited by 2
Lymphoproliferative Disorders Mimicking Rheumatologic Disease: A Clinical Reasoning Perspective
Shen, J. Z., Carlsen, E. D., Carrillo, L. F., Cintrón-López, D., Kellogg, B., Lim, J. L., Nicholas, M. W., Lackey, E., & Dasher, J. (2025) · Current Allergy and Asthma Reports · doi:10.1007/s11882-025-01220-x · Cited by 1
Kamel, F. Z., Ismail, N. A., Khater, A., Shahaway, A. A. E., Almadani, N. A., Sankarapandian, C., & Hammad, N. (2026) · Microorganisms · doi:10.3390/microorganisms14020369
Memon, J. A., Shah, M. S., Memon, Z. A., & Malik, U. (2026) · Current Problems in Diagnostic Radiology · doi:10.1067/j.cpradiol.2026.08.002
Metadata
- Authors
- He, X., Zhang, Y., Zhou, Y., Li, L., & Li, Q.
- Affiliations
- Tongji University (CN)
- Corresponding author
- Li, Qiuhong
- Venue
- BMC Infectious Diseases
- Published
- 2023-10-25
- Volume
- 23
- Issue
- 1
- Pages
- 725-725
- ISSN
- 1471-2334 (ISSN-L)
- PMC
- PMC10601222
- OpenAlex
- W4387935482
- Cited by
- 5
- References
- 20
- Citations by year
- 2026: 2 · 2025: 3
- FWCI
- 1.03
- Type
- journal article
- Language
- en
- Open access
- gold
- doi.org
- Locations
- BMC Infectious Diseases (publishedVersion, cc-by)
- PubMed Central (publishedVersion, cc-by)
- PubMed (publishedVersion)
- DOAJ (DOAJ: Directory of Open Access Journals) (submittedVersion, cc-by-sa)
- Funders
- National Natural Science Foundation of China (81200046, 81903977, 82000068)
- Natural Science Foundation of Shanghai (18ZR1431400, 21ZR1447700, 20ZR1446800)
- Science and Technology Innovation Research Project of Shanghai Science and Technology Commission (20Y11902700)
- Topics
- Health Sciences › Medicine › Infectious Diseases › Tuberculosis Research and Epidemiology
- Health Sciences › Medicine › Pulmonary and Respiratory Medicine › Sarcoidosis and Beryllium Toxicity Research
- Health Sciences › Medicine › Infectious Diseases › Diagnosis and treatment of tuberculosis
- Keywords
- Xpert MTB/RIF, sarcoidosis, tuberculosis, intrathoracic lymphadenopathy, differential diagnosis, endobronchial ultrasound-guided transbronchial needle aspiration, QuantiFERON-TB Gold, Mycobacterium tuberculosis detection, acid-fast bacilli, serum ferritin
- MeSH terms
- Lymphadenopathy, China, Diagnosis, Differential, Humans, Mycobacterium tuberculosis, Retrospective Studies, Sarcoidosis, Sensitivity and Specificity, Tuberculosis
About these checks
Registry, retraction, Cites and statistics results are computed, not judged, with one exception: a printed reference that no index lists is read once by a model before it counts as a citation error. Claims are extracted by a model and kept only when their quote appears verbatim in the text; each cited source is then checked, with a model’s help, for whether it says what the claim relies on. Those verdicts can be wrong — read the claim’s quote and the cited source before relying on one.
Statistics and arithmetic are recomputed, not judged.
Confidence bands are shown only for fields calibrated on our annotated test set. None is calibrated yet, so no band is shown.
What counts as a claim ›How we measure confidence ›How we check this ›
Are you an author, or do you see a problem with this page? Request a review
