

The DOI matches its Crossref record; 40 of the 42 references it cites were found in a registry or an index.
Evolution of Antiretroviral Drug Costs in Brazil in the Context of Free and Universal Access to AIDS Treatment
Open accessAbstract
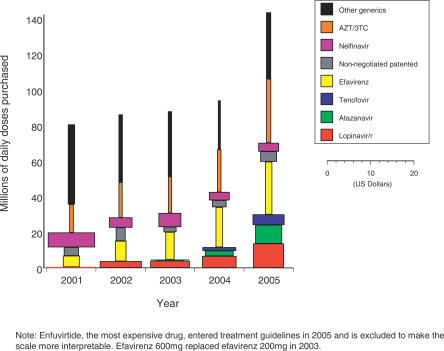
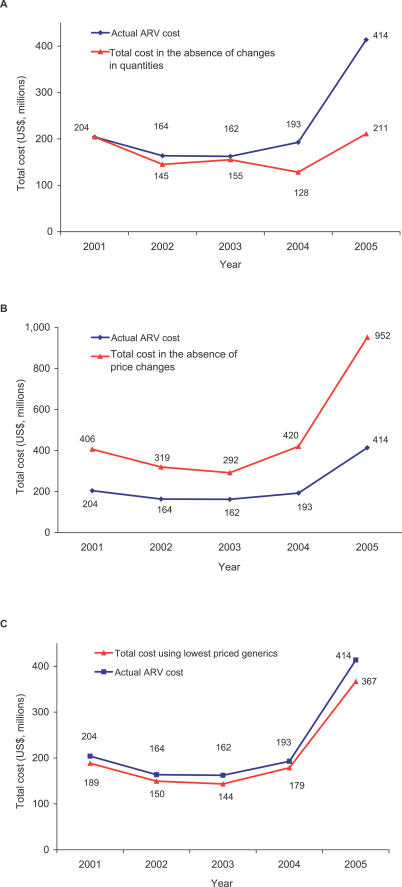
BACKGROUND: Little is known about the long-term drug costs associated with treating AIDS in developing countries. Brazil's AIDS treatment program has been cited widely as the developing world's largest and most successful AIDS treatment program. The program guarantees free access to highly active antiretroviral therapy (HAART) for all people living with HIV/AIDS in need of treatment. Brazil produces non-patented generic antiretroviral drugs (ARVs), procures many patented ARVs with negotiated price reductions, and recently issued a compulsory license to import one patented ARV. In this study, we investigate the drivers of recent ARV cost trends in Brazil through analysis of drug-specific prices and expenditures between 2001 and 2005. METHODS AND FINDINGS: We compared Brazil's ARV prices to those in other low- and middle-income countries. We analyzed trends in drug expenditures for HAART in Brazil from 2001 to 2005 on the basis of cost data disaggregated by each ARV purchased by the Brazilian program. We decomposed the overall changes in expenditures to compare the relative impacts of changes in drug prices and drug purchase quantities. We also estimated the excess costs attributable to the difference between prices for generics in Brazil and the lowest global prices for these drugs. Finally, we estimated the savings attributable to Brazil's reduced prices for patented drugs. Negotiated drug prices in Brazil are lowest for patented ARVs for which generic competition is emerging. In recent years, the prices for efavirenz and lopinavir-ritonavir (lopinavir/r) have been lower in Brazil than in other middle-income countries. In contrast, the price of tenofovir is US$200 higher per patient per year than that reported in other middle-income countries. Despite precipitous price declines for four patented ARVs, total Brazilian drug expenditures doubled, to reach US$414 million in 2005. We find that the major driver of cost increases was increased purchase quantities of six specific drugs: patented lopinavir/r, efavirenz, tenofovir, atazanavir, enfuvirtide, and a locally produced generic, fixed-dose combination of zidovudine and lamivudine (AZT/3TC). Because prices declined for many of the patented drugs that constitute the largest share of drug costs, nearly the entire increase in overall drug expenditures between 2001 and 2005 is attributable to increases in drug quantities. Had all drug quantities been held constant from 2001 until 2005 (or for those drugs entering treatment guidelines after 2001, held constant between the year of introduction and 2005), total costs would have increased by only an estimated US$7 million. We estimate that in the absence of price declines for patented drugs, Brazil would have spent a cumulative total of US$2 billion on drugs for HAART between 2001 and 2005, implying a savings of US$1.2 billion from price declines. Finally, in comparing Brazilian prices for locally produced generic ARVs to the lowest international prices meeting global pharmaceutical quality standards, we find that current prices for Brazil's locally produced generics are generally much higher than corresponding global prices, and note that these prices have risen in Brazil while declining globally. We estimate the excess costs of Brazil's locally produced generics totaled US$110 million from 2001 to 2005. CONCLUSIONS: Despite Brazil's more costly generic ARVs, the net result of ARV price changes has been a cost savings of approximately US$1 billion since 2001. HAART costs have nevertheless risen steeply as Brazil has scaled up treatment. These trends may foreshadow future AIDS treatment cost trends in other developing countries as more people start treatment, AIDS patients live longer and move from first-line to second and third-line treatment, AIDS treatment becomes more complex, generic competition emerges, and newer patented drugs become available. The specific application of the Brazilian model to other countries will depend, however, on the strength of their health systems, intellectual property regulations, epidemiological profiles, AIDS treatment guidelines, and differing capacities to produce drugs locally.
Overview
The claims and statistics of this paper haven’t been checked yet.
Run the check — free, no account needed. It reads the open-access text and checks the sources it cites.
Integrity signals
Registry
Cites
Statistics
Figures
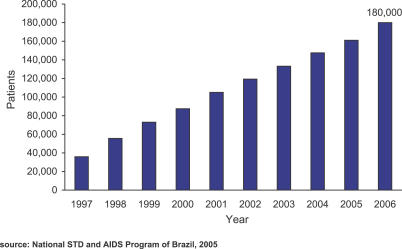
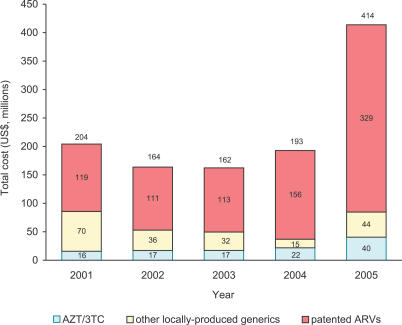
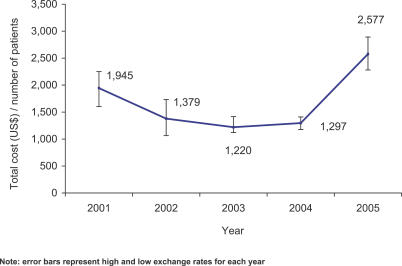
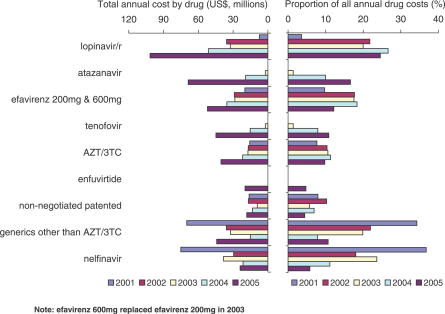
Verification
Claims the paper makes
The claims and statistics of this paper haven’t been checked yet.
Run the check — free, no account needed. It reads the open-access text and checks the sources it cites.
Claims other papers make about this one
Each is checked against this paper’s own text: does it say what the citing paper says it does?
The check wasn’t confident either way, so it gives no verdict — never disputed.
In the citing paper
“inequities in access to COVID-19 vaccines would likely have disproportionately protected higher income sub-city units from hospitalization and death [74].”
From Social epidemiology of urban COVID-19 inequalities in Latin America and Canada (2024) · cites this paper as [74]
Experimental — accuracy not yet measured
Self-check
Percentages, sums and reported differences re-computed from the paper’s own numbers.
The self-check needs the paper’s full text.
Citations
Cites
Global Burden of Disease and Risk Factors
López, A. D., Mathers, C. D., Ezzati, M., Jamison, D. T. T., & Murray, C. J. L. (2006) · World Bank, Washington, DC eBooks · doi:10.1596/978-0-8213-6262-4 · Cited by 2,714
Gallant, J. E. (2004) · JAMA · doi:10.1001/jama.292.2.191 · Cited by 1,341
Staszewski, S., Morales-Ramirez, J. O., Tashima, K. T., Rachlis, A., Skiest, D. J., Stanford, J., Stryker, R., Johnson, P. C., Labriola, D., Farina, D., et al. (1999) · New England Journal of Medicine · doi:10.1056/nejm199912163412501 · Cited by 993
Mills, E. J., Nachega, J. B., Bangsberg, D. R., Singh, S., Rachlis, B., Wu, P., Wilson, K., Buchan, I., Gill, C. J., & Cooper, C. (2006) · PLoS Medicine · doi:10.1371/journal.pmed.0030438 · Cited by 818
Lopinavir–Ritonavir versus Nelfinavir for the Initial Treatment of HIV Infection
Walmsley, S. L., Bernstein, B. M., King, M. S., Arribas, J. R., Beall, G. N., Ruane, P. J., Johnson, M. A., Johnson, D., LALONDE, R. G., Japour, A. J., et al. (2002) · New England Journal of Medicine · doi:10.1056/nejmoa012354 · Cited by 646
Agreement on trade-related aspects of intellectual property rights
Heath, G. (2000) · Comparative law yearbook of international business · Cited by 469
Dramatic improvement in survival among adult Brazilian AIDS patients
Marins, J. R. P., Jamal, L. F., Chen, S. Y., Barros, M. B. D. A., Hudes, E. S., Barbosa, A. A., Chequer, P., Teixeira, P. R., & Hearst, N. (2003) · AIDS · doi:10.1097/00002030-200307250-00012 · Cited by 380
Comparison of Sequential Three-Drug Regimens as Initial Therapy for HIV-1 Infection
Robbins, G. K., Gruttola, V. D., Shafer, R. W., Smeaton, L. M., Snyder, S. W., Pettinelli, C. B., Dubé, M. P., Fischl, M. A., Pollard, R. B., Delapenha, R., et al. (2003) · New England Journal of Medicine · doi:10.1056/nejmoa030264 · Cited by 351
Schooley, R. T., Ruane, P. J., Myers, R. A., Beall, G. N., Lampiris, H. W., Berger, D., Chen, S., Miller, M. D., Isaacson, E., & Cheng, A. (2002) · AIDS · doi:10.1097/00002030-200206140-00008 · Cited by 272
Access to antiretroviral drugs in Brazil
Galvão, J. (2002) · The Lancet · doi:10.1016/s0140-6736(02)11775-2 · Cited by 234
Research works printed but not linked: 42
- Szwarcwald, 2000, Cad de Saúde Pública, 16, 135
- Matida, 2005, AIDS, 19, S37
- Marins, 2003, AIDS, 17, 1675
- Teixeira, 2004, AIDS, 18, S5
- Campos, 2005, AIDS, 19, S22
- Hacker, 2004, Rev Panam Salud Publica, 16, 78
- Dourado, 2006, Rev Saude Publica, 40, 91
- Esau, 2003, AIDS, 17, 1583
- Brito, 2005, Braz J Inf Dis, 9, 9
- Galvão, 2002, Lancet, 360, 1862
- Cohen, 2006, Science, 313, 484
- Tanuri, 2002, J Clin Virol, 25, 39
- Petersen, 2006, Rev Panam Salud Publica, 19, 146
- Soares, 2004, AIDS, 18, S9
- Padua, 2006, Braz J Med Biol Res, 39, 495
- Santos, 2005, AIDS, 19, S14
- Blal, 2005, Eur J Clin Microbiol Infect Dis, 24, 41
- Resende, 2004, Infect Control Hosp Epidemiol, 25, 1115
- Morgado, 2000, Mem Inst Oswaldo Cruz, 95, 145
- Scheffer, 2005, O remédio via justiça
- Okie, 2006, N Engl J Med, 354, 1977
- Grangeiro, 2006, Rev Saude Publica, 40, 60
- Chequer, 2005, Access to treatment and prevention: Brazil and beyond [plenary session presentation]
- Walmsley, 2002, N Engl J Med, 346, 2039
- Sanne, 2003, J Acquir Immune Defic Syndr, 32, 18
- Kempf, 2004, J Infect Dis, 189, 51
- Hicks, 2004, AIDS, 18, 775
- Murphy, 2003, AIDS, 17, 2603
- Schooley, 2002, AIDS, 16, 1257
- Gallant, 2004, JAMA, 292, 191
- Staszewski, 1999, N Engl J Med, 341, 1865
- DeJesus, 2004, Clin Infect Dis, 39, 1038
- Albrecht, 2001, N Engl J Med, 345, 398
- Robbins, 2003, N Engl J Med, 349, 2293
- Clotet, 2004, AIDS, 18, 1137
- Mills, 2006, PLoS Med, 3
- Stone, 2004, J Acquir Immune Defic Syndr, 36, 808
- Legorreta, 2005, AIDS Care, 17, 938
- Pinheiro, 2006, AIDS, 20, 1745
- Landim, 2007, Valor Econômico. São Paulo
- Gentleman, 2006 May 12, The New York Times
- Zamiska, 2007 April 24, The Wall Street Journal
Cited by
Sorted by citations
Barreto, M. L., Teixeira, M. G., Bastos, F. I., Ximenes, R. A. A., Barata, R. B., & Rodrigues, L. C. (2011) · The Lancet · doi:10.1016/s0140-6736(11)60202-x · Cited by 23,063
Self-citationPolitical and economic aspects of the transition to universal health coverage
Savedoff, W. D., de Ferranti, D., Smith, A. L., & Fan, V. Y. (2012) · The Lancet · doi:10.1016/s0140-6736(12)61083-6 · Cited by 297
The ART-LINC Collaboration of the International Databases to Evaluate AIDS (IeDEA) (2008) · Tropical Medicine & International Health · doi:10.1111/j.1365-3156.2008.02078.x · Cited by 187
AIDS Treatment In Brazil: Impacts And Challenges
Nunn, A. S., da Fonseca, E. M., Bastos, F. I., & Gruskin, S. (2009) · Health Affairs · doi:10.1377/hlthaff.28.4.1103 · Cited by 142
Self-citationMalta, M., Magnanini, M. M. F., Mello, M. B., Pascom, A. R. P., Linhares, Y., & Bastos, F. I. (2010) · BMC Public Health · doi:10.1186/1471-2458-10-317 · Cited by 126
Self-citation
Metadata
- Authors
- Nunn, A. S., Fonseca, E. M., Bastos, F. I., Gruskin, S., & Salomon, J. A.
- Affiliations
- Harvard University (US)
- Fundação Oswaldo Cruz (BR)
- Corresponding author
- Nunn, Amy S
- Venue
- PLoS Medicine
- Publisher
- Public Library of Science (PLoS)
- Published
- 2007-11-13
- Volume
- 4
- Issue
- 11
- Pages
- e305
- ISSN
- 1549-1277 (ISSN-L)
- 1549-1676
- PMC
- PMC2071936
- OpenAlex
- W2104489459
- Cited by
- 142
- References
- 42
- Citations by year
- 2026: 1 · 2025: 1 · 2024: 2 · 2023: 2 · 2021: 6 · 2020: 2 · 2019: 3 · 2018: 9 · 2017: 6 · 2016: 5 · 2015: 5 · 2014: 5 · 2013: 12 · 2012: 19
- FWCI
- 35.48
- Type
- journal article
- Language
- en
- Open access
- gold
- doi.org
- Locations
- PLoS Medicine (publishedVersion, cc-by)
- PubMed Central (publishedVersion, cc-by)
- PubMed (publishedVersion)
- Digital Access to Scholarship at Harvard (DASH) (Harvard University) (submittedVersion, cc-by)
- RePEc: Research Papers in Economics (submittedVersion)
- DOAJ (DOAJ: Directory of Open Access Journals) (submittedVersion, cc-by-sa)
- Figshare (submittedVersion, cc-by)
- Funders
- Bill and Melinda Gates Foundation
- Fundação Oswaldo Cruz
- National Institute on Aging
- National Institute of Allergy and Infectious Diseases (P30AI060354)
- Topics
- Social Sciences › Economics, Econometrics and Finance › Economics and Econometrics › Pharmaceutical Economics and Policy
- Social Sciences › Economics, Econometrics and Finance › Economics and Econometrics › HIV/AIDS Impact and Responses
- Health Sciences › Medicine › Infectious Diseases › HIV/AIDS Research and Interventions
- Keywords
- antiretroviral drugs, HIV/AIDS treatment, drug costs, drug expenditure, highly active antiretroviral therapy, generic drugs, patented drugs, compulsory licensing, universal access to treatment, Brazil, tenofovir, lopinavir/ritonavir, efavirenz, fixed-dose combination, cost decomposition, low- and middle-income countries
- MeSH terms
- Acquired Immunodeficiency Syndrome, Brazil, Developing Countries, Foundations, Health Services Accessibility, Humans, National Health Programs, Drug Costs, Drugs, Generic, Cost Savings, Antiretroviral Therapy, Highly Active, Internationality, Anti-Retroviral Agents
About these checks
Registry, retraction, Cites and statistics results are computed, not judged, with one exception: a printed reference that no index lists is read once by a model before it counts as a citation error. Claims are extracted by a model and kept only when their quote appears verbatim in the text; each cited source is then checked, with a model’s help, for whether it says what the claim relies on. Those verdicts can be wrong — read the claim’s quote and the cited source before relying on one.
Statistics and arithmetic are recomputed, not judged.
Confidence bands are shown only for fields calibrated on our annotated test set. None is calibrated yet, so no band is shown.
What counts as a claim ›How we measure confidence ›How we check this ›
Are you an author, or do you see a problem with this page? Request a review
