

The DOI matches its Crossref record; 1 of the 1 references it cites were found in a registry or an index.
Unequal access to opioid agonist treatment and sterile injecting equipment among hospitalized patients with injection drug use-associated infective endocarditis
Abstract
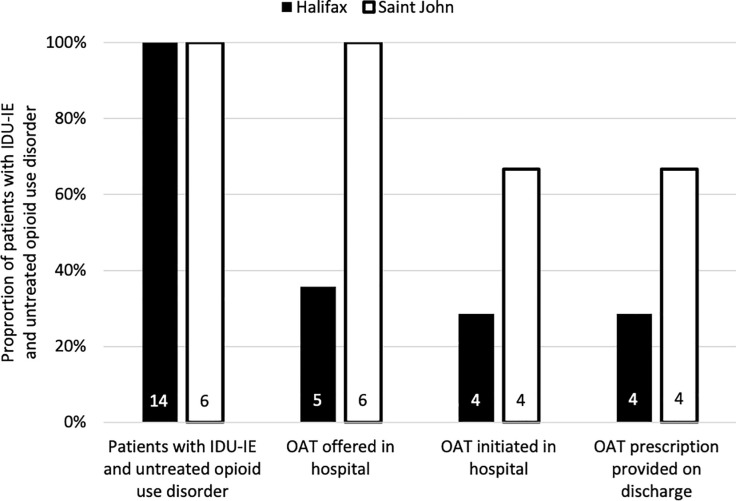
Background: Addiction treatment and harm reduction services reduce risks of death and re-infection among patients with injection drug use-associated infective endocarditis (IDU-IE), but these are not offered at many hospitals. Among hospitalized patients with IDU-IE at the two tertiary-care hospitals in the Canadian Maritimes, we aimed to identify (1) the availability of opioid agonist treatment (OAT) and sterile drug injecting equipment, and (2) indicators of potential unmet addiction care needs. Methods: Retrospective review of IDU-IE hospitalizations at Queen Elizabeth II Health Sciences Centre (Halifax, Nova Scotia) and the Saint John Regional Hospital (Saint John, New Brunswick), October 2015 -March 2017. In Halifax, there are no addiction medicine providers on staff; in Saint John, infectious diseases physicians also practice addiction medicine. Inclusion criteria were: (1) probable or definite IE as defined by the modified Duke criteria; and (2) injection drug use within the prior 3 months. Results: We identified 38 hospitalizations (21 in Halifax and 17 in Saint John), for 30 unique patients. Among patients with IDU-IE and untreated opioid use disorder, OAT was offered to 36% (5/14) of patients in Halifax and 100% (6/6) of patients in Saint John. Once it was offered, most patients at both sites initiated OAT and planned to continue it after discharge. In Halifax, no patients were offered sterile injecting equipment, and during five hospitalizations staff confiscated patients’ own equipment. In Saint John, four patients were offered (and one was provided) injecting equipment in hospital, and during two hospitalizations staff confiscated patients’ own equipment. Concerns regarding undertreated pain or opioid withdrawal were documented during 66% (25/38) of hospitalizations, and in-hospital illicit or non-medical drug use during 32% (12/38). Two patients at each site (11%; 4/38) had self-directed discharges against medical advice. Conclusions: Patients with IDU-IE in the Canadian Maritimes have unequal access to evidence-based addiction care depending on where they are hospitalized, which differs from the community-based standard of care. Indicators of potential unmet addiction care needs in hospital were common.
Overview
The claims and statistics of this paper haven’t been checked yet.
Run the check — free, no account needed. It reads the open-access text and checks the sources it cites.
Integrity signals
Registry
Cites
Statistics
Figures

Verification
Claims the paper makes
The claims and statistics of this paper haven’t been checked yet.
Run the check — free, no account needed. It reads the open-access text and checks the sources it cites.
Claims other papers make about this one
Each is checked against this paper’s own text: does it say what the citing paper says it does?
In the citing paper
“This is represented in low rates of OAT prescribing for these patients in multiple studies from North America [29,31,32] and in qualitative studies from the UK [22].”
In the citing paper
“Suboptimal access to OAT may reflect system-level issues that separate addiction care from specialized, acute medical care for infections [1,22,29,30].”
In the citing paper
“Despite these possible benefits, in many acute care hospitals, OAT is not prioritized as part of treatment planning during and after hospitalization with injecting-related bacterial and fungal infections [22,29–31].”
Self-check
Percentages, sums and reported differences re-computed from the paper’s own numbers.
The self-check needs the paper’s full text.
Citations
Cites
Englander, H., Dobbertin, K., Lind, B. K., Nicolaidis, C., Graven, P., Dorfman, C., & Korthuis, P. T. (2019) · Journal of General Internal Medicine · doi:10.1007/s11606-019-05251-9 · Cited by 234
Research works printed but not linked: 65
- B Jacka, 2020, Prevalence of Injecting Drug Use and Coverage of Interventions to Prevent HIV and Hepatitis C Virus Infection Among People Who Inject Drugs in Canada, Am J Public Health, 110, 45, 10.2105/AJPH.2019.305379 · DOI
- N Coverdale, 2019, Rates of Infective Endocarditis in Substance Use Disorder and Associated Costs in Ontario, Can J Addict, 10, 36, 10.1097/CXA.0000000000000053 · DOI
- MA Weir, 2019, The risk of infective endocarditis among people who inject drugs: a retrospective, population-based time series analysis, CMAJ, 191, E93, 10.1503/cmaj.180694 · DOI
- K Mosseler, 2020, Epidemiology, microbiology, and clinical outcomes among patients with intravenous drug use-associated infective endocarditis in New Brunswick, Can J Cardiol Open, 2, 379
- TD Brothers, 2021, Social and structural determinants of injecting-related bacterial and fungal infections among people who inject drugs: protocol for a mixed studies systematic review, BMJ Open, 11, e049924, 10.1136/bmjopen-2021-049924 · DOI · Paper page
- T Gomes, 2021, Trends in Hospitalizations for Serious Infections Among People With Opioid Use Disorder in Ontario, Canada, J Addict Med.
- TD Brothers, 2021, Caring for people who inject drugs when they are admitted to hospital, CMAJ Can Med Assoc J, 193, E423, 10.1503/cmaj.202124 · DOI · Paper page
- TD Brothers, 2018, Multidisciplinary infective endocarditis care teams should address substance use disorders and harm reduction services, Open Heart, 4
- A Bahji, 2020, Harm Reduction for Injection Drug Users with Infective Endocarditis: A Systematic Review, Can J Addict, 11, 13, 10.1097/CXA.0000000000000080 · DOI
- B Yanagawa, 2018, Endocarditis in the setting of IDU: multidisciplinary management, Curr Opin Cardiol., 33, 140, 10.1097/HCO.0000000000000493 · DOI
- CRISM, 2020, Guidance Document on the Management of Substance Use in Acute Care. Alberta: Canadian Research Initiative on Substance Misuse (CRISM)—Prairie Node
- SD Kimmel, 2020, Association of Treatment With Medications for Opioid Use Disorder With Mortality After Hospitalization for Injection Drug Use–Associated Infective Endocarditis, JAMA Netw Open, 3, e2016228, 10.1001/jamanetworkopen.2020.16228 · DOI · Paper page
- JA Barocas, 2020, Long-term Infective Endocarditis Mortality Associated With Injection Opioid Use in the United States: A Modeling Study, Clin Infect Dis
- JA Barocas, 2021, Outcomes Associated With Medications for Opioid Use Disorder Among Persons Hospitalized for Infective Endocarditis, Clin Infect Dis, 72, 472, 10.1093/cid/ciaa062 · DOI · Paper page
- LR Marks, 2019, Addiction Medicine Consultations Reduce Readmission Rates for Patients With Serious Infections From Opioid Use Disorder, Clin Infect Dis, 68, 1935, 10.1093/cid/ciy924 · DOI
- LR Marks, 2020, A Comparison of Medication for Opioid Use Disorder Treatment Strategies for Persons Who Inject Drugs With Invasive Bacterial and Fungal Infections, J Infect Dis, 222, S513, 10.1093/infdis/jiz516 · DOI
- M Shah, 2020, Risk factors of infective endocarditis in persons who inject drugs, Harm Reduct J, 17, 35, 10.1186/s12954-020-00378-z · DOI
- J Bruneau, 2018, Management of opioid use disorders: a national clinical practice guideline, Can Med Assoc J, 190, E247, 10.1503/cmaj.170958 · DOI
- ES Rosenthal, 2016, Suboptimal Addiction Interventions for Patients Hospitalized with Injection Drug Use-Associated Infective Endocarditis, Am J Med, 129, 481, 10.1016/j.amjmed.2015.09.024 · DOI · Paper page
- Y Jo, 2021, Effect of Initiation of Medications for Opioid Use Disorder on Hospitalization Outcomes for Endocarditis and Osteomyelitis in a Large Private Hospital System in the United States, 2014–2018, Addiction, 116, 2127, 10.1111/add.15393 · DOI
- L Rodger, 2018, Clinical Characteristics and Factors Associated With Mortality in First-Episode Infective Endocarditis Among Persons Who Inject Drugs, JAMA Netw Open, 1, e185220, 10.1001/jamanetworkopen.2018.5220 · DOI
- N Kiepek, 2021, Exploring care of hospital inpatients with substance involvement, Soc Sci Med., 281, 114071, 10.1016/j.socscimed.2021.114071 · DOI
- P Tsybina, 2021, Hospital admissions and mortality due to complications of injection drug use in two hospitals in Regina, Canada: retrospective chart review, Harm Reduct J, 18, 44, 10.1186/s12954-021-00492-6 · DOI
- M. Harris, 2020, Normalised pain and severe health care delay among people who inject drugs in London: Adapting cultural safety principles to promote care, Soc Sci Med, 260, 113183, 10.1016/j.socscimed.2020.113183 · DOI · Paper page
- ZM Weinstein, 2018, Inpatient Addiction Consult Service: Expertise for Hospitalized Patients with Complex Addiction Problems, Med Clin North Am., 102, 587, 10.1016/j.mcna.2018.03.001 · DOI
- TD Brothers, 2020, Implementation and evaluation of a novel, unofficial, trainee-organized hospital addiction medicine consultation service, Subst Abuse, 1
- TKS Christie, 2013, Evaluation of a low-threshold/high-tolerance methadone maintenance treatment clinic in Saint John, New Brunswick, Canada: One year retention rate and illicit drug use, J Addict., 2013, 1, 10.1155/2013/753409 · DOI
- RA Kleinman, 2021, Office-based methadone prescribing for opioid use disorder: The Canadian model, J Addict Med
- JS Li, 2000, Proposed modifications to the Duke Criteria for the diagnosis of infective endocarditis, Clin Infect Dis, 30, 633, 10.1086/313753 · DOI · Paper page
- TD Brothers, 2021, Uptake of slow-release oral morphine as opioid agonist treatment among hospitalised patients with opioid use disorder, Drug Alcohol Rev
- DP Serota, 2017, Treating the symptom but not the underlying disease in infective endocarditis: a teachable moment, JAMA Intern Med, 177, 1026, 10.1001/jamainternmed.2017.1489 · DOI
- E Schleihauf, 2018, Concurrent monitoring of opioid prescribing practices and opioid-related deaths: the context in Nova Scotia, Canada, Health Promot Chronic Dis Prev Can, 38, 334, 10.24095/hpcdp.38.9.05 · DOI
- CW Shanahan, 2010, A Transitional Opioid Program to Engage Hospitalized Drug Users, J Gen Intern Med, 25, 803, 10.1007/s11606-010-1311-3 · DOI
- A Bahji, 2020, The Substance Treatment and Recovery Team (START): Measuring the effectiveness and feasibility of an inpatient addiction consult service at an academic general hospital, Gen Hosp Psychiatry, 67, 160, 10.1016/j.genhosppsych.2020.05.009 · DOI
- JM Liebschutz, 2014, Buprenorphine Treatment for Hospitalized, Opioid-Dependent Patients: A Randomized Clinical Trial, JAMA Intern Med, 174, 1369, 10.1001/jamainternmed.2014.2556 · DOI
- D Lewer, Fatal opioid overdoses during and shortly after hospital admissions in England: case-crossover study, PLOS Med., 18, e1003759, 10.1371/journal.pmed.1003759 · DOI
- M Sharma, 2017, Harm reduction in hospitals, Harm Reduct J, 14, 32, 10.1186/s12954-017-0163-0 · DOI
- B Bearnot, 2019, Experiences of care among individuals with opioid use disorder-associated endocarditis and their healthcare providers: Results from a qualitative study, J Subst Abuse Treat, 102, 16, 10.1016/j.jsat.2019.04.008 · DOI
- K Thakarar, 2019, Mortality, morbidity, and cardiac surgery in Injection Drug Use (IDU)-associated versus non-IDU infective endocarditis: The need to expand substance use disorder treatment and harm reduction services, PLOS ONE, 14, e0225460, 10.1371/journal.pone.0225460 · DOI
- MJ Nguemeni Tiako, 2020, Inconsistent addiction treatment for patients undergoing cardiac surgery for injection drug use-associated infective endocarditis, J Addict Med, 14, e350, 10.1097/ADM.0000000000000710 · DOI · Paper page
- AB Rapoport, 2017, Stretching the Scope—Becoming Frontline Addiction-Medicine Providers, N Engl J Med, 377, 705, 10.1056/NEJMp1706492 · DOI
- DP Serota, Harm reduction for the treatment of patients with severe injection-related infections: description of the Jackson SIRI Team, Ann Med, 53, 1960, 10.1080/07853890.2021.1993326 · DOI
- P Trowbridge, 2017, Addiction consultation services–Linking hospitalized patients to outpatient addiction treatment, J Subst Abuse Treat, 79, 1, 10.1016/j.jsat.2017.05.007 · DOI
- A Pecoraro, 2012, Early data from project engage: a program to identify and transition medically hospitalized patients into addictions treatment, Addict Sci Clin Pract, 7, 20, 10.1186/1940-0640-7-20 · DOI
- V Braithwaite, 2021, Building a hospital-based addiction medicine consult service in Vancouver, Canada: the path taken and lessons learned, Addiction, 116, 1892, 10.1111/add.15383 · DOI
- R Lennox, 2021, The Second Heart Program—A multidisciplinary team supporting people who inject drugs with infective endocarditis: Protocol of a feasibility study, PLoS ONE, 16, e0256839, 10.1371/journal.pone.0256839 · DOI
- MB Weimer, 2021, The Need for Multidisciplinary Hospital Teams for Injection Drug Use-Related Infective Endocarditis, J Addict Med.
- KC Priest, 2020, Expanding Access to Medications for Opioid Use Disorder: Program and Policy Approaches from Outside the Veterans Health Administration, J Gen Intern Med, 35, 886, 10.1007/s11606-020-06266-3 · DOI
- R McNeil, 2016, Advancing patient-centered care for structurally vulnerable drug-using populations: a qualitative study of the perspectives of people who use drugs regarding the potential integration of harm reduction interventions into hospitals: Hospital-based harm reduction, Addiction, 111, 685, 10.1111/add.13214 · DOI
- E Hyshka, 2019, Patient perspectives on a harm reduction-oriented addiction medicine consultation team implemented in a large acute care hospital, Drug Alcohol Depend, 204, 107523, 10.1016/j.drugalcdep.2019.06.025 · DOI
- HL Brooks, 2019, Uptake into a bedside needle and syringe program for acute care inpatients who inject drugs, Drug Alcohol Rev, 38, 423, 10.1111/dar.12930 · DOI
- R Lennox, 2021, Hospital policy as a harm reduction intervention for people who use drugs, Int J Drug Policy, 97, 103324, 10.1016/j.drugpo.2021.103324 · DOI
- L Fanucchi, 2016, Putting Parity into Practice—Integrating Opioid-Use Disorder Treatment into the Hospital Setting, N Engl J Med, 375, 811, 10.1056/NEJMp1606157 · DOI
- TY Yong, 2013, Characteristics and outcomes of discharges against medical advice among hospitalised patients, Intern Med J, 43, 798, 10.1111/imj.12109 · DOI
- B Pauly, 2015, Toward Cultural Safety: Nurse and Patient Perceptions of Illicit Substance Use in a Hospitalized Setting, Adv Nurs Sci., 38, 121, 10.1097/ANS.0000000000000070 · DOI
- CM Velez, 2017, “It’s been an Experience, a Life Learning Experience”: A Qualitative Study of Hospitalized Patients with Substance Use Disorders, J Gen Intern Med, 32, 296, 10.1007/s11606-016-3919-4 · DOI
- S Chan Carusone, 2019, “Maybe if I stop the drugs, then maybe they’d care?”—hospital care experiences of people who use drugs, Harm Reduct J, 16, 16, 10.1186/s12954-019-0285-7 · DOI
- R McNeil, 2014, Hospitals as a “risk environment”: An ethno-epidemiological study of voluntary and involuntary discharge from hospital against medical advice among people who inject drugs, Soc Sci Med, 105, 59, 10.1016/j.socscimed.2014.01.010 · DOI · Paper page
- C Strike, 2020, Illicit drug use while admitted to hospital: Patient and health care provider perspectives, PLOS ONE, 15, e0229713, 10.1371/journal.pone.0229713 · DOI
- S. vanKampen, 2016, Nova Scotia doctors told to dramatically reduce opioid prescriptions, CBC
- Unsigned, 2020, Nova Scotia Drug Report, Nova Scotia Department of Health and Wellness, 4
- M Silverman, 2020, Hydromorphone and the risk of infective endocarditis among people who inject drugs: a population-based, retrospective cohort study, Lancet Infect Dis, 0
- S Larney, 2017, A systematic review of injecting-related injury and disease among people who inject drugs, Drug Alcohol Depend, 171, 39, 10.1016/j.drugalcdep.2016.11.029 · DOI · Paper page
- M Bonn, 2020, Addressing the Syndemic of HIV, Hepatitis C, Overdose, and COVID-19 Among People Who Use Drugs: The Potential Roles for Decriminalization and Safe Supply, J Stud Alcohol Drugs, 81, 556, 10.15288/jsad.2020.81.556 · DOI · Paper page
- Canadian Association of People Who Use Drugs (CAPUD), 2019, Safe Supply Concept Document
Cited by
Sorted by citations
Brothers, T. D., Lewer, D., Jones, N., Colledge-Frisby, S., Farrell, M., Hickman, M., Webster, D., Hayward, A., & Degenhardt, L. (2022) · PLOS Medicine · doi:10.1371/journal.pmed.1004049 · Cited by 25
Self-citation
Metadata
- Authors
- Brothers, T. D., Mosseler, K., Kirkland, S., Melanson, P., Barrett, L., & Webster, D.
- ORCID
- Brothers, Thomas D.
- Venue
- PLOS ONE
- Publisher
- Public Library of Science (PLoS)
- Published
- 2022-01-26
- Volume
- 17
- Issue
- 1
- Pages
- e0263156
- ISSN
- 1932-6203
- PMC
- PMC8791472
- Cited by
- 17
- References
- 1
- Language
- en
- Funders
- Canadian Institutes of Health Research (CIHR-FRN# 171259)
- Dalhousie University Internal Medicine Research Foundation (Internal Fellowship)
- National Institute on Drug Abuse (R25DA033211)
- Faculty of Medicine, Dalhousie University (Ross Stewart Smith Memorial Fellowship in Medical Research)
- Canadian Society of Internal Medicine (Hui Lee Health Promotion Scholarship)
- Dalhousie Medical Research Foundation (Katelyn Robarts Studentship)
About these checks
Registry, retraction, Cites and statistics results are computed, not judged, with one exception: a printed reference that no index lists is read once by a model before it counts as a citation error. Claims are extracted by a model and kept only when their quote appears verbatim in the text; each cited source is then checked, with a model’s help, for whether it says what the claim relies on. Those verdicts can be wrong — read the claim’s quote and the cited source before relying on one.
Statistics and arithmetic are recomputed, not judged.
Confidence bands are shown only for fields calibrated on our annotated test set. None is calibrated yet, so no band is shown.
What counts as a claim ›How we measure confidence ›How we check this ›
Are you an author, or do you see a problem with this page? Request a review
