

The DOI matches its Crossref record; 41 of the 43 references it cites were found in a registry or an index.
Categorization of Fetal Heart Rate Decelerations in American and European Practice: Importance and Imperative of Avoiding Framing and Confirmation Biases
Open accessAbstract
Interpretation of electronic fetal monitoring (EFM) remains controversial and unsatisfactory. Fetal heart rate (FHR) decelerations are the commonest aberrant feature on cardiotocographs and considered "center-stage" in the interpretation of EFM. A recent American study suggested that the lack of correlation of American three-tier system to neonatal acidemia may be due to the current peculiar nomenclature of FHR decelerations leading to loss of meaning. The pioneers like Hon and Caldeyro-Barcia classified decelerations based primarily on time relationship to contractions and not on etiology per se. This critical analysis debates pros and cons of significant anchoring/framing and confirmation biases in defining different types of decelerations based primarily on the shape (slope) or time of descent. It would be important to identify benign early decelerations correctly to avoid unnecessary intervention as well as to improve the positive predictive value of the other types of decelerations. Currently the vast majority of decelerations are classed as "variable". This review shows that the most common rapid decelerations during contractions with trough corresponding to peak of contraction cannot be explained by "cord-compression" hypothesis but by direct/pure (defined here as not mediated through baro-/chemoreceptors) or non-hypoxic vagal reflex. These decelerations are benign, most likely and mainly a result of head-compression and hence should be called "early" rather than "variable". Standardization is important but should be appropriate and withstand scientific scrutiny. Significant framing and confirmation biases are necessarily unscientific and the succeeding three-tier interpretation systems and structures embodying these biases would be dysfunctional and clinically unhelpful. Clinical/pathophysiological analysis and avoidance of flaws/biases suggest that a more physiological and scientific categorization of decelerations should be based on time relationship to contractions alone irrespective of shape or descent time as indeed proposed by pioneers like Hon and Caldeyro-Barcia. Such meaningful categorization, apart from being a scientific necessity, could improve the practical performance of three-tier FHR interpretation systems and possibly application of dependent complementary techniques like fetal ECG/pulse oximetry/computer-aided analysis, thus facilitating future progress in the field of intrapartum fetal monitoring.
Overview
The claims and statistics of this paper haven’t been checked yet.
Run the check — free, no account needed. It reads the open-access text and checks the sources it cites.
Integrity signals
Registry
Cites
Statistics
Figures
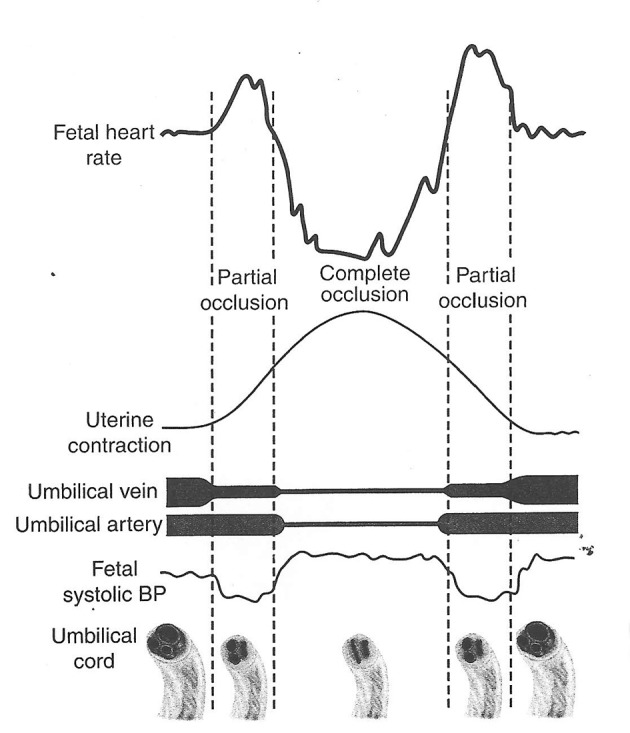
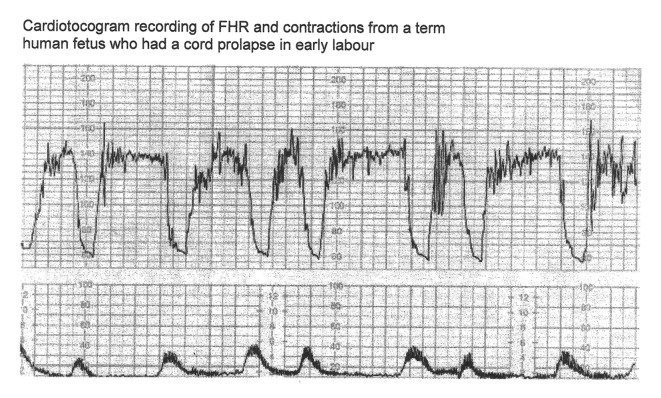
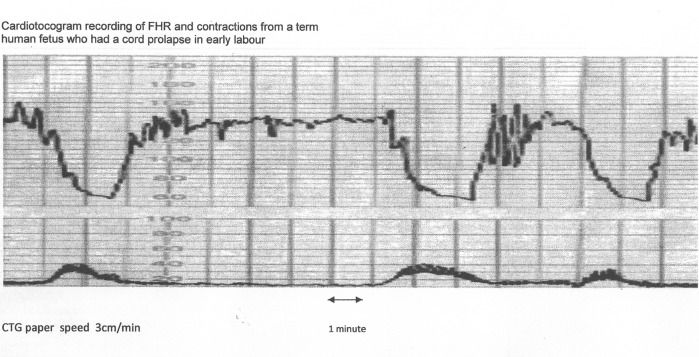
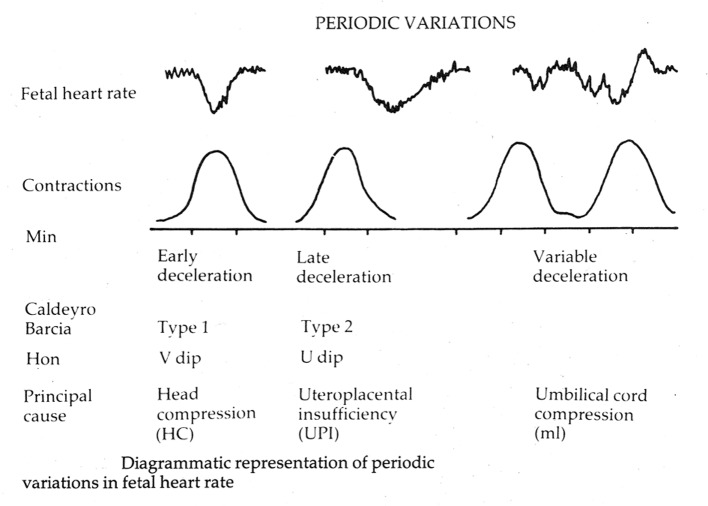
Verification
Claims the paper makes
The claims and statistics of this paper haven’t been checked yet.
Run the check — free, no account needed. It reads the open-access text and checks the sources it cites.
Claims other papers make about this one
Each is checked against this paper’s own text: does it say what the citing paper says it does?
The check wasn’t confident either way, so it gives no verdict — never disputed.
In the citing paper
“Moreover, the preterm newborns with frequent bradycardia, who were at high risk for serious complications, reliably had low amplitude RSA (i.e., heart rate patterns with a relatively constant beat-to-beat rate) prior to a bradycardic event [[19], [20], [21]].”
From The vagal paradox: A polyvagal solution (2023) · cites this paper as [21]
Experimental — accuracy not yet measured
Self-check
Percentages, sums and reported differences re-computed from the paper’s own numbers.
The self-check needs the paper’s full text.
Citations
Cites
Confirmation Bias: A Ubiquitous Phenomenon in Many Guises
Nickerson, R. S. (1998) · Review of General Psychology · doi:10.1037/1089-2680.2.2.175 · Cited by 7,267
Evidence based medicine: a movement in crisis?
Greenhalgh, T., Howick, J., Maskrey, N., & for the Evidence Based Medicine Renaissance Group (2014) · BMJ · doi:10.1136/bmj.g3725 · Cited by 1,921
(2009) · Obstetrics and Gynecology · doi:10.1097/aog.0b013e3181aef106 · Cited by 908
Electronic fetal heart rate monitoring: Research guidelines for interpretation
Parer, J. T. (1997) · American Journal of Obstetrics and Gynecology · doi:10.1016/s0002-9378(97)70079-6 · Cited by 458
Nageotte, M. P. (2007) · Humana Press eBooks · doi:10.1007/978-1-59745-142-0_26 · Cited by 243
Untersuchungen über die Reihe .
Heine, E. (1847) · Journal für die reine und angewandte Mathematik (Crelles Journal) · doi:10.1515/crll.1847.34.285 · Cited by 207
Aviado, D. M., & AVIADO, D. G. (2001) · Annals of the New York Academy of Sciences · doi:10.1111/j.1749-6632.2001.tb03666.x · Cited by 204
The electronic evaluation of fetal heart rate
Hon, E. H., & Wohlgemuth, R. (1961) · American Journal of Obstetrics and Gynecology · doi:10.1016/s0002-9378(16)36378-5 · Cited by 200
Association and prediction of neonatal acidemia
Cahill, A. G., Roehl, K. A., Odibo, A. O., & Macones, G. A. (2012) · American Journal of Obstetrics and Gynecology · doi:10.1016/j.ajog.2012.06.046 · Cited by 194
The electronic evaluation of the fetal heart rate
Hon, E. H. (1958) · American Journal of Obstetrics and Gynecology · doi:10.1016/0002-9378(58)90707-5 · Cited by 193
Research works printed but not linked: 1
- [24]Royal College of Obstetricians and Gynaecologists. Clinical Effectiveness Support Unit. The use of electronic fetal monitoring. The use and interpretation of cardiotocography in intrapartum fetal surveillance Evidence based Clinical Guideline No 8. 2001. London (UK), RCOG Press
Cited by
The vagal paradox: A polyvagal solution
Porges, S. W. (2023) · Comprehensive Psychoneuroendocrinology · doi:10.1016/j.cpnec.2023.100200 · Cited by 52
“Moreover, the preterm newborns with frequent bradycardia, who were at high risk for serious complications, reliably had low amplitude RSA (i.e., heart rate patterns with a relatively constant beat-to-beat rate) prior to a bradycardic event [19 – 21].”
BackgroundA machine learning pipeline to classify foetal heart rate deceleration with optimal feature set
Das, S., Obaidullah, S. M., Mahmud, M., Kaiser, M. S., Roy, K., Saha, C. K., & Goswami, K. (2023) · Scientific Reports · doi:10.1038/s41598-023-27707-z · Cited by 22
Sholapurkar, S. L. (2017) · Journal of Clinical Medicine Research · doi:10.14740/jocmr2877e · Cited by 21
Self-citationSbrollini, A., Carnicelli, A., Massacci, A., Tomaiuolo, L., Zara, T., Marcantoni, I., Burattini, L., Morettini, M., Fioretti, S., & Burattini, L. (2018) · Annual International Conference of the IEEE Engineering in Medicine and Biology Society (EMBC) · doi:10.1109/embc.2018.8512432 · Cited by 16
Neurological Fallacies Leading to Malpractice
Johnston, J. C., Wester, K. G., & Sartwelle, T. P. (2016) · Neurologic Clinics · doi:10.1016/j.ncl.2016.04.011 · Cited by 7
Goel, A., Sonowal, I. B., Saxena, V. K., & Bhukya, R. K. (2024) · International Conference for Emerging Technology (INCET) · doi:10.1109/incet61516.2024.10592910 · Cited by 6
Sholapurkar, S. L. (2020) · The Journal of Maternal-Fetal & Neonatal Medicine · doi:10.1080/14767058.2020.1759537 · Cited by 4
Self-citationSholapurkar, S. L. (2018) · Journal of Clinical Medicine Research · doi:10.14740/jocmr3307e · Cited by 3
Self-citationGimovsky, A. C., Whitney, B., WOOD, D. C., & Weiner, S. (2017) · The Journal of Maternal-Fetal & Neonatal Medicine · doi:10.1080/14767058.2017.1399119 · Cited by 2
Fetal Cerebral Monitoring During the Second Stage of Labor
Năstase, L., Luminos, M. L., Jugulete, G., Merişescu, M. M., & Stoicescu, S. M. (2018) · Revista de Chimie · doi:10.37358/rc.18.11.6685 · Cited by 2
Sholapurkar, S. L. (2016) · American Journal of Obstetrics and Gynecology · doi:10.1016/j.ajog.2016.09.092 · Cited by 2
Self-citationLimits of current cardiotocography interpretation call for a major rethink
Sholapurkar, S. L. (2017) · American Journal of Obstetrics and Gynecology · doi:10.1016/j.ajog.2017.02.048 · Cited by 2
Self-citationTrace display Doppler monitors
Sholapurkar, S. L. (2017) · British Journal of Midwifery · doi:10.12968/bjom.2017.25.5.282 · Cited by 2
Self-citationSholapurkar, S. L. (2017) · The Journal of Physiology · doi:10.1113/jp274478 · Cited by 2
Self-citationFranco, L. C., Buitrago, S. M., Arbelaez, I., Pinto, L. F., BLANCO, A. E. D., Pizarro-Peñaranda, M. C., Santamaria, L., & Trillos, C. (2024) · Journal of Pregnancy · doi:10.1155/2024/9779831 · Cited by 1
Feng, S., & Gu, J. (2022) · BMC Pregnancy and Childbirth · doi:10.1186/s12884-022-05197-7 · Cited by 1
Sholapurkar, S. L. (2016) · The Journal of Maternal-Fetal & Neonatal Medicine · doi:10.1080/14767058.2016.1247801
Self-citationRe: Time to optimise and enforce training in interpretation of intrapartum cardiotocograph
Sholapurkar, S. L. (2016) · BJOG An International Journal of Obstetrics & Gynaecology · doi:10.1111/1471-0528.14402
Self-citationKodali, B. S., & Segal, S. (2023) · Springer eBooks · doi:10.1007/978-3-031-41893-8_11
Metadata
- Authors
- Sholapurkar, S. L.
- Affiliations
- Royal United Hospital (GB)
- Corresponding author
- Sholapurkar, Shashikant L.
- Venue
- Journal of Clinical Medicine Research
- Publisher
- Elmer Press, Inc.
- Published
- 2015
- Volume
- 7
- Issue
- 9
- Pages
- 672-680
- ISSN
- 1918-3003 (ISSN-L)
- 1918-3011
- PMC
- PMC4522983
- OpenAlex
- W1796605382
- Cited by
- 19
- References
- 43
- Citations by year
- 2024: 2 · 2023: 3 · 2022: 1 · 2020: 1 · 2018: 3 · 2017: 5 · 2016: 4
- FWCI
- 0.59
- Type
- journal article
- Language
- en
- Open access
- diamond
- doi.org
- Licence
- cc-by-nc
- Locations
- Journal of Clinical Medicine Research (publishedVersion, cc-by-nc)
- Europe PMC (PubMed Central) (publishedVersion, cc-by)
- PubMed Central (publishedVersion, cc-by)
- PubMed (publishedVersion)
- Topics
- Health Sciences › Medicine › Obstetrics and Gynecology › Maternal and Perinatal Health Interventions
- Health Sciences › Medicine › Pediatrics, Perinatology and Child Health › Neonatal and fetal brain pathology
- Health Sciences › Medicine › Cardiology and Cardiovascular Medicine › Heart Rate Variability and Autonomic Control
- Keywords
- fetal heart rate decelerations, fetal heart rate monitoring, framing bias, confirmation bias, anchoring effect, variable decelerations, vagal reflex, intrapartum fetal monitoring, neonatal acidemia, terminology standardization
About these checks
Registry, retraction, Cites and statistics results are computed, not judged, with one exception: a printed reference that no index lists is read once by a model before it counts as a citation error. Claims are extracted by a model and kept only when their quote appears verbatim in the text; each cited source is then checked, with a model’s help, for whether it says what the claim relies on. Those verdicts can be wrong — read the claim’s quote and the cited source before relying on one.
Statistics and arithmetic are recomputed, not judged.
Confidence bands are shown only for fields calibrated on our annotated test set. None is calibrated yet, so no band is shown.
What counts as a claim ›How we measure confidence ›How we check this ›
Are you an author, or do you see a problem with this page? Request a review
Data sources
Bibliographic data: Semantic Scholar, OpenAlex, Crossref.
Contains information from the Semantic Scholar Academic Graph Datasets, made available under the ODC Attribution License (ODC-BY 1.0).
Semantic Scholar’s data is described in: Kinney, R., et al. (2023). The Semantic Scholar Open Data Platform. arXiv:2301.10140.
