

The DOI matches its Crossref record; 33 of the 33 references it cites were found in a registry or an index.
Meta-analysis to compare the safety and efficacy of manual small incision cataract surgery and phacoemulsification
Open accessAbstract
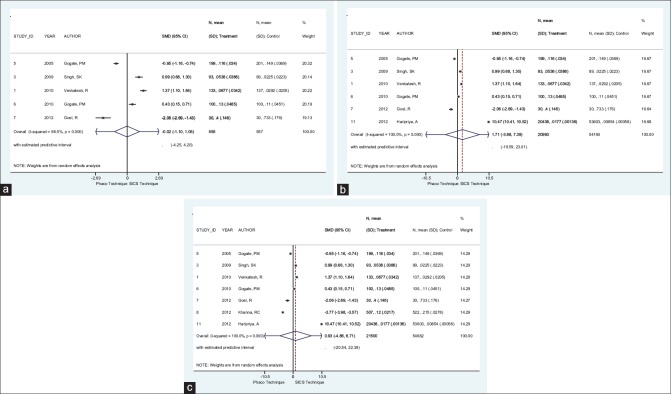
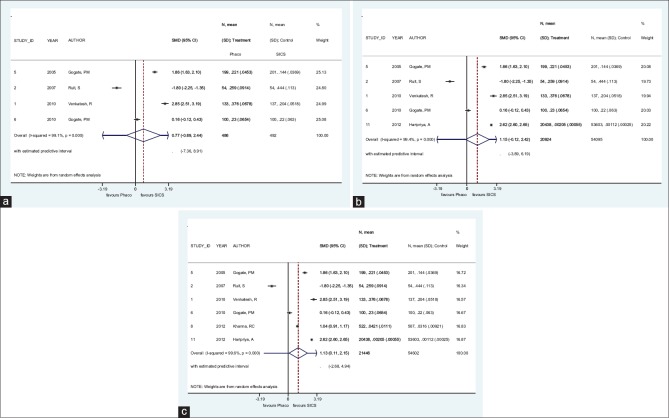
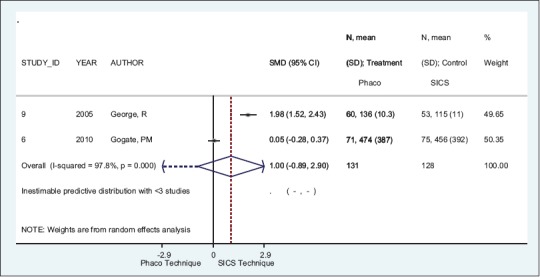
PURPOSE: A systematic review and meta-analysis comparing the safety, efficacy, and expenses related to phacoemulsification versus manual small incision cataract surgery (SICS). METHODS: PubMed, Cochrane, and Scopus databases were searched with key words manual SICS 6/18 and 6/60; astigmatism and endothelial cell loss postoperatively, intra- and post-operative complications, phacoemulsification, and comparison of SICS and phacoemulsification. Non-English language manuscripts and manuscripts not indexed in the three databases were also search for comparison of SICS with phacoemulsification. Data were compared between techniques for postoperative uncorrected and corrected distance visual acuity (UCVA and best corrected visual acuity [BCVA], respectively) better than 6/9, surgical cost and duration of surgery. The Oxford cataract treatment and evaluation team scores were used for grading intraoperative and postoperative complications, uncorrected near vision. RESULT: This review analyzed, 11 comparative studies documenting 76,838 eyes that had undergone cataract surgery considered for analysis. UCVA of 6/18 UCVA and 6/18 BCVA were comparable between techniques (P = 0.373 and P = 0.567, respectively). BCVA of 6/9 was comparable between techniques (P = 0.685). UCVA of 6/60 and 6/60 BCVA aided and unaided vision were comparable (P = 0.126 and P = 0.317, respectively). There was no statistical difference in: Endothelial cell loss during surgery (P = 0.298), intraoperative (P = 0.964) complications, and postoperative complications (P = 0.362). The phacoemulsification group had statistically significantly less astigmatism (P = 0.005) and more eyes with UCVA of 6/9 (P = 0.040). UCVA at near was statistically significantly better with SICS due to astigmatism and safer during the learning phase (P = 0.003). The average time for SICS was lower than phacoemulsification and cost <½ of phacoemulsification. CONCLUSION: The outcome of this meta-analysis indicated there is no difference between phacoemulsification and SICS for BCVA and UCVA of 6/18 and 6/60. Endothelial cell loss and intraoperative and postoperative complications were similar between procedures. SICS resulted in statistically greater astigmatism and UCVA of 6/9 or worse, however, near UCVA was better.
Overview
The claims and statistics of this paper haven’t been checked yet.
Run the check — free, no account needed. It reads the open-access text and checks the sources it cites.
Integrity signals
Registry
Cites
Statistics
Figures
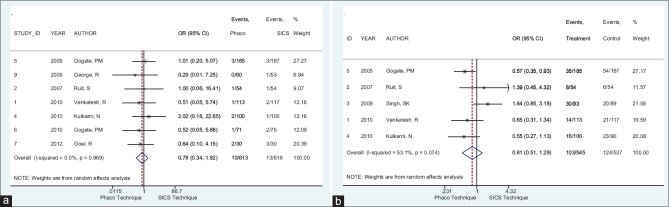
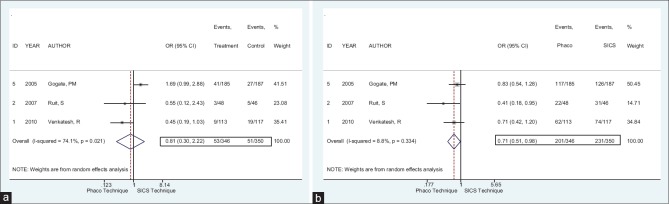
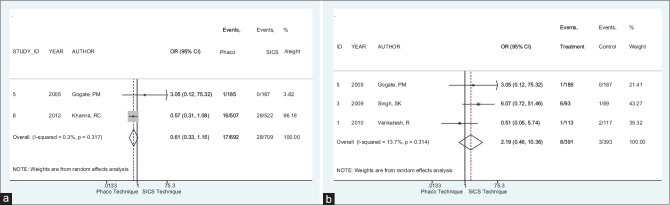
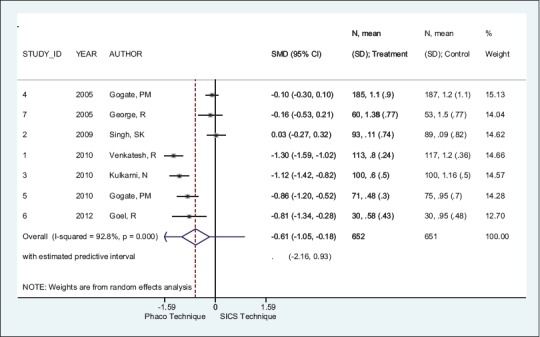
Verification
Claims the paper makes
The claims and statistics of this paper haven’t been checked yet.
Run the check — free, no account needed. It reads the open-access text and checks the sources it cites.
Claims other papers make about this one
Each is checked against this paper’s own text: does it say what the citing paper says it does?
The cited source says what the claim attributes to it.
In the citing paper
“Though the sample sizes are small, there were minimal differences in the price of supplies between phaco and MSICS approaches, which goes against published evidence of the cost efficiency of MSICS versus phaco.”
Self-check
Percentages, sums and reported differences re-computed from the paper’s own numbers.
The self-check needs the paper’s full text.
Citations
Cites
Assessing the quality of reports of randomized clinical trials: Is blinding necessary?
Jadad, A. R., Moore, R. A., Carroll, D., Jenkinson, C., Reynolds, D. J. M., Gavaghan, D. J., & McQuay, H. J. (1996) · Controlled Clinical Trials · doi:10.1016/0197-2456(95)00134-4 · Cited by 17,582
Operating characteristics of a rank correlation test for publication bias
Begg, C. B., & Mazumdar, M. (1994) · Biometrics · doi:10.2307/2533446 · Cited by 16,955
Zhang, Q., Wang, C., Zheng, M., Li, Y., Li, J., Zhang, L., Shang, X., & Yan, C. (2014) · Cerebrovascular Diseases · doi:10.1159/000369778 · Cited by 11,609
Dong, Y., Hao, L., Shi, Z., Wang, G., Zhang, Z., & Han, C. (2013) · Urologia Internationalis · doi:10.1159/000351405 · Cited by 4,557
Global estimates of visual impairment: 2010
Pascolini, D., & Mariotti, S. P. (2011) · British Journal of Ophthalmology · doi:10.1136/bjophthalmol-2011-300539 · Cited by 3,864
Ruit, S., Tabin, G. C., Chang, D. F., Bajracharya, L., Kline, D. C., Richheimer, W., Shrestha, M. K., & Paudyal, G. (2006) · American Journal of Ophthalmology · doi:10.1016/j.ajo.2006.07.023 · Cited by 301
GOGATE, P., KULKARNI, S., Krishnaiah, S., DESHPANDE, R., JOSHI, S., Palimkar, A., & DESHPANDE, M. (2005) · Ophthalmology · doi:10.1016/j.ophtha.2004.11.055 · Cited by 252
Haripriya, A., Chang, D. F., Reena, M., & Shekhar, M. (2012) · Journal of Cataract & Refractive Surgery · doi:10.1016/j.jcrs.2012.04.025 · Cited by 186
Gogate, P., Deshpande, M., & Nirmalan, P. K. (2007) · Ophthalmology · doi:10.1016/j.ophtha.2006.08.057 · Cited by 156
Phacoemulsification versus manual small-incision cataract surgery for white cataract
Venkatesh, R., Tan, C. S., Sengupta, S., Ravindran, R. D., Krishnan, K. T., & Chang, D. F. (2010) · Journal of Cataract & Refractive Surgery · doi:10.1016/j.jcrs.2010.05.025 · Cited by 156
Research works printed but not linked: 4
- Use, 1986, Oxford Cataract Treatment and Evaluation Team (OCTET), Br J Ophthalmol, 411
- Kulkarni AN, Bhomaj P, Badhe G. Manual Small Incision Cataract Surgery is Almost as Effective but Less Expensive than Phacoemulsification. Proceedings of the 73 rd Annual Conference of the All India Ophthalmology Society 2010 at Kolkata, Cataract Session IV; 2010. p. 146-8.
- Venkatesh, 2012, Manual small incision cataract surgery: A review, Asia Pac J Ophthalmol, 113
- Gogate, 2011, Monitoring and modernization improves the outcome of cataract surgery in Maharashtra, India, J Cataract Refract Surg, 328
Cited by
Sorted by citations
The Lancet Global Health Commission on Global Eye Health: vision beyond 2020
Burton, M. J., Ramke, J., Marques, A. P., Bourne, R. R. A., Congdon, N., Jones, I., Ah Tong, B. A. M., Arunga, S., Bachani, D., Bascaran, C., et al. (2021) · The Lancet Global Health · doi:10.1016/s2214-109x(20)30488-5 · Cited by 1,624
Endophthalmitis after Cataract Surgery in the United States
Pershing, S., Lum, F., Hsu, S., Kelly, S., Chiang, M. F., Rich, W. L., & Parke, D. W. (2019) · Ophthalmology · doi:10.1016/j.ophtha.2019.08.026 · Cited by 171
Preoperative optimization of ocular surface disease before cataract surgery
Chuang, J. C., Shih, K. C., Chan, T. C. Y., Wan, K. H.-N., Jhanji, V., & Tong, L. H. T. (2017) · Journal of Cataract & Refractive Surgery · doi:10.1016/j.jcrs.2017.10.033 · Cited by 70
Risk factors for fluctuations in corneal endothelial cell density (Review)
Vaičiulienė, R., Rylskytė, N., Bagužytė, G., & Jašinskas, V. (2021) · Experimental and Therapeutic Medicine · doi:10.3892/etm.2021.11052 · Cited by 66
Goel, H., Wemyss, T. A., Harris, T., Steinbach, I., Stancliffe, R., Cassels-Brown, A., Thomas, P. B. M., & Thiel, C. L. (2021) · BMJ Open Ophthalmology · doi:10.1136/bmjophth-2020-000642 · Cited by 57
Metadata
- Authors
- Gogate, P., Optom, J. J., Deshpande, S., & Naidoo, K.
- Affiliations
- Brien Holden Vision Institute (AU)
- Corresponding author
- Gogate, Parikshit
- Venue
- Middle East African Journal of Ophthalmology
- Published
- 2015
- Volume
- 22
- Issue
- 3
- Pages
- 362
- ISSN
- 0974-9233 (ISSN-L)
- PMC
- PMC4502183
- OpenAlex
- W2168894369
- Cited by
- 106
- References
- 33
- Citations by year
- 2026: 2 · 2025: 8 · 2024: 8 · 2023: 12 · 2022: 20 · 2021: 12 · 2020: 11 · 2019: 14 · 2018: 9 · 2017: 5 · 2016: 4 · 2015: 1
- FWCI
- 6.08
- Type
- journal article
- Language
- en
- Open access
- green
- www.ncbi.nlm.nih.gov
- Licence
- cc-by-nc-sa
- Locations
- Middle East African Journal of Ophthalmology (publishedVersion)
- PubMed Central (publishedVersion, cc-by-nc-sa)
- PubMed (publishedVersion)
- Topics
- Health Sciences › Medicine › Ophthalmology › Intraocular Surgery and Lenses
- Health Sciences › Medicine › Ophthalmology › Retinal and Macular Surgery
- Health Sciences › Medicine › Ophthalmology › Corneal surgery and disorders
- Keywords
- cataract surgery, phacoemulsification, manual small incision cataract surgery, visual acuity outcomes, astigmatism, endothelial cell loss, intraoperative complications, postoperative complications, surgical costs, learning curve, operative time
- MeSH terms
- Astigmatism, Biometry, Cataract Extraction, Humans, Intraoperative Complications, Male, Microsurgery, Postoperative Complications, Visual Acuity, Phacoemulsification, Corneal Endothelial Cell Loss
About these checks
Registry, retraction, Cites and statistics results are computed, not judged, with one exception: a printed reference that no index lists is read once by a model before it counts as a citation error. Claims are extracted by a model and kept only when their quote appears verbatim in the text; each cited source is then checked, with a model’s help, for whether it says what the claim relies on. Those verdicts can be wrong — read the claim’s quote and the cited source before relying on one.
Statistics and arithmetic are recomputed, not judged.
Confidence bands are shown only for fields calibrated on our annotated test set. None is calibrated yet, so no band is shown.
What counts as a claim ›How we measure confidence ›How we check this ›
Are you an author, or do you see a problem with this page? Request a review
