

The DOI matches its Crossref record; 43 of the 43 references it cites were found in a registry or an index; none of the 111 sources its claims cite is checked for support yet.
Distinguishing between post-trauma pituitary stalk disruption and genetic pituitary stalk interruption syndrome – case presentation and literature overview
Open accessAbstract
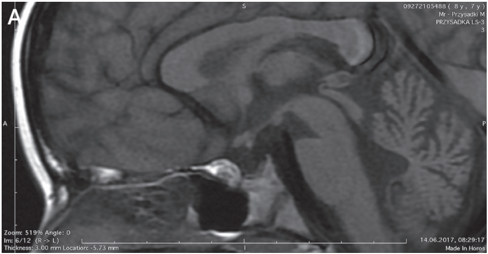
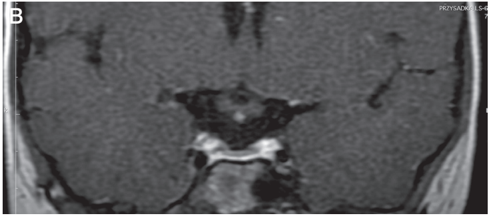
INTRODUCTION: The diagnosis of post-trauma pituitary stalk transection, which is often life-threatening condition, is frequently delayed. In medical litera-ture still exist conflicting data concerning distinguishing this pathology with genetic developmental pituitary stalk interruption syndrome (PSIS). CASE PRESENTATION: We present a case of patient with post-trauma pituitary stalk transection resulting in combined life-threatening pituitary hormone defi-ciency (CPHD) and typical MRI picture: atrophic not visible stalk and posterior pituitary and hypotrophic anterior pituitary with most typical for this disorders hyperintense signal of distal regenerating axon of hypothalamus (pseudo posterior lobe) at median eminence with not visible posterior pituitary. This latter finding is often confused with ectopic posterior lobe in genetically determined PSIS. CONCLUSIONS: MRI image together with medical history of the head trauma and its strict temporal relation with transient diabetes insipidus and the occurrence of CPHD signs, as well as the lack of extrapituitary midline defects differentiate posttraumatic pituitary stalk transection syndrome (PSTS) from genetic PSIS. In every case of severe traumatic head injury hormonal evaluation and MRI of hypothalamic-pituitary axis should be performed.
Overview
CoChat Summary
TL;DR
This case report and literature overview contrasts post-traumatic pituitary stalk transection syndrome (PSTS) with genetic pituitary stalk interruption syndrome (PSIS), which can look similar clinically and on MRI but differ in etiology, midline anomalies, and temporal relation to trauma. It presents a 7-year-10-month-old girl with post-traumatic combined pituitary hormone deficiency and MRI findings of absent stalk with a hyperintense distal hypothalamic axon stump (pseudo-posterior lobe), illustrating PSTS rather than PSIS.
Key findings
- PSTS and PSIS can both present with combined pituitary hormone deficiency (CPHD) and MRI findings of absent pituitary stalk and small anterior pituitary, but PSIS is caused by developmental hypoplasia/aplasia, often genetic, while PSTS follows regenerative and regressive changes after trauma. The paper reports PSIS prevalence of approximately 1 per 6000 births, and notes that pituitary stalk transection can be found in about 4% of pediatric traumatic brain injury cases (with pediatric TBI occurrence about 200–235 per 100 000).
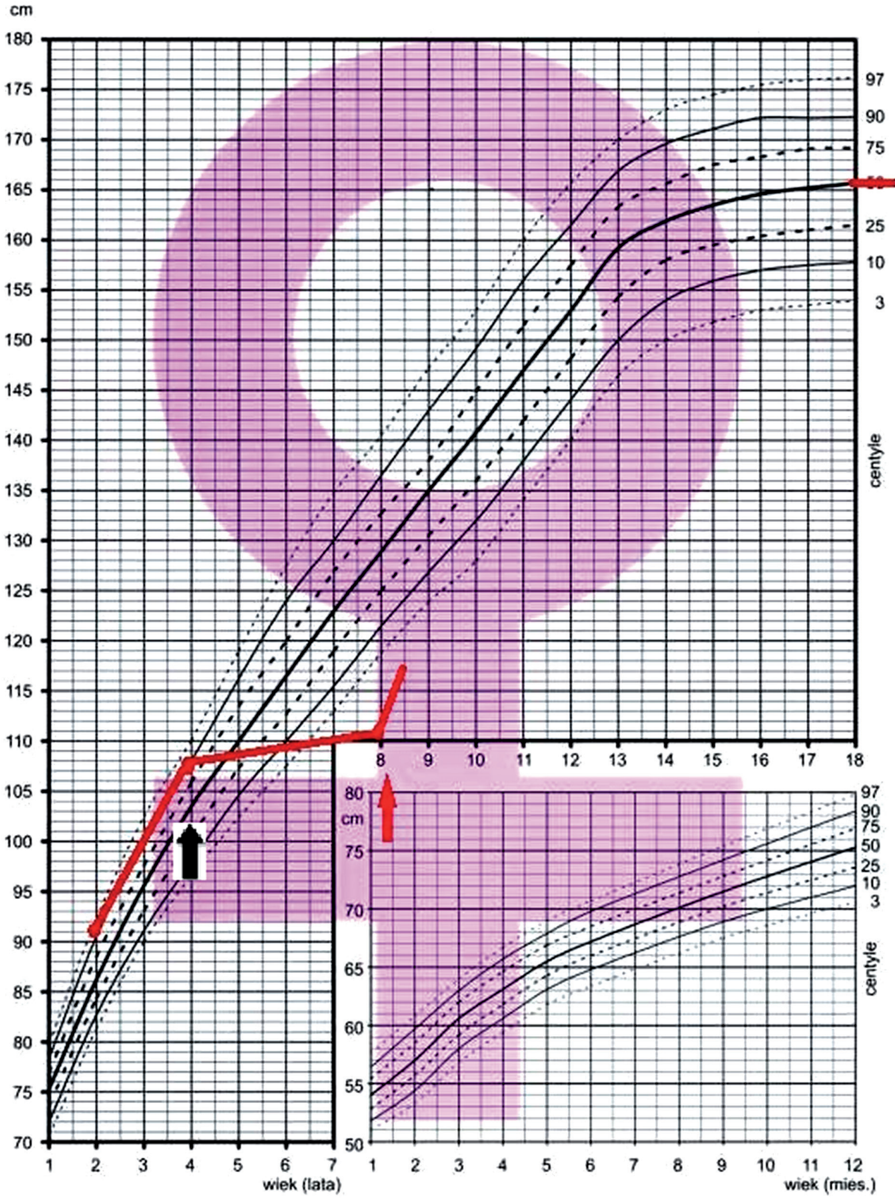
- The case: a girl first admitted at 7 years 10 months with severe symptomatic hypoglycemia (lowest glycemia 25 mg%) after gastroenteritis. She had severe head trauma at 3 years 10 months from being hit by a swing, with basilar skull fracture, cerebral edema, subarachnoid hemorrhage, and transient diabetes insipidus. She was diagnosed with secondary adrenal insufficiency (morning cortisol 44.8 ng/ml, ACTH 5.3 pg/ml), growth hormone deficiency (GH 0.13 ng/ml during hypoglycemia; max 0.49 ng/ml in two stimulation tests; IGF1 27.1 ng/ml), and secondary hypothyroidism (fT4 6.6 pmol/l, fT3 1.8 pmol/l, TSH 2.89 uIU/ml).
- MRI was initially described as PSIS but reassessed as PSTS: absent pituitary stalk, hyperintense signal of the distal regenerating hypothalamic axon (pseudo-posterior lobe) at the median eminence, hypotrophic anterior pituitary, and no posterior pituitary bright spot. Hormone replacement with hydrocortisone, L-thyroxine, and recombinant GH resolved hypotonia and hypoglycemia and normalized growth, with growth velocity 16 cm/year.
- The paper highlights differentiation points: extra-pituitary midline malformations occur in 48% of PSIS cases but never as a PSTS consequence; known gene mutations were confirmed in 5% of examined patients. In a series of 67 children with PSIS, invisible pituitary stalk was found in only 6%, while interrupted or thin stalk was reported in 81% and 13%, respectively; anterior pituitary hypoplasia can be found in 86%. At diagnosis, isolated GH deficiency was diagnosed in 52% of PSIS patients and CPHD in 48%, with CPHD confirmed in 83% after 12 years follow-up.
Methods
- Design: single pediatric case report plus literature overview comparing clinical manifestation, MRI images, and extra-pituitary disorders between PSIS and PSTS.
- Case data: 7-year-10-month-old girl born at 41 weeks by elective cesarean section due to breech presentation, birth weight 3600 g, length 58 cm, Apgar 10; severe head trauma at 3 years 10 months; laboratory testing including glucagon stimulation, hormonal assays, and hypothalamo-pituitary MRI (1.5 Tesla; sagittal/coronal T1- and T2-weighted and dynamic post-contrast T1-weighted; 3 mm sections).
- Analysis: descriptive integration of the patient’s clinical, biochemical, and imaging findings with published data on PSTS and PSIS; MRI was reassessed in light of the strict temporal relation between trauma and CPHD.
Limitations
- No formal limitations section is stated in the paper.
- Evident limitations: the report is based on a single case, so findings cannot be generalized; the literature overview is not described as a systematic review; and the patient’s diagnosis of PSTS is supported by clinical temporal association and imaging rather than direct pathological proof.
Model-written summary. Check it against the paper before relying on it.
Integrity signals
Registry
Cites
Statistics
Figures
Verification
Claims the paper makes
0 Valid · 1 Not valid · 46 Not checked · 30 Own results and interpretations
A result the paper reports from its own data — it cites no other source for it, so there is none to check. The quote shows it is in the paper.
In the paper
“Low serum sodium level (135 mmol/l, N: 135-145) was also found.”
§ Distinguishing between post-trauma pituitary stalk disruption and genetic pituitary stalk interruption syndrome -case presentation and literature overview Różnicowanie pomiędzy pourazowym przerwaniem szypuły przysadki a genetycznie uwarunkowanym zespołem przerwania > Results
plainSingle case- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: unclear — It is unclear whether the paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
A result the paper reports from its own data — it cites no other source for it, so there is none to check. The quote shows it is in the paper.
In the paper
“Based on laboratory studies secondary adrenal insufficiency was confirmed: morning cortisol level was low 44.8 ng/ml (N: 50-230), ACTH -5.3 pg/ml (N: 10-60) and remained low in glucagon stimulation test with max.level 55.5 ng/ml.”
§ Distinguishing between post-trauma pituitary stalk disruption and genetic pituitary stalk interruption syndrome -case presentation and literature overview Różnicowanie pomiędzy pourazowym przerwaniem szypuły przysadki a genetycznie uwarunkowanym zespołem przerwania > Results
plainSingle case- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
A result the paper reports from its own data — it cites no other source for it, so there is none to check. The quote shows it is in the paper.
In the paper
“and there were neither clinical nor laboratory symptoms of diabetes insipidus (serum osmolality 288 mOsm/kg H 2 O, urine osmolality 119 mOsm/kg H 2 O).”
§ Distinguishing between post-trauma pituitary stalk disruption and genetic pituitary stalk interruption syndrome -case presentation and literature overview Różnicowanie pomiędzy pourazowym przerwaniem szypuły przysadki a genetycznie uwarunkowanym zespołem przerwania > Results
plainSingle case- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
A result the paper reports from its own data — it cites no other source for it, so there is none to check. The quote shows it is in the paper.
In the paper
“Prolactin level checked twice was within normal range (197.9 and 185.0,N: 130-260 uIU/ml)”
§ Distinguishing between post-trauma pituitary stalk disruption and genetic pituitary stalk interruption syndrome -case presentation and literature overview Różnicowanie pomiędzy pourazowym przerwaniem szypuły przysadki a genetycznie uwarunkowanym zespołem przerwania > Results
plainSingle case- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: unclear — It is unclear whether the paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
A result the paper reports from its own data — it cites no other source for it, so there is none to check. The quote shows it is in the paper.
In the paper
“Secondary hypothyroidism (fT4 -6.6 pmol/l, N: 10-25; fT3 -1.8 pmol/l, N: 3.0-8.1,TSH -2.89 uIU/ml, N: 0.3-4.0)was also confirmed.”
§ Distinguishing between post-trauma pituitary stalk disruption and genetic pituitary stalk interruption syndrome -case presentation and literature overview Różnicowanie pomiędzy pourazowym przerwaniem szypuły przysadki a genetycznie uwarunkowanym zespołem przerwania > Results
plainSingle case- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: unclear — It is unclear whether the paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
36 more claims
Create a free account to see all 77 claims and every source verdict.
- It may state two separate claims as one. 30
- Probably not a substantial claim. 8
Self-check
Percentages, sums and reported differences re-computed from the paper’s own numbers.
Each contradiction between two passages listed here was confirmed by an independent check.
Rated minor: it would not touch a result — a value no result rests on, a p-value that stays on the same side of the significance level, or a conflict that is clerical, resolved elsewhere in the paper, or outside its own findings.
In the paper
§ Distinguishing between post-trauma pituitary stalk disruption and genetic pituitary stalk interruption syndrome -case presentation and literature overview Różnicowanie pomiędzy pourazowym przerwaniem szypuły przysadki a genetycznie uwarunkowanym zespołem przerwania > Results
“Low serum sodium level”
§ Distinguishing between post-trauma pituitary stalk disruption and genetic pituitary stalk interruption syndrome -case presentation and literature overview Różnicowanie pomiędzy pourazowym przerwaniem szypuły przysadki a genetycznie uwarunkowanym zespołem przerwania > Results
“135 mmol/l, N: 135-145”
Rated minor: it would not touch a result — a value no result rests on, a p-value that stays on the same side of the significance level, or a conflict that is clerical, resolved elsewhere in the paper, or outside its own findings.
In the paper
§ Distinguishing between post-trauma pituitary stalk disruption and genetic pituitary stalk interruption syndrome -case presentation and literature overview Różnicowanie pomiędzy pourazowym przerwaniem szypuły przysadki a genetycznie uwarunkowanym zespołem przerwania > References
“22. Ceballos R. Pituitary changes in head trauma (analysis of 102 con- secutive cases of head injury). Ala J Med Sci 2966; 3: 185.”
§ Distinguishing between post-trauma pituitary stalk disruption and genetic pituitary stalk interruption syndrome -case presentation and literature overview Różnicowanie pomiędzy pourazowym przerwaniem szypuły przysadki a genetycznie uwarunkowanym zespołem przerwania > References
“54. Ceballos R. Pituitary changes in head trauma (analysis of 102 con- secutive cases of head injury). Ala J Med Sci 1966; 3: 185-198.”
Citations
Cites
Schneider, H. J., Kreitschmann-Andermahr, I., Ghigo, E., Stalla, G. K., & Agha, A. (2007) · JAMA · doi:10.1001/jama.298.12.1429 · Cited by 549
Schneier, A. J., Shields, B. J., Hostetler, S. G., Xiang, H., & Smith, G. A. (2006) · Pediatrics · doi:10.1542/peds.2005-2588 · Cited by 423
Brain Injuries Among Infants, Children, Adolescents, and Young Adults
Kraus, J. F. (1990) · Archives of Pediatrics & Adolescent Medicine · doi:10.1001/archpedi.1990.02150300082022 · Cited by 288
Hypothalamic lesions following closed head injury
CROMPTON, M. R. (1971) · Brain · doi:10.1093/brain/94.1.165 · Cited by 243
Triulzi, F. M., Scotti, G., di Natale, B., Pellini, C., Lukezic, M., Scognamiglio, M., & Chiumello, G. (1994) · PEDIATRICS · doi:10.1542/peds.93.3.409 · Cited by 147
KIKUCHI, K., Fujisawa, I., Momoi, T., Yamanaka, C., Kaji, M., Nakano, Y., Konishi, J., Mikawa, H., & Sudo, M. (1988) · The Journal of Clinical Endocrinology & Metabolism · doi:10.1210/jcem-67-4-817 · Cited by 132
(1966) · PubMed · Cited by 123
Mehta, A., & Dattani, M. (2008) · Best Practice & Research Clinical Endocrinology & Metabolism · doi:10.1016/j.beem.2007.07.007 · Cited by 115
Reynaud, R., Albarel, F., Saveanu, A., Kaffel, N., Castinetti, F., Lecomte, P., Brauner, R., Simonin, G., Gaudart, J., Carmona, E., et al. (2011) · European Journal of Endocrinology · doi:10.1530/eje-10-0892 · Cited by 111
Histologic study of the human pituitary gland in acute traumatic brain injury
Salehi, F., Kovacs, K., Scheithauer, B. W., Pfeifer, E. A., & Cusimano, M. (2007) · Brain Injury · doi:10.1080/02699050701426956 · Cited by 96
Research works printed but not linked: 13
- Castinetti F, Reynaud R, Saveanu A, et al. An update in the genetic aetiologies of combined pituitary hormone deficiency. Eur J Endo- crinol 2016; 174: R239-R247. doi: 10.1007/s40618-014-0141-2 · DOI
- Fujisawa I, Kikuchi K, Nishimura K, et al. Transection of the pitu- itary stalk: development of an ectopic posterior lobe assessed with MR imaging. Radiology 1987; 165: 487-489. doi: 10.1148/radiol- ogy.165.2.3659371 · doi:10.1148/radiol-ogy.165.2.3659371
- Masson F, Salmi LR, Maurette P, et al. Characteristics of head trau- ma in children: epidemiology and a 5-year follow-up. Arch Pediatr 1996; 3: 651-660.
- Ceballos R. Pituitary changes in head trauma (analysis of 102 con- secutive cases of head injury). Ala J Med Sci 2966; 3: 185.
- Bierich JR. Aetiology and pathogenesis of growth hormone defi- ciency. Baillieres Clin Endocrinol Metab 1992; 6: 491-511.
- Reichlin S. Neuroendocrinology in Williams RH Textbook of endo- crinology, ed 6. Saunders Philadelphia 1981; 589.
- Gotyo N, Doi M, Izumiyama H, Hirata Y. Secondary adrenal insuf- ficiency caused by adult development of pituitary stalk transec- tion. Intern Med 2007; 46: 1711-1715. doi: 10.2169/internalmedi- cine.46.6404 · doi:10.2169/internalmedi-cine.46.6404
- Kraus JF, Rock A, Hemyari P. Brain injuries among infants, children, adolescents, and young adults. Am J Dis Child 1990; 144: 684- 691. doi: 10.1001/archpedi.1990.02150300082022 · DOI · Paper page
- Masson F, Salmi LR, Maurette P, et al. Characteristics of head trau- ma in children: epidemiology and a 5-year follow-up. Arch Pediatr 1996; 3: 651-660. Pediatr Endocrinol Diabetes Metab 2019
- Ruszała A., Wójcik M., Krystynowicz A., Starzyk J.B. 52. Schneider AJ, Shields BJ, Hostetler SG, et al. Incidence of pediatric traumatic brain injury and associated hospital resource utilization in the United States. Pediatrics 2006; 118: 483-492. doi: 10.1542/ peds.2005-2588 · DOI · Paper page
- Salehi F, Kovacs K, Scheithauer BW, et al. Histologic study of the human pituitary gland in acute traumatic brain injury. Brain Inj 2007; 21: 651-656. doi: 10.1080/02699050701426956 · DOI · Paper page
- Maiya B, Newcombe V, Nortje J, et al. Magnetic resonance imag- ining changes in the pituitary gland following acute traumatic brain injury. Intensive Care Med 2008; 34: 468-475. doi: 10.1007/ s00134-007-0902-x · DOI · Paper page
- Crompton MR. Hypothalamic lesions following closed head injury. Brain 1971; 94: 165-172. doi: 10.1093/brain/94.1.165 · DOI · Paper page
Cited by
Diversity of Pathological Conditions Affecting Pituitary Stalk
Kluczyński, Ł., Gilis‐Januszewska, A., Godlewska, M., Wójcik, M., Zygmunt-Górska, A., Starzyk, J., & Hubalewska–Dydejczyk, A. (2021) · Journal of Clinical Medicine · doi:10.3390/jcm10081692 · Cited by 15
Self-citationIshiki, Y., Tamaki, A., Honma, K.-I., Yonaha, K., Yabiku, T., Teruya, T., Uehara, M., Nakayama, Y., Chinen, R., Uema, T., et al. (2024) · Endocrine Journal · doi:10.1507/endocrj.ej24-0091 · Cited by 5
Progress in investigating pituitary stalk lesions: A review
Zhang, Z., Wang, J., Shi, Y., Zhao, Y., Hu, Y., Wang, W., & Chen, Z. (2025) · Medicine · doi:10.1097/md.0000000000041232 · Cited by 2
Two Cases of Late Diagnosis Pituitary Stalk Interruption Syndrome and Literature Review
Alkhalifa, M., Alsalman, Z., Elq, A. H. A., Al-Khadrawi, Z., & Radwan, H. (2025) · International Medical Case Reports Journal · doi:10.2147/imcrj.s507989 · Cited by 1
Luo, Y., Gu, F., Fan, H.-Q., Du, J.-H., Yu, Y., Liu, L., & Liao, X. (2022) · Frontiers in Oncology · doi:10.3389/fonc.2022.971730 · Cited by 1
Metadata
- Authors
- Ruszała, A., Wójcik, M., Krystynowicz, A., & Starzyk, J.
- Affiliations
- Jagiellonian University (PL)
- Corresponding author
- Starzyk, Jerzy
- Venue
- Pediatric Endocrinology Diabetes and Metabolism
- Publisher
- Termedia Sp. z.o.o.
- Published
- 2019
- Volume
- 25
- Issue
- 3
- Pages
- 155-162
- ISSN
- 1234-625X (ISSN-L)
- 2081-237X
- OpenAlex
- W2979457130
- Cited by
- 7
- References
- 43
- Citations by year
- 2026: 2 · 2025: 2 · 2024: 1 · 2022: 1 · 2021: 1
- FWCI
- 0.26
- Type
- journal article
- Language
- en
- Open access
- diamond
- doi.org
- Licence
- cc-by-nc-sa
- Locations
- Pediatric Endocrinology Diabetes and Metabolism (publishedVersion, cc-by-nc-sa)
- PubMed (publishedVersion)
- Jagiellonian University Repository (Jagiellonian University) (submittedVersion, cc-by-nc-nd)
- Topics
- Health Sciences › Medicine › Endocrinology, Diabetes and Metabolism › Pituitary Gland Disorders and Treatments
- Health Sciences › Medicine › Nephrology › Electrolyte and hormonal disorders
- Health Sciences › Medicine › Endocrinology, Diabetes and Metabolism › Adrenal Hormones and Disorders
- Keywords
- pituitary stalk interruption syndrome, combined pituitary hormone deficiency, traumatic head injury, transient diabetes insipidus, ectopic posterior pituitary, differential diagnosis, pediatric trauma
- MeSH terms
- Child, Diagnosis, Differential, Endocrine System Diseases, Female, Humans, Pituitary Gland, Syndrome, Wounds and Injuries
About these checks
Registry, retraction, Cites and statistics results are computed, not judged, with one exception: a printed reference that no index lists is read once by a model before it counts as a citation error. Claims are extracted by a model and kept only when their quote appears verbatim in the text; each cited source is then checked, with a model’s help, for whether it says what the claim relies on. Those verdicts can be wrong — read the claim’s quote and the cited source before relying on one.
A language model drew the claims from the paper on 2026-11-14, under version 3 of the claim definition (model deepseek-v4.1-flash, prompt extract-v3).
A second model labelled each claim on 2026-11-14 (model jev-1.13-20260917, definition revision gold-guideline-v0.2).
Statistics and arithmetic are recomputed, not judged.
Confidence bands are shown only for fields calibrated on our annotated test set. None is calibrated yet, so no band is shown.
What counts as a claim ›How we measure confidence ›How we check this ›
Are you an author, or do you see a problem with this page? Request a review
Data sources
Bibliographic data: Semantic Scholar, OpenAlex, Crossref.
Contains information from the Semantic Scholar Academic Graph Datasets, made available under the ODC Attribution License (ODC-BY 1.0).
Semantic Scholar’s data is described in: Kinney, R., et al. (2023). The Semantic Scholar Open Data Platform. arXiv:2301.10140.
