

The DOI matches its Crossref record; 27 of the 27 references it cites were found in a registry or an index.
Rapid urine-based screening for tuberculosis in HIV-positive patients admitted to hospital in Africa (STAMP): a pragmatic, multicentre, parallel-group, double-blind, randomised controlled trial
Open accessAbstract
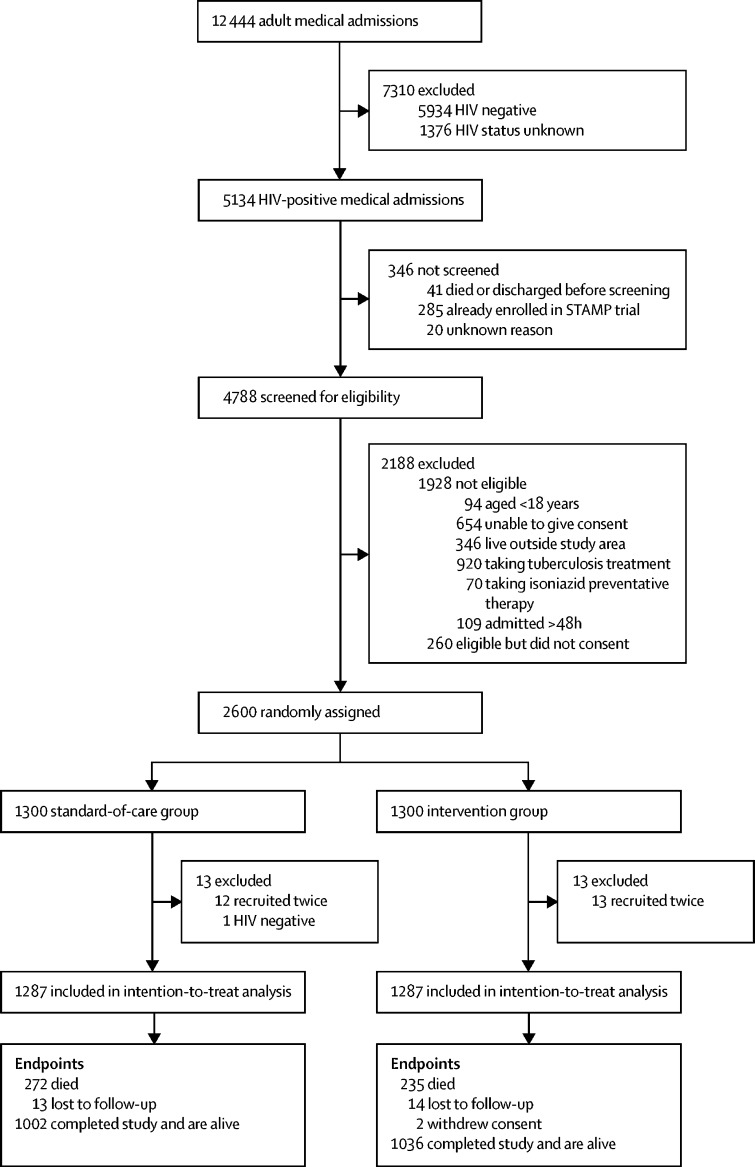
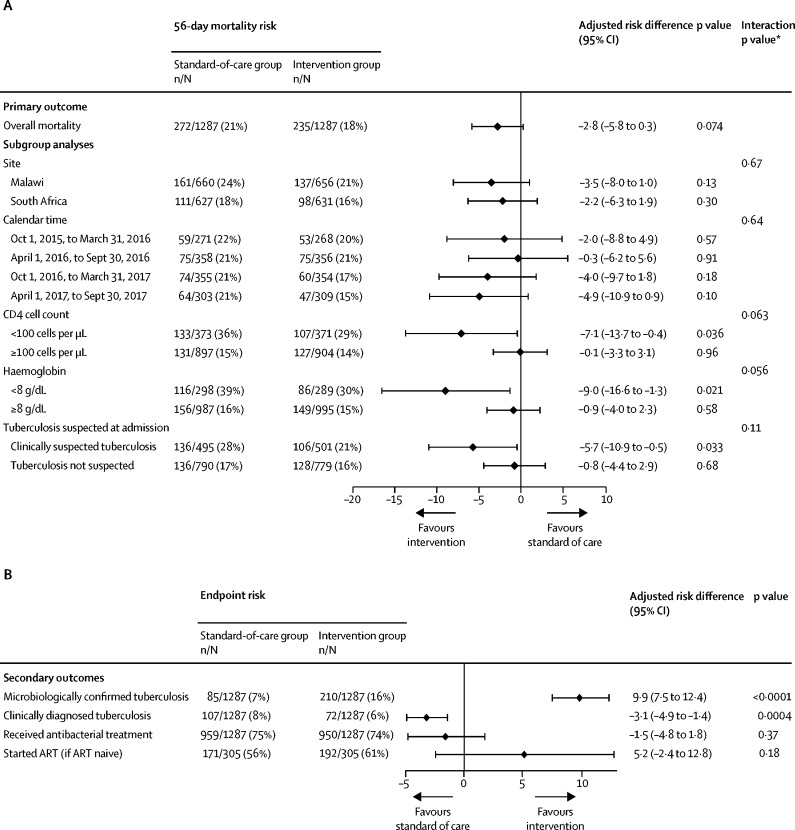
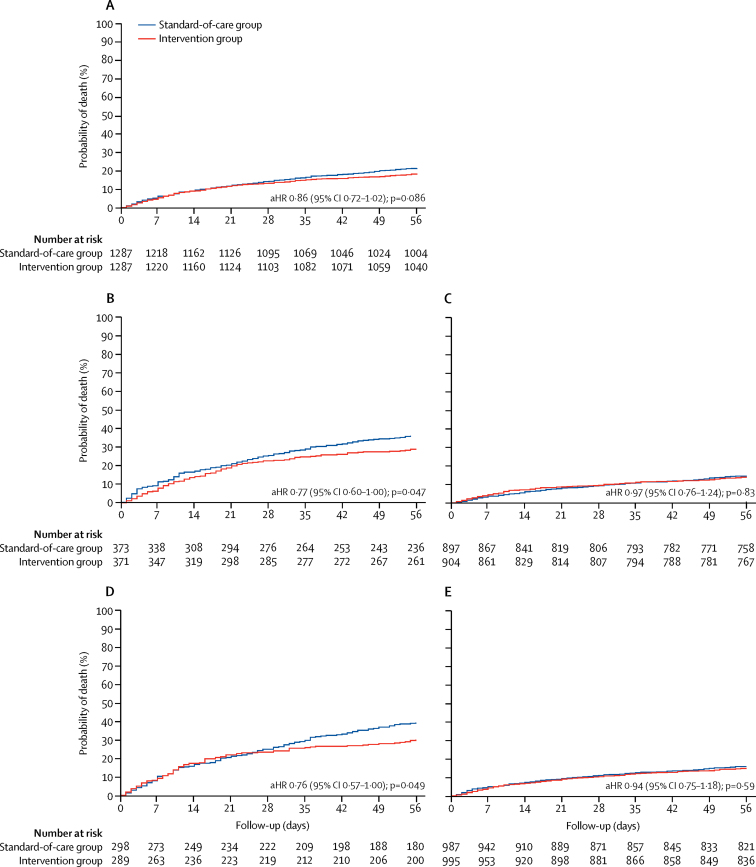
BACKGROUND: Current diagnostics for HIV-associated tuberculosis are suboptimal, with missed diagnoses contributing to high hospital mortality and approximately 374 000 annual HIV-positive deaths globally. Urine-based assays have a good diagnostic yield; therefore, we aimed to assess whether urine-based screening in HIV-positive inpatients for tuberculosis improved outcomes. METHODS: We did a pragmatic, multicentre, double-blind, randomised controlled trial in two hospitals in Malawi and South Africa. We included HIV-positive medical inpatients aged 18 years or more who were not taking tuberculosis treatment. We randomly assigned patients (1:1), using a computer-generated list of random block size stratified by site, to either the standard-of-care or the intervention screening group, irrespective of symptoms or clinical presentation. Attending clinicians made decisions about care; and patients, clinicians, and the study team were masked to the group allocation. In both groups, sputum was tested using the Xpert MTB/RIF assay (Xpert; Cepheid, Sunnyvale, CA, USA). In the standard-of-care group, urine samples were not tested for tuberculosis. In the intervention group, urine was tested with the Alere Determine TB-LAM Ag (TB-LAM; Alere, Waltham, MA, USA), and Xpert assays. The primary outcome was all-cause 56-day mortality. Subgroup analyses for the primary outcome were prespecified based on baseline CD4 count, haemoglobin, clinical suspicion for tuberculosis; and by study site and calendar time. We used an intention-to-treat principle for our analyses. This trial is registered with the ISRCTN registry, number ISRCTN71603869. FINDINGS: Between Oct 26, 2015, and Sept 19, 2017, we screened 4788 HIV-positive adults, of which 2600 (54%) were randomly assigned to the study groups (n=1300 for each group). 13 patients were excluded after randomisation from analysis in each group, leaving 2574 in the final intention-to-treat analysis (n=1287 in each group). At admission, 1861 patients were taking antiretroviral therapy and median CD4 count was 227 cells per μL (IQR 79-436). Mortality at 56 days was reported for 272 (21%) of 1287 patients in the standard-of-care group and 235 (18%) of 1287 in the intervention group (adjusted risk reduction [aRD] -2·8%, 95% CI -5·8 to 0·3; p=0·074). In three of the 12 prespecified, but underpowered subgroups, mortality was lower in the intervention group than in the standard-of-care group for CD4 counts less than 100 cells per μL (aRD -7·1%, 95% CI -13·7 to -0·4; p=0.036), severe anaemia (-9·0%, -16·6 to -1·3; p=0·021), and patients with clinically suspected tuberculosis (-5·7%, -10·9 to -0·5; p=0·033); with no difference by site or calendar period. Adverse events were similar in both groups. INTERPRETATION: Urine-based tuberculosis screening did not reduce overall mortality in all HIV-positive inpatients, but might benefit some high-risk subgroups. Implementation could contribute towards global targets to reduce tuberculosis mortality. FUNDING: Joint Global Health Trials Scheme of the Medical Research Council, the UK Department for International Development, and the Wellcome Trust.
Overview
The claims and statistics of this paper haven’t been checked yet.
Run the check — free, no account needed. It reads the open-access text and checks the sources it cites.
Integrity signals
Registry
Cites
Statistics
Figures
Verification
Claims the paper makes
The claims and statistics of this paper haven’t been checked yet.
Run the check — free, no account needed. It reads the open-access text and checks the sources it cites.
Claims other papers make about this one
Each is checked against this paper’s own text: does it say what the citing paper says it does?
The source backs part of the claim, not all of it — or backs it for a different population, condition or comparison.
In the citing paper
“In two randomized trials, the use of Alere LAM in HIV‐positive adult inpatients was shown to reduce mortality (Gupta‐Wright 2018; Peter 2016).”
From Xpert MTB/RIF Ultra and Xpert MTB/RIF assays for extrapulmonary tuberculosis and rifampicin resistance in adults (2021) · cites this paper as Gupta‐Wright 2018
Experimental — accuracy not yet measured
Self-check
Percentages, sums and reported differences re-computed from the paper’s own numbers.
The self-check needs the paper’s full text.
Citations
Cites
Xpert® MTB/RIF assay for pulmonary tuberculosis and rifampicin resistance in adults
Steingart, K. R., Schiller, I., Horne, D. J. D. L., Pai, M., Boehme, C. C., & Dendukuri, N. (2014) · Cochrane Database of Systematic Reviews · doi:10.1002/14651858.cd009593.pub3 · Cited by 1,187
Denkinger, C. M., Schumacher, S. G., Boehme, C. C., Dendukuri, N., Pai, M., & Steingart, K. R. (2014) · European Respiratory Journal · doi:10.1183/09031936.00007814 · Cited by 527
Lawn, S. D., Mwaba, P., Bates, M., Piatek, A. S., Alexander, H. L., Marais, B. J., Cuevas, L. E., McHugh, T. D., Zijenah, L. S., Kapata, N., et al. (2013) · The Lancet Infectious Diseases · doi:10.1016/s1473-3099(13)70008-2 · Cited by 459
Self-citationGupta, R. K., Lucas, S. B., Fielding, K., & Lawn, S. D. (2015) · AIDS · doi:10.1097/qad.0000000000000802 · Cited by 373
Self-citationFord, N. P., Shubber, Z., Meintjes, G., Grinsztejn, B. G. J., Eholié, S. P., Mills, E. J., Davies, M., Vitória, M., Penazzato, M., Nsanzimana, S., et al. (2015) · The Lancet HIV · doi:10.1016/s2352-3018(15)00137-x · Cited by 328
Peter, J. G., Zijenah, L. S., Chanda, D., Clowes, P., Lesosky, M., Gina, P., Mehta, N., Calligaro, G., Lombard, C. J., Kadzirange, G., et al. (2016) · The Lancet · doi:10.1016/s0140-6736(15)01092-2 · Cited by 276
Enhanced Prophylaxis plus Antiretroviral Therapy for Advanced HIV Infection in Africa
Hakim, J. G., Musiime, V., Szubert, A. J., Mallewa, J., Siika, A. M., Agutu, C., Walker, S., Pett, S. L., Bwakura‐Dangarembizi, M., Lugemwa, A., et al. (2017) · New England Journal of Medicine · doi:10.1056/nejmoa1615822 · Cited by 207
Lateral flow urine lipoarabinomannan assay for detecting active tuberculosis in HIV-positive adults
Shah, M., Hanrahan, C. F., Wang, Z. Y., Dendukuri, N., Lawn, S. D., Denkinger, C. M., & Steingart, K. R. (2016) · Cochrane Database of Systematic Reviews · doi:10.1002/14651858.cd011420.pub2 · Cited by 178
Self-citationBadje, A., Moh, R., Gabillard, D., Guéhi, C., Kabran, M., Ntakpé, J.-B., Carrou, J. L., Kouamé, G. M., Ouattara, E. N., Messou, E., et al. (2017) · The Lancet Global Health · doi:10.1016/s2214-109x(17)30372-8 · Cited by 170
Ford, N. P., Matteelli, A., Shubber, Z., Hermans, S., Meintjes, G., Grinsztejn, B. G. J., Waldrop, G. E., Kranzer, K., Doherty, M. C., & Getahun, H. (2016) · Journal of the International AIDS Society · doi:10.7448/ias.19.1.20714 · Cited by 164
Research works printed but not linked: 1
- Reddy KP, Gupta-Wright A, Fielding K, et al. Cost-effectiveness of urine TB screening for hospitalized people with HIV in Africa. The Conference on Retroviruses and Opportunistic Infections (CROI); Boston, MA, USA; 2018. Abstract number 3521.
Cited by
Sorted by citations
Furin, J. J., Cox, H. S., & Pai, M. (2019) · The Lancet · doi:10.1016/s0140-6736(19)30308-3 · Cited by 876
Xpert MTB/RIF and Xpert MTB/RIF Ultra for pulmonary tuberculosis and rifampicin resistance in adults
Horne, D. J. D. L., Kohli, M., Zifodya, J. S., Schiller, I., Dendukuri, N., Tollefson, D., Schumacher, S. G., Ochodo, E., Pai, M., & Steingart, K. R. (2019) · Cochrane Database of Systematic Reviews · doi:10.1002/14651858.cd009593.pub4 · Cited by 296
Drug resistant Tuberculosis: A review
Khawbung, J. L., Nath, D., & Chakraborty, S. (2020) · Comparative Immunology Microbiology and Infectious Diseases · doi:10.1016/j.cimid.2020.101574 · Cited by 252
Urogenital tuberculosis — epidemiology, pathogenesis and clinical features
Muneer, A., Macrae, B., Krishnamoorthy, S., & Zumla, A. I. (2019) · Nature Reviews Urology · doi:10.1038/s41585-019-0228-9 · Cited by 219
Novel High Sensitivity Tuberculosis Point-of-Care Test for People Living with HIV
Broger, T., Sossen, B., du Toit, E., Kerkhoff, A. D., Schutz, C., Reipold, E. I., Ward, A. M., Barr, D. A., Macé, A., Trollip, A., et al. (2018) · The Lancet Infectious Diseases · doi:10.1016/s1473-3099(19)30001-5 · Cited by 222
Metadata
- Authors
- Gupta-Wright, A., Corbett, E. L., van Oosterhout, J. J., Wilson, D., Grint, D., Alufandika-Moyo, M., Peters, J. A., Chiume, L., Flach, C., Lawn, S. D., & Fielding, K.
- Affiliations
- Malawi-Liverpool-Wellcome Trust Clinical Research Programme (MW)
- Edendale Hospital (ZA)
- London School of Hygiene & Tropical Medicine (GB)
- King's College London (GB)
- University of the Witwatersrand (ZA)
- ORCID
- Venue
- The Lancet
- Publisher
- Elsevier BV
- Published
- 2018-07
- Volume
- 392
- Issue
- 10144
- Pages
- 292-301
- ISSN
- 0099-5355 (ISSN-L)
- 0140-6736
- PMC
- PMC6078909
- OpenAlex
- W2883578784
- Cited by
- 213
- References
- 27
- Citations by year
- 2026: 15 · 2025: 23 · 2024: 17 · 2023: 22 · 2022: 29 · 2021: 18 · 2020: 35 · 2019: 46 · 2018: 8
- FWCI
- 20.20
- Type
- journal article
- Language
- en
- Open access
- hybrid
- doi.org
- Locations
- The Lancet (publishedVersion, cc-by)
- Europe PMC (PubMed Central) (publishedVersion, cc-by)
- PubMed Central (publishedVersion, cc-by)
- PubMed (publishedVersion)
- LSTM Online Archive (Liverpool School of Tropical Medicine) (acceptedVersion)
- LSHTM Research Online (London School of Hygiene and Tropical Medicine) (acceptedVersion)
- Research Portal (King's College London) (submittedVersion, cc-by)
- Greater South Information System
- Funders
- Wellcome Trust (WT200901, MR/M007375, WT200901/Z/16/Z, MR/M007375/1)
- Department for International Development
- Medical Research Council (MR/M007375/1, MR/K012126/1)
- Topics
- Health Sciences › Medicine › Infectious Diseases › Tuberculosis Research and Epidemiology
- Health Sciences › Medicine › Infectious Diseases › Infectious Diseases and Tuberculosis
- Health Sciences › Medicine › Infectious Diseases › HIV/AIDS Research and Interventions
- Keywords
- HIV-associated tuberculosis, tuberculosis screening, Xpert MTB/RIF, in-hospital mortality, CD4 count, antiretroviral therapy, tuberculosis diagnosis, Malawi, South Africa, Africa
- MeSH terms
- Adult, Developing Countries, Double-Blind Method, Female, HIV Seropositivity, Humans, Malawi, Male, Mass Screening, Middle Aged, Rifampin, South Africa, Sputum, Tuberculosis, Urinalysis, AIDS-Related Opportunistic Infections, Drug Resistance, Bacterial
About these checks
Registry, retraction, Cites and statistics results are computed, not judged, with one exception: a printed reference that no index lists is read once by a model before it counts as a citation error. Claims are extracted by a model and kept only when their quote appears verbatim in the text; each cited source is then checked, with a model’s help, for whether it says what the claim relies on. Those verdicts can be wrong — read the claim’s quote and the cited source before relying on one.
Statistics and arithmetic are recomputed, not judged.
Confidence bands are shown only for fields calibrated on our annotated test set. None is calibrated yet, so no band is shown.
What counts as a claim ›How we measure confidence ›How we check this ›
Are you an author, or do you see a problem with this page? Request a review
