

The DOI matches its Crossref record; 19 of the 19 references it cites were found in a registry or an index.
Intravenous angiotensin II for the treatment of high-output shock (ATHOS trial): a pilot study
Open accessAbstract
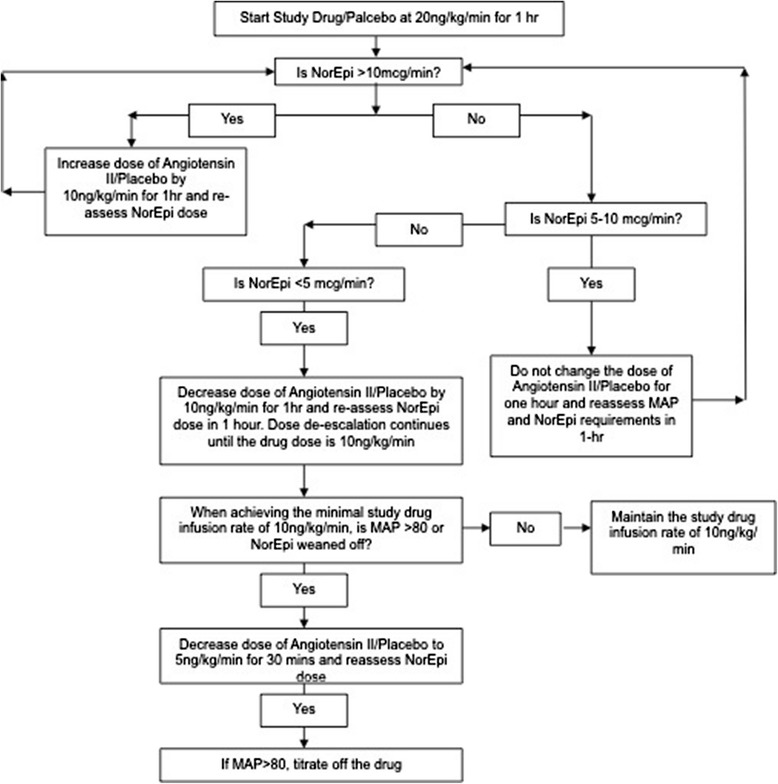
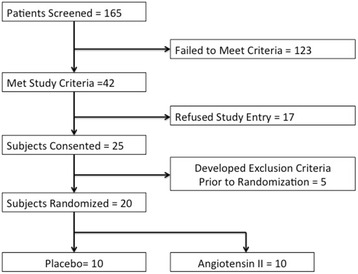
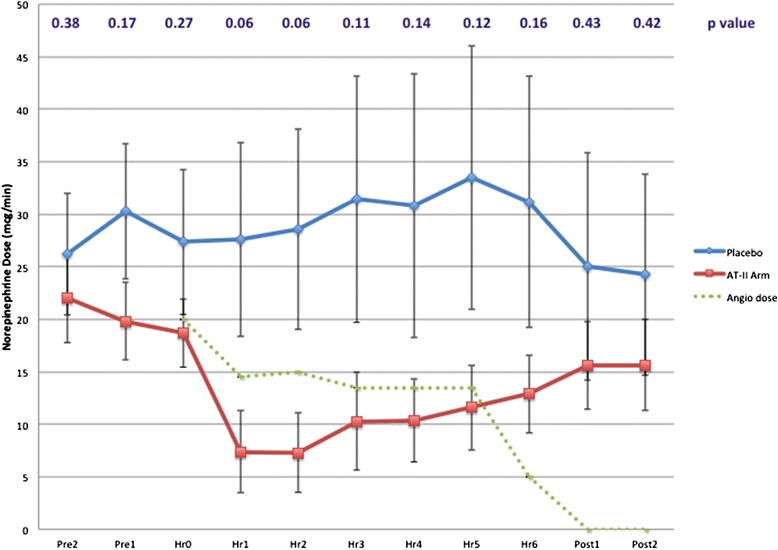
Introduction: Patients with distributive shock who require high dose vasopressors have a high mortality. Angiotensin II (ATII) may prove useful in patients who remain hypotensive despite catecholamine and vasopressin therapy. The appropriate dose of parenteral angiotensin II for shock is unknown. Methods: In total, 20 patients with distributive shock and a cardiovascular Sequential Organ Failure Assessment score of 4 were randomized to either ATII infusion (N =10) or placebo (N =10) plus standard of care. ATII was started at a dose of 20 ng/kg/min, and titrated for a goal of maintaining a mean arterial pressure (MAP) of 65 mmHg. The infusion (either ATII or placebo) was continued for 6 hours then titrated off. The primary endpoint was the effect of ATII on the standing dose of norepinephrine required to maintain a MAP of 65 mmHg. Results: ATII resulted in marked reduction in norepinephrine dosing in all patients. The mean hour 1 norepinephrine dose for the placebo cohort was 27.6 ± 29.3 mcg/min versus 7.4 ± 12.4 mcg/min for the ATII cohort ( P =0.06). The most common adverse event attributable to ATII was hypertension, which occurred in 20% of patients receiving ATII. 30-day mortality for the ATII cohort and the placebo cohort was similar (50% versus 60%, P =1.00). Conclusion: Angiotensin II is an effective rescue vasopressor agent in patients with distributive shock requiring multiple vasopressors. The initial dose range of ATII that appears to be appropriate for patients with distributive shock is 2 to 10 ng/kg/min. Trial registration: Clinicaltrials.gov NCT01393782 . Registered 12 July 2011.
Overview
The claims and statistics of this paper haven’t been checked yet.
Run the check — free, no account needed. It reads the open-access text and checks the sources it cites.
Integrity signals
Registry
Cites
Statistics
Figures
Verification
Claims the paper makes
The claims and statistics of this paper haven’t been checked yet.
Run the check — free, no account needed. It reads the open-access text and checks the sources it cites.
Claims other papers make about this one
Each is checked against this paper’s own text: does it say what the citing paper says it does?
The check wasn’t confident either way, so it gives no verdict — never disputed.
In the citing paper
“There are data from RCTs in specific conditions such as pneumonia (286-289), urinary tract infections (290), bacteremia (291, 292), and intraabdominal infections (293).”
From Surviving Sepsis Campaign: International Guidelines for Management of Sepsis and Septic Shock 2021. (2021) · cites this paper as [290]
Experimental — accuracy not yet measuredIn the citing paper
“After a small, short-term pilot of 20 patients with vasodilatory (septic) shock 10 patients in each group which showed physiological efficacy without obvious safety issues [365]”
From Surviving sepsis campaign: international guidelines for management of sepsis and septic shock 2021 (2021) · cites this paper as [365]
Self-check
Percentages, sums and reported differences re-computed from the paper’s own numbers.
The self-check needs the paper’s full text.
Citations
Cites
Vincent, J. L., Moreno, R., Takala, J., Willatts, S., De Mendonça, A., Bruining, H., Reinhart, C. K., Suter, P. M., & Thijs, L. G. (1996) · Intensive Care Medicine · doi:10.1007/bf01709751 · Cited by 11,674
Vasopressin versus Norepinephrine Infusion in Patients with Septic Shock
Russell, J. A., Walley, K. R., Singer, J., Gordon, A. C., Hébert, P. C., Cooper, D. J., Holmes, C. L., Mehta, S., Granton, J. T., Storms, M. M., et al. (2008) · New England Journal of Medicine · doi:10.1056/nejmoa067373 · Cited by 1,924
Vincent, J., & Backer, D. D. (2013) · New England Journal of Medicine · doi:10.1056/nejmra1208943 · Cited by 1,532
Morelli, A., Ertmer, C., Westphal, M., Rehberg, S. W., Kampmeier, T., Ligges, S., Orecchioni, A., D’Egidio, A., D''Ippoliti, F., Raffone, C., et al. (2013) · JAMA · doi:10.1001/jama.2013.278477 · Cited by 741
Róna, G. (1985) · Journal of Molecular and Cellular Cardiology · doi:10.1016/s0022-2828(85)80130-9 · Cited by 726
A comparison of epinephrine and norepinephrine in critically ill patients
Myburgh, J. A., Higgins, A., Jovanovska, A., Lipman, J., Ramakrishnan, N., Santamaria, J., & the CAT Study investigators (2008) · Intensive Care Medicine · doi:10.1007/s00134-008-1219-0 · Cited by 368
Review of aldosterone- and angiotensin II-induced target organ damage and prevention
Struthers, A. D. (2004) · Cardiovascular Research · doi:10.1016/j.cardiores.2003.11.037 · Cited by 262
History about the discovery of the renin-angiotensin system.
Basso, N., & Terragno, N. (2001) · HYPERTENSION · doi:10.1161/hy1201.101214 · Cited by 236
Angiotensin II in experimental hyperdynamic sepsis
Wan, L., Langenberg, C., Bellomo, R., & May, C. N. (2009) · Critical Care · doi:10.1186/cc8185 · Cited by 148
Angiotensin II in Septic Shock
Corrêa, T. D., Jeger, V., Pereira, A. J., Takala, J. A., Djafarzadeh, S., & Jakob, S. M. (2014) · Critical Care Medicine · doi:10.1097/ccm.0000000000000397 · Cited by 79
Cited by
Sorted by citations
Surviving sepsis campaign: international guidelines for management of sepsis and septic shock 2021
Evans, L., Rhodes, A., Alhazzani, W., Antonelli, M., Coopersmith, C. M., French, C., Machado, F. R., Mcintyre, L., Ostermann, M., Prescott, H. C., et al. (2021) · Intensive Care Medicine · doi:10.1007/s00134-021-06506-y · Cited by 5,082
Surviving Sepsis Campaign: International Guidelines for Management of Sepsis and Septic Shock 2021.
Evans, L., Rhodes, A., Alhazzani, W., Antonelli, M., Coopersmith, C. M., French, C., Machado, F. R., Mcintyre, L., Ostermann, M., Prescott, H. C., et al. (2021) · Critical Care Medicine · doi:10.1097/ccm.0000000000005337 · Cited by 2,935
Peerapornratana, S., Manrique‐Caballero, C. L., Gómez, H., & Kellum, J. A. (2019) · Kidney International · doi:10.1016/j.kint.2019.05.026 · Cited by 1,557
Angiotensin II for the Treatment of Vasodilatory Shock
Khanna, A., English, S. W., Wang, X. S., Ham, K., Tumlin, J., Szerlip, H., Busse, L. W., Altaweel, L., Albertson, T. E., Mackey, C., et al. (2017) · New England Journal of Medicine · doi:10.1056/nejmoa1704154 · Cited by 916
Self-citationBellomo, R., Kellum, J. A., Ronco, C., Wald, R., Mårtensson, J., Maiden, M. J., Bagshaw, S. M., Glassford, N. J., Lankadeva, Y. R., Vaara, S. T., et al. (2017) · Intensive Care Medicine · doi:10.1007/s00134-017-4755-7 · Cited by 794
Metadata
- Authors
- Chawla, L. S., Busse, L., Brasha-Mitchell, E., Davison, D., Honiq, J., Alotaibi, Z., & Seneff, M. G.
- Affiliations
- United States Department of Veterans Affairs (US)
- Inova Fairfax Hospital (US)
- Riyadh Armed Forces Hospital (SA)
- Corresponding author
- Chawla, Lakhmir S
- Venue
- Critical Care
- Published
- 2014-10-06
- Volume
- 18
- Issue
- 5
- Pages
- 534-534
- ISSN
- 1364-8535 (ISSN-L)
- PMC
- PMC4212099
- OpenAlex
- W2031987490
- Cited by
- 197
- References
- 19
- Citations by year
- 2026: 11 · 2025: 19 · 2024: 20 · 2023: 19 · 2022: 11 · 2021: 16 · 2020: 25 · 2019: 28 · 2018: 21 · 2017: 17 · 2016: 7 · 2015: 2 · 2014: 1
- FWCI
- 8.93
- Type
- journal article
- Language
- en
- Open access
- gold
- doi.org
- Locations
- Critical Care (publishedVersion, cc-by)
- PubMed Central (publishedVersion, cc-by)
- PubMed (publishedVersion)
- Funders
- George Washington University
- Topics
- Health Sciences › Medicine › Surgery › Hemodynamic Monitoring and Therapy
- Health Sciences › Medicine › Critical Care and Intensive Care Medicine › Trauma, Hemostasis, Coagulopathy, Resuscitation
- Health Sciences › Medicine › Critical Care and Intensive Care Medicine › Sepsis Diagnosis and Treatment
- Keywords
- angiotensin II, distributive shock, 30-day mortality
- MeSH terms
- Aged, Angiotensin II, Blood Pressure, Cardiac Output, Catecholamines, Female, Humans, Male, Middle Aged, Norepinephrine, Pilot Projects, Shock, Septic, Vasoconstrictor Agents, Treatment Outcome, Administration, Intravenous
About these checks
Registry, retraction, Cites and statistics results are computed, not judged, with one exception: a printed reference that no index lists is read once by a model before it counts as a citation error. Claims are extracted by a model and kept only when their quote appears verbatim in the text; each cited source is then checked, with a model’s help, for whether it says what the claim relies on. Those verdicts can be wrong — read the claim’s quote and the cited source before relying on one.
Statistics and arithmetic are recomputed, not judged.
Confidence bands are shown only for fields calibrated on our annotated test set. None is calibrated yet, so no band is shown.
What counts as a claim ›How we measure confidence ›How we check this ›
Are you an author, or do you see a problem with this page? Request a review
