Student or educator? Sign up with your school email and get 6 months of Pro free.
Cited by 288Medical Imaging Techniques and ApplicationsRadiopharmaceutical Chemistry and ApplicationsProstate Cancer Diagnosis and Treatment

The DOI matches its Crossref record; 74 of the 75 references it cites were found in a registry or an index.

Nonprostatic diseases on PSMA PET imaging: a spectrum of benign and malignant findings

Open access

Abstract

PSMA PET imaging was originally used to assess biochemical recurrence of prostate cancer (PCa), but its clinical use was promptly extended to detection, staging and therapy response assessment. The expanding use of PSMA PET worldwide has also revealed PSMA ligand uptake in diverse nonprostatic diseases, which raised questions about the specificity of this imaging modality. Although not very common initially, a growing number of pathologies presenting PSMA uptake on PET have been reported in the last few years, and a proper interpretation of PSMA PET imaging findings suddenly became challenging and, to some extent, confusing. Compared to cytoplasmic PSMA expression in nonprostatic cells, the molecular features of apical PSMA expression in PCa cells can help to distinguish these various conditions. Correlations of imaging findings to patient history, to the expected pattern of disease spread and mainly to computed tomography (CT) and/or magnetic resonance imaging (MRI) characteristics will reinforce the distinction of lesions that are more likely related to PCa from those that could lead to an incorrect diagnosis. The overall benefits of endothelial PSMA expression, which is associated with the neovasculature of malignant neoplasms, will be highlighted, stating the potential use of PSMA ligand uptake as a theranostic tool. This review aims to cover the collection of nonprostatic diseases, including benign and malignant tumors, in a didactic approach according to disease etiology, with discussion of bone-related conditions and inflammatory and infectious processes.

Overview

The claims and statistics of this paper haven’t been checked yet.

Run the check — free, no account needed. It reads the open-access text and checks the sources it cites.

A few free checks a day · papers already verified open instantly · results are public

Integrity signals

Registry

Crossref · 10.1186/s40644-020-00300-7

Cites

74 of 74 references verified0 citation errors · 0 not checkable

Statistics

Figures
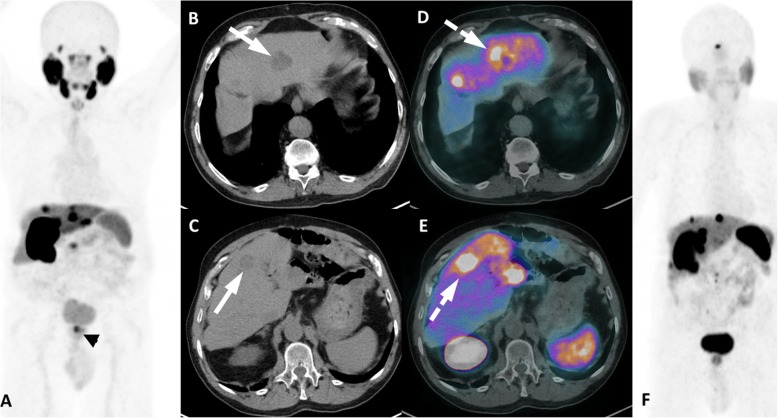
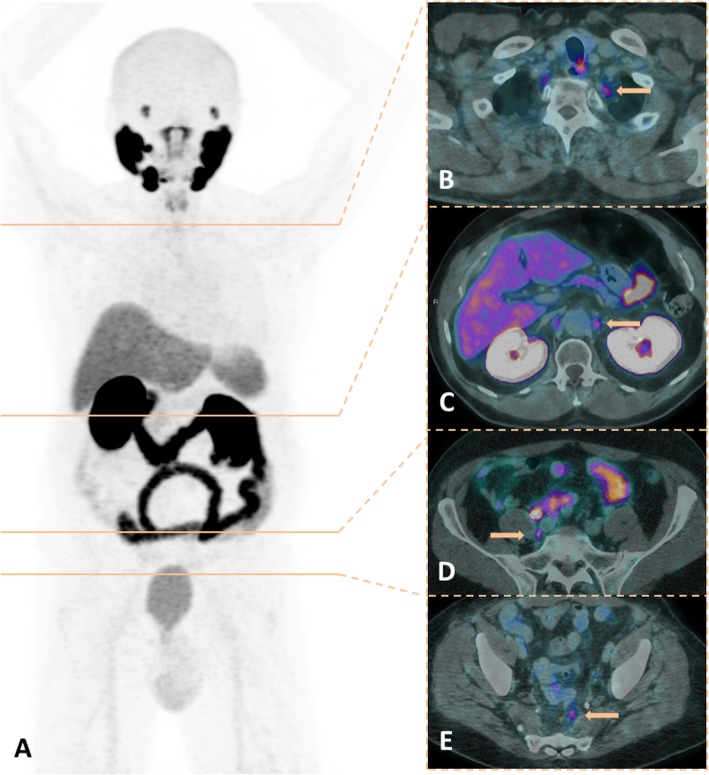
Fig. 1 An overview of physiological PSMA uptake in sympathetic ganglia. 68Ga-PSMA-PET MIP (a) with corresponding levels on fused PET/CT images (b, stelate ganglia; c, celiac ganglia; d, hypogastric ganglia; e, sacral ganglia)
Fig. 1 An overview of physiological PSMA uptake in sympathetic ganglia. 68Ga-PSMA-PET MIP (a) with corresponding levels on fused PET/CT images (b, stelate ganglia; c, celiac ganglia; d, hypogastric ganglia; e, sacral ganglia)CC BY · PubMed Central
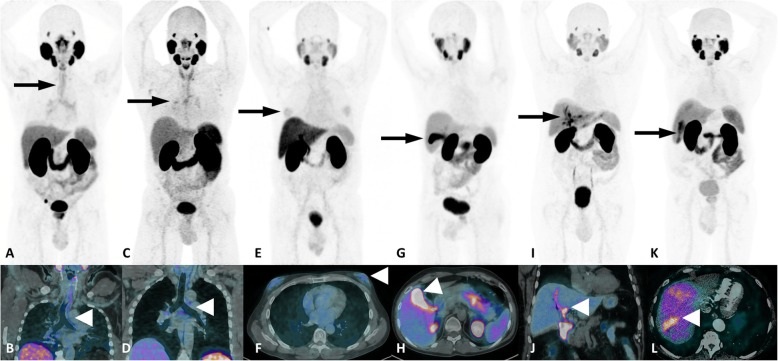
Fig. 2 A miscelanea of normal variants of PSMA uptake. 68Ga-PSMA-PET MIP images on top (a, c, e, g, i and k) and corresponding fused PET/CT images on bottom (b, d, f, h and l) showing trachea and bronchi (a, b), mediastinal lymph nodes (c, d), gynecomastia (e, f), gallbladder (g, h), billiary tract (i, j) and liver perfusion defect (k, l)
Fig. 2 A miscelanea of normal variants of PSMA uptake. 68Ga-PSMA-PET MIP images on top (a, c, e, g, i and k) and corresponding fused PET/CT images on bottom (b, d, f, h and l) showing trachea and bronchi (a, b), mediastinal lymph nodes (c, d), gynecomastia (e, f), gallbladder (g, h), billiary tract (i, j) and liver perfusion defect (k, l)CC BY · PubMed Central
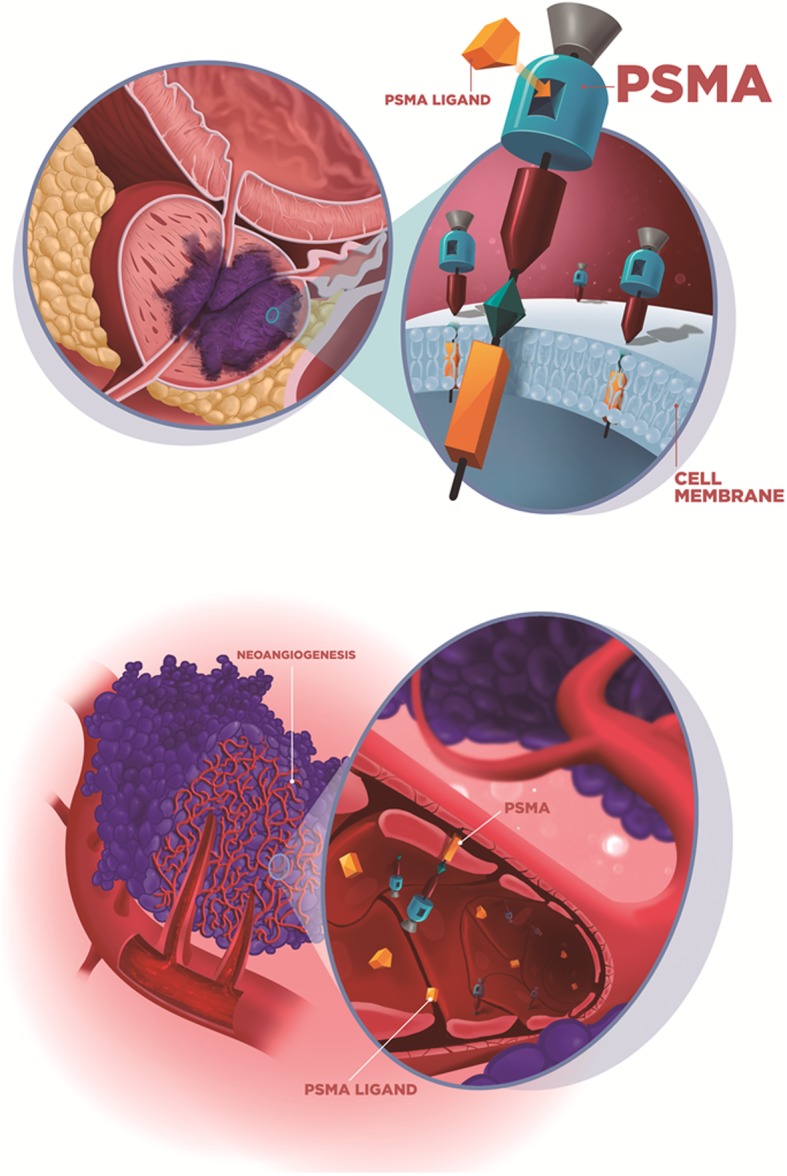
Fig. 3 Ilustration of the two main mechanism os PSMA expression that explains the radiotracer uptake in prostate cancer (a) and other non-prostatic causes with endothelial expression (b)
Fig. 3 Ilustration of the two main mechanism os PSMA expression that explains the radiotracer uptake in prostate cancer (a) and other non-prostatic causes with endothelial expression (b)CC BY · PubMed Central
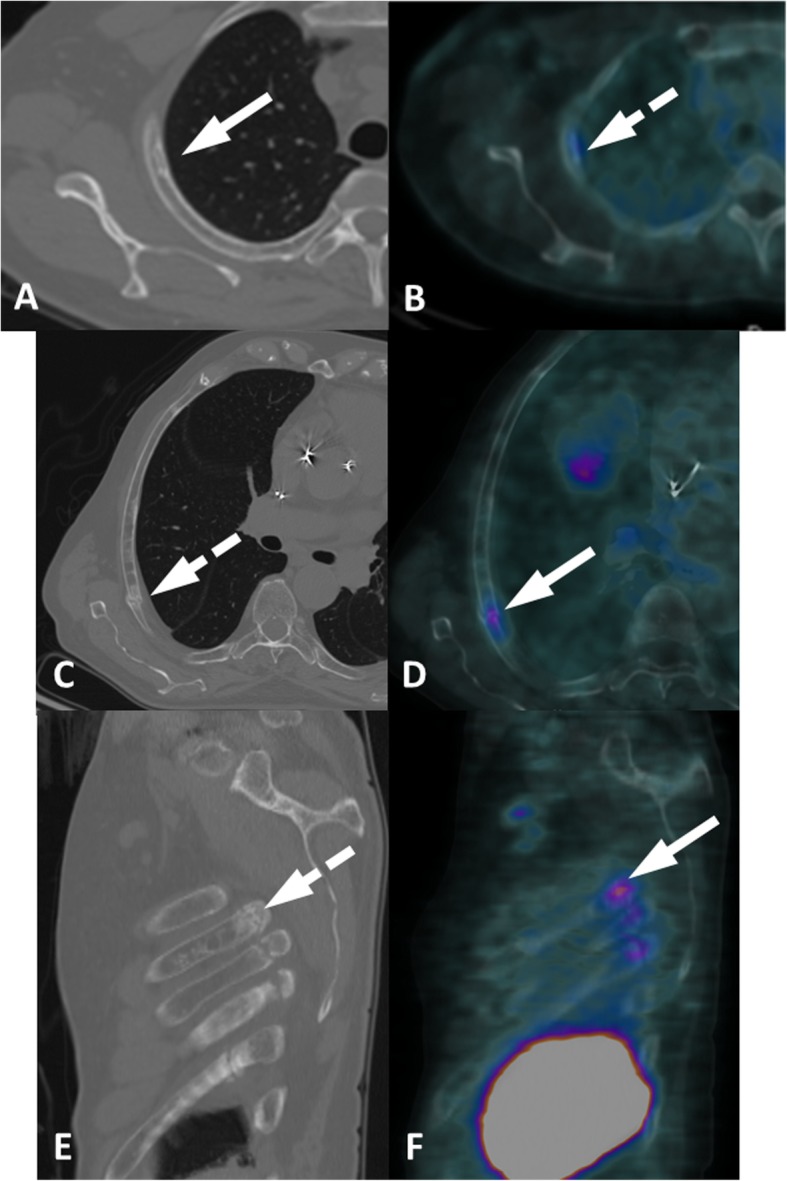
Fig. 4 Focal PSMA uptake in the ribs in two different patients. Patient 1, fibrous osseus defect (a, b). Axial CT (a) and axial 68Ga-PSMA-PET/CT (b) show a single focus of faint uptake (dashed arrow) in a typical fibrous osseous defect of the third right rib (arrow). Patient 2, ribs fractures (c-f). Axial CT (c), sagittal CT (e), axial 68Ga-PSMA-PET/CT (d) and sagittal 68Ga-PSMA-PET/CT (f) show mild uptake (arrows) in continuous ribs fractures (dashed arrows)
Fig. 4 Focal PSMA uptake in the ribs in two different patients. Patient 1, fibrous osseus defect (a, b). Axial CT (a) and axial 68Ga-PSMA-PET/CT (b) show a single focus of faint uptake (dashed arrow) in a typical fibrous osseous defect of the third right rib (arrow). Patient 2, ribs fractures (c-f). Axial CT (c), sagittal CT (e), axial 68Ga-PSMA-PET/CT (d) and sagittal 68Ga-PSMA-PET/CT (f) show mild uptake (arrows) in continuous ribs fractures (dashed arrows)CC BY · PubMed Central
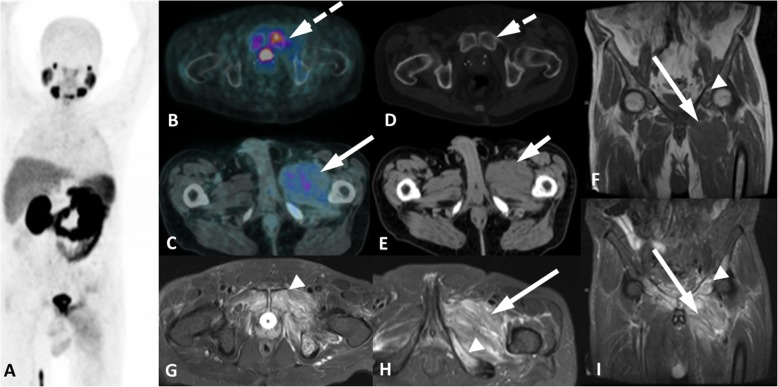
Fig. 5 Osteomyelitis with PSMA uptake. 68Ga-PSMA-PET/CT MIP (a), axial PET/CT (b, c) and axial CT (d, e) images show a lytic lesion in the left pubic bone with bilateral diffuse bone sclerosis (small dashed arrow) with mild uptake (dashed arrow). Additionally, there is edema in the right adductors muscles (arrow) with discrete and heterogeneous uptake (short arrow). These findings - osteomyelitis (arrowheads) and inflamation in the adjacent soft-tissue (long arrows) - were confirmed on MR images in coronal T1w (f) axial (g, h) and coronal (i) T2w Fat Sat
Fig. 5 Osteomyelitis with PSMA uptake. 68Ga-PSMA-PET/CT MIP (a), axial PET/CT (b, c) and axial CT (d, e) images show a lytic lesion in the left pubic bone with bilateral diffuse bone sclerosis (small dashed arrow) with mild uptake (dashed arrow). Additionally, there is edema in the right adductors muscles (arrow) with discrete and heterogeneous uptake (short arrow). These findings - osteomyelitis (arrowheads) and inflamation in the adjacent soft-tissue (long arrows) - were confirmed on MR images in coronal T1w (f) axial (g, h) and coronal (i) T2w Fat SatCC BY · PubMed Central
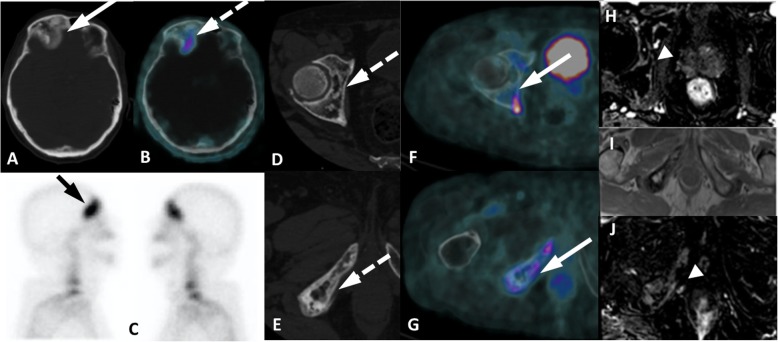
Fig. 6 Bone PSMA uptake in correlation with morphology and other imaging modalities in two different patients. Patient 1, fibrous dysplasia (a-c). Axial CT (a) and axial 68Ga-PSMA-PET/CT (b) show a homogeneously sclerotic lesion with well-defined borders (arrow) and mild PSMA uptake (dashed arrow), suggestive of fibrous dysplasia. Previous MDP-bone scan lateral images (c) showed an intense osteogenic reaction (black arrow) in the right frontal bone, which is impossible to differentiate from a bone metastatis without a CT. Patient 2, Paget’s disease (d-j). Axial CT (d, e), axial 68Ga-PSMA-PET/CT (f, g) and axial T1w MR (i) images show mild uptake (arrows) in the cortical thickening and sclerosis of the right ischium (dashed arrows). Axial perfusion (h, j) MR images show an increased vascularization exactly in the same areas of the PSMA uptake (arrowheads). These findings are highly suggestive of Paget’s disease
Fig. 6 Bone PSMA uptake in correlation with morphology and other imaging modalities in two different patients. Patient 1, fibrous dysplasia (a-c). Axial CT (a) and axial 68Ga-PSMA-PET/CT (b) show a homogeneously sclerotic lesion with well-defined borders (arrow) and mild PSMA uptake (dashed arrow), suggestive of fibrous dysplasia. Previous MDP-bone scan lateral images (c) showed an intense osteogenic reaction (black arrow) in the right frontal bone, which is impossible to differentiate from a bone metastatis without a CT. Patient 2, Paget’s disease (d-j). Axial CT (d, e), axial 68Ga-PSMA-PET/CT (f, g) and axial T1w MR (i) images show mild uptake (arrows) in the cortical thickening and sclerosis of the right ischium (dashed arrows). Axial perfusion (h, j) MR images show an increased vascularization exactly in the same areas of the PSMA uptake (arrowheads). These findings are highly suggestive of Paget’s diseaseCC BY · PubMed Central
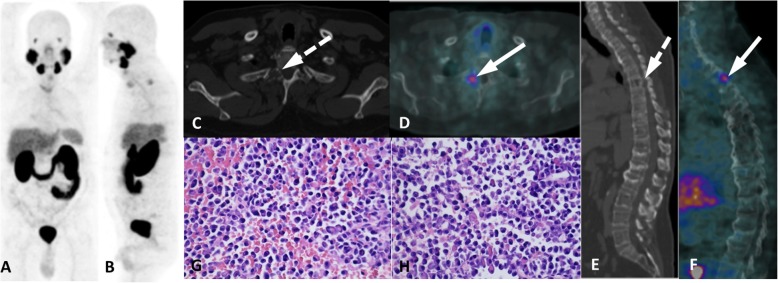
Fig. 7 Multiple myeloma with PSMA uptake. 68Ga-PSMA PET/CT (a, b), axial CT (c), axial PET/CT (d), sagittal (e) and sagittal PET/CT (f) images show multiple osteolytic lesions (dashed arrows) in the whole axial skeleton but there is a mild uptake in the right pedicle of T2 (arrows), confirmed as multiple myeloma after imaging-guided biopsy (g, h)
Fig. 7 Multiple myeloma with PSMA uptake. 68Ga-PSMA PET/CT (a, b), axial CT (c), axial PET/CT (d), sagittal (e) and sagittal PET/CT (f) images show multiple osteolytic lesions (dashed arrows) in the whole axial skeleton but there is a mild uptake in the right pedicle of T2 (arrows), confirmed as multiple myeloma after imaging-guided biopsy (g, h)CC BY · PubMed Central
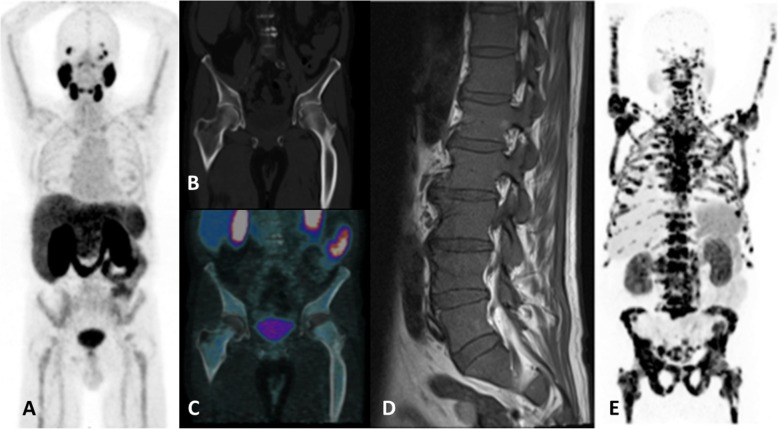
Fig. 8 Patterns of diffuse bone PSMA uptake in two different patients. 68Ga-PSMA-PET/CT MIP (a), coronal CT (b) and coronal PET/CT (d) images show dense and inhomogeneous bone marrow throughout the skeleton with a discrete diffuse uptake, in a patient with a previous diagnosis of myelodysplasia syndrome. A T1w (d) MRI corroborates showing a diffuse infiltration of the bone marrow. A neoplastic infiltration in a different patient is shown on another 68Ga-PSMA-PET/CT MIP (e) to highlight the uptake pattern differences
Fig. 8 Patterns of diffuse bone PSMA uptake in two different patients. 68Ga-PSMA-PET/CT MIP (a), coronal CT (b) and coronal PET/CT (d) images show dense and inhomogeneous bone marrow throughout the skeleton with a discrete diffuse uptake, in a patient with a previous diagnosis of myelodysplasia syndrome. A T1w (d) MRI corroborates showing a diffuse infiltration of the bone marrow. A neoplastic infiltration in a different patient is shown on another 68Ga-PSMA-PET/CT MIP (e) to highlight the uptake pattern differencesCC BY · PubMed Central
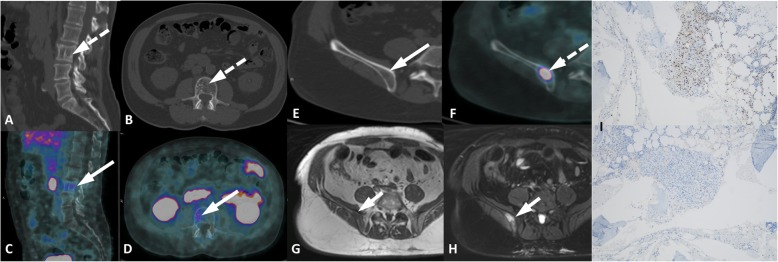
Fig. 9 Different patterns of osseous hemangioma in two patients. Patient 1, spinal hemangioma (a-d). Sagittal CT (a), axial CT (b), sagital PET/CT (c), e axial PET/CT (d) show mild uptake (arrows) in a thickened vertical trabeculae lesion (dashed arrows) surrounded by fat marrow in the right side of L3, typical of hemangioma. Patient 2, iliac hemangioma (e-i). Axial CT (e) and axial PET/CT (f) images showi a lytic lesion (arrow) in the right iliac bone with intense uptake (dashed arrow) and axial T1w (g) and T2w Fat Sat (h) MR images demonstrated a bone lesion without aggressiveness (short arrows). Bone hemangioma was confirmed with percutaneous biopsy and immunohistochemistry (i) showed PSMA expression on the endothelial cells membrane
Fig. 9 Different patterns of osseous hemangioma in two patients. Patient 1, spinal hemangioma (a-d). Sagittal CT (a), axial CT (b), sagital PET/CT (c), e axial PET/CT (d) show mild uptake (arrows) in a thickened vertical trabeculae lesion (dashed arrows) surrounded by fat marrow in the right side of L3, typical of hemangioma. Patient 2, iliac hemangioma (e-i). Axial CT (e) and axial PET/CT (f) images showi a lytic lesion (arrow) in the right iliac bone with intense uptake (dashed arrow) and axial T1w (g) and T2w Fat Sat (h) MR images demonstrated a bone lesion without aggressiveness (short arrows). Bone hemangioma was confirmed with percutaneous biopsy and immunohistochemistry (i) showed PSMA expression on the endothelial cells membraneCC BY · PubMed Central
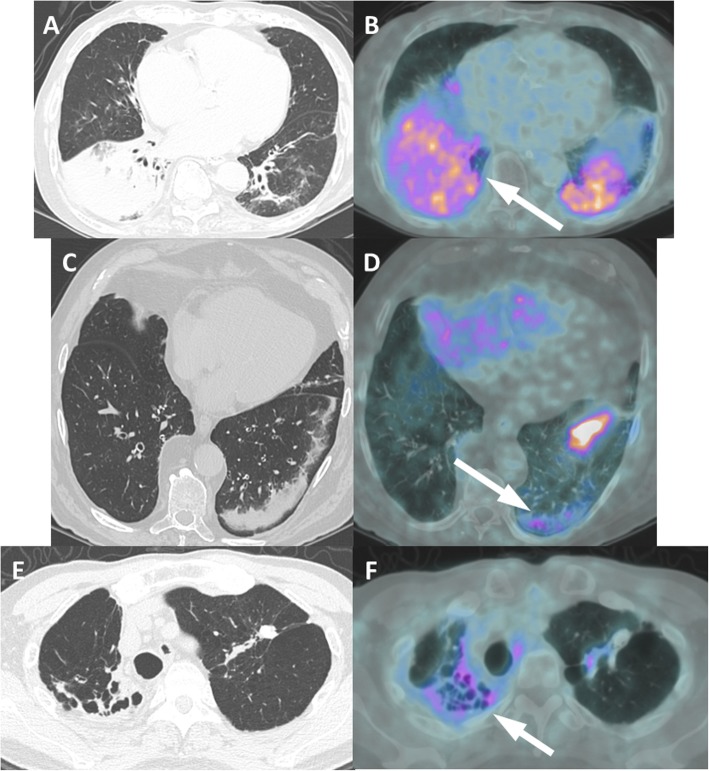
Fig. 10 Pulmonary diseases with PSMA uptake. Patient 1, pulmonary consolidation (a, b). Axial CT (a) and PET/CT (b) show a pulmonary consolidation with air bronchogram in both lower lobes (arrow on B) of the lungs in a 90-year-old patient presenting cough and fever. Patient 2, pulmonary atelectasis (c, d). Axial CT (c) and PET/CT (d) show a laminar atelectasis in both lower lobes of the lungs with tiny PSMA uptake (arrow on D). Patient 3, tuberculosis sequelae (e, f). Axial CT (e) and PET/CT (f) show retractile bronchiectasis in the upper bilateral lung lobes with a few calcifications and mild uptake (arrow on F), suggestive of tuberculosis sequelae
Fig. 10 Pulmonary diseases with PSMA uptake. Patient 1, pulmonary consolidation (a, b). Axial CT (a) and PET/CT (b) show a pulmonary consolidation with air bronchogram in both lower lobes (arrow on B) of the lungs in a 90-year-old patient presenting cough and fever. Patient 2, pulmonary atelectasis (c, d). Axial CT (c) and PET/CT (d) show a laminar atelectasis in both lower lobes of the lungs with tiny PSMA uptake (arrow on D). Patient 3, tuberculosis sequelae (e, f). Axial CT (e) and PET/CT (f) show retractile bronchiectasis in the upper bilateral lung lobes with a few calcifications and mild uptake (arrow on F), suggestive of tuberculosis sequelaeCC BY · PubMed Central
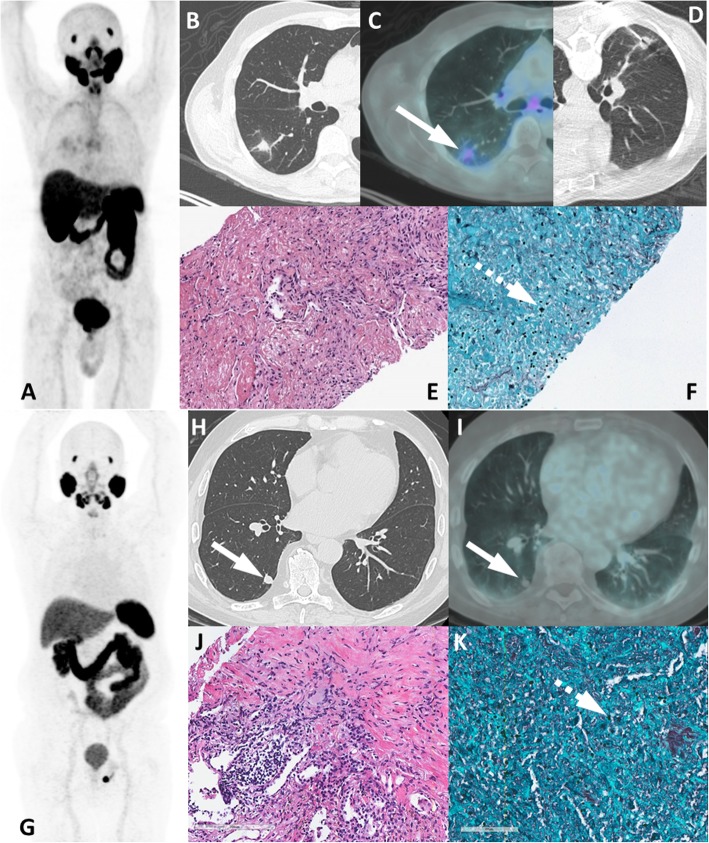
Fig. 11 Two different patients with pulmonary histoplasmosis. On top, a 70-year-old patient under staging of prostate cancer (iPSA = 7.0 ng/mL, Gleason 8 = 4 + 4). 68Ga-PSMA-PET MIP (a), axial CT (b), axial PET/CT (c) and CT-guided biopsy (d) images show an irregular pulmonary nodule with faint uptake (arrow). See also the primary tumor on A (arrowhead). On bottom, a 64-year-old patient with biochemical recurrence (PSA = 0.66 ng/mL, Gleason 9 = 4 + 5) 8 years after radical prostatectomy and under androgen deprivation therapy (Abiraterone) for the last 2 years. 68Ga-PSMA-PET MIP (g), axial CT (h) and PET/CT (i) images show a rounded lung nodule in the lower lobe of the right lung without PSMA utpake (arrows). Histology images (e, f, j, k) show a positive Grocott stain, with multiple yeasts (dashed arrow) and areas of focal neutrophils conglomerates, consistent with histoplasmosis
Fig. 11 Two different patients with pulmonary histoplasmosis. On top, a 70-year-old patient under staging of prostate cancer (iPSA = 7.0 ng/mL, Gleason 8 = 4 + 4). 68Ga-PSMA-PET MIP (a), axial CT (b), axial PET/CT (c) and CT-guided biopsy (d) images show an irregular pulmonary nodule with faint uptake (arrow). See also the primary tumor on A (arrowhead). On bottom, a 64-year-old patient with biochemical recurrence (PSA = 0.66 ng/mL, Gleason 9 = 4 + 5) 8 years after radical prostatectomy and under androgen deprivation therapy (Abiraterone) for the last 2 years. 68Ga-PSMA-PET MIP (g), axial CT (h) and PET/CT (i) images show a rounded lung nodule in the lower lobe of the right lung without PSMA utpake (arrows). Histology images (e, f, j, k) show a positive Grocott stain, with multiple yeasts (dashed arrow) and areas of focal neutrophils conglomerates, consistent with histoplasmosisCC BY · PubMed Central
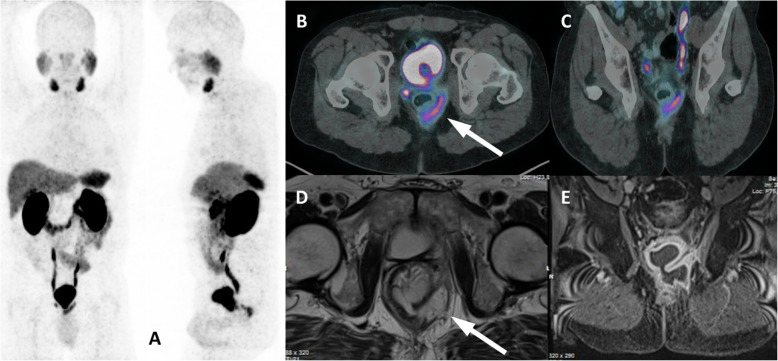
Fig. 12 Perianal fistula with PSMA uptake. 68Ga-PSMA-PET MIP (a), axial PET/CT (b), coronal PET/CT (c) and axial T2w MR (d) and coronal T1w with gadolinum (e) show a perirectal fistula in the posterior left ischiorectal fossa (arrows)
Fig. 12 Perianal fistula with PSMA uptake. 68Ga-PSMA-PET MIP (a), axial PET/CT (b), coronal PET/CT (c) and axial T2w MR (d) and coronal T1w with gadolinum (e) show a perirectal fistula in the posterior left ischiorectal fossa (arrows)CC BY · PubMed Central
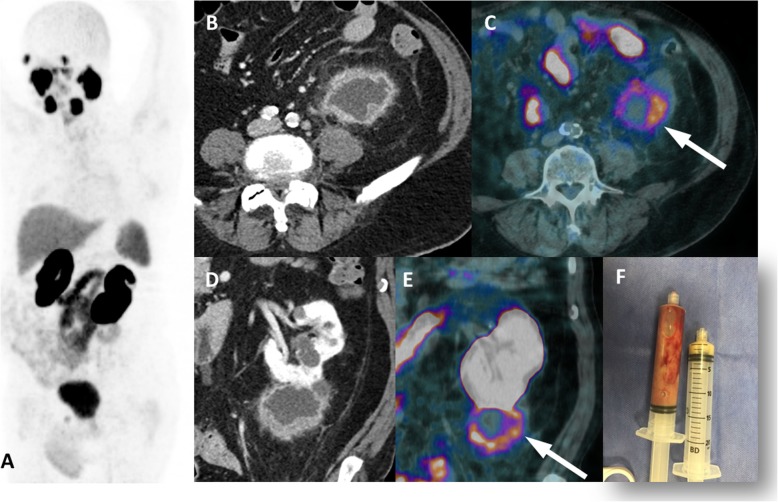
Fig. 13 Renal abscess with PSMA uptake. 68Ga-PSMA-PET MIP (a), axial and coronal contrast-enhanced CT (b, c), axial and coronal PET/CT (d, e) images show a complex cystic mass on the lower pole of the left kidney presenting moderate peripheric PSMA uptake (arrows), with purulent content after percutaneous drainage (f)
Fig. 13 Renal abscess with PSMA uptake. 68Ga-PSMA-PET MIP (a), axial and coronal contrast-enhanced CT (b, c), axial and coronal PET/CT (d, e) images show a complex cystic mass on the lower pole of the left kidney presenting moderate peripheric PSMA uptake (arrows), with purulent content after percutaneous drainage (f)CC BY · PubMed Central
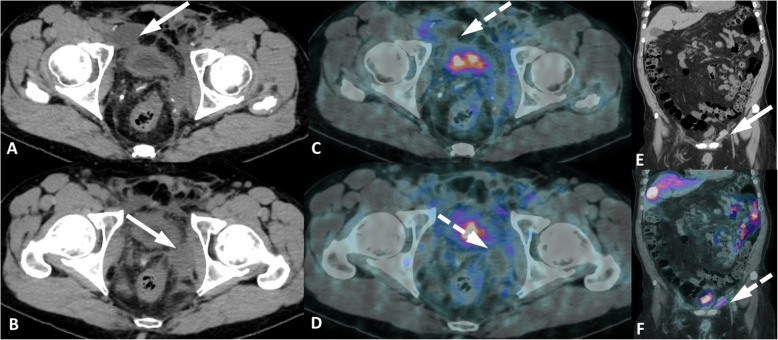
Fig. 14 Post-operative inflammatory findings in two patients. Patient 1, prostatic bed inflammation immediate after radical prostatectomy (a-d). Axial CT (a, b) axial PET/CT (c, d) show faint uptake around bilateral lymphoceles (arrows) and inflammatory changes at bilateral pelvic walls (dashed arrows). Patient 2, inflammatory foreign body reaction of mesh material from left inguinal hernia surgery (e, f). Coronal CT (e) and PET/CT (f) images show an elongated hyperattenuating material along the left inguinal canal (arrow) with mild uptake (dashed arrow)
Fig. 14 Post-operative inflammatory findings in two patients. Patient 1, prostatic bed inflammation immediate after radical prostatectomy (a-d). Axial CT (a, b) axial PET/CT (c, d) show faint uptake around bilateral lymphoceles (arrows) and inflammatory changes at bilateral pelvic walls (dashed arrows). Patient 2, inflammatory foreign body reaction of mesh material from left inguinal hernia surgery (e, f). Coronal CT (e) and PET/CT (f) images show an elongated hyperattenuating material along the left inguinal canal (arrow) with mild uptake (dashed arrow)CC BY · PubMed Central
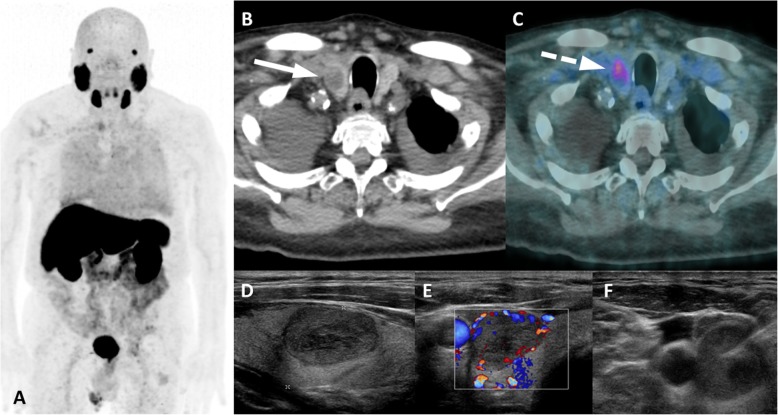
Fig. 15 Thyroid benign adenoma with PSMA uptake. 68Ga-PSMA-PET MIP (a), axial CT (b) and axial PET/CT (c) images show nodulae with mild uptake (dashed arrow) in the right thyroid lobe (arrow). Thyroid ultrasound revealed a hypoecogenic nodule with cystic areas (d) and peripheric vascularization (d). Fine needle aspiration of the thyroid nodule (e) revealed follicular adenoma without malignant cells
Fig. 15 Thyroid benign adenoma with PSMA uptake. 68Ga-PSMA-PET MIP (a), axial CT (b) and axial PET/CT (c) images show nodulae with mild uptake (dashed arrow) in the right thyroid lobe (arrow). Thyroid ultrasound revealed a hypoecogenic nodule with cystic areas (d) and peripheric vascularization (d). Fine needle aspiration of the thyroid nodule (e) revealed follicular adenoma without malignant cellsCC BY · PubMed Central
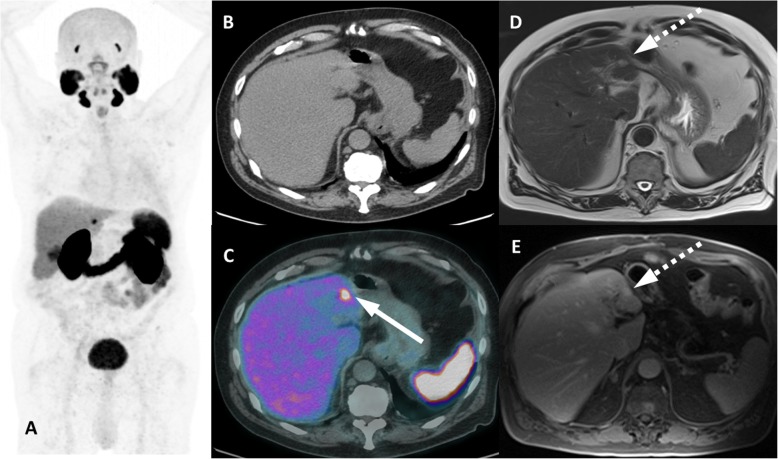
Fig. 16 Benign hepatic hemangioma with PSMA uptake. 68Ga-PSMA-PET MIP (a) and axial PET/CT (c) images show an isolated moderate focal uptake on the left liver lobe (arrow) not seen on non-contrast enhanced CT in (b), which was subsequently caractherized as a typical hemangioma (dashed arrows) in axial T2w (d) and axial T1w after gadolinum (e). Contrast-enhanced CT performed 10 years earlier (not shown) had already characterized the lesion
Fig. 16 Benign hepatic hemangioma with PSMA uptake. 68Ga-PSMA-PET MIP (a) and axial PET/CT (c) images show an isolated moderate focal uptake on the left liver lobe (arrow) not seen on non-contrast enhanced CT in (b), which was subsequently caractherized as a typical hemangioma (dashed arrows) in axial T2w (d) and axial T1w after gadolinum (e). Contrast-enhanced CT performed 10 years earlier (not shown) had already characterized the lesionCC BY · PubMed Central
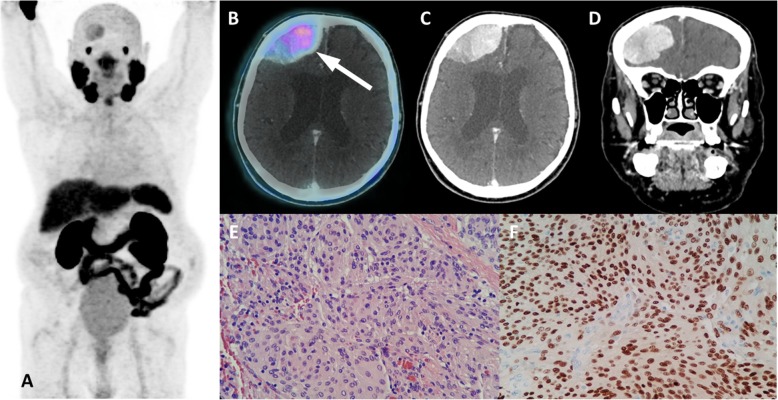
Fig. 17 Typical meningioma with PSMA uptake. 68Ga-PSMA PET MIP (a), axial PET/CT (b) and axial and coronal contrast-enhanced CT (c, d) images show right frontal extra-axial vascularized lesion with dural tail (arrow), presenting mild uptake. Histopathology and immunmohistochemistry images (e, f) from tumor ressection depicted meningothelial cells with high progesterone stainning, confirming meningioma
Fig. 17 Typical meningioma with PSMA uptake. 68Ga-PSMA PET MIP (a), axial PET/CT (b) and axial and coronal contrast-enhanced CT (c, d) images show right frontal extra-axial vascularized lesion with dural tail (arrow), presenting mild uptake. Histopathology and immunmohistochemistry images (e, f) from tumor ressection depicted meningothelial cells with high progesterone stainning, confirming meningiomaCC BY · PubMed Central
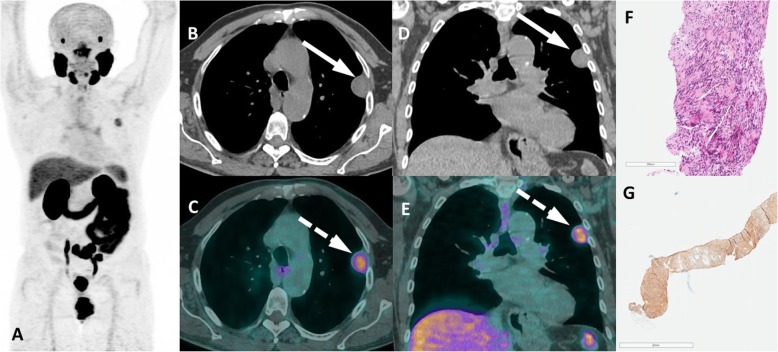
Fig. 18 Intercostal schwanomma with PSMA uptake. 68Ga-PSMA PET MIP (a), axial and coronal CT (b, d) and PET/CT (c, e) show extrapulmonar intercostal lesion (arrows) with moderate uptake (dashed arrows), which was confirmed as a schwannoma by percutaneous biopsy. Histopathology showing spindled Schwann cells (f) with positivity S100 immunohistochemistry staining (g)
Fig. 18 Intercostal schwanomma with PSMA uptake. 68Ga-PSMA PET MIP (a), axial and coronal CT (b, d) and PET/CT (c, e) show extrapulmonar intercostal lesion (arrows) with moderate uptake (dashed arrows), which was confirmed as a schwannoma by percutaneous biopsy. Histopathology showing spindled Schwann cells (f) with positivity S100 immunohistochemistry staining (g)CC BY · PubMed Central
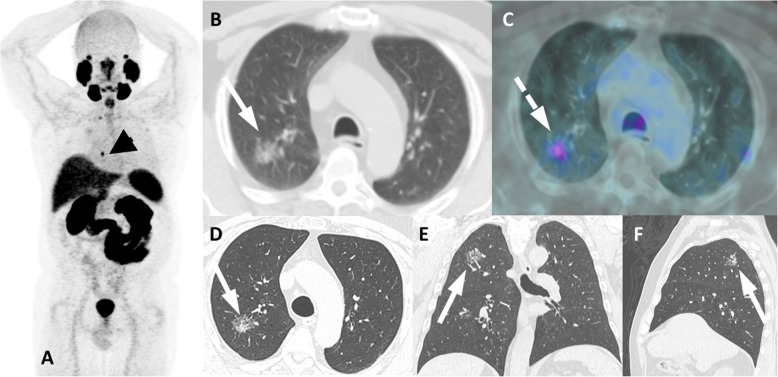
Fig. 19 Lung adenocarcinoma with PSMA uptake. 68Ga-PSMA-PET MIP (a), axial CT (b) and axial PET/CT (c) and axial, coronal and sagittal dedicated lung CT (d, e and f) show a slight uptake (dashed arrow) in peribronchial subsolid pulmonary nodule in the posterior segment of the right upper lobe (arrows), which biopsy revealed primary lung adenocarcinoma. Note also a confirmed prostate cancer metastatic right pulmonary hilar lymph node with intense uptake (arrowhead in A)
Fig. 19 Lung adenocarcinoma with PSMA uptake. 68Ga-PSMA-PET MIP (a), axial CT (b) and axial PET/CT (c) and axial, coronal and sagittal dedicated lung CT (d, e and f) show a slight uptake (dashed arrow) in peribronchial subsolid pulmonary nodule in the posterior segment of the right upper lobe (arrows), which biopsy revealed primary lung adenocarcinoma. Note also a confirmed prostate cancer metastatic right pulmonary hilar lymph node with intense uptake (arrowhead in A)CC BY · PubMed Central
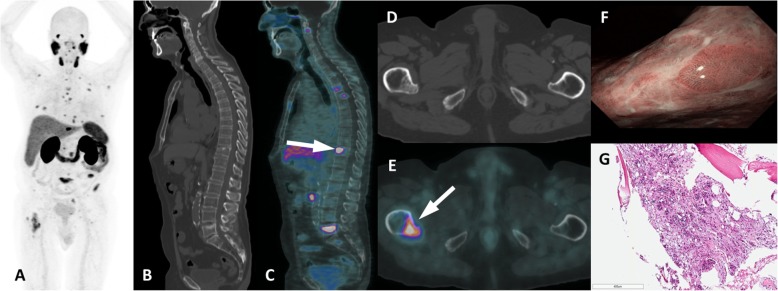
Fig. 20 Signet-cell gastric adenocarcinoma with bone metastases in a 82-year-old patient with prostate cancer 5 years after radical prostatectomy and biochemical recurrence (PSA = 0.67 ng/mL). 68Ga-PSMA-PET/CT MIP (a), coronal and axial CT (b, d) and coronal and axial PET/CT (c, e) images show multiple osteoblastic lesions with intense uptake (arrows in C and E). The patient performed an endoscopy (f) due to dyspeptic symptoms and diagnosed a signet cell gastric carcinoma. Additionally, the discrepancy between low PSA level and high tumor burden on PSMA PET imaging, patient underwent a left femur percutaneous biopsy that histopathology confirmed metastatic adenocarcinoma from gastric origin (g)
Fig. 20 Signet-cell gastric adenocarcinoma with bone metastases in a 82-year-old patient with prostate cancer 5 years after radical prostatectomy and biochemical recurrence (PSA = 0.67 ng/mL). 68Ga-PSMA-PET/CT MIP (a), coronal and axial CT (b, d) and coronal and axial PET/CT (c, e) images show multiple osteoblastic lesions with intense uptake (arrows in C and E). The patient performed an endoscopy (f) due to dyspeptic symptoms and diagnosed a signet cell gastric carcinoma. Additionally, the discrepancy between low PSA level and high tumor burden on PSMA PET imaging, patient underwent a left femur percutaneous biopsy that histopathology confirmed metastatic adenocarcinoma from gastric origin (g)CC BY · PubMed Central
Fig. 21 Neuroendocrine liver metastases in 68Ga-PSMA and 68Ga-DOTATATE PET. 68Ga-PSMA PET MIP (a), axial CT (b, c) and axial PET/CT (d, e) show a high uptake (dashed arrows) in metastatic liver lesions of neuroendocrine tumor (arrows). Note also the primary prostate tumor (arrowhead in A). 68Ga-DOTATATE PET MIP (f) 2 years before showing that these hepatic lesions had also high somatostatin receptors expression
Fig. 21 Neuroendocrine liver metastases in 68Ga-PSMA and 68Ga-DOTATATE PET. 68Ga-PSMA PET MIP (a), axial CT (b, c) and axial PET/CT (d, e) show a high uptake (dashed arrows) in metastatic liver lesions of neuroendocrine tumor (arrows). Note also the primary prostate tumor (arrowhead in A). 68Ga-DOTATATE PET MIP (f) 2 years before showing that these hepatic lesions had also high somatostatin receptors expressionCC BY · PubMed Central
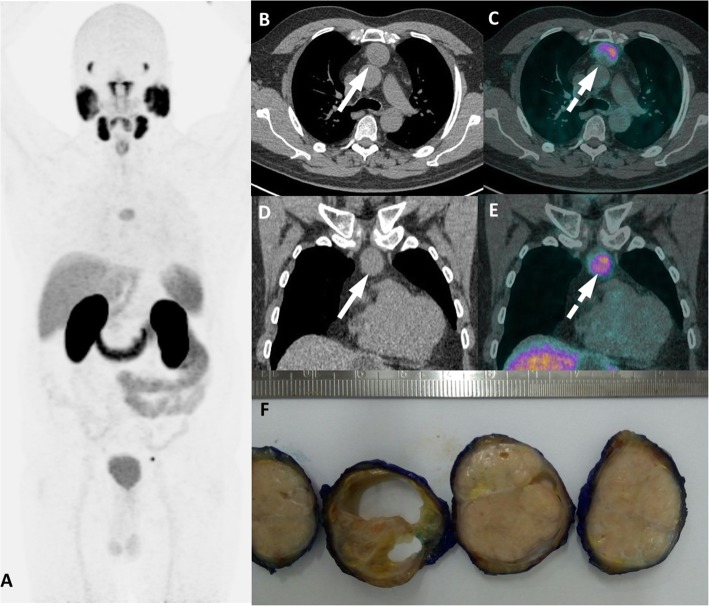
Fig. 22 Thymic carcinoma with PSMA uptake. 68Ga-PSMA-PET/CT MIP (a), axial and coronal CT (b, d) and axial and coronal PET/CT (c, e) images show an anterior mediastinal mass (arrows) with mild uptake (dashed arrows). As an atypical spread for prostate cancer, this lesion was first biopsied and then resected diagnosed as thymoma as shown in pathology macroscopy (f). Case courtesy of Bernardo Bacelar, MD and Thiago F. Nunes, MD
Fig. 22 Thymic carcinoma with PSMA uptake. 68Ga-PSMA-PET/CT MIP (a), axial and coronal CT (b, d) and axial and coronal PET/CT (c, e) images show an anterior mediastinal mass (arrows) with mild uptake (dashed arrows). As an atypical spread for prostate cancer, this lesion was first biopsied and then resected diagnosed as thymoma as shown in pathology macroscopy (f). Case courtesy of Bernardo Bacelar, MD and Thiago F. Nunes, MDCC BY · PubMed Central
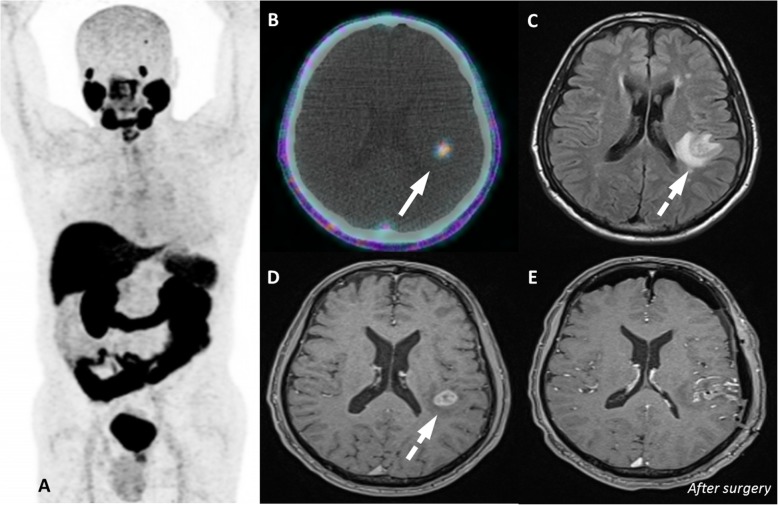
Fig. 23 Glioblastoma multiforme with PSMA uptake. 68Ga-PSMA PET MIP (a), axial PET/CT (b), axial FLAIR (c) and T1w after gadolinium (d) images show a mild uptake in a cortico-subcortical lesion on the left parietal lobe (arrows) corresponding to a necrotic lesion with anelar enhancement and adjacent vasogenic edema (dashed arrows), confirmed as a Glioblastoma after surgical resection (e)
Fig. 23 Glioblastoma multiforme with PSMA uptake. 68Ga-PSMA PET MIP (a), axial PET/CT (b), axial FLAIR (c) and T1w after gadolinium (d) images show a mild uptake in a cortico-subcortical lesion on the left parietal lobe (arrows) corresponding to a necrotic lesion with anelar enhancement and adjacent vasogenic edema (dashed arrows), confirmed as a Glioblastoma after surgical resection (e)CC BY · PubMed Central
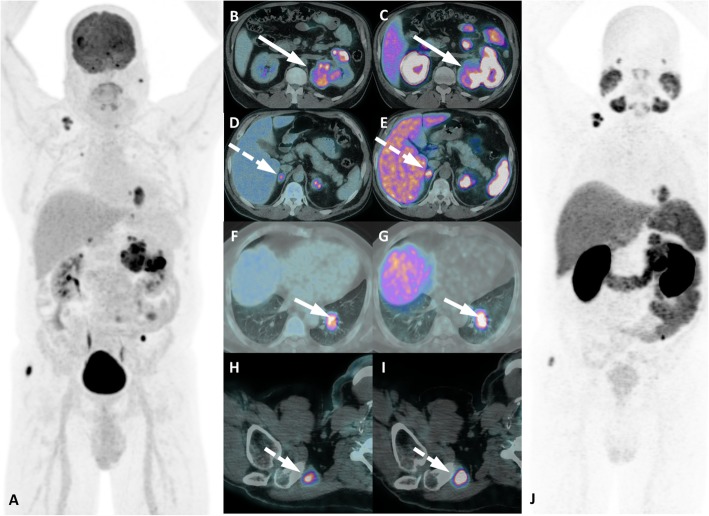
Fig. 24 Metastatic clear renal cell carcinoma staging with 18F-FDG and 68Ga-PSMA-PET/CT. 18F-FDG-PET/CT MIP (a) and axial PET/CT at different levels (b, d, f and h) and 68Ga-PSMA-PET/CT MIP (J), axial PET/CT (c, e, g and i) images show the high uptake of both tracers in all malignant lesions, highlighting the primary kidney lesion (long arrows), adrenals (long dashed arrows), lung (small arrows) and a soft tissue metastatic lesions (small dashed arrows)
Fig. 24 Metastatic clear renal cell carcinoma staging with 18F-FDG and 68Ga-PSMA-PET/CT. 18F-FDG-PET/CT MIP (a) and axial PET/CT at different levels (b, d, f and h) and 68Ga-PSMA-PET/CT MIP (J), axial PET/CT (c, e, g and i) images show the high uptake of both tracers in all malignant lesions, highlighting the primary kidney lesion (long arrows), adrenals (long dashed arrows), lung (small arrows) and a soft tissue metastatic lesions (small dashed arrows)CC BY · PubMed Central
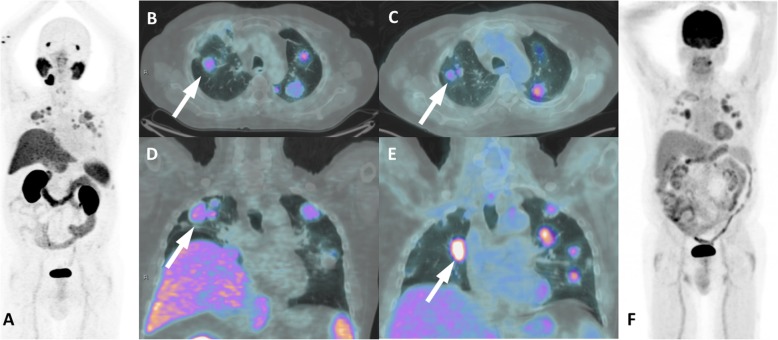
Fig. 25 Metastatic adenoid cystic carcinoma in 68Ga-PSMA and 18F-FDG-PET/CT. 68Ga-PSMA-PET/CT MIP (a), axial and coronal PET/CT (b, d) and 18F-FDG-PET/CT MIP (f), axial and coronal PET/CT (c, e) images show multiple solid nodules (arrows) with a heterogeneous moderate to intense uptake of both tracers. This patient was referred to treatment with Lu-PSMA after progressive disease despite all previous treatments
Fig. 25 Metastatic adenoid cystic carcinoma in 68Ga-PSMA and 18F-FDG-PET/CT. 68Ga-PSMA-PET/CT MIP (a), axial and coronal PET/CT (b, d) and 18F-FDG-PET/CT MIP (f), axial and coronal PET/CT (c, e) images show multiple solid nodules (arrows) with a heterogeneous moderate to intense uptake of both tracers. This patient was referred to treatment with Lu-PSMA after progressive disease despite all previous treatmentsCC BY · PubMed Central

Verification

Claims the paper makes

The claims and statistics of this paper haven’t been checked yet.

Run the check — free, no account needed. It reads the open-access text and checks the sources it cites.

A few free checks a day · papers already verified open instantly · results are public

Claims other papers make about this one

Each is checked against this paper’s own text: does it say what the citing paper says it does?

Self-check

Percentages, sums and reported differences re-computed from the paper’s own numbers.

The self-check needs the paper’s full text.

Citations

Cites

Show all 75 references

Research works printed but not linked: 1

  1. Ruf J, Huber-Schumacher S, Stoykow C, Almanasreh N, Jilg C. Strong PSMA Radioligand uptake by rectal carcinoma. Clin Nucl Med. 2016;42:225–6.

Cited by

See all 288

Metadata

Authors
de Galiza Barbosa, F., Queiroz, M. A., Nunes, R. F., Costa, L. B., Zaniboni, E. C., Marin, J. F. G., Cerri, G. G., & Buchpiguel, C. A.
Affiliations
Hospital Sírio-Libanês (BR)
Corresponding author
Queiroz, Marcelo Araujo
Venue
Cancer Imaging
Published
2020-03-14
Volume
20
Issue
1
Pages
23-23
ISSN
1470-7330 (ISSN-L)
OpenAlex
W3011546611
Cited by
288
References
75
Citations by year
2026: 27 · 2025: 48 · 2024: 67 · 2023: 53 · 2022: 51 · 2021: 27 · 2020: 15
FWCI
5.38
Type
journal article
Language
en
Open access
Licence
Locations
  • Cancer Imaging (publishedVersion, cc-by)
  • PubMed Central (publishedVersion, cc-by)
  • PubMed (publishedVersion)
  • DOAJ (DOAJ: Directory of Open Access Journals) (submittedVersion, cc-by-sa)
Topics
  • Health Sciences › Medicine › Radiology, Nuclear Medicine and Imaging › Medical Imaging Techniques and Applications
  • Health Sciences › Medicine › Radiology, Nuclear Medicine and Imaging › Radiopharmaceutical Chemistry and Applications
  • Health Sciences › Medicine › Urology › Prostate Cancer Diagnosis and Treatment
Keywords
PSMA PET, prostate-specific membrane antigen, prostate cancer, theranostics, benign and malignant tumors
MeSH terms
Positron Emission Tomography Computed Tomography, Gallium Isotopes, Gallium Radioisotopes, Humans, Membrane Glycoproteins, Neoplasms, Organometallic Compounds, Sensitivity and Specificity, Radiopharmaceuticals

About these checks

Registry, retraction, Cites and statistics results are computed, not judged, with one exception: a printed reference that no index lists is read once by a model before it counts as a citation error. Claims are extracted by a model and kept only when their quote appears verbatim in the text; each cited source is then checked, with a model’s help, for whether it says what the claim relies on. Those verdicts can be wrong — read the claim’s quote and the cited source before relying on one.

Statistics and arithmetic are recomputed, not judged.

Confidence bands are shown only for fields calibrated on our annotated test set. None is calibrated yet, so no band is shown.

What counts as a claim ›How we measure confidence ›How we check this ›

Are you an author, or do you see a problem with this page? Request a review

Data sources

Bibliographic data: Semantic Scholar, OpenAlex, Crossref.

Contains information from the Semantic Scholar Academic Graph Datasets, made available under the ODC Attribution License (ODC-BY 1.0).

Semantic Scholar’s data is described in: Kinney, R., et al. (2023). The Semantic Scholar Open Data Platform. arXiv:2301.10140.