

The DOI matches its Crossref record; 44 of the 44 references it cites were found in a registry or an index; 5 of the 30 sources its claims cite were checked for support.
An Internet-Based Cognitive Behavioral Therapy Program Adapted to Patients With Cardiovascular Disease and Depression: Randomized Controlled Trial
Open accessPublished version of a preprint
Abstract
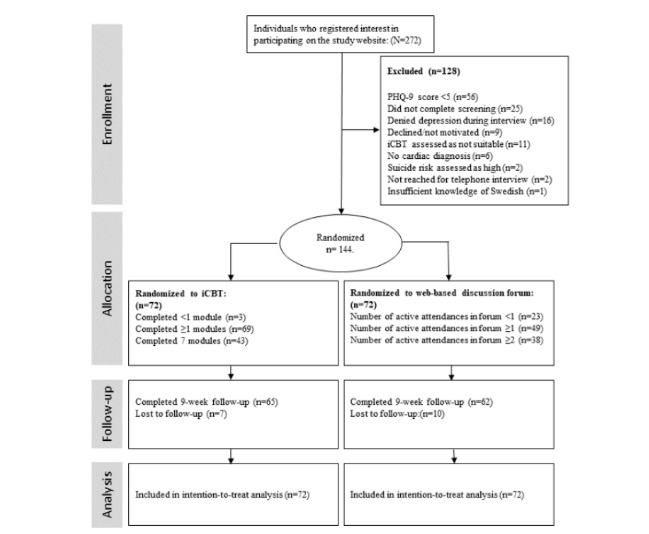
Background: Depression is a common cause of reduced well-being and prognosis in patients with cardiovascular disease (CVD). However, there is a lack of effective intervention strategies targeting depression. Objective: The study aimed to evaluate the effects of a nurse-delivered and adapted internet-based cognitive behavioral therapy (iCBT) program aimed at reducing depression in patients with CVD. Methods: A randomized controlled trial was conducted. A total of 144 patients with CVD with at least mild depression (Patient Health Questionnaire–9 [PHQ-9] score ≥5) were randomized 1:1 to a 9-week program of iCBT (n=72) or an active control participating in a Web-based discussion forum (online discussion forum [ODF], n=72). The iCBT program, which included 7 modules, was adapted to fit patients with CVD. Nurses with an experience of CVD care provided feedback and a short introduction to cognitive behavioral therapy. The primary outcome, depression, was measured using PHQ-9. Secondary outcomes were depression measured using the Montgomery-Åsberg Depression Rating Scale–self-rating version (MADRS-S), health-related quality of life (HRQoL) measured using Short Form 12 (SF-12) survey and EuroQol Visual Analogue Scale (EQ-VAS), and the level of adherence. An intention-to-treat analysis with multiple imputations was used. Between-group differences in the primary and secondary outcomes were determined by the analysis of covariance, and a sensitivity analysis was performed using mixed models. Results: Compared with ODF, iCBT had a significant and moderate treatment effect on the primary outcome depression (ie, PHQ-9; mean group difference=−2.34 [95% CI −3.58 to −1.10], P<.001, Cohen d=0.62). In the secondary outcomes, compared with ODF, iCBT had a significant and large effect on depression (ie, MADRS-S; P<.001, Cohen d=0.86) and a significant and moderate effect on the mental component scale of the SF-12 (P<.001, Cohen d=0.66) and the EQ-VAS (P<.001, Cohen d=0.62). Overall, 60% (n=43) of the iCBT group completed all 7 modules, whereas 82% (n=59) completed at least half of the modules. No patients were discontinued from the study owing to a high risk of suicide or deterioration in depression. Conclusions: Nurse-delivered iCBT can reduce depression and improve HRQoL in patients with CVD, enabling treatment for depression in their own homes and at their preferred time. Trial Registration: ClinicalTrials.gov NCT02778074; https://clinicaltrials.gov/ct2/show/NCT02778074
Overview
CoChat Summary
TL;DR
This randomized controlled trial found that a nurse-delivered, CVD-adapted internet-based CBT program reduced depression more than an online discussion forum in patients with cardiovascular disease and at least mild depressive symptoms. It also improved health-related quality of life, with no patients discontinued because of suicide risk or worsening depression.
Key findings
- Among 144 randomized patients (72 iCBT, 72 online discussion forum), the primary outcome PHQ-9 improved more with iCBT: mean group difference = −2.34 (95% CI −3.58 to −1.10), P<.001, Cohen d=0.62.
- Secondary outcomes also favored iCBT: MADRS-S P<.001, d=0.86; SF-12 mental component scale P<.001, d=0.66; EQ-VAS P<.001, d=0.62. The SF-12 physical component showed a small, nonsignificant improvement (P=.06, d=0.32).
- In per-protocol analyses, clinically significant PHQ-9 improvement occurred in 43% (28/65) of iCBT vs 24% (15/62) of ODF participants (P=.02); nondepressed at follow-up: 35% (23/65) vs 21% (13/62) (P=.02). The reported NNT was 5 for clinical improvement, 7 to become nondepressed, and 3 on MADRS-S.
- Adherence was substantial: 60% (43/72) completed all 7 modules and 82% (59/72) completed at least half; in the ODF group, 27% (20/72) completed 9 or more activities.
Methods
- Randomized controlled trial at 4 hospitals in southeastern Sweden; invitations were mailed to 11,992 patients with atrial fibrillation/flutter, coronary heart disease, or heart failure.
- Eligibility required age ≥18, stable CVD, and at least mild depressive symptoms (PHQ-9 ≥5); 144 patients were randomized 1:1 to 9 weeks of nurse-delivered iCBT (n=72) or an active control online discussion forum (n=72).
- Primary analysis used intention-to-treat with ANCOVA adjusting for baseline scores; missing data were handled with LOCF, and mixed models with multiple imputation were run as sensitivity analyses.
Limitations
- The paper states that patients were included based on self-reported depression rather than a diagnostic depression interview, which may have increased misclassification risk.
- It also notes that high alcohol consumption was not a specific exclusion criterion, although nurses assessed it during telephone screening.
- The paper criticizes the online discussion forum control as possibly too low in activity and lacking feedback, which may have made it closer to care as usual than to an active comparator.
- Evident from the text: recruitment was difficult, with only 272/11,992 (2.26%) expressing interest and 144 ultimately randomized, so generalizability may be limited to patients willing and able to use an internet-based program.
Model-written summary. Check it against the paper before relying on it.
Integrity signals
Registry
Cites
Statistics
Figures


Verification
Claims the paper makes
4 Valid · 0 Not valid · 18 Not checked · 36 Own results and interpretations
The cited sources support only part of this claim — read each source’s verdict below.
In the paper
“A recent systematic review has reported that psychological interventions in CVD, such as cognitive behavioral therapy (CBT), have small effects on depression in patients with CVD [5].”
§ An Internet-Based Cognitive Behavioral Therapy Program Adapted to Patients With Cardiovascular Disease and Depression: Randomized Controlled Trial > Introduction > Psychological Interventions for Depression in Cardiovascular Disease One possible alternative and complementary treatment option is psychological interventions that patients with CVD also seem to prefer to antidepressant treatment [4]. A recent systematic review has reported that psychological interventions in CVD, such as cognitive behavioral therapy (CBT), have small effects on depression in patients with CVD [5]. This, however, does not necessarily mean that CBT is ineffective in CVD. One explanation for the small effects reported may be the heterogeneity of the studies included in the systematic review [5]. Many of them evaluate the complex interventions based on different multiple components, which are often poorly described. Moreover, many of the studies in the review also evaluate non-CBT interventions. It is therefore problematic to determine which types of interventions will work. Another important issue is that many psychological interventional studies of CVD have included samples irrespective of whether the patient has elevated levels of depression or not [5]. This will lead to an increased risk of a floor effect, meaning that participants with no or low levels of depressive symptoms will be unlikely to experience a decrease in depression as a response to the intervention. However, a recent meta-analysis of 12 randomized controlled trials (RCTs) evaluating the effectiveness of CBT on patients with CVD with depression and/or anxiety reported significantly lower depression scores at follow-up compared with controls, which in most cases was care as usual [6]. This suggests that interventions based on CBT or CBT principles could be a treatment option for depression in patients with CVD with increased levels of depressive symptoms. However, one barrier to the implementation of CBT in current clinical and cardiac care is low access to psychotherapists, leading to a treatment-demand gap. A solution could be internet-based CBT (iCBT), which can be provided at low cost and has been proven effective in patients with depression [7,8]. iCBT can be delivered in a guided format (ie, support and/or encouragement and/or feedback on homework assignments [9]) or unguided; however, guided iCBT tends to be more effective [10]. One important aspect that may facilitate the implementation of guided iCBT in clinical care is that it can be delivered by health care professionals with little or no specific training, without reducing the effect of the treatment [11]. Another advantage of iCBT is that it enables patients with CVD to access CBT in their own homes and at a time that suits them. However, generic iCBT programs may not be optimal for targeting depression in patients with chronic diseases, as these programs are not tailored to the context of the disease [12,13].
What the sources say
- Partly supportedcites [5] sourceExperimental — accuracy not yet measured
Our copy supports the core attribution: the Psychological outcomes section (p. ~Results) reports a reduction in depressive symptoms with psychological interventions versus comparator (SMD -0.27, 95% CI -0.39 to -0.15; 19 trials, 5825 participants; GRADE low), and the Discussion 'Summary of main results' describes these as 'small to moderate improvements in the levels of depressive symptoms'. However, two parts are not supported by this source: (1) the review's population is coronary heart disease specifically, not CVD generally, so 'patients with CVD' widens it; (2) the 'such as CBT' exemplar is not this review's finding — its own univariate meta-regression for depression (Table 5) found cognitive challenge/restructuring techniques non-significant (exp(β) 0.07, P = 0.59) and states its data showed no evidence that cognitive interventions were more effective; the CBT-specific small beneficial effect it reports belongs to Dickens 2013, which it cites in 'Agreements and disagreements with other studies or reviews'. (LLM, conf=0.78)
plainstates a cause- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
- Partly supported
The cited sources support only part of this claim — read each source’s verdict below.
In the paper
“One important aspect that may facilitate the implementation of guided iCBT in clinical care is that it can be delivered by health care professionals with little or no specific training, without reducing the effect of the treatment [11].”
§ An Internet-Based Cognitive Behavioral Therapy Program Adapted to Patients With Cardiovascular Disease and Depression: Randomized Controlled Trial > Introduction > Psychological Interventions for Depression in Cardiovascular Disease One possible alternative and complementary treatment option is psychological interventions that patients with CVD also seem to prefer to antidepressant treatment [4]. A recent systematic review has reported that psychological interventions in CVD, such as cognitive behavioral therapy (CBT), have small effects on depression in patients with CVD [5]. This, however, does not necessarily mean that CBT is ineffective in CVD. One explanation for the small effects reported may be the heterogeneity of the studies included in the systematic review [5]. Many of them evaluate the complex interventions based on different multiple components, which are often poorly described. Moreover, many of the studies in the review also evaluate non-CBT interventions. It is therefore problematic to determine which types of interventions will work. Another important issue is that many psychological interventional studies of CVD have included samples irrespective of whether the patient has elevated levels of depression or not [5]. This will lead to an increased risk of a floor effect, meaning that participants with no or low levels of depressive symptoms will be unlikely to experience a decrease in depression as a response to the intervention. However, a recent meta-analysis of 12 randomized controlled trials (RCTs) evaluating the effectiveness of CBT on patients with CVD with depression and/or anxiety reported significantly lower depression scores at follow-up compared with controls, which in most cases was care as usual [6]. This suggests that interventions based on CBT or CBT principles could be a treatment option for depression in patients with CVD with increased levels of depressive symptoms. However, one barrier to the implementation of CBT in current clinical and cardiac care is low access to psychotherapists, leading to a treatment-demand gap. A solution could be internet-based CBT (iCBT), which can be provided at low cost and has been proven effective in patients with depression [7,8]. iCBT can be delivered in a guided format (ie, support and/or encouragement and/or feedback on homework assignments [9]) or unguided; however, guided iCBT tends to be more effective [10]. One important aspect that may facilitate the implementation of guided iCBT in clinical care is that it can be delivered by health care professionals with little or no specific training, without reducing the effect of the treatment [11]. Another advantage of iCBT is that it enables patients with CVD to access CBT in their own homes and at a time that suits them. However, generic iCBT programs may not be optimal for targeting depression in patients with chronic diseases, as these programs are not tailored to the context of the disease [12,13].
What the sources say
- Partly supportedcites [11] sourceExperimental — accuracy not yet measured
Titov et al. (2010) support the substance of the claim: the Methods (Interventions) state the technician 'reported no prior experience with research programs, no qualifications in health care or counseling', and the Discussion > Conclusions and Abstract report 'no difference between a clinician- and technician-assisted Internet-based treatment program for depression at post-treatment', with large within-group effect sizes (BDI-II 1.27 vs 1.20) and further gains in the technician group at follow-up — i.e., the effect was not reduced. However, the source bounds this by clinician supervision, which the citing sentence drops: Discussion > Generalizability states 'when supervised by a clinician, I-CBT programs may be effectively and safely administered by a non-clinician', and the technician worked from a guideline script, was not permitted to provide clinical advice, and could 'step-up' participants to the clinician. The unsupported part of the claim is therefore delivery 'with little or no specific training' as an unconditional feature; the paper's finding holds only under supervised, non-clinical-advice conditions, and its delivered-by-a-non-clinician model is not quite 'health care professionals'. (LLM, conf=0.75)
hedged- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
- Partly supported
Every source the paper cites for this claim was checked and supports it.
In the paper
“However, our results correspond to the overall moderate effect size of 0.67 for depression reported in a recent meta-analysis [8] of iCBT studies”
§ An Internet-Based Cognitive Behavioral Therapy Program Adapted to Patients With Cardiovascular Disease and Depression: Randomized Controlled Trial > Discussion > Principal Findings
What the sources say
- Supportedcites [8] source
Section 3.2 'Between-group effect sizes' (p. ~6) states the combined Hedges' g for Major Depression was 0.67 (95% CI 0.51-0.81) for computer therapy versus control, which is exactly the figure the citing sentence attributes; the surrounding text (Discussion, Limitations) frames the pooled analyses as iCBT versus control conditions, so describing it as a meta-analysis of iCBT studies is accurate. The 'moderate' label and the comparison to the citing authors' own result are the citing authors' own characterisation, not attributed content. (LLM, conf=0.92)
plainstates an association- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: unclear — It is unclear whether the paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
- Supported
A result the paper reports from its own data — it cites no other source for it, so there is none to check. The quote shows it is in the paper.
In the paper
“In the PCS of the SF-12, a small but nonsignificant improvement owing to iCBT was found (P=.06, Cohen d=0.32; Table 2).”
§ An Internet-Based Cognitive Behavioral Therapy Program Adapted to Patients With Cardiovascular Disease and Depression: Randomized Controlled Trial > Results > Outcomes
plainn = 72- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: unclear — It is unclear whether the paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
A result the paper reports from its own data — it cites no other source for it, so there is none to check. The quote shows it is in the paper.
In the paper
“and the NNT to become mildly depressed was 6.”
§ An Internet-Based Cognitive Behavioral Therapy Program Adapted to Patients With Cardiovascular Disease and Depression: Randomized Controlled Trial > Results > Outcomes
plain- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: unclear — It is unclear whether the paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
23 more claims
Create a free account to see all 58 claims and to verify the 25 references still open.
- It may state two separate claims as one. 16
- The quote only partly states this claim. 1
- Probably not a substantial claim. 15
Claims other papers make about this one
Each is checked against this paper’s own text: does it say what the citing paper says it does?
The cited source doesn’t support the claim as written.
In the citing paper
“The sample size calculation recommended 42 observations in each arm of the hypothetical study considered.”
From Improving the mental health of farmers: what types of remote support are acceptable, feasible, and improve outcomes? A feasibility RCT (2024) · cites this paper as [23]
Checked by a reasoning model — may be wrong.
Experimental — accuracy not yet measuredThe source backs part of the claim, not all of it — or backs it for a different population, condition or comparison.
In the citing paper
“Third, the recruitment rate was low. As reported in previously published article, 21 the recruitment rate to the iCBT trial is low and may have affected the generalizability of the findings.”
From The effects of internet-based cognitive behaviour therapy for depression in cardiovascular disease on symptoms of anxiety: a secondary analysis of a randomized trial. (2024) · cites this paper as [21]
Experimental — accuracy not yet measuredThe cited source says what the claim attributes to it.
In the citing paper
“Only few studies [27–29] have examined the efficacy of an approach like eMindYourHeart to treat compromised mental health in patients with IHD, with the studies showing mixed results.”
The cited source says what the claim attributes to it.
In the citing paper
“The effect of iCBT on symptoms of anxiety was, however, not evaluated in that study.”
The cited source says what the claim attributes to it.
In the citing paper
“Our research team found that an iCBT programme developed to target depression in CVD patients statistically significantly reduced levels of depressive symptoms compared to an online discussion forum (ODF) 21”
Self-check
Percentages, sums and reported differences re-computed from the paper’s own numbers.
Rated minor: it would not touch a result — a value no result rests on, a p-value that stays on the same side of the significance level, or a conflict that is clerical, resolved elsewhere in the paper, or outside its own findings.
In the paper
“89% (n=110) used antiplatelets or anticoagulants.”
§ An Internet-Based Cognitive Behavioral Therapy Program Adapted to Patients With Cardiovascular Disease and Depression: Randomized Controlled Trial > Results > Population
Reported 89 · recomputed 76.388889
Citations
Cites
The PHQ-9: Validity of a brief depression severity measure
Kroenke, K., Spitzer, R. L., & Williams, J. B. W. (2001) · Journal of General Internal Medicine · doi:10.1046/j.1525-1497.2001.016009606.x · Cited by 44,910
McDonagh, T. A., Metra, M., Adamo, M., Gardner, R. S., Baumbach, A., Böhm, M., Burri, H., Butler, J., Čelutkienė, J., Chioncel, O., et al. (2021) · European Heart Journal · doi:10.1093/eurheartj/ehab670 · Cited by 19,442
Self-citationWARE, J. E., KOSINSKI, M., & KELLER, S. D. (1996) · Medical Care · doi:10.1097/00005650-199603000-00003 · Cited by 17,392
Spitzer, R. L. (1999) · JAMA · doi:10.1001/jama.282.18.1737 · Cited by 9,802
2016 ESC Guidelines for the management of atrial fibrillation developed in collaboration with EACTS
Kirchhof, P., Benussi, S., Kotecha, D., Ahlsson, A., Atar, D., Casadei, B., Castella, M., Diener, H.-C., Heidbuchel, H., Hendriks, J., et al. (2016) · Europace · doi:10.1093/europace/euw295 · Cited by 6,439
2016 ESC Guidelines for the Diagnosis and Treatment of Acute and Chronic Heart Failure
Ponikowski, P., Voors, A. A., Anker, S. D., Bueno, H., Cleland, J. G. F., Coats, A. J. S., Falk, V., González-Juanatey, J. R., Harjola, V.-P., Jankowska, E. A., et al. (2016) · European Journal of Heart Failure · doi:10.1002/ejhf.592 · Cited by 5,866
2013 ESC guidelines on the management of stable coronary artery disease
Task Force Members, Montalescot, G., Sechtem, U., Achenbach, S., Andreotti, F., Arden, C., Budaj, A., Bugiardini, R., Crea, F., Cuisset, T., et al. (2013) · European Heart Journal · doi:10.1093/eurheartj/eht296 · Cited by 4,510
Depression, chronic diseases, and decrements in health: results from the World Health Surveys
Moussavi, S., Chatterji, S., Verdes, E., Tandon, A., Patel, V., & Ustun, B. (2007) · The Lancet · doi:10.1016/s0140-6736(07)61415-9 · Cited by 4,070
How Many Imputations are Really Needed? Some Practical Clarifications of Multiple Imputation Theory
Graham, J. W., Olchowski, A. E., & Gilreath, T. D. (2007) · Prevention Science · doi:10.1007/s11121-007-0070-9 · Cited by 2,795
Analysing controlled trials with baseline and follow up measurements
Vickers, A. J., & Altman, D. G. (2001) · BMJ · doi:10.1136/bmj.323.7321.1123 · Cited by 2,116
Research works printed but not linked: 2
- Vernmark, K, 2013, Internetbehandling Med KBT n Praktisk Handbok. First Edition
- 10.1080/08039480310002084 · doi:10.1080/08039480310002084
Cited by
Digital interventions for the treatment of depression: a meta-analytic review
Moshe, I., Terhorst, Y., Philippi, P., Domhardt, M., Cuijpers, P., Cristea, I., Pulkki-Råback, L., Baumeister, H., & Sander, L. B. (2021) · Psychological Bulletin · doi:10.1037/bul0000334 · Cited by 390
Zambrano, J., Celano, C. M., Januzzi, J. L., Massey, C. N., Chung, W., Millstein, R. A., & Huffman, J. C. (2020) · Journal of the American Heart Association · doi:10.1161/jaha.120.018686 · Cited by 131
Psychological Preparation for Cardiac Surgery
Salzmann, S., Salzmann-Djufri, M., Wilhelm, M., & Euteneuer, F. (2020) · Current Cardiology Reports · doi:10.1007/s11886-020-01424-9 · Cited by 72
Koehler, J., Stengel, A., Hofmann, T., Wegscheider, K., Koehler, K., Sehner, S., Rose, M., Deckwart, O., Anker, S. D., Koehler, F., et al. (2020) · European Journal of Heart Failure · doi:10.1002/ejhf.2025 · Cited by 54
Tao, T. J., Lim, T. K., Yeung, E. T. F., Liu, H., Shris, P. B., Lawrence, K., Lee, T. M. C., & Hou, W. K. (2023) · npj Digital Medicine · doi:10.1038/s41746-023-00809-8 · Cited by 65
Metadata
- Authors
- Johansson, P., Westas, M., Andersson, G., Alehagen, U., Broström, A., Jaarsma, T., Mourad, G., & Lundgren, J.
- Affiliations
- Linköping University (SE)
- Jönköping University (SE)
- Corresponding author
- Johansson, Peter
- ORCID
- Venue
- JMIR Mental Health
- Publisher
- JMIR Publications Inc.
- Published
- 2019-10-03
- Volume
- 6
- Issue
- 10
- Pages
- e14648
- ISSN
- 2368-7959 (ISSN-L)
- PMC
- PMC7020777
- OpenAlex
- W2964767251
- Cited by
- 77
- References
- 44
- Citations by year
- 2026: 4 · 2025: 10 · 2024: 11 · 2023: 12 · 2022: 14 · 2021: 17 · 2020: 9
- FWCI
- 11.30
- Type
- journal article
- Language
- en
- Open access
- gold
- doi.org
- Licence
- cc-by
- Locations
- JMIR Mental Health (publishedVersion, cc-by)
- Europe PMC (PubMed Central) (publishedVersion, cc-by)
- PubMed Central (publishedVersion, cc-by)
- PubMed (publishedVersion)
- KTH Publication Database DiVA (KTH Royal Institute of Technology) (submittedVersion, other-oa)
- Topics
- Social Sciences › Psychology › Applied Psychology › Digital Mental Health Interventions
- Health Sciences › Medicine › Cardiology and Cardiovascular Medicine › Cardiac Health and Mental Health
- Social Sciences › Psychology › Experimental and Cognitive Psychology › Anxiety, Depression, Psychometrics, Treatment, Cognitive Processes
- Keywords
- internet-based cognitive behavioral therapy, depression, cardiovascular disease, nurse-led intervention, online forums, health-related quality of life, medication adherence, PHQ-9, SF-12, EQ-VAS, digital mental health interventions, treatment effect size
About these checks
Registry, retraction, Cites and statistics results are computed, not judged, with one exception: a printed reference that no index lists is read once by a model before it counts as a citation error. Claims are extracted by a model and kept only when their quote appears verbatim in the text; each cited source is then checked, with a model’s help, for whether it says what the claim relies on. Those verdicts can be wrong — read the claim’s quote and the cited source before relying on one.
The claim verdicts this report counts are experimental: their accuracy is not yet measured.
A language model drew the claims from the paper on 2026-10-11, under version 3 of the claim definition (model deepseek-v4.1-flash, prompt extract-v3).
A second model labelled each claim on 2026-10-11 (model jev-1.13-20260917, definition revision gold-guideline-v0.2).
Cited sources are checked with a language model’s help (qwen3.8-omni-flash).
Statistics and arithmetic are recomputed, not judged.
Confidence bands are shown only for fields calibrated on our annotated test set. None is calibrated yet, so no band is shown.
What counts as a claim ›How we measure confidence ›How we check this ›
Are you an author, or do you see a problem with this page? Request a review
How to cite
Cite CoChat for the checks on this page, and the paper for its own findings.
- This page
- CoChat. (2026). Citation check: An Internet-Based Cognitive Behavioral Therapy Program Adapted to Patients With Cardiovascular Disease and Depression: Randomized Controlled Trial. https://app.cochat.ai/papers/10.2196/14648
- The paper
- Johansson, P., Westas, M., Andersson, G., Alehagen, U., Broström, A., Jaarsma, T., Mourad, G., & Lundgren, J. (2019). An Internet-Based Cognitive Behavioral Therapy Program Adapted to Patients With Cardiovascular Disease and Depression: Randomized Controlled Trial. JMIR Mental Health. https://doi.org/10.2196/14648
Data sources
Bibliographic data: Semantic Scholar, OpenAlex, Crossref.
Contains information from the Semantic Scholar Academic Graph Datasets, made available under the ODC Attribution License (ODC-BY 1.0).
Semantic Scholar’s data is described in: Kinney, R., et al. (2023). The Semantic Scholar Open Data Platform. arXiv:2301.10140.
