

The DOI matches its Crossref record; 33 of the 33 references it cites were found in a registry or an index.
Clinical practice guidelines for bipolar affective disorder (BPAD) in children and adolescents
Open accessAbstract
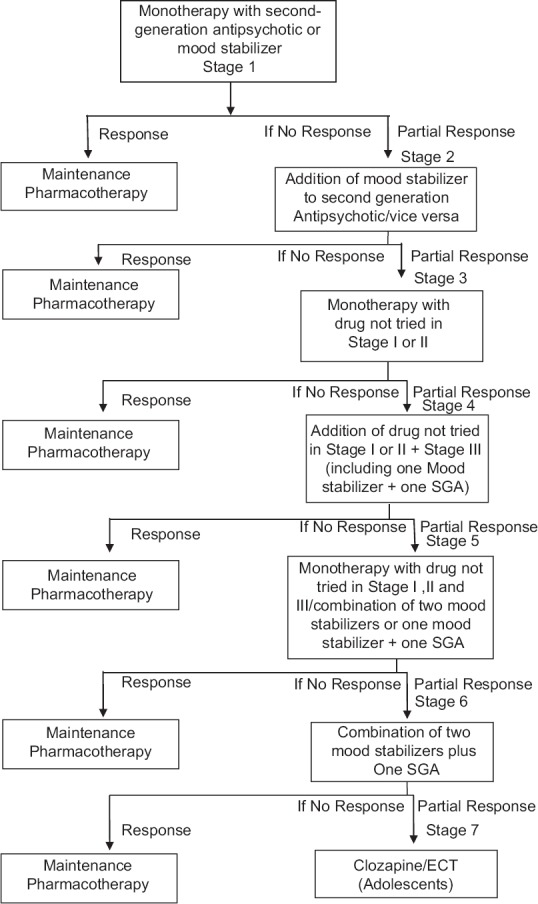
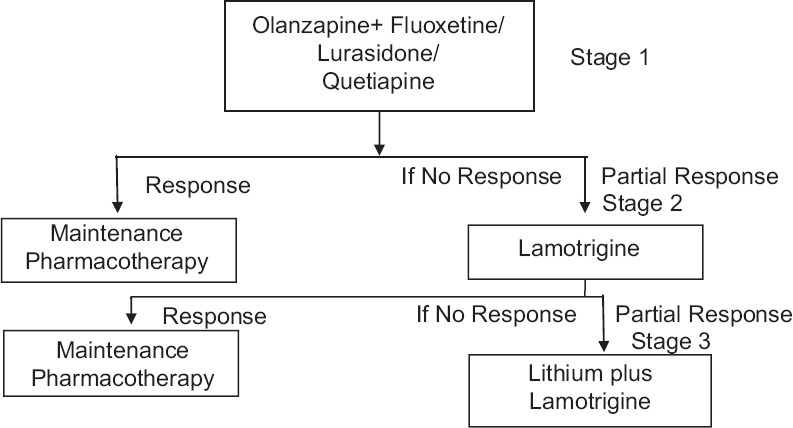
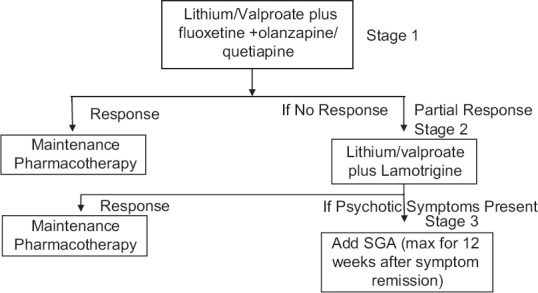
INTRODUCTION According to the census of India, 40% of individuals are children below 16 years of age. There is a paucity of prevalence studies of mental disorders in children and adolescents. There are some community studies who have reported prevalence rates of 9.4% in children aged 8–12 years, 12.5% in children aged 0–16 years, and 1.81% in adolescents aged 12–16 years. Bipolar affective disorder (BPAD) has been recognized in children since 1990; however, there is active controversy whether it could occur before the age of 12 years. Some robust Indian studies have reported 3%–4% prevalence of mood disorders in children and adolescents. Lifetime prevalence rates of BPADs in this age group have been calculated 2.1% equal in males and females. These disorders are often associated with comorbid disorders such as anxiety disorders, attention-deficit/hyperactivity disorder (ADHD), oppositional defiant disorder (ODD), and conduct disorders (CDs). Some authors feel that bipolar disorders often start in adolescents with an episode of major depression, chronic fluctuating abnormalities of mood overactivity, cognition, and conduct disturbances. In the early stage, presenting symptoms are nonspecific and not limited to mood spectrum. ASSESSMENT AND EVALUATION Usually, the diagnoses in children are difficult because of commonly associated comorbidities. Children present with atypical or mixed features such as labile mood, irritability, behavioral problems, and rapid cycling course. Some may have school problems such as fighting substance abuse and sexual behavior with nonepisodic and chronic course. Adolescent presentation may be mood incongruent, bizarre, and/or paranoid, which may make the diagnosis difficult. Normal imaginative play, overactivity, boastfulness, and grandiosity should not be mistaken for child BPAD. The assessment of children for BPAD should be done as follows: Screening One should look for clear periods of low moods with emphasis in context in which the symptoms occur. Family history of mood disorders, substance use disorders along with presence of any other stressors must be explored. Diagnostic criterion The Diagnostic and Statistical Manual of Mental Disorders, 5th Edition (DSM-V) or International Classification of Diseases, 10th Revision Criterion is often used. Symptoms of BPAD (irritability/grandiosity/persistent sadness or low mood/loss of interests and/or pleasure, low energy, sleep and appetite disturbances, poor concentration or indecisiveness low self-confidence, suicidal thoughts and acts guilt or self-blame, and agitation or psychomotor retardation) should be present on the most days, most of the time for at least 2 weeks. Instruments for evaluation In case of difficulty or clarity, some instruments which can be used are severity rating using the Child Depression Inventory or Childhood Depression Rating Scale–Revised, Kiddie Schedule for Affective Disorders and Schizophrenia, and Mini-International Neuropsychiatric Interview for Children and Adolescents for the assessment of depression. Evaluation of comorbidity Comorbid disorders such as anxiety disorders, ADHD, ODD, and CDs may influence treatment decisions and also help in understanding long-term course, and hence, they should be evaluated and appropriate diagnosis should be made. FORMULATING A TREATMENT PLAN If possible, the diagnoses should establish using structured instrument for assessment and one should monitor the symptom patterns prospectively by providing a diary to record symptoms to the parents or caregivers of the patients. Baseline symptoms of mania or depression can be recorded using appropriate scales to be more objective (Young Mania Rating Scale/Children's Depression Rating Scale and global impression of the clinician). Baseline height, weight, waist circumference, pulse electrocardiography, blood pressure, and appropriate baseline blood tests such as complete blood count, blood sugar, lipid profile, urea electrolytes, creatinine, and liver function tests may be recorded in case of female adolescents’ serum prolactin. Treatment has to be planned according to the presentation of BPAD. Treatment for mild depression does not usually require medication. It will depend on the availability of psychological therapies, behavior therapies, counseling services, and family therapy. In some settings, medication and psychosocial management is provided simultaneously. For moderate depression, a combination of antidepressant and psychotherapy is recommended. For severe depression, psychopharmacological management with cognitive behavior therapy (CBT) and family therapy is advisable. For manic symptoms of BPAD, treatment can be initiated with low-dose antimanic agents and mood stabilizers. Guiding principles for treatment plan include: Begin with less, go slow, and monitor efficacy and adverse reactions Monotherapy is ideal; however, multiple medications are often required in the severely ill Allow adequate trial of treatment in ch
Overview
The claims and statistics of this paper haven’t been checked yet.
Run the check — free, no account needed. It reads the open-access text and checks the sources it cites.
Integrity signals
Registry
Cites
Statistics
Figures
Verification
Claims the paper makes
The claims and statistics of this paper haven’t been checked yet.
Run the check — free, no account needed. It reads the open-access text and checks the sources it cites.
Claims other papers make about this one
Each is checked against this paper’s own text: does it say what the citing paper says it does?
The check wasn’t confident either way, so it gives no verdict — never disputed.
In the citing paper
“There is no evidence for differential efficacy or safety in this group.”
From Clinical Practice Guidelines for the Use of Electroconvulsive Therapy (2023) · cites this paper as [31]
Experimental — accuracy not yet measured
Self-check
Percentages, sums and reported differences re-computed from the paper’s own numbers.
The self-check needs the paper’s full text.
Citations
Cites
Diagnostic and Statistical Manual of Mental Disorders
American Psychiatric Association (2013) · doi:10.1176/appi.books.9780890425596 · Cited by 116,369
Perlis, R. H., Miyahara, S., Marangell, L. B., Wisniewski, S. R., Ostacher, M., DelBello, M. P., Bowden, C. L., Sachs, G. S., & Nierenberg, A. A. (2004) · Biological Psychiatry · doi:10.1016/j.biopsych.2004.01.022 · Cited by 852
Clinical Course of Children and Adolescents With Bipolar Spectrum Disorders
Birmaher, B. B., Axelson, D., Strober, M. A., Gill, M. K., Valeri, S. M., Chiappetta, L., Ryan, N. D., Leonard, H., Hunt, J., Iyengar, S., et al. (2006) · Archives of General Psychiatry · doi:10.1001/archpsyc.63.2.175 · Cited by 664
McClellan, J., Kowatch, R. A., & Findling, R. L. (2006) · Journal of the American Academy of Child & Adolescent Psychiatry · doi:10.1097/01.chi.0000242240.69678.c4 · Cited by 516
Axelson, D., Birmaher, B. B., Strober, M. A., Goldstein, B. I., Ha, W., Gill, M. K., Goldstein, T. R., Yen, S., Hower, H. M., Hunt, J., et al. (2011) · Journal of the American Academy of Child & Adolescent Psychiatry · doi:10.1016/j.jaac.2011.07.005 · Cited by 249
Pediatric bipolar disorder: validity, phenomenology, and recommendations for diagnosis
Youngstrom, E. A., Birmaher, B. B., & Findling, R. L. (2008) · Bipolar Disorders · doi:10.1111/j.1399-5618.2007.00563.x · Cited by 236
Geller, B., Zimerman, B., Williams, M., DelBello, M. P., Frazier, J., & Beringer, L. (2002) · Journal of Child and Adolescent Psychopharmacology · doi:10.1089/10445460252943524 · Cited by 236
Causes of decreased life expectancy over the life span in bipolar disorder
Kessing, L. V., Vradi, E., McIntyre, R. S., & Andersen, P. K. (2015) · Journal of Affective Disorders · doi:10.1016/j.jad.2015.03.027 · Cited by 209
Disruptive Mood Dysregulation Disorder: A New Diagnostic Approach to Chronic Irritability in Youth
Roy, A. K., Lopes, V., & Klein, R. G. (2014) · American Journal of Psychiatry · doi:10.1176/appi.ajp.2014.13101301 · Cited by 117
Comorbidity in pediatric bipolar disorder: Prevalence, clinical impact, etiology and treatment
Frías, Á., Palma, C., & Farriols, N. (2014) · Journal of Affective Disorders · doi:10.1016/j.jad.2014.12.008 · Cited by 115
Research works printed but not linked: 2
- Carlson GA, Meyer SE. Bipolar disorder. In: Dulcan M, editor. Dulcan's Textbook of Child and Adolescent Psychiatry. Arlington, VA: APP; 2010. · DOI
- Stahl SM. Stahl's Essential Psychopharmacology. Prescribers Guide. 5th ed. Cambridge, UK: Cambridge University press; 2014.
Cited by
Sorted by citations
Clinical Practice Guidelines for the Use of Electroconvulsive Therapy
Thirthalli, J., Sinha, P., & Sreeraj, V. S. (2023) · Indian Journal of Psychiatry · doi:10.4103/indianjpsychiatry.indianjpsychiatry_491_22 · Cited by 74
Rambabu, K., & Pavuluri, S. K. (2024) · Future Journal of Pharmaceutical Sciences · doi:10.1186/s43094-023-00570-5 · Cited by 12
Adverse effects of electroconvulsive therapy
Munkholm, K., Jørgensen, K. J., & Paludan‐Müller, A. S. (2021) · Cochrane Database of Systematic Reviews · doi:10.1002/14651858.cd014995 · Cited by 9
The pulvinar nucleus and its role in cognitive functions
Cortes, N., Mandel, C., Ikan, L., & Casanova, C. (2025) · Brain Research Bulletin · doi:10.1016/j.brainresbull.2025.111672 · Cited by 7
The economic burden of bipolar disorder: a case study in Southern Iran
Shaker, Z., Goudarzi, Z., Ravangard, R., Shaker, Z., Hedayati, A., & Keshavarz, K. (2024) · Cost Effectiveness and Resource Allocation · doi:10.1186/s12962-024-00560-1 · Cited by 7
Metadata
- Authors
- Gautam, S., Jain, A., Gautam, M., Gautam, A., & Jagawat, T.
- Affiliations
- NIMS University (IN)
- Corresponding author
- Gautam, Shiv
- Gautam, Manaswi
- Gautam, Anita
- Venue
- Indian Journal of Psychiatry
- Published
- 2019
- Volume
- 61
- Issue
- 8
- Pages
- 294
- ISSN
- 0019-5545 (ISSN-L)
- PMC
- PMC6345130
- OpenAlex
- W2911156211
- Cited by
- 30
- References
- 33
- Citations by year
- 2026: 4 · 2025: 2 · 2024: 8 · 2023: 2 · 2022: 1 · 2021: 5 · 2020: 8
- FWCI
- 2.79
- Type
- journal article
- Language
- en
- Open access
- diamond
- doi.org
- Licence
- cc-by-nc-sa
- Locations
- Indian Journal of Psychiatry (publishedVersion, cc-by-nc-sa)
- Europe PMC (PubMed Central) (publishedVersion, cc-by-nc-sa)
- PubMed Central (publishedVersion, cc-by-nc-sa)
- PubMed (publishedVersion)
- DOAJ (DOAJ: Directory of Open Access Journals) (submittedVersion)
- Topics
- Health Sciences › Medicine › Psychiatry and Mental health › Bipolar Disorder and Treatment
- Social Sciences › Psychology › Clinical Psychology › Personality Disorders and Psychopathology
- Social Sciences › Psychology › Clinical Psychology › Child and Adolescent Psychosocial and Emotional Development
- Keywords
- bipolar disorder, pediatric bipolar disorder, children and adolescents, diagnosis, screening, comorbidities, rapid cycling, mixed features, irritability, grandiosity, mood stabilizers, psychoeducation, family involvement, relapse prevention, suicide prevention, substance use disorders, DSM-5, ICD-10
About these checks
Registry, retraction, Cites and statistics results are computed, not judged, with one exception: a printed reference that no index lists is read once by a model before it counts as a citation error. Claims are extracted by a model and kept only when their quote appears verbatim in the text; each cited source is then checked, with a model’s help, for whether it says what the claim relies on. Those verdicts can be wrong — read the claim’s quote and the cited source before relying on one.
Statistics and arithmetic are recomputed, not judged.
Confidence bands are shown only for fields calibrated on our annotated test set. None is calibrated yet, so no band is shown.
What counts as a claim ›How we measure confidence ›How we check this ›
Are you an author, or do you see a problem with this page? Request a review
