

The DOI matches its Crossref record; 29 of the 29 references it cites were found in a registry or an index; 2 of the 7 sources its claims cite were checked for support.
The SANAD II study of the effectiveness and cost-effectiveness of levetiracetam, zonisamide, or lamotrigine for newly diagnosed focal epilepsy: an open-label, non-inferiority, multicentre, phase 4, randomised controlled trial
Open accessAbstract
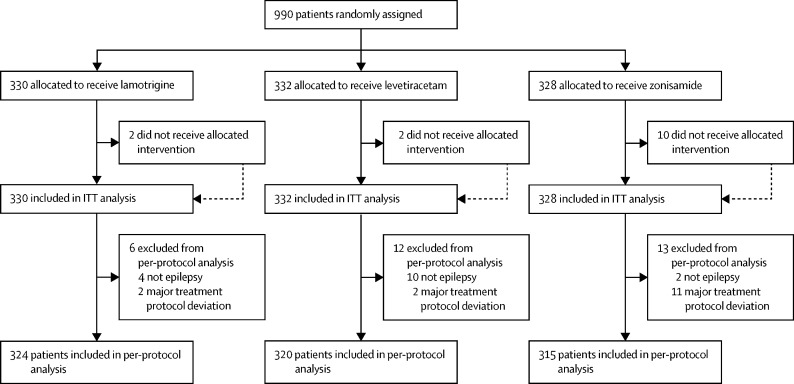
BACKGROUND: Levetiracetam and zonisamide are licensed as monotherapy for patients with focal epilepsy, but there is uncertainty as to whether they should be recommended as first-line treatments because of insufficient evidence of clinical effectiveness and cost-effectiveness. We aimed to assess the long-term clinical effectiveness and cost-effectiveness of levetiracetam and zonisamide compared with lamotrigine in people with newly diagnosed focal epilepsy. METHODS: This randomised, open-label, controlled trial compared levetiracetam and zonisamide with lamotrigine as first-line treatment for patients with newly diagnosed focal epilepsy. Adult and paediatric neurology services across the UK recruited participants aged 5 years or older (with no upper age limit) with two or more unprovoked focal seizures. Participants were randomly allocated (1:1:1) using a minimisation programme with a random element utilising factor to receive lamotrigine, levetiracetam, or zonisamide. Participants and investigators were not masked and were aware of treatment allocation. SANAD II was designed to assess non-inferiority of both levetiracetam and zonisamide to lamotrigine for the primary outcome of time to 12-month remission. Anti-seizure medications were taken orally and for participants aged 12 years or older the initial advised maintenance doses were lamotrigine 50 mg (morning) and 100 mg (evening), levetiracetam 500 mg twice per day, and zonisamide 100 mg twice per day. For children aged between 5 and 12 years the initial daily maintenance doses advised were lamotrigine 1·5 mg/kg twice per day, levetiracetam 20 mg/kg twice per day, and zonisamide 2·5 mg/kg twice per day. All participants were included in the intention-to-treat (ITT) analysis. The per-protocol (PP) analysis excluded participants with major protocol deviations and those who were subsequently diagnosed as not having epilepsy. Safety analysis included all participants who received one dose of any study drug. The non-inferiority limit was a hazard ratio (HR) of 1·329, which equates to an absolute difference of 10%. A HR greater than 1 indicated that an event was more likely on lamotrigine. The trial is registered with the ISRCTN registry, 30294119 (EudraCt number: 2012-001884-64). FINDINGS: 990 participants were recruited between May 2, 2013, and June 20, 2017, and followed up for a further 2 years. Patients were randomly assigned to receive lamotrigine (n=330), levetiracetam (n=332), or zonisamide (n=328). The ITT analysis included all participants and the PP analysis included 324 participants randomly assigned to lamotrigine, 320 participants randomly assigned to levetiracetam, and 315 participants randomly assigned to zonisamide. Levetiracetam did not meet the criteria for non-inferiority in the ITT analysis of time to 12-month remission versus lamotrigine (HR 1·18; 97·5% CI 0·95-1·47) but zonisamide did meet the criteria for non-inferiority in the ITT analysis versus lamotrigine (1·03; 0·83-1·28). The PP analysis showed that 12-month remission was superior with lamotrigine than both levetiracetam (HR 1·32 [97·5% CI 1·05 to 1·66]) and zonisamide (HR 1·37 [1·08-1·73]). There were 37 deaths during the trial. Adverse reactions were reported by 108 (33%) participants who started lamotrigine, 144 (44%) participants who started levetiracetam, and 146 (45%) participants who started zonisamide. Lamotrigine was superior in the cost-utility analysis, with a higher net health benefit of 1·403 QALYs (97·5% central range 1·319-1·458) compared with 1·222 (1·110-1·283) for levetiracetam and 1·232 (1·112, 1·307) for zonisamide at a cost-effectiveness threshold of £20 000 per QALY. Cost-effectiveness was based on differences between treatment groups in costs and QALYs. INTERPRETATION: These findings do not support the use of levetiracetam or zonisamide as first-line treatments for patients with focal epilepsy. Lamotrigine should remain a first-line treatment for patients with focal epilepsy and should be the standard treatment in future trials. FUNDING: National Institute for Health Research Health Technology Assessment programme.
Overview
AI snapshot
Written from the paper’s full text.
TL;DR
In newly diagnosed focal epilepsy, levetiracetam did not meet non-inferiority to lamotrigine for time to 12-month remission, while zonisamide did in the intention-to-treat analysis. Lamotrigine remained superior for treatment failure and cost-effectiveness, supporting its continued first-line use.
Key findings
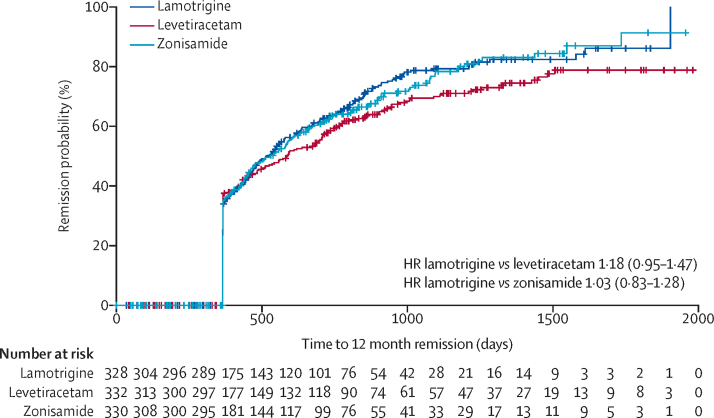
- Among 990 participants randomised to lamotrigine (n=330), levetiracetam (n=332), or zonisamide (n=328), levetiracetam did not meet non-inferiority versus lamotrigine for time to 12-month remission (HR 1·18; 97·5% CI 0·95–1·47), whereas zonisamide did (HR 1·03; 97·5% CI 0·83–1·28).
- In per-protocol analysis, 12-month remission was superior with lamotrigine than levetiracetam (HR 1·32; 97·5% CI 1·05–1·66) and zonisamide (HR 1·37; 97·5% CI 1·08–1·73).
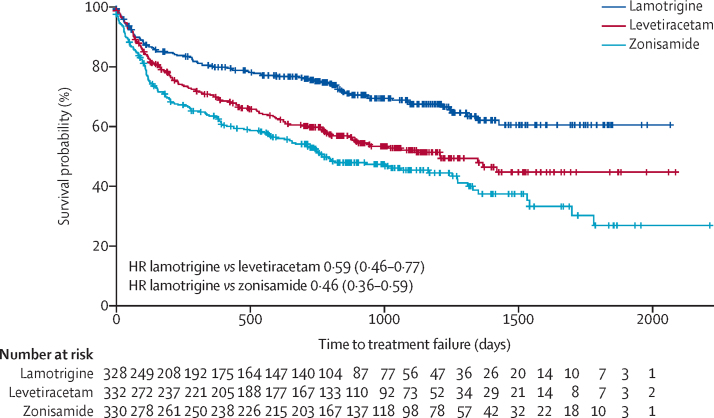
- Lamotrigine was significantly less likely to fail than levetiracetam (HR 0·60; 95% CI 0·46–0·77) or zonisamide (HR 0·46; 95% CI 0·36–0·60); adverse reactions were reported by 108 (33%) on lamotrigine, 144 (44%) on levetiracetam, and 146 (45%) on zonisamide.
- Lamotrigine dominated in cost-utility analysis, with net health benefit 1·403 QALYs (97·5% central range 1·319–1·458) versus 1·222 (1·110–1·283) for levetiracetam and 1·232 (1·112–1·307) for zonisamide at £20 000 per QALY.
Methods
- Phase 4, multicentre, open-label, non-inferiority randomised controlled trial in 65 UK NHS adult and paediatric neurology services; participants were aged 5 years or older with newly diagnosed focal epilepsy and at least two unprovoked focal seizures.
- Participants were randomly allocated 1:1:1 to lamotrigine, levetiracetam, or zonisamide; primary outcome was time to 12-month remission, with non-inferiority margin HR 1·329 and 97·5% CIs for the two primary comparisons.
- Analyses included intention-to-treat and per-protocol populations, plus competing-risks analyses for treatment failure and a health economic cost-utility analysis using QALYs and NHS/personal social services perspective.
Limitations
- The paper states that seizure data came from diaries and clinic reports, so seizures may have been missed or unreported; only 177 (17·9%) participants were younger than 18 years, limiting applicability to children; maintenance doses may have introduced systematic bias; QOL questionnaire return was low; and newer drugs such as lacosamide and perampanel were not assessed.
- The paper also states economic limitations: poor questionnaire return, free-text resource-use questions, and assuming unanswered questions meant no resource use; EQ-5D-3L-Y and proxy measures were limited by unavailable value sets and use of adult tariffs.
- Evident from the text: the trial was open-label, so participants and investigators were aware of treatment allocation, and the paediatric cost-effectiveness finding was based on a small subgroup and principally due to a single participant with an atypical medical journey.
Model-written summary. Check it against the paper before relying on it.
Integrity signals
Registry
Cites
Statistics
Figures
Verification
Claims the paper makes
22 Own result · 12 Own method · 4 Own interpretation · 3 No full text of the sources · 2 Partly supported · 2 Sources not found · 1 No basis given · accuracy not yet measured
The cited sources support only part of this claim — read each source’s verdict below.
In the paper
“Although focal epilepsies can be classified according to site of seizure onset and cause, there is no evidence to suggest that one syndrome or cause responds better to one specific treatment than to another.8”
§ The SANAD II study of the effectiveness and cost-effectiveness of levetiracetam, zonisamide, or lamotrigine for newly diagnosed focal epilepsy: an open-label, non-inferiority, multicentre, phase 4, randomised controlled trial > Introduction
What the sources say
- Partly supportedcites [8] Bonnett L Smith CT Smith D Williamson P Chadwick D Marson AG Prognostic factors for time to treatment failure and time to 12 months of remission for patients with focal epilepsy: post-hoc, subgroup analyses of data from the SANAD trial Lancet Neurol 11 2012 331 340 22377180 sourceExperimental — accuracy not yet measured
The Interpretation (page unavailable) says that predictors of seizure control have not yet been established, which is consistent with the claim’s general caution. The Prognostic modelling section classifies focal epilepsy by site of onset, but our copy does not establish that no syndrome or cause responds preferentially to a particular treatment. (LLM, conf=0.72)
plain- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
- Partly supported
A result the paper reports from its own data — it cites no other source for it, so there is none to check. The quote shows it is in the paper.
In the paper
“but zonisamide did meet the criteria for non-inferiority in the ITT analysis versus lamotrigine (1·03; 0·83–1·28)”
§ The SANAD II study of the effectiveness and cost-effectiveness of levetiracetam, zonisamide, or lamotrigine for newly diagnosed focal epilepsy: an open-label, non-inferiority, multicentre, phase 4, randomised controlled trial > Abstract > Findings
plainn = 990- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
A result the paper reports from its own data — it cites no other source for it, so there is none to check. The quote shows it is in the paper.
In the paper
“or for lamotrigine versus zonisamide (0·96 [0·75–1·23])”
§ The SANAD II study of the effectiveness and cost-effectiveness of levetiracetam, zonisamide, or lamotrigine for newly diagnosed focal epilepsy: an open-label, non-inferiority, multicentre, phase 4, randomised controlled trial > Results
plain- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
A result the paper reports from its own data — it cites no other source for it, so there is none to check. The quote shows it is in the paper.
In the paper
“and zonisamide (HR 1·37 [1·08–1·73])”
§ The SANAD II study of the effectiveness and cost-effectiveness of levetiracetam, zonisamide, or lamotrigine for newly diagnosed focal epilepsy: an open-label, non-inferiority, multicentre, phase 4, randomised controlled trial > Abstract > Findings
plaindirectn = 315- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
A result the paper reports from its own data — it cites no other source for it, so there is none to check. The quote shows it is in the paper.
In the paper
“Levetiracetam did not meet the criteria for non-inferiority in the ITT analysis of time to 12-month remission versus lamotrigine (HR 1·18; 97·5% CI 0·95–1·47)”
§ The SANAD II study of the effectiveness and cost-effectiveness of levetiracetam, zonisamide, or lamotrigine for newly diagnosed focal epilepsy: an open-label, non-inferiority, multicentre, phase 4, randomised controlled trial > Abstract > Findings
plainn = 990- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
A result the paper reports from its own data — it cites no other source for it, so there is none to check. The quote shows it is in the paper.
In the paper
“The PP analysis showed that 12-month remission was superior with lamotrigine than both levetiracetam (HR 1·32 [97·5% CI 1·05 to 1·66])”
§ The SANAD II study of the effectiveness and cost-effectiveness of levetiracetam, zonisamide, or lamotrigine for newly diagnosed focal epilepsy: an open-label, non-inferiority, multicentre, phase 4, randomised controlled trial > Abstract > Findings
plaindirectn = 324- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
A result the paper reports from its own data — it cites no other source for it, so there is none to check. The quote shows it is in the paper.
In the paper
“No significant difference was found in time to 24-month remission (using ITT analysis) for lamotrigine versus levetiracetam (HR 1·04 [95% CI 0·81–1·33])”
§ The SANAD II study of the effectiveness and cost-effectiveness of levetiracetam, zonisamide, or lamotrigine for newly diagnosed focal epilepsy: an open-label, non-inferiority, multicentre, phase 4, randomised controlled trial > Results
plain- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
A result the paper reports from its own data — it cites no other source for it, so there is none to check. The quote shows it is in the paper.
In the paper
“Levetiracetam did not meet our definition of non-inferiority for time to 12-month remission compared with lamotrigine, and it was inferior for time to treatment failure.”
§ The SANAD II study of the effectiveness and cost-effectiveness of levetiracetam, zonisamide, or lamotrigine for newly diagnosed focal epilepsy: an open-label, non-inferiority, multicentre, phase 4, randomised controlled trial > Abstract > Funding
plaindirect- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
A result the paper reports from its own data — it cites no other source for it, so there is none to check. The quote shows it is in the paper.
In the paper
“1% fewer on zonisamide compared with lamotrigine (–9 to 7)”
§ The SANAD II study of the effectiveness and cost-effectiveness of levetiracetam, zonisamide, or lamotrigine for newly diagnosed focal epilepsy: an open-label, non-inferiority, multicentre, phase 4, randomised controlled trial > Results
plain- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: unclear — It is unclear whether the paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
A result the paper reports from its own data — it cites no other source for it, so there is none to check. The quote shows it is in the paper.
In the paper
“Zonisamide did meet our definition of non-inferiority for time to 12-month remission but it too was inferior for time to treatment failure.”
§ The SANAD II study of the effectiveness and cost-effectiveness of levetiracetam, zonisamide, or lamotrigine for newly diagnosed focal epilepsy: an open-label, non-inferiority, multicentre, phase 4, randomised controlled trial > Abstract > Funding
plaindirect- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
- Probably not a substantial claim. 10
- It may state two separate claims as one. 14
The cited sources support only part of this claim — read each source’s verdict below.
In the paper
“which identified lamotrigine as non-inferior to carbamazepine for time to 12-month remission and superior to carbamazepine, gabapentin, oxcarbazepine, and topiramate for time to treatment failure.”
§ The SANAD II study of the effectiveness and cost-effectiveness of levetiracetam, zonisamide, or lamotrigine for newly diagnosed focal epilepsy: an open-label, non-inferiority, multicentre, phase 4, randomised controlled trial > Introduction
What the sources say
- Partly supportedcites [10] Marson AG Al-Kharusi AM Alwaidh M The SANAD study of effectiveness of carbamazepine, gabapentin, lamotrigine, oxcarbazepine, or topiramate for treatment of partial epilepsy: an unblinded randomised controlled trial Lancet 369 2007 1000 1015 17382827 PMC2080688 sourceExperimental — accuracy not yet measured
The Discussion reports that lamotrigine was non-inferior to carbamazepine for time to 12-month remission and significantly better than carbamazepine, gabapentin, and topiramate for time to treatment failure. The Abstract Findings describe its advantage over oxcarbazepine as non-significant, so the claim of superiority to oxcarbazepine is not supported. (LLM, conf=0.94)
plaindirect- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
Probably not a substantial claim. It may state two separate claims as one.
- Partly supported
A result the paper reports from its own data — it cites no other source for it, so there is none to check. The quote shows it is in the paper.
In the paper
“There were 37 deaths during the trial.”
§ The SANAD II study of the effectiveness and cost-effectiveness of levetiracetam, zonisamide, or lamotrigine for newly diagnosed focal epilepsy: an open-label, non-inferiority, multicentre, phase 4, randomised controlled trial > Abstract > Findings
plain- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: fails — The paper’s conclusions may not depend on it.
- Based: passes — The paper gives a reason why it holds.
Probably not a substantial claim. The paper’s conclusions may not depend on it.
A result the paper reports from its own data — it cites no other source for it, so there is none to check. The quote shows it is in the paper.
In the paper
“Adverse reactions were reported by 108 (33%) participants who started lamotrigine, 144 (44%) participants who started levetiracetam, and 146 (45%) participants who started zonisamide.”
§ The SANAD II study of the effectiveness and cost-effectiveness of levetiracetam, zonisamide, or lamotrigine for newly diagnosed focal epilepsy: an open-label, non-inferiority, multicentre, phase 4, randomised controlled trial > Abstract > Findings
plain- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: unclear — It is unclear whether the paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
A result the paper reports from its own data — it cites no other source for it, so there is none to check. The quote shows it is in the paper.
In the paper
“The ITT analysis included all participants and the PP analysis included 324 participants randomly assigned to lamotrigine, 320 participants randomly assigned to levetiracetam, and 315 participants randomly assigned to zonisamide.”
§ The SANAD II study of the effectiveness and cost-effectiveness of levetiracetam, zonisamide, or lamotrigine for newly diagnosed focal epilepsy: an open-label, non-inferiority, multicentre, phase 4, randomised controlled trial > Abstract > Findings
plainn = 324- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: unclear — It is unclear whether the paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
A result the paper reports from its own data — it cites no other source for it, so there is none to check. The quote shows it is in the paper.
In the paper
“990 participants were recruited between May 2, 2013, and June 20, 2017, and followed up for a further 2 years.”
§ The SANAD II study of the effectiveness and cost-effectiveness of levetiracetam, zonisamide, or lamotrigine for newly diagnosed focal epilepsy: an open-label, non-inferiority, multicentre, phase 4, randomised controlled trial > Abstract > Findings
plainn = 990- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: fails — The paper’s conclusions may not depend on it.
- Based: passes — The paper gives a reason why it holds.
Probably not a substantial claim. The paper’s conclusions may not depend on it. It may state two separate claims as one.
A result the paper reports from its own data — it cites no other source for it, so there is none to check. The quote shows it is in the paper.
In the paper
“The Kaplan-Meier estimates of the median time to achieve 12-month remission were 516 days (95% CI 457–577) for lamotrigine, 588 days (472–706) for levetiracetam, and 530 days (453–601) for zonisamide (figure 2).”
§ The SANAD II study of the effectiveness and cost-effectiveness of levetiracetam, zonisamide, or lamotrigine for newly diagnosed focal epilepsy: an open-label, non-inferiority, multicentre, phase 4, randomised controlled trial > Results
plain- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: unclear — It is unclear whether the paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
What the paper did — it cites no source for this, so there is none to check. The quote shows it is in the paper.
In the paper
“Participants and investigators were not masked and were all aware of treatment allocation.”
§ The SANAD II study of the effectiveness and cost-effectiveness of levetiracetam, zonisamide, or lamotrigine for newly diagnosed focal epilepsy: an open-label, non-inferiority, multicentre, phase 4, randomised controlled trial > Methods > Randomisation and masking
plain- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
Probably not a substantial claim. It may state two separate claims as one.
What the paper did — it cites no source for this, so there is none to check. The quote shows it is in the paper.
In the paper
“with completeness of follow-up statistics for the primary outcome of 77% for lamotrigine, 78% for levetiracetam, and 76% for zonisamide.”
§ The SANAD II study of the effectiveness and cost-effectiveness of levetiracetam, zonisamide, or lamotrigine for newly diagnosed focal epilepsy: an open-label, non-inferiority, multicentre, phase 4, randomised controlled trial > Results
plain- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: unclear — It is unclear whether the paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
What the paper did — it cites no source for this, so there is none to check. The quote shows it is in the paper.
In the paper
“Interim monitoring was done by an independent data safety and monitoring committee, meeting approximately annually.”
§ The SANAD II study of the effectiveness and cost-effectiveness of levetiracetam, zonisamide, or lamotrigine for newly diagnosed focal epilepsy: an open-label, non-inferiority, multicentre, phase 4, randomised controlled trial > Methods > Statistical analysis
plain- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: fails — The paper’s conclusions may not depend on it.
- Based: passes — The paper gives a reason why it holds.
Probably not a substantial claim. The paper’s conclusions may not depend on it.
What the paper did — it cites no source for this, so there is none to check. The quote shows it is in the paper.
In the paper
“The statistical and health economic analysis plans were developed before doing the final analyses and are available in appendix 1 and appendix 2.”
§ The SANAD II study of the effectiveness and cost-effectiveness of levetiracetam, zonisamide, or lamotrigine for newly diagnosed focal epilepsy: an open-label, non-inferiority, multicentre, phase 4, randomised controlled trial > Methods > Statistical analysis
plain- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: fails — The paper’s conclusions may not depend on it.
- Based: passes — The paper gives a reason why it holds.
Probably not a substantial claim. The paper’s conclusions may not depend on it.
A conclusion the paper draws from its own results — it cites no other source for it, so there is none to check. The quote shows it is in the paper.
In the paper
“These findings do not support the use of levetiracetam or zonisamide as first-line treatments for patients with focal epilepsy.”
§ The SANAD II study of the effectiveness and cost-effectiveness of levetiracetam, zonisamide, or lamotrigine for newly diagnosed focal epilepsy: an open-label, non-inferiority, multicentre, phase 4, randomised controlled trial > Abstract > Interpretation
plain- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
A conclusion the paper draws from its own results — it cites no other source for it, so there is none to check. The quote shows it is in the paper.
In the paper
“The study is pragmatic in design and recruited a cohort of participants older than 5 years from routine UK National Health Service clinics, and the results are relevant to every day clinical practice.”
§ The SANAD II study of the effectiveness and cost-effectiveness of levetiracetam, zonisamide, or lamotrigine for newly diagnosed focal epilepsy: an open-label, non-inferiority, multicentre, phase 4, randomised controlled trial > Abstract > Funding
plain- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
What the paper did — it cites no source for this, so there is none to check. The quote shows it is in the paper.
In the paper
“Therefore, assuming a HR of 1 and 80% power with a one-sided alpha of 0·025, 330 patients were required in each of three treatment groups, allowing for 5% losses to follow-up, as occurred in SANAD I (990 total patients).”
§ The SANAD II study of the effectiveness and cost-effectiveness of levetiracetam, zonisamide, or lamotrigine for newly diagnosed focal epilepsy: an open-label, non-inferiority, multicentre, phase 4, randomised controlled trial > Methods > Statistical analysis
plainn = 330- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
What the paper did — it cites no source for this, so there is none to check. The quote shows it is in the paper.
In the paper
“The assumption of proportional hazards was investigated by examining Schoenfeld residual plots and incorporating time-dependent covariates in all models.”
§ The SANAD II study of the effectiveness and cost-effectiveness of levetiracetam, zonisamide, or lamotrigine for newly diagnosed focal epilepsy: an open-label, non-inferiority, multicentre, phase 4, randomised controlled trial > Methods > Statistical analysis
plain- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
Probably not a substantial claim.
What the paper did — it cites no source for this, so there is none to check. The quote shows it is in the paper.
In the paper
“All participants were included in the intention-to-treat (ITT) analysis.”
§ The SANAD II study of the effectiveness and cost-effectiveness of levetiracetam, zonisamide, or lamotrigine for newly diagnosed focal epilepsy: an open-label, non-inferiority, multicentre, phase 4, randomised controlled trial > Abstract > Methods
plain- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
Probably not a substantial claim.
What the paper did — it cites no source for this, so there is none to check. The quote shows it is in the paper.
In the paper
“although this trial was powered for non-inferiority, it was also designed to show superiority.”
§ The SANAD II study of the effectiveness and cost-effectiveness of levetiracetam, zonisamide, or lamotrigine for newly diagnosed focal epilepsy: an open-label, non-inferiority, multicentre, phase 4, randomised controlled trial > Results
plain- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
What the paper did — it cites no source for this, so there is none to check. The quote shows it is in the paper.
In the paper
“The PP analyses (using the Fine and Gray model) for time to 12-month remission (appendix 3 p 3) excluded patients with major protocol deviations (15 participants; 1·5%) and patients later diagnosed as not meeting the diagnosis of epilepsy (16 participants; 1·6%), and accounted for treatment failures before achieving 12-month remission”
§ The SANAD II study of the effectiveness and cost-effectiveness of levetiracetam, zonisamide, or lamotrigine for newly diagnosed focal epilepsy: an open-label, non-inferiority, multicentre, phase 4, randomised controlled trial > Results
plainn = 15- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: unclear — It is unclear whether the paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
In the paper
“This knowledge gap is reflected in the National Institute for Health and Care Excellence epilepsy guidelines, which do not recommend either drug as a first-line treatment.”
§ The SANAD II study of the effectiveness and cost-effectiveness of levetiracetam, zonisamide, or lamotrigine for newly diagnosed focal epilepsy: an open-label, non-inferiority, multicentre, phase 4, randomised controlled trial > Abstract > Funding
What the sources say
- Not matchedcites [9] National Institute for Health and Clinical Excellence Epilepsies: diagnosis and management https://www.nice.org.uk/guidance/cg137 2012
Couldn’t be matched to a paper in Crossref, so it can’t be checked.
plain- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
- Not matched
What the paper did — it cites no source for this, so there is none to check. The quote shows it is in the paper.
In the paper
“The funder of the study had no role in study design, data collection, data analysis, data interpretation, or writing of the report.”
§ The SANAD II study of the effectiveness and cost-effectiveness of levetiracetam, zonisamide, or lamotrigine for newly diagnosed focal epilepsy: an open-label, non-inferiority, multicentre, phase 4, randomised controlled trial > Methods > Role of the funding source
plain- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: fails — The paper’s conclusions may not depend on it.
- Based: passes — The paper gives a reason why it holds.
Probably not a substantial claim. The paper’s conclusions may not depend on it.
A conclusion the paper draws from its own results — it cites no other source for it, so there is none to check. The quote shows it is in the paper.
In the paper
“Neither levetiracetam or zonisamide were found to be cost-effective alternatives.”
§ The SANAD II study of the effectiveness and cost-effectiveness of levetiracetam, zonisamide, or lamotrigine for newly diagnosed focal epilepsy: an open-label, non-inferiority, multicentre, phase 4, randomised controlled trial > Abstract > Funding
plain- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
A conclusion the paper draws from its own results — it cites no other source for it, so there is none to check. The quote shows it is in the paper.
In the paper
“The primary outcome in those trials was 6-month seizure freedom, which is too short a timeframe to assess clinical effectiveness in a long-term condition such as epilepsy.”
§ The SANAD II study of the effectiveness and cost-effectiveness of levetiracetam, zonisamide, or lamotrigine for newly diagnosed focal epilepsy: an open-label, non-inferiority, multicentre, phase 4, randomised controlled trial > Abstract > Funding
plain- Asserted: passes — The authors put it forward as true.
- Checkable: fails — It may be too vague to check against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
Probably not a substantial claim. It may be too vague to check against evidence.
The paper relies on this without support.
To the best of our knowledge, this study is the first randomised controlled trial to assess the longer term clinical effectiveness and cost-effectiveness of levetiracetam and zonisamide as first-line treatments for patients with newly diagnosed focal epilepsy.
“To the best of our knowledge, this study is the first randomised controlled trial to assess the longer term clinical effectiveness and cost-effectiveness of levetiracetam and zonisamide as first-line treatments for patients with newly diagnosed focal epilepsy.”
Self-check
Percentages, sums and reported differences re-computed from the paper’s own numbers.
Each contradiction between two passages listed here was confirmed by an independent check.
Rated minor: it would not touch a result — a value no result rests on, a p-value that stays on the same side of the significance level, or a conflict that is clerical, resolved elsewhere in the paper, or outside its own findings.
In the paper
§ The SANAD II study of the effectiveness and cost-effectiveness of levetiracetam, zonisamide, or lamotrigine for newly diagnosed focal epilepsy: an open-label, non-inferiority, multicentre, phase 4, randomised controlled trial > Methods > Statistical analysis
“the one-sided significance level was divided by two (one-side alpha of 0·0125)”
§ The SANAD II study of the effectiveness and cost-effectiveness of levetiracetam, zonisamide, or lamotrigine for newly diagnosed focal epilepsy: an open-label, non-inferiority, multicentre, phase 4, randomised controlled trial > Methods > Statistical analysis
“Therefore, assuming a HR of 1 and 80% power with a one-sided alpha of 0·025, 330 patients were required in each of three treatment groups”
Rated minor: it would not touch a result — a value no result rests on, a p-value that stays on the same side of the significance level, or a conflict that is clerical, resolved elsewhere in the paper, or outside its own findings.
In the paper
“177 [35%] participants in the levetiracetam group”
§ The SANAD II study of the effectiveness and cost-effectiveness of levetiracetam, zonisamide, or lamotrigine for newly diagnosed focal epilepsy: an open-label, non-inferiority, multicentre, phase 4, randomised controlled trial > Results
Reported 35 · recomputed 55.3125
Citations
Cites
A Proportional Hazards Model for the Subdistribution of a Competing Risk
Fine, J. P., & Gray, R. J. (1999) · Journal of the American Statistical Association · doi:10.1080/01621459.1999.10474144 · Cited by 14,290
Scheffer, I. E., Berkovic, S., Capovilla, G., Connolly, M. B., French, J., Guilhoto, L., Hirsch, E., Jain, S., Mathern, G. W., Moshé, S. L., et al. (2017) · Epilepsia · doi:10.1111/epi.13709 · Cited by 5,054
Self-citationProposal for Revised Clinical and Electroencephalographic Classification of Epileptic Seizures
(1981) · Epilepsia · doi:10.1111/j.1528-1157.1981.tb06159.x · Cited by 3,433
Prevalence and incidence of epilepsy
Fiest, K. M., Sauro, K. M., Wiebe, S., Patten, S. B., Kwon, C., Dykeman, J., Pringsheim, T. M., Lorenzetti, D., & Jetté, N. (2016) · Neurology · doi:10.1212/wnl.0000000000003509 · Cited by 1,920
Ravens‐Sieberer, U., & Bullinger, M. (1998) · Quality of Life Research · doi:10.1023/a:1008853819715 · Cited by 1,103
Marson, A. G., Al-Kharusi, A. M., Alwaidh, M., Appleton, R., Baker, G. A., Chadwick, D. W., Cramp, C., Cockerell, O. C., Cooper, P. N., Doughty, J., et al. (2007) · The Lancet · doi:10.1016/s0140-6736(07)60460-7 · Cited by 976
Self-citationReview of statistical methods for analysing healthcare resources and costs
Mihaylova, B., Briggs, A., O'Hagan, A., & Thompson, S. G. (2011) · Health Economics · doi:10.1002/hec.1653 · Cited by 767
Comparison of levetiracetam and controlled-release carbamazepine in newly diagnosed epilepsy
Brodie, M. J., Perucca, E., Ryvlin, P., Ben-Menachem, E., & Meencke, H.-J. (2007) · Neurology · doi:10.1212/01.wnl.0000252941.50833.4a · Cited by 467
Quantification of the completeness of follow-up
Clark, T. G., Altman, D. G., & Stavola, B. L. D. (2002) · The Lancet · doi:10.1016/s0140-6736(02)08272-7 · Cited by 406
Estimating risk for developing epilepsy: A population-based study in Rochester, Minnesota
Hesdorffer, D. C., Logroscino, G., Benn, E. K. T., Katri, N., Cascino, G., & Hauser, W. A. (2011) · Neurology · doi:10.1212/wnl.0b013e318204a36a · Cited by 324
Development of the Quality of Life in Epilepsy Inventory for Adolescents: The QOLIE‐AD‐48
Cramer, J. A., Westbrook, L. E., Devinsky, O., Perrine, K. R., Glassman, M. B., & Camfield, C. (1999) · Epilepsia · doi:10.1111/j.1528-1157.1999.tb00828.x · Cited by 275
Antiepileptic drug monotherapy for epilepsy: a network meta-analysis of individual participant data
Nevitt, S. J., Sudell, M., Weston, J., Smith, C. T., & Marson, A. G. (2017) · Cochrane Database of Systematic Reviews · doi:10.1002/14651858.cd011412.pub3 · Cited by 207
Self-citationThe epilepsies; diagnosis and management
(1991) · General Pharmacology The Vascular System · doi:10.1016/0306-3623(91)90110-r · Cited by 201
Baulac, M., Brodie, M. J., Patten, A., Segieth, J., & Giorgi, L. (2012) · The Lancet Neurology · doi:10.1016/s1474-4422(12)70105-9 · Cited by 186
International Valuation Protocol for the EQ-5D-Y-3L
Ramos-Goñi, J. M., Oppe, M., Stolk, E. A., Shah, K. K., Kreimeier, S., Rivero‐Arias, O., & Devlin, N. J. (2020) · PharmacoEconomics · doi:10.1007/s40273-020-00909-3 · Cited by 166
Measuring the impact of epilepsy: the development of a novel scale
Jacoby, A., Baker, G. A., Smith, D. C., Dewey, M. E., & Chadwick, D. W. (1993) · Epilepsy Research · doi:10.1016/0920-1211(93)90042-6 · Cited by 158
Self-citationTrinka, E., Marson, A. G., Van Paesschen, W., Kälviäinen, R., Marovac, J., Duncan, B., Buyle, S., Hallström, Y., Hon, P., Muscas, G. C., et al. (2013) · Journal of Neurology, Neurosurgery & Psychiatry · doi:10.1136/jnnp-2011-300376 · Cited by 121
Self-citationAntiepileptic drug monotherapy for epilepsy: a network meta-analysis of individual participant data
Nevitt, S. J., Sudell, M., Weston, J., Smith, C. T., & Marson, A. G. (2017) · Cochrane Database of Systematic Reviews · doi:10.1002/14651858.cd011412.pub2 · Cited by 110
Self-citationSchachter, S. C. (2006) · Expert Review of Neurotherapeutics · doi:10.1586/14737175.6.1.111 · Cited by 78
Bonnett, L., Smith, C. T., Smith, D., Williamson, P., Chadwick, D., & Marson, A. G. (2012) · The Lancet Neurology · doi:10.1016/s1474-4422(12)70018-2 · Cited by 69
Self-citationThe development of a QALY measure for epilepsy: NEWQOL-6D
Mulhern, B. J., Rowen, D., Jacoby, A., Marson, A. G., Snape, D., Hughes, D. A., Latimer, N. R., Baker, G. A., & Brazier, J. E. (2012) · Epilepsy & Behavior · doi:10.1016/j.yebeh.2012.02.025 · Cited by 64
Self-citationGabrio, A., Mason, A. J., & Baio, G. (2017) · PharmacoEconomics - Open · doi:10.1007/s41669-017-0015-6 · Cited by 57
Hill, H. R., Rowen, D., Pennington, B., Wong, R., & Wailoo, A. (2020) · Value in Health · doi:10.1016/j.jval.2020.02.011 · Cited by 55
Labor market participation following onset of seizures and early epilepsy: Findings from a UK cohort
Holland, P., Lane, S., Whitehead, M. M., Marson, A. G., & Jacoby, A. (2009) · Epilepsia · doi:10.1111/j.1528-1167.2008.01819.x · Cited by 47
Self-citationFrom clinical trials of antiepileptic drugs to treatment
Perucca, E. (2018) · Epilepsia Open · doi:10.1002/epi4.12239 · Cited by 41
Review of zonisamide development in Japan
Seino, M. (2004) · Seizure · doi:10.1016/j.seizure.2004.04.015 · Cited by 36
Importance of competing risks in the analysis of anti-epileptic drug failure
Williamson, P. R., Smith, C. T., Sander, J. W. A. S., & Marson, A. G. (2007) · Trials · doi:10.1186/1745-6215-8-12 · Cited by 13
Self-citation
Cited by
Sorted by citations
Antiseizure Medications for Adults With Epilepsy
Kanner, A. M., & Bicchi, M. M. (2022) · JAMA · doi:10.1001/jama.2022.3880 · Cited by 480
Asadi‐Pooya, A. A., Brigo, F., Lattanzi, S., & Blümcke, I. (2023) · The Lancet · doi:10.1016/s0140-6736(23)01048-6 · Cited by 269
Stevelink, R., Campbell, C., Chen, S., Abou-Khalil, B. W., Adesoji, O. M., Afawi, Z., Amadori, E., Anderson, A., Anderson, J., Andrade, D. M., et al. (2023) · Nature Genetics · doi:10.1038/s41588-023-01485-w · Cited by 231
Self-citationNeuropharmacology of Antiseizure Drugs
Hakami, T. M. (2021) · Neuropsychopharmacology Reports · doi:10.1002/npr2.12196 · Cited by 171
Antiepileptic drug monotherapy for epilepsy: a network meta-analysis of individual participant data
Nevitt, S. J., Sudell, M., Cividini, S., Marson, A. G., & Smith, C. T. (2022) · Cochrane Database of Systematic Reviews · doi:10.1002/14651858.cd011412.pub4 · Cited by 119
Self-citation
Metadata
- Authors
- Marson, A., Burnside, G., Appleton, R., Smith, D., Leach, J. P., Sills, G., Tudur-Smith, C., Plumpton, C., Hughes, D. A., Williamson, P., Baker, G. A., Balabanova, S., Taylor, C., Brown, R., Hindley, D., Howell, S., Maguire, M., Mohanraj, R., Smith, P. E., Lanyon, K., Manford, M., Chitre, M., Parker, A., Swiderska, N., Appleton, R., Pauling, J., Hughes, A., Gupta, R., Hanif, S., Awadh, M., Ragunathan, S., Cable, N., Cooper, P., Hindley, D., Rakshi, K., Molloy, S., Reuber, M., Ayonrinde, K., Wilson, M., Saladi, S., Gibb, J., Funston, L.-A., Cassidy, D., Boyd, J., Ratnayaka, M., Faza, H., Sadler, M., Al-Moasseb, H., Galtrey, C., Wren, D., Olabi, A., Fuller, G., Khan, M., Kallappa, C., Chinthapalli, R., Aji, B., Davies, R., Foster, K., Hitiris, N., Maguire, M., Hussain, N., Dowson, S., Ellison, J., Sharrack, B., Gandhi, V., Powell, R., Tittensor, P., Summers, B., Shashikiran, S., Dison, P. J., Samarasekera, S., McCorry, D., White, K., Nithi, K., Richardson, M., Brown, R., Page, R., Deekollu, D., Slaght, S., Warriner, S., Ahmed, M., Chaudhuri, A., Chow, G., Artal, J., Kucinskiene, D., Sreenivasa, H., Velmurugan, Zipitis, C. S., McLean, B., Lal, V., Gregoriou, A., Maddison, P., Pickersgill, T., Anderson, J., Lawthom, C., Howell, S., Whitlingum, G., Rakowicz, W., Kinton, L., McLellan, A., Zuberi, S., Kelso, A., Hughes, I., Martland, J., Emsley, H., de Goede, C., Singh, R., Moor, C.-C., Aram, J., Mohanraj, R., Sakthivel, K., Nelapatla, S., Rittey, C., Pinto, A., Leach, J. P., Cock, H., Richardson, A., Houston, E., Cooper, C., Lawson, G., Massarano, A., Burness, C., Marson, A., Smith, D., Wieshmann, U., Dey, I., Sivakumar, P., Yeung, L.-K., Smith, P., Bentur, H., Heafield, T., Mathew, A., Smith, D., & Jauhari, P.
- Affiliations
- University of Liverpool (GB)
- Bangor University (GB)
- Bolton NHS Foundation Trust (GB)
- University of Glasgow (GB)
- Salford Royal NHS Foundation Trust (GB)
- University Hospital of Wales (GB)
- Royal Hallamshire Hospital (GB)
- ORCID
- Burnside, Girvan
- Sills, Graeme
- Plumpton, Catrin
- Hughes, Dyfrig A
- Williamson, Paula
- Baker, Gus A
- Balabanova, Silviya
- Taylor, Claire
- Hindley, Dan
- Manford, Mark
- Parker, Alasdair
- Cooper, Paul
- Hindley, Daniel
- Molloy, Sophie
- Reuber, Markus
- Gibb, John
- Sharrack, Basil
- Tittensor, Phil
- Samarasekera, Shanika
- Nithi, Kannan
- Ahmed, Mansoor
- Chow, Gabriel
- McLean, Brendan
- Maddison, Paul
- Anderson, Joseph
- Lawthom, Charlotte
- Zuberi, Sameer
- Hughes, Imelda
- Emsley, Hedley
- Rittey, Chris
- Pinto, Ashwin
- Cock, Hannah
- Richardson, Anna
- Burness, Christine
- Dey, Indranil
- Smith, David
- Venue
- The Lancet
- Publisher
- Elsevier BV
- Published
- 2021-04
- Volume
- 397
- Issue
- 10282
- Pages
- 1363-1374
- ISSN
- 0099-5355 (ISSN-L)
- 0140-6736
- PMC
- PMC8047799
- OpenAlex
- W3147714437
- Cited by
- 208
- References
- 29
- Citations by year
- 2026: 33 · 2025: 40 · 2024: 44 · 2023: 37 · 2022: 39 · 2021: 15
- FWCI
- 24.40
- Type
- journal article
- Language
- en
- Update notices
- erratum (2021-05-15)
- Open access
- hybrid
- doi.org
- Licence
- Locations
- The Lancet (publishedVersion, cc-by)
- PubMed Central (publishedVersion, cc-by)
- PubMed (publishedVersion)
- ENLIGHTEN (Jurnal Bimbingan dan Konseling Islam) (acceptedVersion, cc-by-sa)
- ORCA Online Research @Cardiff (Cardiff University) (acceptedVersion)
- Research Explorer (The University of Manchester) (submittedVersion, cc-by)
- Bangor University Research Portal (Bangor University) (submittedVersion, other-oa)
- Funders
- National Institute for Health Research
- Topics
- Health Sciences › Medicine › Clinical Neurology › Epilepsy research and treatment
- Health Sciences › Medicine › Pediatrics, Perinatology and Child Health › Pharmacological Effects and Toxicity Studies
- Health Sciences › Medicine › Physiology (medical) › Diet and metabolism studies
- Keywords
- focal epilepsy, newly diagnosed epilepsy, levetiracetam, zonisamide, lamotrigine, non-inferiority, seizure remission, cost-effectiveness, antiepileptic drugs, pediatric epilepsy, adults with epilepsy, drug safety, drug tolerability
- MeSH terms
- Lamotrigine, Levetiracetam, Zonisamide, Administration, Oral, Adolescent, Adult, Aged, Anticonvulsants, Child, Cost-Benefit Analysis, Epilepsies, Partial, Female, Humans, Male, Middle Aged, Treatment Outcome, Young Adult
About these checks
Registry, retraction, Cites and statistics results are computed, not judged, with one exception: a printed reference that no index lists is read once by a model before it counts as a citation error. Claims are extracted by a model and kept only when their quote appears verbatim in the text; each cited source is then checked, with a model’s help, for whether it says what the claim relies on. Those verdicts can be wrong — read the claim’s quote and the cited source before relying on one.
A language model drew the claims from the paper on 2026-10-30, under version 3 of the claim definition (model deepseek-v4.1-flash, prompt extract-v3).
A second model labelled each claim on 2026-10-30 (model jev-1.13-20260917, definition revision gold-guideline-v0.2).
Cited sources are checked with a language model’s help (gpt-6-sol).
Statistics and arithmetic are recomputed, not judged.
Confidence bands are shown only for fields calibrated on our annotated test set. None is calibrated yet, so no band is shown.
What counts as a claim ›How we measure confidence ›How we check this ›
Are you an author, or do you see a problem with this page? Request a review
