

The DOI matches its Crossref record; 31 of the 35 references it cites were found in a registry or an index; none of the 10 sources its claims cite is checked for support yet.
6-month neurological and psychiatric outcomes in 236 379 survivors of COVID-19: a retrospective cohort study using electronic health records
Open accessPublished version of a preprint
Abstract
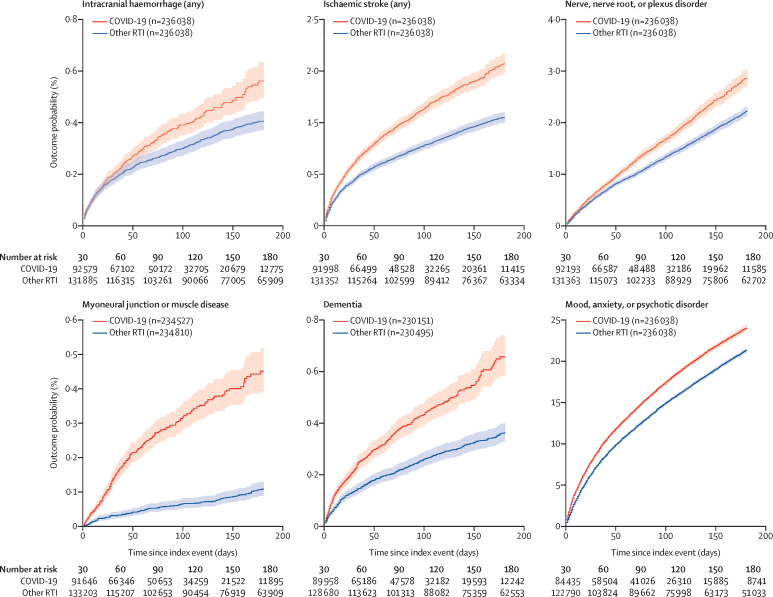
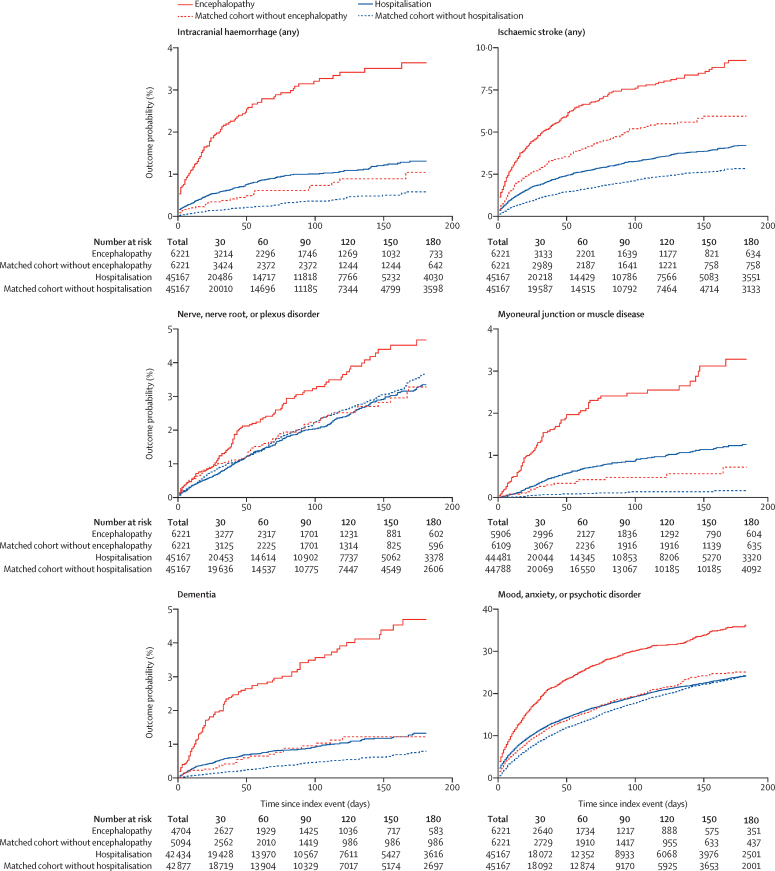
BACKGROUND: Neurological and psychiatric sequelae of COVID-19 have been reported, but more data are needed to adequately assess the effects of COVID-19 on brain health. We aimed to provide robust estimates of incidence rates and relative risks of neurological and psychiatric diagnoses in patients in the 6 months following a COVID-19 diagnosis. METHODS: For this retrospective cohort study and time-to-event analysis, we used data obtained from the TriNetX electronic health records network (with over 81 million patients). Our primary cohort comprised patients who had a COVID-19 diagnosis; one matched control cohort included patients diagnosed with influenza, and the other matched control cohort included patients diagnosed with any respiratory tract infection including influenza in the same period. Patients with a diagnosis of COVID-19 or a positive test for SARS-CoV-2 were excluded from the control cohorts. All cohorts included patients older than 10 years who had an index event on or after Jan 20, 2020, and who were still alive on Dec 13, 2020. We estimated the incidence of 14 neurological and psychiatric outcomes in the 6 months after a confirmed diagnosis of COVID-19: intracranial haemorrhage; ischaemic stroke; parkinsonism; Guillain-Barré syndrome; nerve, nerve root, and plexus disorders; myoneural junction and muscle disease; encephalitis; dementia; psychotic, mood, and anxiety disorders (grouped and separately); substance use disorder; and insomnia. Using a Cox model, we compared incidences with those in propensity score-matched cohorts of patients with influenza or other respiratory tract infections. We investigated how these estimates were affected by COVID-19 severity, as proxied by hospitalisation, intensive therapy unit (ITU) admission, and encephalopathy (delirium and related disorders). We assessed the robustness of the differences in outcomes between cohorts by repeating the analysis in different scenarios. To provide benchmarking for the incidence and risk of neurological and psychiatric sequelae, we compared our primary cohort with four cohorts of patients diagnosed in the same period with additional index events: skin infection, urolithiasis, fracture of a large bone, and pulmonary embolism. FINDINGS: Among 236 379 patients diagnosed with COVID-19, the estimated incidence of a neurological or psychiatric diagnosis in the following 6 months was 33·62% (95% CI 33·17-34·07), with 12·84% (12·36-13·33) receiving their first such diagnosis. For patients who had been admitted to an ITU, the estimated incidence of a diagnosis was 46·42% (44·78-48·09) and for a first diagnosis was 25·79% (23·50-28·25). Regarding individual diagnoses of the study outcomes, the whole COVID-19 cohort had estimated incidences of 0·56% (0·50-0·63) for intracranial haemorrhage, 2·10% (1·97-2·23) for ischaemic stroke, 0·11% (0·08-0·14) for parkinsonism, 0·67% (0·59-0·75) for dementia, 17·39% (17·04-17·74) for anxiety disorder, and 1·40% (1·30-1·51) for psychotic disorder, among others. In the group with ITU admission, estimated incidences were 2·66% (2·24-3·16) for intracranial haemorrhage, 6·92% (6·17-7·76) for ischaemic stroke, 0·26% (0·15-0·45) for parkinsonism, 1·74% (1·31-2·30) for dementia, 19·15% (17·90-20·48) for anxiety disorder, and 2·77% (2·31-3·33) for psychotic disorder. Most diagnostic categories were more common in patients who had COVID-19 than in those who had influenza (hazard ratio [HR] 1·44, 95% CI 1·40-1·47, for any diagnosis; 1·78, 1·68-1·89, for any first diagnosis) and those who had other respiratory tract infections (1·16, 1·14-1·17, for any diagnosis; 1·32, 1·27-1·36, for any first diagnosis). As with incidences, HRs were higher in patients who had more severe COVID-19 (eg, those admitted to ITU compared with those who were not: 1·58, 1·50-1·67, for any diagnosis; 2·87, 2·45-3·35, for any first diagnosis). Results were robust to various sensitivity analyses and benchmarking against the four additional index health events. INTERPRETATION: Our study provides evidence for substantial neurological and psychiatric morbidity in the 6 months after COVID-19 infection. Risks were greatest in, but not limited to, patients who had severe COVID-19. This information could help in service planning and identification of research priorities. Complementary study designs, including prospective cohorts, are needed to corroborate and explain these findings. FUNDING: National Institute for Health Research (NIHR) Oxford Health Biomedical Research Centre.
Overview
AI snapshot
Written from the paper’s full text.
TL;DR
In a retrospective cohort of 236,379 COVID-19 survivors, 33.62% received a neurological or psychiatric diagnosis within 6 months, and 12.84% received a first such diagnosis. Risks were higher than after influenza or other respiratory tract infections and were greatest in patients with more severe COVID-19, including ITU admission or encephalopathy.
Key findings
- Among 236,379 patients with COVID-19, the estimated 6-month incidence of any neurological or psychiatric diagnosis was 33.62% (95% CI 33.17–34.07), and of any first diagnosis was 12.84% (12.36–13.33). For ITU-admitted patients, these were 46.42% (44.78–48.09) and 25.79% (23.50–28.25); for patients with encephalopathy, 62.34% (60.14–64.55) and 31.13% (27.29–35.36).
- Individual 6-month incidences in the whole COVID-19 cohort included anxiety disorder 17.39% (17.04–17.74), mood disorder 13.66% (13.35–13.99), psychotic disorder 1.40% (1.30–1.51), ischaemic stroke 2.10% (1.97–2.23), intracranial haemorrhage 0.56% (0.50–0.63), dementia 0.67% (0.59–0.75), and parkinsonism 0.11% (0.08–0.14).
- Compared with influenza, COVID-19 was associated with higher risk of any diagnosis (HR 1.44, 95% CI 1.40–1.47) and any first diagnosis (1.78, 1.68–1.89); compared with other respiratory tract infections, HRs were 1.16 (1.14–1.17) and 1.32 (1.27–1.36), respectively. ITU admission versus no ITU admission was associated with HR 1.58 (1.50–1.67) for any diagnosis and 2.87 (2.45–3.35) for any first diagnosis.
- Most diagnostic categories were more common after COVID-19 than after influenza, except parkinsonism and Guillain-Barré syndrome, for which HRs were not significantly greater than 1 versus influenza.
Methods
- Retrospective cohort and time-to-event analysis using the TriNetX electronic health records network (over 81 million patients, 62 health-care organisations, primarily USA). The primary cohort had confirmed COVID-19 (ICD-10 U07.1); control cohorts had influenza or any respiratory tract infection including influenza, with COVID-19/SARS-CoV-2-positive patients excluded. All cohorts included patients older than 10 years with an index event on or after Jan 20, 2020, alive on Dec 13, 2020.
- Fourteen neurological and psychiatric outcomes were assessed 1–180 days after the index event, with first versus any diagnoses estimated depending on whether outcomes were chronic or recurrent. Cohorts were propensity-score matched 1:1 on 55 variables; incidence was estimated with Kaplan-Meier, comparisons with log-rank tests, and hazard ratios with Cox proportional hazards models.
- Secondary analyses examined COVID-19 severity via hospitalisation, ITU admission, and encephalopathy, with matched comparisons; sensitivity analyses included patients who died, test-confirmed COVID-19, and pre-pandemic influenza comparisons, plus benchmarking against four additional index events.
Limitations
- The paper states limitations inherent to electronic health records: unknown completeness of records, no validation of diagnoses, and sparse information on socioeconomic and lifestyle factors. It also notes that the choice of comparator cohort influenced hazard ratio magnitude, that encephalopathy was likely under-recorded and results should not be generalised to all patients with delirium, that timing differences and undiagnosed COVID-19 in controls likely made HRs underestimates, and that the study can only show associations, not causality.
- Evident from the text: despite propensity-score matching, residual confounding may remain; diagnoses rely on ICD-10 codes; and follow-up is limited to 6 months, so longer-term trajectories and duration of risk are not established.
Model-written summary. Check it against the paper before relying on it.
Integrity signals
Registry
Cites
Statistics
Figures
Verification
Claims the paper makes
61 Own result · 12 Own interpretation · 8 Not checked yet · 8 Own method · 1 No basis given
A result the paper reports from its own data — it cites no other source for it, so there is none to check. The quote shows it is in the paper.
In the paper
“For a first diagnosis, the HRs were 1·83 (1·71–1·96) versus patients who had influenza and 1·28 (1·23–1·33) versus those who had other respiratory tract infections.”
§ 6-month neurological and psychiatric outcomes in 236 379 survivors of COVID-19: a retrospective cohort study using electronic health records > Results
plaincorrelational- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
- Rests on an assumption: Diagnoses recorded in the electronic health records accurately reflect patients' true clinical diagnoses.
- Rests on an assumption: The propensity score matching adequately controls for confounding by measured covariates.
- Rests on an assumption: The comparator cohorts (influenza and other respiratory tract infections) are appropriate to estimate the excess risk attributable to COVID-19.
A result the paper reports from its own data — it cites no other source for it, so there is none to check. The quote shows it is in the paper.
In the paper
“with a HR of 1·58 (1·50–1·67) for any diagnosis and 2·87 (2·45–3·35) for any first diagnosis (table 5, appendix p 22).”
§ 6-month neurological and psychiatric outcomes in 236 379 survivors of COVID-19: a retrospective cohort study using electronic health records > Results
plaincorrelationaln = 8,942- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
- Rests on an assumption: Diagnoses recorded in the electronic health records accurately reflect patients' true clinical diagnoses.
- Rests on an assumption: The propensity score matching adequately controls for confounding by measured covariates.
A result the paper reports from its own data — it cites no other source for it, so there is none to check. The quote shows it is in the paper.
In the paper
“Among 236 379 patients diagnosed with COVID-19, the estimated incidence of a neurological or psychiatric diagnosis in the following 6 months was 33·62% (95% CI 33·17–34·07), with 12·84% (12·36–13·33) receiving their first such diagnosis.”
- Also stated in: § Results · plain
“In the whole cohort, 33·62% (95% CI 33·17–34·07) of patients received a diagnosis (table 2).”
§ 6-month neurological and psychiatric outcomes in 236 379 survivors of COVID-19: a retrospective cohort study using electronic health records > Abstract > Findings
plainn = 379- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
- Rests on an assumption: Diagnoses recorded in the TriNetX electronic health records accurately reflect the neurological and psychiatric outcomes under study.
- Rests on an assumption: The ICD-10 code U07.1 reliably identifies patients with COVID-19.
- Also stated in: § Results · plain
A result the paper reports from its own data — it cites no other source for it, so there is none to check. The quote shows it is in the paper.
In the paper
“In the group with ITU admission, estimated incidences were 2·66% (2·24–3·16) for intracranial haemorrhage, 6·92% (6·17–7·76) for ischaemic stroke, 0·26% (0·15–0·45) for parkinsonism, 1·74% (1·31–2·30) for dementia, 19·15% (17·90–20·48) for anxiety disorder, and 2·77% (2·31–3·33) for psychotic disorder.”
§ 6-month neurological and psychiatric outcomes in 236 379 survivors of COVID-19: a retrospective cohort study using electronic health records > Abstract > Findings
hedged- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
- Rests on an assumption: Diagnoses recorded in the TriNetX electronic health records accurately reflect the neurological and psychiatric outcomes under study.
- Rests on an assumption: The ICD-10 code U07.1 reliably identifies patients with COVID-19.
A result the paper reports from its own data — it cites no other source for it, so there is none to check. The quote shows it is in the paper.
In the paper
“This comparison showed greater hazard rates for all outcomes in the hospitalised group than in the non-hospitalised group, except for nerve, nerve root, or plexus disorders (table 5, figure 2), with an overall HR of 1·33 (1·29–1·37) for any diagnosis and 1·70 (1·56–1·86) for any first diagnosis.”
§ 6-month neurological and psychiatric outcomes in 236 379 survivors of COVID-19: a retrospective cohort study using electronic health records > Results
plaincorrelationaln = 927- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
- Rests on an assumption: Diagnoses recorded in the electronic health records accurately reflect patients' true clinical diagnoses.
- Rests on an assumption: The propensity score matching adequately controls for confounding by measured covariates.
A result the paper reports from its own data — it cites no other source for it, so there is none to check. The quote shows it is in the paper.
In the paper
“In the group with ITU admission, estimated incidences were 2·66% (2·24–3·16) for intracranial haemorrhage, 6·92% (6·17–7·76) for ischaemic stroke, 0·26% (0·15–0·45) for parkinsonism, 1·74% (1·31–2·30) for dementia, 19·15% (17·90–20·48) for anxiety disorder, and 2·77% (2·31–3·33) for psychotic disorder.”
§ 6-month neurological and psychiatric outcomes in 236 379 survivors of COVID-19: a retrospective cohort study using electronic health records > Abstract > Findings
hedged- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: unclear — It is unclear whether the paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
- Rests on an assumption: Diagnoses recorded in the TriNetX electronic health records accurately reflect the neurological and psychiatric outcomes under study.
- Rests on an assumption: The ICD-10 code U07.1 reliably identifies patients with COVID-19.
A result the paper reports from its own data — it cites no other source for it, so there is none to check. The quote shows it is in the paper.
In the paper
“Any first outcome | 1·78 (1·68–1·89) | <0·0001 | 1·32 (1·27–1·36) | <0·0001 |”
§ 6-month neurological and psychiatric outcomes in 236 379 survivors of COVID-19: a retrospective cohort study using electronic health records > Results
plaincorrelational- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
- Rests on an assumption: Diagnoses recorded in the electronic health records accurately reflect patients' true clinical diagnoses.
- Rests on an assumption: The comparator cohorts (influenza and other respiratory tract infections) are appropriate to estimate the excess risk attributable to COVID-19.
A result the paper reports from its own data — it cites no other source for it, so there is none to check. The quote shows it is in the paper.
In the paper
“HRs remained significantly greater than 1 in this subgroup, with an overall HR for any diagnosis of 1·47 (95% CI 1·44–1·51) for patients who had COVID-19 compared with patients who had influenza, and 1·16 (1·14–1·17) compared with those who had other respiratory tract infections”
§ 6-month neurological and psychiatric outcomes in 236 379 survivors of COVID-19: a retrospective cohort study using electronic health records > Results
plaincorrelational- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
- Rests on an assumption: Diagnoses recorded in the electronic health records accurately reflect patients' true clinical diagnoses.
- Rests on an assumption: The propensity score matching adequately controls for confounding by measured covariates.
- Rests on an assumption: The comparator cohorts (influenza and other respiratory tract infections) are appropriate to estimate the excess risk attributable to COVID-19.
A result the paper reports from its own data — it cites no other source for it, so there is none to check. The quote shows it is in the paper.
In the paper
“Our primary cohort comprised 236 379 patients diagnosed with COVID-19, and our two propensity-score-matched control cohorts comprised 105 579 patients diagnosed with influenza and 236 038 patients diagnosed with any respiratory tract infection including influenza.”
§ 6-month neurological and psychiatric outcomes in 236 379 survivors of COVID-19: a retrospective cohort study using electronic health records > Results
plainn = 579- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
A result the paper reports from its own data — it cites no other source for it, so there is none to check. The quote shows it is in the paper.
In the paper
“For patients who had been admitted to an ITU, the estimated incidence of a diagnosis was 46·42% (44·78–48·09) and for a first diagnosis was 25·79% (23·50–28·25).”
- Also stated in: § Results · plain
“For the cohort subgroups, these estimates were 38·73% (37·87–39·60) for patients who were hospitalised, 46·42% (44·78–48·09) for those admitted to ITU, and 62·34% (60·14–64·55) for those diagnosed with encephalopathy.”
§ 6-month neurological and psychiatric outcomes in 236 379 survivors of COVID-19: a retrospective cohort study using electronic health records > Abstract > Findings
plain- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
- Rests on an assumption: Diagnoses recorded in the TriNetX electronic health records accurately reflect the neurological and psychiatric outcomes under study.
- Rests on an assumption: The ICD-10 code U07.1 reliably identifies patients with COVID-19.
- Also stated in: § Results · plain
- It may state two separate claims as one. 24
- Probably not a substantial claim. 10
A result the paper reports from its own data — it cites no other source for it, so there is none to check. The quote shows it is in the paper.
In the paper
“Most diagnostic categories were more common in patients who had COVID-19 than in those who had influenza (hazard ratio [HR] 1·44, 95% CI 1·40–1·47, for any diagnosis; 1·78, 1·68–1·89, for any first diagnosis) and those who had other respiratory tract infections (1·16, 1·14–1·17, for any diagnosis; 1·32, 1·27–1·36, for any first diagnosis).”
§ 6-month neurological and psychiatric outcomes in 236 379 survivors of COVID-19: a retrospective cohort study using electronic health records > Abstract > Findings
plaincorrelational- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
- Rests on an assumption: Diagnoses recorded in the TriNetX electronic health records accurately reflect the neurological and psychiatric outcomes under study.
- Rests on an assumption: The ICD-10 code U07.1 reliably identifies patients with COVID-19.
- Rests on an assumption: Propensity score matching on the measured covariates adequately controls for confounding by unmeasured factors.
A result the paper reports from its own data — it cites no other source for it, so there is none to check. The quote shows it is in the paper.
In the paper
“HRs were significantly greater than 1 for all diagnoses for patients who had COVID-19 compared with those who had influenza, except for parkinsonism and Guillain-Barré syndrome, and significantly greater than 1 for all diagnoses compared with patients who had respiratory tract infections (table 3).”
§ 6-month neurological and psychiatric outcomes in 236 379 survivors of COVID-19: a retrospective cohort study using electronic health records > Results
plaincorrelational- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
- Rests on an assumption: Diagnoses recorded in the TriNetX electronic health records accurately reflect the neurological and psychiatric outcomes under study.
- Rests on an assumption: The ICD-10 code U07.1 reliably identifies patients with COVID-19.
- Rests on an assumption: Propensity score matching on the measured covariates adequately controls for confounding by unmeasured factors.
A result the paper reports from its own data — it cites no other source for it, so there is none to check. The quote shows it is in the paper.
In the paper
“Most diagnostic categories were more common in patients who had COVID-19 than in those who had influenza (hazard ratio [HR] 1·44, 95% CI 1·40–1·47, for any diagnosis; 1·78, 1·68–1·89, for any first diagnosis) and those who had other respiratory tract infections (1·16, 1·14–1·17, for any diagnosis; 1·32, 1·27–1·36, for any first diagnosis).”
§ 6-month neurological and psychiatric outcomes in 236 379 survivors of COVID-19: a retrospective cohort study using electronic health records > Abstract > Findings
plaincorrelationaln = 379- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
- Rests on an assumption: Diagnoses recorded in the TriNetX electronic health records accurately reflect the neurological and psychiatric outcomes under study.
- Rests on an assumption: The ICD-10 code U07.1 reliably identifies patients with COVID-19.
- Rests on an assumption: Propensity score matching on the measured covariates adequately controls for confounding by unmeasured factors.
A result the paper reports from its own data — it cites no other source for it, so there is none to check. The quote shows it is in the paper.
In the paper
“The COVID-19 cohort was divided into subgroups of patients who were not hospitalised (190 077 patients), those who were hospitalised (46 302 patients), those who required ITU admission (8945 patients), and those who received a diagnosis of encephalopathy (6229 patients).”
§ 6-month neurological and psychiatric outcomes in 236 379 survivors of COVID-19: a retrospective cohort study using electronic health records > Results
plainn = 302- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: fails — The paper’s conclusions may not depend on it.
- Based: passes — The paper gives a reason why it holds.
Probably not a substantial claim. The paper’s conclusions may not depend on it.
A result the paper reports from its own data — it cites no other source for it, so there is none to check. The quote shows it is in the paper.
In the paper
“The COVID-19 cohort was divided into subgroups of patients who were not hospitalised (190 077 patients), those who were hospitalised (46 302 patients), those who required ITU admission (8945 patients), and those who received a diagnosis of encephalopathy (6229 patients).”
§ 6-month neurological and psychiatric outcomes in 236 379 survivors of COVID-19: a retrospective cohort study using electronic health records > Results
plainn = 8,945- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: fails — The paper’s conclusions may not depend on it.
- Based: passes — The paper gives a reason why it holds.
Probably not a substantial claim. The paper’s conclusions may not depend on it.
A result the paper reports from its own data — it cites no other source for it, so there is none to check. The quote shows it is in the paper.
In the paper
“Most diagnostic categories were more common in patients who had COVID-19 than in those who had influenza (hazard ratio [HR] 1·44, 95% CI 1·40–1·47, for any diagnosis; 1·78, 1·68–1·89, for any first diagnosis) and those who had other respiratory tract infections (1·16, 1·14–1·17, for any diagnosis; 1·32, 1·27–1·36, for any first diagnosis).”
§ 6-month neurological and psychiatric outcomes in 236 379 survivors of COVID-19: a retrospective cohort study using electronic health records > Abstract > Findings
plaincorrelational- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
- Rests on an assumption: Diagnoses recorded in the TriNetX electronic health records accurately reflect the neurological and psychiatric outcomes under study.
- Rests on an assumption: The ICD-10 code U07.1 reliably identifies patients with COVID-19.
- Rests on an assumption: Propensity score matching on the measured covariates adequately controls for confounding by unmeasured factors.
A result the paper reports from its own data — it cites no other source for it, so there is none to check. The quote shows it is in the paper.
In the paper
“The COVID-19 cohort was divided into subgroups of patients who were not hospitalised (190 077 patients), those who were hospitalised (46 302 patients), those who required ITU admission (8945 patients), and those who received a diagnosis of encephalopathy (6229 patients).”
§ 6-month neurological and psychiatric outcomes in 236 379 survivors of COVID-19: a retrospective cohort study using electronic health records > Results
plainn = 6,229- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: fails — The paper’s conclusions may not depend on it.
- Based: passes — The paper gives a reason why it holds.
Probably not a substantial claim. The paper’s conclusions may not depend on it.
A result the paper reports from its own data — it cites no other source for it, so there is none to check. The quote shows it is in the paper.
In the paper
“Most diagnostic categories were more common in patients who had COVID-19 than in those who had influenza (hazard ratio [HR] 1·44, 95% CI 1·40–1·47, for any diagnosis; 1·78, 1·68–1·89, for any first diagnosis) and those who had other respiratory tract infections (1·16, 1·14–1·17, for any diagnosis; 1·32, 1·27–1·36, for any first diagnosis).”
§ 6-month neurological and psychiatric outcomes in 236 379 survivors of COVID-19: a retrospective cohort study using electronic health records > Abstract > Findings
plaincorrelational- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
- Rests on an assumption: Diagnoses recorded in the TriNetX electronic health records accurately reflect the neurological and psychiatric outcomes under study.
- Rests on an assumption: The ICD-10 code U07.1 reliably identifies patients with COVID-19.
- Rests on an assumption: Propensity score matching on the measured covariates adequately controls for confounding by unmeasured factors.
A result the paper reports from its own data — it cites no other source for it, so there is none to check. The quote shows it is in the paper.
In the paper
“Similar results were observed when patients who had COVID-19 were compared with those who had one of the four other index events (appendix pp 11–14, 34), except when an outcome had a predicted relationship with the comparator condition (eg, intracranial haemorrhage was more common in association with fracture of a large bone).”
§ 6-month neurological and psychiatric outcomes in 236 379 survivors of COVID-19: a retrospective cohort study using electronic health records > Results
plain- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
- Rests on an assumption: Diagnoses recorded in the TriNetX electronic health records accurately reflect the neurological and psychiatric outcomes under study.
- Rests on an assumption: The ICD-10 code U07.1 reliably identifies patients with COVID-19.
- Rests on an assumption: Propensity score matching on the measured covariates adequately controls for confounding by unmeasured factors.
A result the paper reports from its own data — it cites no other source for it, so there is none to check. The quote shows it is in the paper.
In the paper
“The COVID-19 cohort was divided into subgroups of patients who were not hospitalised (190 077 patients), those who were hospitalised (46 302 patients), those who required ITU admission (8945 patients), and those who received a diagnosis of encephalopathy (6229 patients).”
§ 6-month neurological and psychiatric outcomes in 236 379 survivors of COVID-19: a retrospective cohort study using electronic health records > Results
plainn = 77- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: fails — The paper’s conclusions may not depend on it.
- Based: passes — The paper gives a reason why it holds.
Probably not a substantial claim. The paper’s conclusions may not depend on it.
A result the paper reports from its own data — it cites no other source for it, so there is none to check. The quote shows it is in the paper.
In the paper
“For the overall psychiatric disorder category (ICD-10 F20–48), the HR did vary with time, declining but remaining significantly higher than 1, indicating that the risk was attenuated but maintained 6 months after COVID-19 diagnosis (appendix p 9).”
§ 6-month neurological and psychiatric outcomes in 236 379 survivors of COVID-19: a retrospective cohort study using electronic health records > Results
hedgedcorrelational- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
- Rests on an assumption: Diagnoses recorded in the electronic health records accurately reflect patients' true clinical diagnoses.
A result the paper reports from its own data — it cites no other source for it, so there is none to check. The quote shows it is in the paper.
In the paper
“The timing of index events was such that most infections with influenza and many of the other respiratory tract infections occurred earlier on during the pandemic, whereas the incidence of COVID-19 diagnoses increased over time (appendix p 24).”
§ 6-month neurological and psychiatric outcomes in 236 379 survivors of COVID-19: a retrospective cohort study using electronic health records > Discussion
plaincorrelational- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: fails — The paper’s conclusions may not depend on it.
- Based: passes — The paper gives a reason why it holds.
Probably not a substantial claim. The paper’s conclusions may not depend on it. It may state two separate claims as one.
- Rests on an assumption: Diagnoses recorded in the electronic health records accurately reflect patients' true clinical diagnoses.
A result the paper reports from its own data — it cites no other source for it, so there is none to check. The quote shows it is in the paper.
In the paper
“Our data provide some support for this possibility, although the incidence was low and not all HRs were significant.”
§ 6-month neurological and psychiatric outcomes in 236 379 survivors of COVID-19: a retrospective cohort study using electronic health records > Discussion
hedgedcorrelational- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
- Rests on an assumption: Diagnoses recorded in the electronic health records accurately reflect patients' true clinical diagnoses.
In the paper
“Whether COVID-19 is associated with Guillain-Barré syndrome remains unclear;26 our data were also equivocal, with HRs increased with COVID-19 compared with other respiratory tract infections but not with influenza (table 3), and increased compared with three of the four other index health events (appendix p 34).”
§ 6-month neurological and psychiatric outcomes in 236 379 survivors of COVID-19: a retrospective cohort study using electronic health records > Discussion
What the sources say
- Not checked yetcites [26] Keddie, 2020, Epidemiological and cohort study finds no association between COVID-19 and Guillain-Barré syndrome, Brain
plaincorrelational- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
- Rests on an assumption: Diagnoses recorded in the electronic health records accurately reflect patients' true clinical diagnoses.
- Rests on an assumption: The comparator cohorts (influenza and other respiratory tract infections) are appropriate to estimate the excess risk attributable to COVID-19.
None of the sources cited for this claim have been checked yet.
In the paper
“Consistent with several other reports,23, 24 the risk of cerebrovascular events (ischaemic stroke and intracranial haemorrhage) was elevated after COVID-19, with the incidence of ischaemic stroke rising to almost one in ten (or three in 100 for a first stroke) in patients with encephalopathy.”
§ 6-month neurological and psychiatric outcomes in 236 379 survivors of COVID-19: a retrospective cohort study using electronic health records > Discussion
What the sources say
- Not checked yetcites [23] Siow, 2021, Stroke as a neurological complication of COVID-19: a systematic review and meta-analysis of incidence, outcomes and predictors, J Stroke Cerebrovasc Dis source
- Not checked yetcites [24] Hernandez-Fernandez, 2020, Cerebrovascular disease in patients with COVID-19: neuroimaging, histological and clinical description, Brain source
plaincorrelational- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
- Rests on an assumption: Diagnoses recorded in the electronic health records accurately reflect patients' true clinical diagnoses.
None of the sources cited for this claim have been checked yet.
In the paper
“Even among patients who were hospitalised, only about 11% received this diagnosis, whereas much higher rates would be expected.18, 30”
§ 6-month neurological and psychiatric outcomes in 236 379 survivors of COVID-19: a retrospective cohort study using electronic health records > Discussion
What the sources say
- Not checked yetcites [18] Oldham, 2020, Characterising neuropsychiatric disorders in patients with COVID-19, Lancet Psychiatry source
- Not checked yetcites [30] Docherty, 2020, Features of 20 133 UK patients in hospital with covid-19 using the ISARIC WHO Clinical Characterisation Protocol: prospective observational cohort study, BMJ
plain- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: unclear — It is unclear whether the paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
- Rests on an assumption: Diagnoses recorded in the electronic health records accurately reflect patients' true clinical diagnoses.
A result the paper reports from its own data — it cites no other source for it, so there is none to check. The quote shows it is in the paper.
In the paper
“Although the estimated incidence was modest in the whole COVID-19 cohort (table 2), 2·66% of patients older than 65 years (appendix p 28) and 4·72% who had encephalopathy (table 2), received a first diagnosis of dementia within 6 months of having COVID-19.”
§ 6-month neurological and psychiatric outcomes in 236 379 survivors of COVID-19: a retrospective cohort study using electronic health records > Discussion
plaincorrelational- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
- Rests on an assumption: Diagnoses recorded in the electronic health records accurately reflect patients' true clinical diagnoses.
The paper states this without a source or data behind it here, so there is nothing to check it against. The quote shows it is in the paper.
In the paper
“HRs for most neurological outcomes were constant, and hence the risks associated with COVID-19 persisted up to the 6-month timepoint.”
§ 6-month neurological and psychiatric outcomes in 236 379 survivors of COVID-19: a retrospective cohort study using electronic health records > Discussion
plaincorrelational- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
- Rests on an assumption: Diagnoses recorded in the electronic health records accurately reflect patients' true clinical diagnoses.
A result the paper reports from its own data — it cites no other source for it, so there is none to check. The quote shows it is in the paper.
In the paper
“Substance use disorders and insomnia were also more common in COVID-19 survivors than in those who had influenza or other respiratory tract infections (except for the incidence of a first diagnosis of substance use disorder after COVID-19 compared with other respiratory tract infections).”
§ 6-month neurological and psychiatric outcomes in 236 379 survivors of COVID-19: a retrospective cohort study using electronic health records > Discussion
plaincorrelational- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
- Rests on an assumption: Diagnoses recorded in the electronic health records accurately reflect patients' true clinical diagnoses.
- Rests on an assumption: The comparator cohorts (influenza and other respiratory tract infections) are appropriate to estimate the excess risk attributable to COVID-19.
What the paper did — it cites no source for this, so there is none to check. The quote shows it is in the paper.
In the paper
“The proportional hazard assumption was tested with the generalised Schoenfeld approach.”
§ 6-month neurological and psychiatric outcomes in 236 379 survivors of COVID-19: a retrospective cohort study using electronic health records > Methods > Statistical analysis
plain- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: fails — The paper’s conclusions may not depend on it.
- Based: passes — The paper gives a reason why it holds.
Probably not a substantial claim. The paper’s conclusions may not depend on it.
What the paper did — it cites no source for this, so there is none to check. The quote shows it is in the paper.
In the paper
“Our study was reported according to the Reporting of studies Conducted using Observational Routinely-collected health Data (RECORD, appendix pp 55–60).”
§ 6-month neurological and psychiatric outcomes in 236 379 survivors of COVID-19: a retrospective cohort study using electronic health records > Methods > Statistical analysis
plain- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: fails — The paper’s conclusions may not depend on it.
- Based: passes — The paper gives a reason why it holds.
Probably not a substantial claim. The paper’s conclusions may not depend on it.
In the paper
“Similar concerns have been raised regarding psychiatric sequelae of COVID-19,12, 13 with evidence showing that survivors are indeed at increased risk of mood and anxiety disorders in the 3 months after infection.14”
§ 6-month neurological and psychiatric outcomes in 236 379 survivors of COVID-19: a retrospective cohort study using electronic health records > Introduction
What the sources say
- Not checked yetcites [14] Taquet, 2021, Bidirectional associations between COVID-19 and psychiatric disorder: retrospective cohort studies of 62 354 COVID-19 cases in the USA, Lancet Psychiatry source
boostedcorrelational- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
Probably not a substantial claim.
What the paper did — it cites no source for this, so there is none to check. The quote shows it is in the paper.
In the paper
“The only exception was for intracranial haemorrhage and ischaemic stroke in patients who had COVID-19 when compared with patients who had other respiratory tract infections (p=0·012 for intracranial haemorrhage and p=0·032 for ischaemic stroke).”
§ 6-month neurological and psychiatric outcomes in 236 379 survivors of COVID-19: a retrospective cohort study using electronic health records > Results
plain- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: unclear — It is unclear whether the paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
A conclusion the paper draws from its own results — it cites no other source for it, so there is none to check. The quote shows it is in the paper.
In the paper
“Some patients in the comparison cohorts are likely to have had undiagnosed COVID-19; this would also tend to make our HRs an underestimate.”
§ 6-month neurological and psychiatric outcomes in 236 379 survivors of COVID-19: a retrospective cohort study using electronic health records > Discussion
hedgedconditional- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: unclear — It is unclear whether the paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
- Rests on an assumption: Diagnoses recorded in the electronic health records accurately reflect patients' true clinical diagnoses.
What the paper did — it cites no source for this, so there is none to check. The quote shows it is in the paper.
In the paper
“The increased rates of neurological and psychiatric sequelae were robust in all three sensitivity analyses: when patients who had died by the time of the analysis were included (appendix p 51), when the COVID-19 diagnosis was confirmed by use of an RNA or antigen test (appendix p 52), and when the sequelae were compared with those observed in patients who had influenza in 2019 or 2018 (appendix pp”
§ 6-month neurological and psychiatric outcomes in 236 379 survivors of COVID-19: a retrospective cohort study using electronic health records > Results
plaincorrelational- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
- Rests on an assumption: Diagnoses recorded in the electronic health records accurately reflect patients' true clinical diagnoses.
A conclusion the paper draws from its own results — it cites no other source for it, so there is none to check. The quote shows it is in the paper.
In the paper
“Overall, COVID-19 was associated with increased risk of neurological and psychiatric outcomes, but the incidences and HRs of these were greater in patients who had required hospitalisation, and markedly so in those who had required ITU admission or had developed encephalopathy, even after extensive propensity score matching for other factors (eg, age or previous cerebrovascular disease).”
§ 6-month neurological and psychiatric outcomes in 236 379 survivors of COVID-19: a retrospective cohort study using electronic health records > Discussion
plaincorrelational- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
- Rests on an assumption: Diagnoses recorded in the electronic health records accurately reflect patients' true clinical diagnoses.
- Rests on an assumption: The propensity score matching adequately controls for confounding by measured covariates.
What the paper did — it cites no source for this, so there is none to check. The quote shows it is in the paper.
In the paper
“Our findings are robust given the sample size, the propensity score matching, and the results of the sensitivity and secondary analyses.”
§ 6-month neurological and psychiatric outcomes in 236 379 survivors of COVID-19: a retrospective cohort study using electronic health records > Discussion
plain- Asserted: passes — The authors put it forward as true.
- Checkable: fails — It may be too vague to check against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
Probably not a substantial claim. It may be too vague to check against evidence.
- Rests on an assumption: The propensity score matching adequately controls for confounding by measured covariates.
A conclusion the paper draws from its own results — it cites no other source for it, so there is none to check. The quote shows it is in the paper.
In the paper
“Finally, a study of this kind can only show associations; efforts to identify mechanisms and assess causality will require prospective cohort studies and additional study designs.”
§ 6-month neurological and psychiatric outcomes in 236 379 survivors of COVID-19: a retrospective cohort study using electronic health records > Discussion
plaincorrelational- Asserted: passes — The authors put it forward as true.
- Checkable: fails — It may be too vague to check against evidence.
- Load-bearing: fails — The paper’s conclusions may not depend on it.
- Based: passes — The paper gives a reason why it holds.
Probably not a substantial claim. It may be too vague to check against evidence. The paper’s conclusions may not depend on it. It may state two separate claims as one.
A conclusion the paper draws from its own results — it cites no other source for it, so there is none to check. The quote shows it is in the paper.
In the paper
“Therefore, as with the neurological outcomes, the psychiatric sequelae of COVID-19 appear widespread and to persist up to, and probably beyond, 6 months.”
§ 6-month neurological and psychiatric outcomes in 236 379 survivors of COVID-19: a retrospective cohort study using electronic health records > Discussion
hedgedcorrelational- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
- Rests on an assumption: Diagnoses recorded in the electronic health records accurately reflect patients' true clinical diagnoses.
In the paper
“Nevertheless, they have weaknesses inherent to an electronic health records study,29 such as the unknown completeness of records, no validation of diagnoses, and sparse information on socioeconomic and lifestyle factors.”
§ 6-month neurological and psychiatric outcomes in 236 379 survivors of COVID-19: a retrospective cohort study using electronic health records > Discussion
What the sources say
- Not checked yetcites [29] Casey, 2016, Using electronic health records for population health research: a review of methods and applications, Annu Rev Public Health source
plain- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: unclear — It is unclear whether the paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
A conclusion the paper draws from its own results — it cites no other source for it, so there is none to check. The quote shows it is in the paper.
In the paper
“The effect of these timing differences on observed rates of sequelae is unclear but, if anything, they are likely to make the HRs an underestimate because COVID-19 cases were diagnosed at a time when all other diagnoses were made at a lower rate in the population (appendix p 24).”
§ 6-month neurological and psychiatric outcomes in 236 379 survivors of COVID-19: a retrospective cohort study using electronic health records > Discussion
hedgedconditional- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: unclear — It is unclear whether the paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
- Rests on an assumption: Diagnoses recorded in the electronic health records accurately reflect patients' true clinical diagnoses.
A conclusion the paper draws from its own results — it cites no other source for it, so there is none to check. The quote shows it is in the paper.
In the paper
“Under-recording of delirium during acute illness is well known and probably means that the diagnosed cases had prominent or sustained features; as such, results for this group should not be generalised to all patients with COVID-19 who experience delirium.”
§ 6-month neurological and psychiatric outcomes in 236 379 survivors of COVID-19: a retrospective cohort study using electronic health records > Discussion
hedgedconditional- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
- Rests on an assumption: Diagnoses recorded in the electronic health records accurately reflect patients' true clinical diagnoses.
The paper relies on this without support.
Diagnoses recorded in the TriNetX electronic health records accurately reflect the neurological and psychiatric outcomes under study.
“Available data include demographics, diagnoses (using codes from ICD-10), medications, procedures, and measurements (eg, blood pressure and body-mass index).”
The paper relies on this without support.
The ICD-10 code U07.1 reliably identifies patients with COVID-19.
“The primary cohort was defined as all patients who had a confirmed diagnosis of COVID-19 (ICD-10 code U07.1).”
The paper relies on this without support.
Propensity score matching on the measured covariates adequately controls for confounding by unmeasured factors.
“We used propensity score matching19 to create cohorts with matched baseline characteristics, done within the TriNetX network.”
The authors state this as an assumption.
Hospitalisation, ITU admission, and encephalopathy are valid proxies for COVID-19 severity.
“We investigated how these estimates were affected by COVID-19 severity, as proxied by hospitalisation, intensive therapy unit (ITU) admission, and encephalopathy (delirium and related disorders).”
The paper relies on this without support.
Diagnoses recorded in the electronic health records accurately reflect patients' true clinical diagnoses.
“Nevertheless, they have weaknesses inherent to an electronic health records study,29 such as the unknown completeness of records, no validation of diagnoses, and sparse information on socioeconomic and lifestyle factors.”
The paper relies on this without support.
The propensity score matching adequately controls for confounding by measured covariates.
“even after extensive propensity score matching for other factors (eg, age or previous cerebrovascular disease)”
The paper relies on this without support.
The comparator cohorts (influenza and other respiratory tract infections) are appropriate to estimate the excess risk attributable to COVID-19.
“the choice of cohorts against which to compare COVID-19 outcomes influenced the magnitude of the HRs (table 3, appendix p 34).”
The paper relies on this without support.
The 6-month follow-up period is sufficient to capture the main neurological and psychiatric outcomes of interest.
“Longer-term studies are needed to ascertain the duration of risk and the trajectory for individual diagnoses.”
Claims other papers make about this one
Each is checked against this paper’s own text: does it say what the citing paper says it does?
The source backs part of the claim, not all of it — or backs it for a different population, condition or comparison.
In the citing paper
“compared to 24 and 25 percent of non-hospitalized, and non-ICU-treated hospitalized patients (18).”
From Cognitive Behavioral Therapy and Acceptance and Commitment Therapy (CBT-ACT) vs. Standard Care After Critical Illness Due to COVID-19: Protocol for a Pilot Randomized Controlled Trial (2022) · cites this paper as [18]
Experimental — accuracy not yet measuredThe source backs part of the claim, not all of it — or backs it for a different population, condition or comparison.
In the citing paper
“6-month prevalence of depression, mood or psychotic disorders was seen in 28 percent of ICU-treated COVID-19 patients in a recent study”
From Cognitive Behavioral Therapy and Acceptance and Commitment Therapy (CBT-ACT) vs. Standard Care After Critical Illness Due to COVID-19: Protocol for a Pilot Randomized Controlled Trial (2022) · cites this paper as [18]
Experimental — accuracy not yet measuredThe cited source says what the claim attributes to it.
In the citing paper
“These issues appear to arise more frequently among COVID-19 survivors compared with other respiratory infections,9 healthcare workers or the general population3 as seen in the larger prevalence of depression, anxiety and insomnia.”
From Psychological treatments for the mental health symptoms among individuals infected with COVID-19: a scoping review protocol (2023) · cites this paper as [9]
The cited source says what the claim attributes to it.
In the citing paper
“Thus, although there is data pointing toward a narrow difference in mental health consequences between ICU-treated and other COVID-19 patients (18), there is still reason to believe that severity of disease in COVID-19 is associated with long-term mental health problems.”
The cited source says what the claim attributes to it.
In the citing paper
“Another study found that the hazard ratios for developing a mood or anxiety disorder in a COVID-19 recovery sample compared to people who had been infected with influenza were 1.47, p < 0.001 (1.79 for first-time mood diagnosis) and 1.45, p < 0.001 (1.78 for first-time anxiety diagnosis), respectively (Taquet et al. 2021).”
From Illness Stigma and Shame in People With Chronic Illnesses vs. SARS‐CoV‐2 Survivors: Associations With Psychological Distress Through Psychological Flexibility and Self‐Compassion. (2024) · cites this paper as Taquet et al. 2021
In the citing paper
“Taquet et al. (2021) reported a prevalence of anxiety disorder of 7.11% (95% CI = 6.82, 7.41).”
From Long-term effects of COVID-19 on mental health: a systematic review (2022) · cites this paper as Taquet et al. (2021)
In the citing paper
“Compared to clinical diagnoses reported by Taquet et al. (2021), self-reported anxiety prevalence was significantly higher, further indicating the disparities between clinical diagnosis and patient-reported screening questionnaires.”
From Long-term effects of COVID-19 on mental health: a systematic review (2022) · cites this paper as Taquet et al. (2021)
In the citing paper
“Taquet et al. (2021) reported a low prevalence of mood disorders, with other studies stating that long-term anxiety and depression in COVID-19 patients are similar to pre-pandemic levels (Klaser et al., 2021).”
From Long-term effects of COVID-19 on mental health: a systematic review (2022) · cites this paper as Taquet et al., 2021
Self-check
Percentages, sums and reported differences re-computed from the paper’s own numbers.
Each contradiction between two passages listed here was confirmed by an independent check.
Rated minor: it would not touch a result — a value no result rests on, a p-value that stays on the same side of the significance level, or a conflict that is clerical, resolved elsewhere in the paper, or outside its own findings.
In the paper
§ 6-month neurological and psychiatric outcomes in 236 379 survivors of COVID-19: a retrospective cohort study using electronic health records > Results
“44 927 matched patients; matched baseline characteristics are presented in the appendix, pp 41–42”
§ 6-month neurological and psychiatric outcomes in 236 379 survivors of COVID-19: a retrospective cohort study using electronic health records > Results
“COVID-19 with vs without hospitalisation (N=45 167) HR (95% CI)”
Rated minor: it would not touch a result — a value no result rests on, a p-value that stays on the same side of the significance level, or a conflict that is clerical, resolved elsewhere in the paper, or outside its own findings.
In the paper
§ 6-month neurological and psychiatric outcomes in 236 379 survivors of COVID-19: a retrospective cohort study using electronic health records > Results
“significantly greater than 1 for all diagnoses compared with patients who had respiratory tract infections (table 3)”
§ 6-month neurological and psychiatric outcomes in 236 379 survivors of COVID-19: a retrospective cohort study using electronic health records > Results
“| Substance use disorder (first) | 1·22 (1·09–1·37) | 0·0006 | 0·92 (0·86–0·99) | 0·033 |”
Citations
Cites
Austin, P. C. (2011) · Multivariate Behavioral Research · doi:10.1080/00273171.2011.568786 · Cited by 12,242 · cited 1×
“HRs for COVID-19 diagnosis compared with the additional four index events showed more variation with time, partly reflecting the natural history of the comparator condition (appendix, pp 16–19, 36).”
Factors associated with COVID-19-related death using OpenSAFELY
Williamson, E. J., Walker, A. J., Bhaskaran, K., Bacon, S., Bates, C., Morton, C. E., Curtis, H. J., Mehrkar, A., Evans, D., Inglesby, P., et al. (2020) · Nature · doi:10.1038/s41586-020-2521-4 · Cited by 6,674
Holmes, E. A., O'Connor, R. C., Perry, V. H., Tracey, I., Wessely, S., Arseneault, L., Ballard, C., Christensen, H., Cohen Silver, R., Everall, I., et al. (2020) · The Lancet Psychiatry · doi:10.1016/s2215-0366(20)30168-1 · Cited by 5,715 · cited 5×
“Our primary cohort comprised 236 379 patients diagnosed with COVID-19, and our two propensity-score-matched control cohorts comprised 105 579 patients diagnosed with influenza and 236 038 patients diagnosed with any respiratory tract infection including influenza.”
InfluentialDocherty, A. B., Harrison, E. M., Green, C. A., Hardwick, H. E., Pius, R., Norman, L., Holden, K. A., Read, J. M., Dondelinger, F., Carson, G., et al. (2020) · BMJ · doi:10.1136/bmj.m1985 · Cited by 3,481
COVID-19 pandemic and mental health consequences: Systematic review of the current evidence
Vindegaard, N., & Benros, M. E. (2020) · Brain, Behavior, and Immunity · doi:10.1016/j.bbi.2020.05.048 · Cited by 3,221 · cited 1×
“11 Similar concerns have been raised regarding psychiatric sequelae of COVID-19, 12,13 with evidence showing that survivors are indeed at increased risk of mood and anxiety disorders in the 3 months after infection.”
Rogers, J. P., Chesney, E., Oliver, D., Pollak, T. A., McGuire, P., Fusar-Poli, P., Zandi, M. S., Lewis, G., & David, A. S. (2020) · The Lancet Psychiatry · doi:10.1016/s2215-0366(20)30203-0 · Cited by 2,407
Neurological associations of COVID-19
Ellul, M. A., Benjamin, L., Singh, B., Lant, S., Michael, B. D., Easton, A., Kneen, R., Defres, S., Sejvar, J., & Solomon, T. (2020) · The Lancet Neurology · doi:10.1016/s1474-4422(20)30221-0 · Cited by 2,156
Royston, P. J., & Parmar, M. (2002) · Statistics in Medicine · doi:10.1002/sim.1203 · Cited by 1,537 · cited 2×
“…significantly greater than 1 in this subgroup, with an overall HR for any diagnosis of 1·47 (95% CI 1·44–1·51) for patients who had COVID-19 compared with patients who had influenza, and 1·16 (1·14–1·17) compared with those who had other respiratory tract infections (table 4, appendix pp 20–21).”
Taquet, M., Luciano, S., Geddes, J. R., & Harrison, P. J. (2021) · The Lancet Psychiatry · doi:10.1016/s2215-0366(20)30462-4 · Cited by 1,484
Self-citationMeinhardt, J., Radke, J., Dittmayer, C., Franz, J., Thomas, C., Mothes, R., Laue, M., Schneider, J., Brünink, S., Greuel, S., et al. (2021) · Nature Neuroscience · doi:10.1038/s41593-020-00758-5 · Cited by 1,458 · cited 1×
“Potential mechanisms for this association include viral invasion of the CNS, 10,11 hypercoagulable states, 22 and neural effects of the immune response.”
Cited by
Sorted by citations
Items 301–400 of 1,002
Human resources analytics: where do we go from here?
Bahuguna, P. C., Srivastava, R., & Tiwari, S. (2023) · Benchmarking An International Journal · doi:10.1108/bij-06-2022-0401 · Cited by 60
Digital epidemiology: harnessing big data for early detection and monitoring of viral outbreaks
Fallatah, D. I., & Adekola, H. A. (2024) · Infection Prevention in Practice · doi:10.1016/j.infpip.2024.100382 · Cited by 50
Secuelas médicas de la COVID-19
Peramo-Álvarez, F. P., Zúñiga, M. Á. L., & López‐Ruz, M. Á. (2021) · Medicina Clínica · doi:10.1016/j.medcli.2021.04.023 · Cited by 55
Townsend, L., Dyer, A. H., McCluskey, P., O’Brien, K., Dowds, J., Laird, E. J., Bannan, C., Bourke, N. M., Cheallaigh, C. N., Byrne, D., et al. (2021) · Nutrients · doi:10.3390/nu13072430 · Cited by 44
Psychosis during the COVID-19 pandemic: A systematic review of case reports and case series
Chaudhary, A. M. D., Musavi, N. B., Saboor, S., Javed, S., Khan, S., & Naveed, S. (2022) · Journal of Psychiatric Research · doi:10.1016/j.jpsychires.2022.06.041 · Cited by 40
Diana, L., Regazzoni, R., Sozzi, M., Piconi, S., Borghesi, L., Lazzaroni, E., Basilico, P., Aliprandi, A., Bolognini, N., Bonardi, D. R., et al. (2022) · Journal of the Neurological Sciences · doi:10.1016/j.jns.2022.120511 · Cited by 39
Infection and chronic disease activate a systemic brain-muscle signaling axis
Yang, S., Tian, M., Dai, Y., Wang, R., Yamada, S., Feng, S., Wang, Y., Chhangani, D., Ou, T., Li, W., et al. (2024) · Science Immunology · doi:10.1126/sciimmunol.adm7908 · Cited by 58
Weich, S. (2022) · BMJ · doi:10.1136/bmj.o326 · Cited by 38
Garout, M. A., Saleh, S. A. K., Adly, H. M., Abdulkhaliq, A. A., Khafagy, A. A., Abdeltawab, M. R., Rabaan, A. A., Rodriguez-Morales, A. J., Al‐Tawfiq, J. A., & Alandiyjany, M. N. (2022) · Infection · doi:10.1007/s15010-022-01788-w · Cited by 46
Skyrud, K. D., Hernæs, K. H., Telle, K. E., & Magnusson, K. (2021) · PLoS ONE · doi:10.1371/journal.pone.0257926 · Cited by 38
Engelmann, P., Löwe, B., Brehm, T. T., Weigel, A., Ullrich, F., Addo, M. M., Wiesch, J. S. Z., Lohse, A. W., & Toussaint, A. C. (2022) · Frontiers in Psychology · doi:10.3389/fpsyg.2022.1022203 · Cited by 42
Godoy-González, M., Navarra‐Ventura, G., Gomà, G., de Haro, C., Espinal, C., Fortià, C., Ridao, N., Rebanal, N. M., Oliveras-Furriols, L., Subirá, C., et al. (2023) · Critical Care · doi:10.1186/s13054-023-04478-7 · Cited by 47
SARS-CoV-2 RNA in the Cerebrospinal Fluid of a Patient with Long COVID
Viszlayová, D., Sojka, M., Dobrodenková, S., Szabó, S., Bilec, O., Turzová, M., Ďurina, J., Baloghová, B., Borbély, Z., & Kršák, M. (2021) · Therapeutic Advances in Infectious Disease · doi:10.1177/20499361211048572 · Cited by 38
Post COVID-19 neurological complications; a meta-analysis
Ahmed, J. O., Ahmad, S. A., Hassan, M. N., Kakamad, F. H., Salih, R. Q. M., Abdullah, H. O., Fattah, F. H. R., Mohammed, S. H., Ali, R. K., & Salih, A. M. (2022) · Annals of Medicine and Surgery · doi:10.1016/j.amsu.2022.103440 · Cited by 41
Gan, Y., Wang, C., He, R.-H., Hsu, P.-C., Yeh, H.-H., Hsieh, T.-H., Lin, H., Cheng, M.-Y., Jeng, C., Huang, M., et al. (2022) · Journal of Neuroinflammation · doi:10.1186/s12974-022-02517-8 · Cited by 40
Brain hypoxia, neurocognitive impairment, and quality of life in people post-COVID-19
Adingupu, D. D., Soroush, A., Hansen, A., Twomey, R., & Dunn, J. F. (2023) · Journal of Neurology · doi:10.1007/s00415-023-11767-2 · Cited by 46
Is there a common pathophysiological mechanism between COVID-19 and depression?
Lopes, L. D. S., Silva, R. O., Lima, G. D. S., Costa, A. C. D. A., de Barros, D. F., & Silva‐Néto, R. P. (2021) · Acta Neurologica Belgica · doi:10.1007/s13760-021-01748-5 · Cited by 42
Beghi, E., Helbok, R., Öztürk, Ş., Karadaş, Ö., Lisnic, V., Grosu, O., Kovács, T., Dobronyi, L., Bereczki, D., Cotelli, M. S., et al. (2022) · European Journal of Neurology · doi:10.1111/ene.15293 · Cited by 39
Braga, L. W., de Oliveira, S. B., Moreira, A. S., Pereira, M. E., Carneiro, V. S., Serio, A., Freitas, L. F., Isidro, H. B. L., & Souza, L. M. N. (2022) · Neurorehabilitation · doi:10.3233/nre-228020 · Cited by 40
Direct health care costs associated with COVID-19 in the United States
DeMartino, J. K., Swallow, E., Goldschmidt, D., Yang, K., Viola, M., Radtke, T., & Kirson, N. Y. (2022) · Journal of Managed Care & Specialty Pharmacy · doi:10.18553/jmcp.2022.22050 · Cited by 39
Agergaard, J., Gunst, J. D., Schiøttz‐Christensen, B., Østergaard, L. J., & Wejse, C. M. (2023) · International Journal of Infectious Diseases · doi:10.1016/j.ijid.2023.10.022 · Cited by 37
Delirium and neuropsychological outcomes in critically Ill patients with COVID-19: a cohort study
Ragheb, J. W., McKinney, A., Zierau, M., Brooks, J., Hill-Caruthers, M., Iskander, M., Ahmed, Y., Lobo, R. R., Mentz, G. B., & Vlisides, P. E. (2021) · BMJ Open · doi:10.1136/bmjopen-2021-050045 · Cited by 38
Kunzler, A. M., Lindner, S., Röthke, N., Schäfer, S. K., Metzendorf, M., Sachkova, A., Müller-Eberstein, R., Klinger, C., Burns, J., Coenen, M., et al. (2023) · International Journal of Environmental Research and Public Health · doi:10.3390/ijerph20020948 · Cited by 40
Brimson, J. M., Prasanth, M. I., Malar, D. S., Brimson, S., Thitilertdecha, P., & Tencomnao, T. (2021) · Expert Opinion on Therapeutic Targets · doi:10.1080/14728222.2021.1952987 · Cited by 36
Setting Priorities to Address Research Gaps in Long-term COVID-19 Outcomes in Children
Munblit, D., Sigfrid, L., & Warner, J. O. (2021) · Archives of Pediatrics and Adolescent Medicine · doi:10.1001/jamapediatrics.2021.2281 · Cited by 37
Neurological sequelae of COVID-19: a review
Peterson, C., Sarangi, A., & Bangash, F. (2021) · The Egyptian Journal of Neurology Psychiatry and Neurosurgery · doi:10.1186/s41983-021-00379-0 · Cited by 36
Mental health outcomes of adults hospitalized for COVID-19: A systematic review
Veazie, S., Lafavor, B., Vela, K., Young, S., Sayer, N. A., Carlson, K. F., & O'Neil, M. E. (2022) · Journal of Affective Disorders Reports · doi:10.1016/j.jadr.2022.100312 · Cited by 35
Frontera, J. A., Sabadia, S. B., Yang, D., de Havenon, A., Yaghi, S. R., Lewis, A. K., Lord, A. S., Melmed, K. R., Thawani, S. P., Balcer, L. J., et al. (2022) · Journal of the Neurological Sciences · doi:10.1016/j.jns.2022.120487 · Cited by 42
Kalamara, E. I., Pataka, A., Boutou, A., Panagiotidou, E. S., Georgopoulou, A., Ballas, E. T., Chloros, D. A., Metallidis, S., Kioumis, I. P., & Pitsiou, G. (2022) · Journal of Personalized Medicine · doi:10.3390/jpm12111909 · Cited by 39
Al‐Hakeim, H. K., Al-Rubaye, H. T., Jubran, A. S., Almulla, A. F., Moustafa, S. R., & Maes, M. H. J. (2023) · Brazilian Journal of Psychiatry · doi:10.47626/1516-4446-2022-3002 · Cited by 35
COVID-19 and Risk for Mental Disorders Among Adults in Denmark
Nersesjan, V., Christensen, R. H. B., Kondziella, D., & Benros, M. E. (2023) · JAMA Psychiatry · doi:10.1001/jamapsychiatry.2023.1265 · Cited by 35
Post-COVID-19 Syndrome Mechanisms, Prevention and Management
Najafi, M. B., & Javanmard, S. (2023) · International Journal of Preventive Medicine · doi:10.4103/ijpvm.ijpvm_508_21 · Cited by 38
Factors associated with impaired quality of life three months after being diagnosed with COVID-19
Rass, V., Ianosi, B., Zamarian, L., Beer, R., Sahanic, S., Lindner, A., Kofler, M., Schiefecker, A. J., Mahlknecht, P., Heim, B., et al. (2021) · Quality of Life Research · doi:10.1007/s11136-021-02998-9 · Cited by 40
Jovanoski, N., Chen, X., Becker, U., Zalocusky, K. A., Chawla, D., Tsai, L. W., Borm, M. E. A., Neighbors, M., & Yau, V. (2021) · BMJ Open · doi:10.1136/bmjopen-2021-056284 · Cited by 35
Incidence of Epilepsy and Seizures Over the First 6 Months After a COVID-19 Diagnosis
Taquet, M., Devinsky, O., Cross, J. H., Harrison, P. J., & Sen, A. (2022) · Neurology · doi:10.1212/wnl.0000000000201595 · Cited by 37
Self-citationRoessler, M., Tesch, F., Batram, M., Jacob, J., Loser, F., Weidinger, O., Wende, D., Vivirito, A., Toepfner, N., Seifert, M., et al. (2021) · medRxiv · doi:10.1101/2021.10.21.21265133 · Cited by 34
Liu, N., Tan, J., Liu, L., Wang, Y., Hua, L., & Qian, Q. (2021) · Frontiers in Psychiatry · doi:10.3389/fpsyt.2021.746276 · Cited by 31
Factors associated with psychiatric outcomes and coping in Long COVID
Re’em, Y., Stelson, E., Davis, H., McCorkell, L., Wei, H., Assaf, G., & Akrami, A. (2023) · Nature Mental Health · doi:10.1038/s44220-023-00064-6 · Cited by 33
Damiano, R. F., Rocca, C. C. D. A., Serafim, A. D. P., Loftis, J. M., Talib, L. L., Pan, P. M., Cunha‐Neto, E., Kalil, J. E., de Castro, G. S., Seelaender, M. C. L., et al. (2023) · Frontiers in Immunology · doi:10.3389/fimmu.2023.1174020 · Cited by 36
Beretta, S., Cristillo, V., Camera, G., et al. (2023) · Neurology · doi:10.1212/wnl.0000000000207534 · Cited by 36
Santos, J. V., Padrón‐Monedero, A., Bikbov, B. T., et al. (2024) · BMC Public Health · doi:10.1186/s12889-024-18529-3 · Cited by 36
Long-COVID: Cognitive deficits (brain fog) and brain lesions in non–hospitalized patients
Hugon, J. (2021) · La Presse Médicale · doi:10.1016/j.lpm.2021.104090 · Cited by 34
Perception, Prevalence, and Prediction of Severe Infection and Post-acute Sequelae of COVID-19
Knight, D. R. T., Munipalli, B., Logvinov, I. I., Halkar, M. G., Mitri, G., Dabrh, A. M. A., & Hines, S. L. (2022) · The American Journal of the Medical Sciences · doi:10.1016/j.amjms.2022.01.002 · Cited by 35
Human Brain Organoids as an In Vitro Model System of Viral Infectious Diseases
Su, X., Yue, P., Kong, J., Xu, X., Zhang, Y. L., Cao, W., Fan, Y., Liu, M., Chen, J., Liu, A., et al. (2022) · Frontiers in Immunology · doi:10.3389/fimmu.2021.792316 · Cited by 38
An End-to-End Depression Recognition Method Based on EEGNet
Liu, B., Chang, H., Peng, K., & Wang, X. (2022) · Frontiers in Psychiatry · doi:10.3389/fpsyt.2022.864393 · Cited by 37
del Corral, T., Menor‐Rodríguez, N., Fernández‐Vega, S., Díaz‐Ramos, C., Aguilar‐Zafra, S., & López‐de‐Uralde‐Villanueva, I. (2022) · Journal of Clinical Nursing · doi:10.1111/jocn.16352 · Cited by 35
Post‐COVID‐19 complications: Multisystemic approach
Suvvari, T. K., Kutikuppala, L. V. S., Tsagkaris, C., Corriero, A. C., & Kandi, V. (2021) · Journal of Medical Virology · doi:10.1002/jmv.27222 · Cited by 34
Astrocytes and the Psychiatric Sequelae of COVID-19: What We Learned from the Pandemic
Steardo, L., Steardo, L., & Scuderi, C. (2022) · Neurochemical Research · doi:10.1007/s11064-022-03709-7 · Cited by 34
Long COVID: Complications, Underlying Mechanisms, and Treatment Strategies
Zadeh, F. H. (2023) · Archives of Microbiology & Immunology · doi:10.26502/ami.93650103 · Cited by 35
Kennedy, J. I., Parker, M., Seaborne, M., Mhereeg, M., Walker, A. J., Walker, V. M., Denaxas, S., Kennedy, N., Katikireddi, S. V., & Brophy, S. T. (2023) · BMC Medicine · doi:10.1186/s12916-023-02897-5 · Cited by 19
Gutman, E. G., Salvio, A. L., Fernandes, R. A., Duarte, L. A., Raposo-Vedovi, J. V., Alcaraz, H. F., Teixeira, M., Passos, G. F., Medeiros, K. Q. M. D., Hämmerle, M. B., et al. (2024) · Molecular Psychiatry · doi:10.1038/s41380-024-02554-0 · Cited by 39
Fountoulakis, K., Karakatsoulis, G., Abraham, S., Adorjan, K., Ahmed, H., Alarcón, R. D., Arai, K., Auwal, S. S., Berk, M., Bjedov, S., et al. (2022) · Psychiatry Research · doi:10.1016/j.psychres.2022.114702 · Cited by 28
Blackett, J. W., Sun, Y., Purpura, L. J., Margolis, K. G., Elkind, M. S. V., O’Byrne, S. M., Wainberg, M. L., Abrams, J. A., Wang, H. H., Chang, L., et al. (2022) · Clinical and Translational Gastroenterology · doi:10.14309/ctg.0000000000000524 · Cited by 36
Luca, R. D., Bonanno, M., & Calabrò, R. S. (2022) · Journal of Clinical Medicine · doi:10.3390/jcm11216554 · Cited by 38
Neuropsychiatric disorders following SARS-CoV-2 infection
Harrison, P. J., & Taquet, M. (2023) · Brain · doi:10.1093/brain/awad008 · Cited by 34
Self-citationThe Appearance Design of Agricultural Product Packaging Art Style Under the Intelligent Computer Aid
Zhao, Z., Hai-rong, Z., & Liu, Y. (2021) · Computer-Aided Design and Applications · doi:10.14733/cadaps.2022.s3.164-173 · Cited by 34
Brain Fog: a Narrative Review of the Most Common Mysterious Cognitive Disorder in COVID-19
Mir, M. A. (2023) · Molecular Neurobiology · doi:10.1007/s12035-023-03715-y · Cited by 38
Persistent cognitive slowing in post-COVID patients: longitudinal study over 6 months
Martin, E. M., Srowig, A., Utech, I., Schrenk, S. J., Kattlun, F., Radscheidt, M., Brodoehl, S., Bublak, P., Schwab, M. G., Geis, C., et al. (2023) · Journal of Neurology · doi:10.1007/s00415-023-12069-3 · Cited by 33
Lee, C., Vu, T. T., Fuller, J. A., Freedman, M. E., Bannon, J., Wilkins, J. T., Moskowitz, J. T., Hirschhorn, L. R., Wallia, A., & Evans, C. T. (2023) · Frontiers in Health Services · doi:10.3389/frhs.2023.1272285 · Cited by 35
Defining brain fog across medical conditions
Denno, P., Zhao, S., Husain, M., & Hampshire, A. (2025) · Trends in Neurosciences · doi:10.1016/j.tins.2025.01.003 · Cited by 44
Self-citationEmerging potential mechanisms and predispositions to the neurological manifestations of COVID-19
Jesuthasan, A., Massey, F., Manji, H., Zandi, M. S., & Wiethoff, S. (2021) · Journal of the Neurological Sciences · doi:10.1016/j.jns.2021.117608 · Cited by 34
Gramaglia, C. M., GATTONI, E., Gambaro, E., Bellan, M., Balbo, P. E., Baricich, A., Sainaghi, P. P., Pirisi, M., Binda, V., Feggi, A., et al. (2022) · Frontiers in Psychiatry · doi:10.3389/fpsyt.2022.862651 · Cited by 34
Ho, A. (2023) · doi:10.1093/med/9780197556269.001.0001 · Cited by 35
Color Effect of Landscape Architecture Design under Computer Aided Collaborative Design System
Zhang, M., & Deng, X. (2021) · Computer-Aided Design and Applications · doi:10.14733/cadaps.2022.s3.13-22 · Cited by 33
Computer Aided Design in the Diversified Forms of Artistic Design
Liu, F., Gao, Y., Yu, Y., et al. (2021) · Computer-Aided Design and Applications · doi:10.14733/cadaps.2022.s3.33-44 · Cited by 33
Pathophysiology, diagnosis, and management of neuroinflammation in covid-19
Brown, R. L., Benjamin, L. A., Lunn, M. P., Bharucha, T., Zandi, M. S., Hoskote, C., McNamara, P., & Manji, H. (2023) · BMJ · doi:10.1136/bmj-2022-073923 · Cited by 37
Central nervous system outcomes of COVID-19
Doyle, M. F. (2021) · Translational research · doi:10.1016/j.trsl.2021.09.002 · Cited by 33
Verde, F., Milone, I., Bulgarelli, I., Peverelli, S., Colombrita, C., Maranzano, A., Calcagno, N., Ticozzi, N., Perego, G. B., Parati, G., et al. (2022) · Journal of Neurology · doi:10.1007/s00415-022-11233-5 · Cited by 35
Melamed, E., Rydberg, L., Ambrose, A. F., Bhavaraju-Sanka, R. K., Fine, J. S., Fleming, T. K., Herman, E., Johnson, J. L. P., Kucera, J. R., Longo, M. T., et al. (2023) · PM&R · doi:10.1002/pmrj.12976 · Cited by 31
Taquet, M., Husain, M., Geddes, J., et al. (2021) · medRxiv · doi:10.1101/2021.04.27.21256153 · Cited by 33
Self-citationIncreasing digitalization is associated with anxiety and depression: A Google Ngram analysis
Teepe, G. W., Glase, E. M., & Reips, U. (2023) · PLoS ONE · doi:10.1371/journal.pone.0284091 · Cited by 30
Wang, Y., Su, B., Xie, J., García‐Rizo, C., & Prieto‐Alhambra, D. (2024) · Nature Human Behaviour · doi:10.1038/s41562-024-01853-4 · Cited by 36
Papadopoulou, P., Polissidis, A., Kythreoti, G., Sagnou, M., Stefanatou, A., & Theoharides, T. C. (2024) · International Journal of Molecular Sciences · doi:10.3390/ijms252011040 · Cited by 36
Patnaik, S., Jain, M. K., Ahmed, S., Dash, A. K., Ram Kumar, P., Sahoo, B., Mishra, R., & Behera, M. R. (2021) · Rheumatology International · doi:10.1007/s00296-021-04932-1 · Cited by 31
Murray, E., Kaufman, K. R., & Williams, R. (2021) · BJPsych Open · doi:10.1192/bjo.2021.981 · Cited by 30
Paul, E., & Fancourt, D. E. (2021) · The British Journal of Psychiatry · doi:10.1192/bjp.2021.130 · Cited by 33
Molecular Insights into SARS-CoV2-Induced Alterations of the Gut/Brain Axis
Nataf, S., & Pays, L. (2021) · International Journal of Molecular Sciences · doi:10.3390/ijms221910440 · Cited by 33
Xie, J., Tian, S., Liu, J., Cao, R., Yue, P., Cai, X., Shang, Q., Yang, M. H., Han, L., & Zhang, D. (2022) · Pharmacological Research · doi:10.1016/j.phrs.2022.106189 · Cited by 30
Appelt, P. A., Sisconetto, A. T., Sucupira, K. S. M. B., Neto, E. D. M., Chagas, T. D. J., Bazán, R., Cabral, A. M., Andrade, A. D. O., de Souza, L. A. P. S., & Luvizutto, G. J. (2022) · Clinical EEG and Neuroscience · doi:10.1177/15500594221103834 · Cited by 31
MRI Assessment of Cerebral Blood Flow in Nonhospitalized Adults Who Self‐Isolated Due to COVID ‐19
Kim, W. S. H., Ji, X., Roudaia, E., Chen, J. J., Gilboa, A., Sekuler, A. B., Gao, F., Lin, Z., Jegatheesan, A., Masellis, M., et al. (2022) · Journal of Magnetic Resonance Imaging · doi:10.1002/jmri.28555 · Cited by 33
Vakili, K. G., Fathi, M., Yaghoobpoor, S., Sayehmiri, F., Nazerian, Y., Nazerian, A., Mohamadkhani, A., Khodabakhsh, P., Réus, G. Z., Hajibeygi, R., et al. (2022) · Frontiers in Cellular and Infection Microbiology · doi:10.3389/fcimb.2022.983089 · Cited by 32
Persistent neuropsychiatric symptoms after COVID-19: a systematic review and meta-analysisPreprint
Badenoch, J., Rengasamy, E. R., Watson, C. J., Jansen, K., Chakraborty, S., Sundaram, R. D., Hafeez, D., Burchill, E., Saini, A., Thomas, L., et al. (2021) · medRxiv · doi:10.1101/2021.04.30.21256413 · Cited by 31
SARS-CoV-2 Infection Causes Dopaminergic Neuron SenescencePreprint
Chen, S., Han, Y., Yang, L., Kim, T., Nair, M. S., Harschnitz, O., Wang, P., Zhu, J., Koo, S. Y., Tang, X., et al. (2021) · Research Square · doi:10.21203/rs.3.rs-513461/v1 · Cited by 31
Evaluation of Cultural Creative Product Design Based on Computer-Aided Perceptual Imagery System
Xu, X., & Zheng, J. (2021) · Computer-Aided Design and Applications · doi:10.14733/cadaps.2022.s3.142-152 · Cited by 31
A case report of ChAdOx1 nCoV-19 vaccine–associated encephalitis
Takata, J., Durkin, S. M., Wong, S., et al. (2021) · BMC Neurology · doi:10.1186/s12883-021-02517-w · Cited by 31
HIV, HSV, SARS-CoV-2 and Ebola Share Long-Term Neuropsychiatric Sequelae
Büttiker, P., Stefano, G. B., Weissenberger, S., Ptáček, R., Anders, M., Raboch, J., & Kream, R. M. (2022) · Neuropsychiatric Disease and Treatment · doi:10.2147/ndt.s382308 · Cited by 36
Biobehavioral Aspects of the COVID-19 Pandemic: A Review
Hall, P. A., Sheeran, P., Fong, G. T., Cheah, C. S. L., Oremus, M., Liu-Ambrose, T. Y. L., Sakib, M. N., Butt, Z. A., Ayaz, H., Jandu, N., et al. (2021) · Psychosomatic Medicine · doi:10.1097/psy.0000000000000932 · Cited by 31
Botha, F., Butterworth, P., & Wilkins, R. (2022) · International Journal of Environmental Research and Public Health · doi:10.3390/ijerph19010558 · Cited by 32
Antioxidant Genetic Profile Modifies Probability of Developing Neurological Sequelae in Long-COVID
Ercegovac, M., Ašanin, M., Savic-Radojevic, A. R., Ranin, J. T., Matic, M. G., Djukic, T. I., Coric, V. M., Jerotić, D., Todorović, N., Milošević, I., et al. (2022) · Antioxidants · doi:10.3390/antiox11050954 · Cited by 29
Neuropsychiatric phenotype of post COVID-19 syndrome in non-hospitalized patients
Lier, J., Stoll, K., Obrig, H., Baum, P., Deterding, L., Bernsdorff, N., Hermsdorf, F., Kunis, I., Bräsecke, A., Herzig, S., et al. (2022) · Frontiers in Neurology · doi:10.3389/fneur.2022.988359 · Cited by 29
Long COVID at Different Altitudes: A Countrywide Epidemiological Analysis
Izquierdo‐Condoy, J. S., Fernández-Naranjo, R., Vásconez-González, J., Cordovez, S., Tello-De-la-Torre, A., Paz, C., Delgado-Moreira, K., Carrington, S. J., Viscor, G., & Ortiz‐Prado, E. (2022) · International Journal of Environmental Research and Public Health · doi:10.3390/ijerph192214673 · Cited by 33
Jing, Y., Wang, J., Zhang, H., Yang, K., Li, J., Zhao, T., Liu, J., Wu, J., & Chen, Y. (2022) · Frontiers in Immunology · doi:10.3389/fimmu.2022.841739 · Cited by 22
Szekanecz, Z., & Valyi-Nagy, I. T. (2021) · Orvosi Hetilap · doi:10.1556/650.2021.32282 · Cited by 31
Damiano, R. F., Neto, D. B., Oliveira, J. V. R., Santos, J. M., Alves, J. V. R., Guedes, B. F., Nitríni, R., de Araújo, A. L., de Oliveira, M. H. D. S. B., Brunoni, A. R., et al. (2022) · European Archives of Psychiatry and Clinical Neuroscience · doi:10.1007/s00406-022-01427-3 · Cited by 35
Cecon, E., Fernandois, D., Renault, N., Coêlho, C. F. F., Wenzel, J., Bedart, C., Izabelle, C., Gallet, S., Poder, S. L., Klonjkowski, B., et al. (2022) · Cellular and Molecular Life Sciences · doi:10.1007/s00018-022-04390-3 · Cited by 34
International electronic health record-derived post-acute sequelae profiles of COVID-19 patients
Zhang, H. G., Dagliati, A., Abad, Z. S. H., Xiong, X., Bonzel, C.-L., Xia, Z., Tan, B. W. Q., Avillach, P., Brat, G. A., Hong, C., et al. (2022) · npj Digital Medicine · doi:10.1038/s41746-022-00623-8 · Cited by 29
In SARS-CoV-2, astrocytes are in it for the long haul
Huang, S., & Fishell, G. (2022) · Proceedings of the National Academy of Sciences · doi:10.1073/pnas.2209130119 · Cited by 27
ElTohamy, A., Hyun, S., Macaranas, A. R., Chen, J. A., Stevens, C., & Liu, C. H. (2022) · Journal of Affective Disorders · doi:10.1016/j.jad.2022.07.022 · Cited by 33
COVID‐19: Implications for Nursing and Health Care in the United States
Reynolds, N. R., Baker, D. C., D’Aoust, R., Docal, M., Goldstein, N. S., Grubb, L. M., Hladek, M. D., Koirala, B., Kverno, K. S., Ling, C. G., et al. (2022) · Journal of Nursing Scholarship · doi:10.1111/jnu.12853 · Cited by 33
Samper-Pardo, M., León-Herrera, S., Oliván‐Blázquez, B., Gascón, S., & Sánchez‐Recio, R. (2023) · PLoS ONE · doi:10.1371/journal.pone.0278728 · Cited by 33
Metadata
- Authors
- Taquet, M., Geddes, J. R., Husain, M., Luciano, S., & Harrison, P. J.
- Affiliations
- Oxford Health NHS Foundation Trust (GB)
- TriNetX (United States) (US)
- Corresponding author
- Harrison, Paul J
- Venue
- The Lancet Psychiatry
- Publisher
- Elsevier BV
- Published
- 2021-05
- Volume
- 8
- Issue
- 5
- Pages
- 416-427
- ISSN
- 2215-0366 (ISSN-L)
- PMC
- PMC8023694
- OpenAlex
- W3148333766
- Semantic Scholar
- 81d0f9614f3454de7682cc062b48e04d82329866
- Cited by
- 2,189
- References
- 35
- Citations by year
- 2026: 137 · 2025: 186 · 2024: 346 · 2023: 467 · 2022: 640 · 2021: 408
- FWCI
- 222.72
- Type
- journal article
- Language
- en
- Open access
- hybrid
- doi.org
- Licence
- Locations
- The Lancet Psychiatry (publishedVersion, cc-by)
- medRxiv (acceptedVersion, cc-by-nc-nd)
- PubMed Central (publishedVersion, cc-by)
- PubMed (publishedVersion)
- Funders
- NIHR
- Topics
- Health Sciences › Medicine › Clinical Neurology › Long-Term Effects of COVID-19
- Health Sciences › Medicine › Infectious Diseases › COVID-19 Clinical Research Studies
- Social Sciences › Psychology › Clinical Psychology › COVID-19 and Mental Health
- Keywords
- COVID-19 pandemic, neurological sequelae, psychiatric sequelae, long COVID, incidence, respiratory infections, stroke, dementia, psychosis, anxiety disorders, substance use disorders, insomnia, Guillain-Barré syndrome, parkinsonism, encephalitis, delirium, COVID-19 severity, hospitalization, intensive care unit admission
- MeSH terms
- COVID-19, SARS-CoV-2, Mental Disorders, Female, Humans, Influenza, Human, Male, Middle Aged, Nervous System Diseases, Outcome and Process Assessment, Health Care, Research Design, Respiratory Tract Infections, Risk Factors, Severity of Illness Index, Global Health, Cohort Studies, Incidence, Proportional Hazards Models, Risk Assessment, Electronic Health Records
About these checks
Registry, retraction, Cites and statistics results are computed, not judged, with one exception: a printed reference that no index lists is read once by a model before it counts as a citation error. Claims are extracted by a model and kept only when their quote appears verbatim in the text; each cited source is then checked, with a model’s help, for whether it says what the claim relies on. Those verdicts can be wrong — read the claim’s quote and the cited source before relying on one.
A language model drew the claims from the paper on 2026-10-07, under version 3 of the claim definition (model deepseek-v4.1-flash, prompt extract-v3).
A second model labelled each claim on 2026-10-07 (model jev-1.13-20260917, definition revision gold-guideline-v0.2).
Statistics and arithmetic are recomputed, not judged.
Confidence bands are shown only for fields calibrated on our annotated test set. None is calibrated yet, so no band is shown.
What counts as a claim ›How we measure confidence ›How we check this ›
Are you an author, or do you see a problem with this page? Request a review
