Student or educator? Sign up with your school email and get 6 months of Pro free.
Cited by 72

The DOI matches its Crossref record; 66 of the 66 references it cites were found in a registry or an index.

Permanent neuroglial remodeling of the retina following infiltration of CSF1R inhibition-resistant peripheral monocytes

Paschalis, Eleftherios I., Lei, Fengyang, Zhou, Chengxin, Kapoulea, Vassiliki, Dana, Reza, Chodosh, James, Vavvas, Demetrios G., Dohlman, Claes H.·2018·Proceedings of the National Academy of Sciences

Published version of a preprint

Abstract

Significance: This work contributes to the understanding of the enigmatic progressive retinal damage following acute ocular surface injury. Clinical findings in patients suggest that such injuries can adversely affect the retina. This study demonstrates that corneal injury leads to rapid infiltration of blood-derived monocytes into the retina and to subsequent remodeling of the neuroglial system. In contrast to previously held belief, this study shows that the blood-derived monocytes engraft permanently into the retina and differentiate into microglia-like cells. Although these cells are morphologically indistinguishable from native microglia, they retain a distinct signature and insensitivity to CSF1R inhibition and exhibit a reactive phenotype which persists long after the noxious stimuli is removed, ultimately contributing to progressive neuroretinal degeneration.

Overview

The claims and statistics of this paper haven’t been checked yet.

Run the check — free, no account needed. It reads the open-access text and checks the sources it cites.

A few free checks a day · papers already verified open instantly · results are public

Integrity signals

Registry

Crossref · 10.1073/pnas.1807123115

Cites

66 of 66 references verified0 citation errors · 0 not checkable

Statistics

Figures

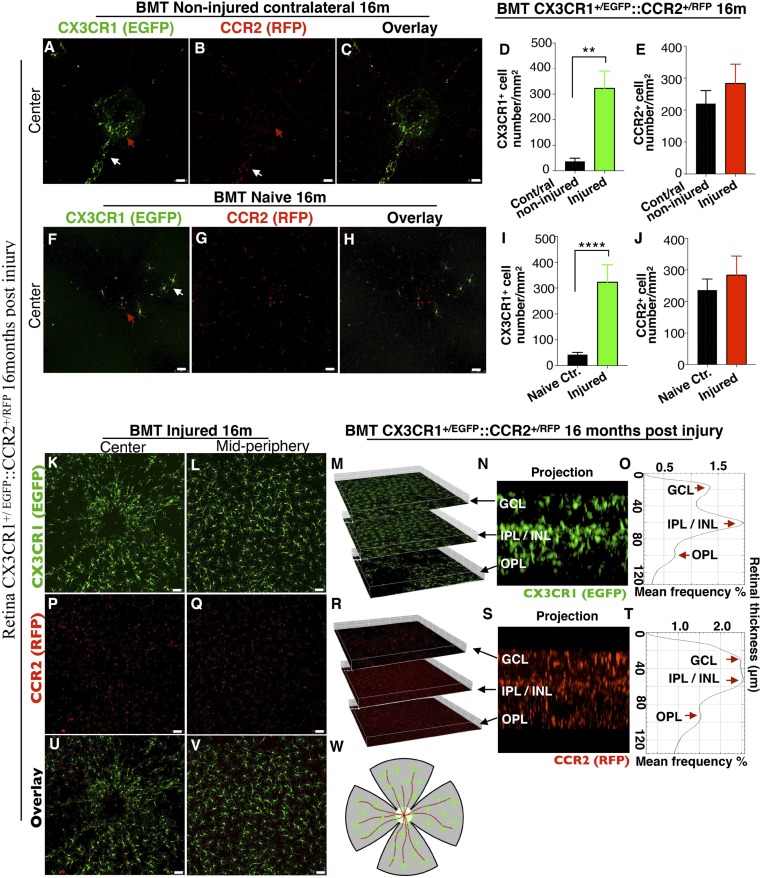
Fig. 1. Ocular injury causes permanent engraftment in the retina of peripheral CX3CR1+ cells which adopt microglia morphology. (A–C and F–H) Confocal microscopy of busulfan-myelodepleted and bone-marrow–transferred mice with CX3CR1+/EGFP::CCR2+/RFP cells 16 mo after corneal alkali burn injury. Maximum projection of confocal images shows that CX3CR1+ cells cannot enter into the retina of the contralateral noninjured eye 16 mo after injury (A), nor can they populate the retina of naive eyes under physiological conditions (F). Few cells are present around the optic nerve head (red arrow) and along the major retinal vessels (white arrow). Maximum projection of confocal images shows CCR2+ cells are scattered across the retina of the contralateral noninjured (B) and of the naive (G) eye, located mainly in the GCL. C and H show overlay images of CX3CR1 and CCR2 channels. (D, E, I, and J) Quantification of the number of peripheral CX3CR1+ and CCR2+ cells 16 mo after ocular injury shows a marked increase in CX3CR1+ cells (P < 0.003) but normal numbers of CCR2+ cells (P > 0.415) compared with contralateral noninjured and naive eyes. Data in D and E are presented as mean ± SD, paired t test. Data in I and J are presented as mean ± SD, independent t test. **P < 0.01; ****P < 0.0001. (K and L) Ocular injury causes infiltration and permanent engraftment of peripheral CX3CR1+ cells in the retina. (M–O) Sixteen months after the injury, infiltrated CX3CR1+ cells migrate into the three distinct microglia strata (GCL, IPL/INL, OPL) and adopt dendritiform microglia morphology. (M) Isometric reconstruction of confocal stacks separated by retinal layers (GCL, IPL/INL, and OPL). (N) A cross-section of the retina shows the presence of CX3CR1+ cells in the GCL, IPL/INL, and OPL. (O) A histogram of CX3CR1+/EGFP expression within the retinal tissue shows intensity peaks of EGFP signal in the GCL, IPL/INL, and OPL. (P and Q) Patrolling CCR2+ cells are present in the retina but do not differentiate into CX3CR1+ cells. (R–T) Even though the number of peripheral CCR2+ cells is normal, peripheral CCR2+ cells are present in all three distinct microglia strata (GCL, IPL/INL, and OPL) 16 mo after the injury. In O and T the thickness of the retinal tissue and the relative position of each microglia stratum was derived automatically by the confocal system (Leica SP8) and was calculated by multiplying the number of serial confocal scans by the step of each scan in micrometers. (U and V) Overlay images of CX3CR1 and CCR2 channels 16 mo after ocular injury. (W) A representative schematic of a flat-mount retina as used for confocal imaging. The center white circle represents the optic nerve head, red lines represent the retinal vessels, and green dots represent the peripheral monocytes. (Scale bars: 50 μm in A–C, F–H, K, L, P, Q, U, and V.) n ≥ 5 mice per group.
Fig. 1. Ocular injury causes permanent engraftment in the retina of peripheral CX3CR1+ cells which adopt microglia morphology. (A–C and F–H) Confocal microscopy of busulfan-myelodepleted and bone-marrow–transferred mice with CX3CR1+/EGFP::CCR2+/RFP cells 16 mo after corneal alkali burn injury. Maximum projection of confocal images shows that CX3CR1+ cells cannot enter into the retina of the contralateral noninjured eye 16 mo after injury (A), nor can they populate the retina of naive eyes under physiological conditions (F). Few cells are present around the optic nerve head (red arrow) and along the major retinal vessels (white arrow). Maximum projection of confocal images shows CCR2+ cells are scattered across the retina of the contralateral noninjured (B) and of the naive (G) eye, located mainly in the GCL. C and H show overlay images of CX3CR1 and CCR2 channels. (D, E, I, and J) Quantification of the number of peripheral CX3CR1+ and CCR2+ cells 16 mo after ocular injury shows a marked increase in CX3CR1+ cells (P < 0.003) but normal numbers of CCR2+ cells (P > 0.415) compared with contralateral noninjured and naive eyes. Data in D and E are presented as mean ± SD, paired t test. Data in I and J are presented as mean ± SD, independent t test. **P < 0.01; ****P < 0.0001. (K and L) Ocular injury causes infiltration and permanent engraftment of peripheral CX3CR1+ cells in the retina. (M–O) Sixteen months after the injury, infiltrated CX3CR1+ cells migrate into the three distinct microglia strata (GCL, IPL/INL, OPL) and adopt dendritiform microglia morphology. (M) Isometric reconstruction of confocal stacks separated by retinal layers (GCL, IPL/INL, and OPL). (N) A cross-section of the retina shows the presence of CX3CR1+ cells in the GCL, IPL/INL, and OPL. (O) A histogram of CX3CR1+/EGFP expression within the retinal tissue shows intensity peaks of EGFP signal in the GCL, IPL/INL, and OPL. (P and Q) Patrolling CCR2+ cells are present in the retina but do not differentiate into CX3CR1+ cells. (R–T) Even though the number of peripheral CCR2+ cells is normal, peripheral CCR2+ cells are present in all three distinct microglia strata (GCL, IPL/INL, and OPL) 16 mo after the injury. In O and T the thickness of the retinal tissue and the relative position of each microglia stratum was derived automatically by the confocal system (Leica SP8) and was calculated by multiplying the number of serial confocal scans by the step of each scan in micrometers. (U and V) Overlay images of CX3CR1 and CCR2 channels 16 mo after ocular injury. (W) A representative schematic of a flat-mount retina as used for confocal imaging. The center white circle represents the optic nerve head, red lines represent the retinal vessels, and green dots represent the peripheral monocytes. (Scale bars: 50 μm in A–C, F–H, K, L, P, Q, U, and V.) n ≥ 5 mice per group.CC BY-NC-ND · PubMed Central
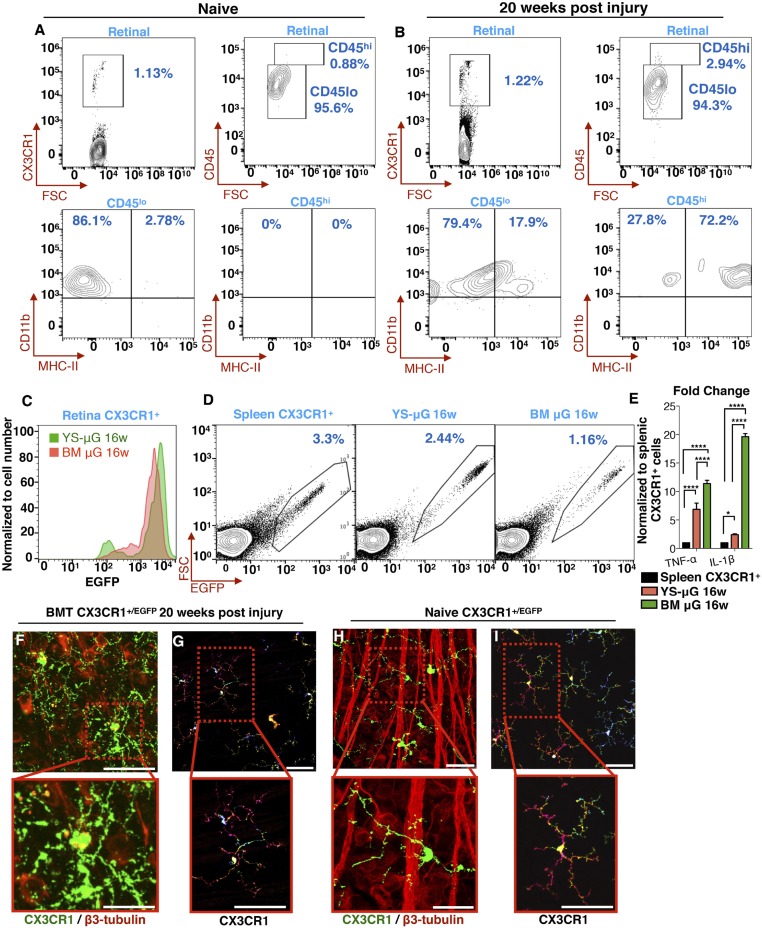
Fig. 2. Engrafted peripheral CX3CR1+ cells remain reactive despite their morphometric quiescence. (A–D) Flow cytometric analysis of retinal cells from CX3CR1+/EGFP mice. (A) In naive mice, CX3CR1+ cells are predominantly CD45lo (96%), and only a small percentage is CD45hi (4%). CX3CR1+ CD45lo cells do not express MHC-II; however, 2.8% of CX3CR1+ CD45hi cells have baseline MHC-II expression. (B) Twenty weeks after ocular injury, 94% percent of the CX3CR1+ cells are CD45lo, 20% of which express MHC-II. Likewise, 3% of the CX3CR1+ cells are CD45hi, 72% of which express MHC-II. (C) Flow cytometry for the differentiation of yolk-sac–derived retinal microglia (YS-μGlia 16w) from peripherally engrafted bone-marrow CX3CR1+ monocytes (MB μG 16w) 16 wk after ocular injury using RFP-conjugated CX3CR1 antibody against bone-marrow–transferred CX3CR1+/EGFP retinal cells. Both cell populations are strongly expressed. (D) Flow cytometry and cell sorting of splenic CX3CR1+ cells (control), retinal yolk-sac–derived microglia, and retinal peripherally engrafted monocytes 16 wk after ocular injury for subsequent analysis of IL-1β and TNF-α expression with qPCR. (E) Compared with splenic CX3CR1+ cells, both yolk-sac–derived and peripheral microglia had elevated TNF-α and IL-1β gene expression. However, peripherally engrafted monocytes had significantly higher expression than yolk-sac–derived microglia 16 wk after injury. *P < 0.05; ****P < 0.0001; Tukey’s method for multiple comparisons. (F and G) Twenty weeks after the injury, peripheral CX3CR1+ monocytes appear to frequently interact with and engulf β3 tubulin+ neuroretinal tissue (F), despite their otherwise ramified and quiescent morphology (G). (H and I) In contrast, in naive eyes, although ramified CX3CR1+ monocytes come into contact with β3 tubulin+ neuronal tissue, they do not internalize it. (Scale bars: F–I, Upper, 50 μm; F–I, Lower, 20 μm.) All experiments were performed in triplicate.
Fig. 2. Engrafted peripheral CX3CR1+ cells remain reactive despite their morphometric quiescence. (A–D) Flow cytometric analysis of retinal cells from CX3CR1+/EGFP mice. (A) In naive mice, CX3CR1+ cells are predominantly CD45lo (96%), and only a small percentage is CD45hi (4%). CX3CR1+ CD45lo cells do not express MHC-II; however, 2.8% of CX3CR1+ CD45hi cells have baseline MHC-II expression. (B) Twenty weeks after ocular injury, 94% percent of the CX3CR1+ cells are CD45lo, 20% of which express MHC-II. Likewise, 3% of the CX3CR1+ cells are CD45hi, 72% of which express MHC-II. (C) Flow cytometry for the differentiation of yolk-sac–derived retinal microglia (YS-μGlia 16w) from peripherally engrafted bone-marrow CX3CR1+ monocytes (MB μG 16w) 16 wk after ocular injury using RFP-conjugated CX3CR1 antibody against bone-marrow–transferred CX3CR1+/EGFP retinal cells. Both cell populations are strongly expressed. (D) Flow cytometry and cell sorting of splenic CX3CR1+ cells (control), retinal yolk-sac–derived microglia, and retinal peripherally engrafted monocytes 16 wk after ocular injury for subsequent analysis of IL-1β and TNF-α expression with qPCR. (E) Compared with splenic CX3CR1+ cells, both yolk-sac–derived and peripheral microglia had elevated TNF-α and IL-1β gene expression. However, peripherally engrafted monocytes had significantly higher expression than yolk-sac–derived microglia 16 wk after injury. *P < 0.05; ****P < 0.0001; Tukey’s method for multiple comparisons. (F and G) Twenty weeks after the injury, peripheral CX3CR1+ monocytes appear to frequently interact with and engulf β3 tubulin+ neuroretinal tissue (F), despite their otherwise ramified and quiescent morphology (G). (H and I) In contrast, in naive eyes, although ramified CX3CR1+ monocytes come into contact with β3 tubulin+ neuronal tissue, they do not internalize it. (Scale bars: F–I, Upper, 50 μm; F–I, Lower, 20 μm.) All experiments were performed in triplicate.CC BY-NC-ND · PubMed Central
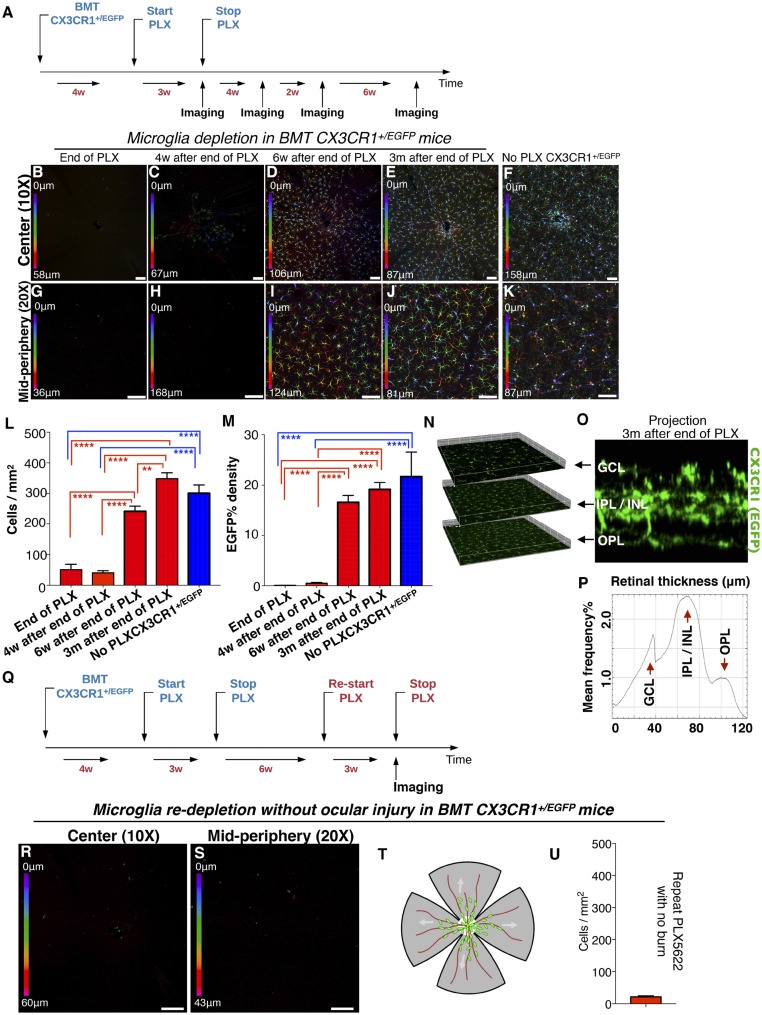
Fig. 3. Microglia repopulation after PLX5622 treatment occurs primarily by peripheral CX3CR1+ cells. (A) Schematic of the experiment: Busulfan-myelodepleted C57BL/6 mice received adoptive transfer of CX3CR1+/EGFP bone-marrow cells. Four weeks later they received PLX5622 treatment for 3 wk followed by confocal microscopy 3 wk after the cessation of PLX5622 treatment. (B–F) Central color-depth–coded (0 represents innermost retina) confocal images of flat-mount retinas 0, 4, 6 wk, and 3 mo after cessation of PLX5622 treatment (B–E) and of naive CX3CR1+/EGFP mice (F). (G–K) Midperipheral color-depth–coded confocal images of flat-mount retinas 0, 4, 6 wk, and 3 mo after cessation of PLX5622 treatment (G–J) and of naive CX3CR1+/EGFP mice (K). (Scale bars: 100 μm.) (L) Quantification of CX3CR1+ cell number at the indicated times post PLX5622 treatment. (M) Quantification of EGFP intensity at the indicated times post PLX5622 treatment. **P < 0.01, ****P < 0.0001; Tukey’s multiple-comparisons method. PLX5622 treatment for 3 wk does not cause acute peripheral CX3CR1+ cell infiltration into the retina (B, F, G, L, and M). However, 6 wk after cessation of PLX5622 treatment peripheral CX3CR1+ cells appeared to occupy the majority of the retina area (D, I, L, and M), and at 3 mo, the retina is completely repopulated by peripheral CX3CR1+ cells (E, J, L, and M). The number of repopulated peripheral CX3CR1+ cells at 3 mo after the end of PLX5622 treatment approximates that of naive CX3CR1+/EGFP mice with no PLX5622 treatment (F, K, L, and M). (N) Repopulating peripheral CX3CR1+ cells migrated into all three distinct microglia strata (GCL, IPL/INL, and OPL) 3 mo after the injury. (O) A cross-section of the retina shows the presence of CX3CR1+ cells in the GCL, IPL/INL, and OPL. (P) A histogram of CX3CR1+/EGFP expression within the retinal tissue shows intensity peaks of EGFP signal in the GCL, IPL/INL, and OPL. (Q) Schematic showing reapplication of PLX5622 in repopulated peripheral microglia. (R and S) Peripheral monocytes that repopulate the retina remain sensitive to CSF1R inhibition and can be redepleted by reapplication of PLX5622 treatment. (T) A representative schematic of a flat-mount retina as used for confocal imaging. The center white circle represents the optic nerve head, red lines represent the retinal vessels, and green dots represent the peripheral monocytes. (U) Quantification of peripheral CX3CR1+ cells after reapplication of PLX5622 shows complete depletion of repopulated CX3CR1+ cells. n = 5 mice per group.
Fig. 3. Microglia repopulation after PLX5622 treatment occurs primarily by peripheral CX3CR1+ cells. (A) Schematic of the experiment: Busulfan-myelodepleted C57BL/6 mice received adoptive transfer of CX3CR1+/EGFP bone-marrow cells. Four weeks later they received PLX5622 treatment for 3 wk followed by confocal microscopy 3 wk after the cessation of PLX5622 treatment. (B–F) Central color-depth–coded (0 represents innermost retina) confocal images of flat-mount retinas 0, 4, 6 wk, and 3 mo after cessation of PLX5622 treatment (B–E) and of naive CX3CR1+/EGFP mice (F). (G–K) Midperipheral color-depth–coded confocal images of flat-mount retinas 0, 4, 6 wk, and 3 mo after cessation of PLX5622 treatment (G–J) and of naive CX3CR1+/EGFP mice (K). (Scale bars: 100 μm.) (L) Quantification of CX3CR1+ cell number at the indicated times post PLX5622 treatment. (M) Quantification of EGFP intensity at the indicated times post PLX5622 treatment. **P < 0.01, ****P < 0.0001; Tukey’s multiple-comparisons method. PLX5622 treatment for 3 wk does not cause acute peripheral CX3CR1+ cell infiltration into the retina (B, F, G, L, and M). However, 6 wk after cessation of PLX5622 treatment peripheral CX3CR1+ cells appeared to occupy the majority of the retina area (D, I, L, and M), and at 3 mo, the retina is completely repopulated by peripheral CX3CR1+ cells (E, J, L, and M). The number of repopulated peripheral CX3CR1+ cells at 3 mo after the end of PLX5622 treatment approximates that of naive CX3CR1+/EGFP mice with no PLX5622 treatment (F, K, L, and M). (N) Repopulating peripheral CX3CR1+ cells migrated into all three distinct microglia strata (GCL, IPL/INL, and OPL) 3 mo after the injury. (O) A cross-section of the retina shows the presence of CX3CR1+ cells in the GCL, IPL/INL, and OPL. (P) A histogram of CX3CR1+/EGFP expression within the retinal tissue shows intensity peaks of EGFP signal in the GCL, IPL/INL, and OPL. (Q) Schematic showing reapplication of PLX5622 in repopulated peripheral microglia. (R and S) Peripheral monocytes that repopulate the retina remain sensitive to CSF1R inhibition and can be redepleted by reapplication of PLX5622 treatment. (T) A representative schematic of a flat-mount retina as used for confocal imaging. The center white circle represents the optic nerve head, red lines represent the retinal vessels, and green dots represent the peripheral monocytes. (U) Quantification of peripheral CX3CR1+ cells after reapplication of PLX5622 shows complete depletion of repopulated CX3CR1+ cells. n = 5 mice per group.CC BY-NC-ND · PubMed Central
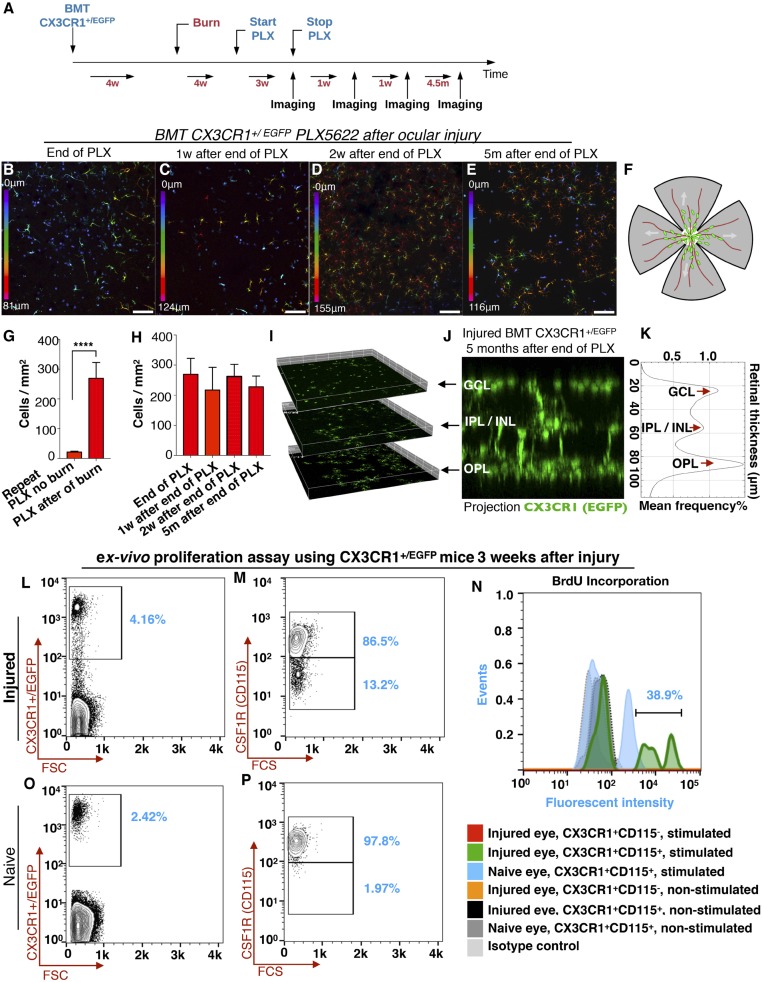
Fig. 4. Ocular injury leads to population of the retina by peripheral CX3CR1+ cells that are resistant to the CSF1R inhibitor. (A) Schematic of the experiment: Busulfan-myelodepleted, CX3CR1+/EGFP bone-marrow chimeras received ocular injury and 4 wk later received PLX5622 treatment for 3 wk. (B and G) Immediately after cessation of PLX5622 treatment, peripherally derived, retina-repopulating CX3CR1+ cells remained present in the retina (B) and were resistant to CSF1R inhibition, unlike peripherally derived retina-repopulating CX3CR1+ cells in the absence of ocular injury (G). ****P < 0.0001; independent t test. (C–E and H) One week (C), 2 wk (D), and 5 mo (E) after cessation of PLX5622 treatment peripherally populating CX3CR1+ cells remained present in the retina (H) with unchanged cell number. Depth color-coding in B–E: 0 represents innermost retina. (Scale bars: 100 μm in B–E.) (F) A representative schematic of a flat-mount retina as used for confocal imaging. The center white circle represents the optic nerve head, red lines represent the retinal vessels, and green dots represent the peripheral monocytes. (I–K) Inhibition-resistant peripheral CX3CR1+ cells that were localized primarily in the GCL/IPL in the early stages after repopulation (see the depth color-code in B–E) migrated into all three distinct microglia strata 5 mo after the injury with unusually increased cell density in the OPL. (L–P) Ex vivo functional analysis using flow cytometry of CSF1R+ and CSF1R− CX3CR1+ retina cells isolated from CX3CR1+/EGFP mice 3 wk after ocular injury or from naive mice. (L and M) Three weeks after the ocular injury, 86.5% of the CX3CR1+ retinal cells were CSF1R+ (CD115+), and 13.2% were CSF1R− (CD115−). (O and P) In naive eyes, 97.8% of retinal CX3CR1+ cells were CSF1R+ (CD115+), and 1.97% were CSF1Rlo (CD115lo). (N) CSF1R− and CSF1R+ cells were cultured for 5 d with or without recombinant CSF1 and IL-4 stimulation. BrdU was used in the culture to assess cell proliferation. CSF1R− cells from both naive and injured eyes were not influenced or rescued by CSF1 and IL-4 stimulation, and cells did not survive the 5-d culture. In contrast, CSF1R+ cells were rescued with CSF1 and IL-4 stimulation and showed increased proliferation and BrdU retention. n = 3 mice per group.
Fig. 4. Ocular injury leads to population of the retina by peripheral CX3CR1+ cells that are resistant to the CSF1R inhibitor. (A) Schematic of the experiment: Busulfan-myelodepleted, CX3CR1+/EGFP bone-marrow chimeras received ocular injury and 4 wk later received PLX5622 treatment for 3 wk. (B and G) Immediately after cessation of PLX5622 treatment, peripherally derived, retina-repopulating CX3CR1+ cells remained present in the retina (B) and were resistant to CSF1R inhibition, unlike peripherally derived retina-repopulating CX3CR1+ cells in the absence of ocular injury (G). ****P < 0.0001; independent t test. (C–E and H) One week (C), 2 wk (D), and 5 mo (E) after cessation of PLX5622 treatment peripherally populating CX3CR1+ cells remained present in the retina (H) with unchanged cell number. Depth color-coding in B–E: 0 represents innermost retina. (Scale bars: 100 μm in B–E.) (F) A representative schematic of a flat-mount retina as used for confocal imaging. The center white circle represents the optic nerve head, red lines represent the retinal vessels, and green dots represent the peripheral monocytes. (I–K) Inhibition-resistant peripheral CX3CR1+ cells that were localized primarily in the GCL/IPL in the early stages after repopulation (see the depth color-code in B–E) migrated into all three distinct microglia strata 5 mo after the injury with unusually increased cell density in the OPL. (L–P) Ex vivo functional analysis using flow cytometry of CSF1R+ and CSF1R− CX3CR1+ retina cells isolated from CX3CR1+/EGFP mice 3 wk after ocular injury or from naive mice. (L and M) Three weeks after the ocular injury, 86.5% of the CX3CR1+ retinal cells were CSF1R+ (CD115+), and 13.2% were CSF1R− (CD115−). (O and P) In naive eyes, 97.8% of retinal CX3CR1+ cells were CSF1R+ (CD115+), and 1.97% were CSF1Rlo (CD115lo). (N) CSF1R− and CSF1R+ cells were cultured for 5 d with or without recombinant CSF1 and IL-4 stimulation. BrdU was used in the culture to assess cell proliferation. CSF1R− cells from both naive and injured eyes were not influenced or rescued by CSF1 and IL-4 stimulation, and cells did not survive the 5-d culture. In contrast, CSF1R+ cells were rescued with CSF1 and IL-4 stimulation and showed increased proliferation and BrdU retention. n = 3 mice per group.CC BY-NC-ND · PubMed Central

Verification

Claims the paper makes

The claims and statistics of this paper haven’t been checked yet.

Run the check — free, no account needed. It reads the open-access text and checks the sources it cites.

A few free checks a day · papers already verified open instantly · results are public

Claims other papers make about this one

Each is checked against this paper’s own text: does it say what the citing paper says it does?

Self-check

Percentages, sums and reported differences re-computed from the paper’s own numbers.

The self-check needs the paper’s full text.

Citations

Cites

1 retracted

Show all 66 references

Cited by

Metadata

Authors
Paschalis, E. I., Lei, F., Zhou, C., Kapoulea, V., Dana, R., Chodosh, J., Vavvas, D. G., & Dohlman, C. H.
Affiliations
Department of Ophthalmology, Massachusetts Eye and Ear Infirmary, Harvard Medical School, Boston, MA 02114;
Venue
Proceedings of the National Academy of Sciences
Published
2018-11-15
Volume
115
Issue
48
ISSN
  • 0027-8424
  • 1091-6490
Cited by
72
References
66
Language
en
Funders
  • Massachusetts Eye and Ear (Boston Keratoprosthesis)
  • Massachusetts Lions Eye Research Fund (MEEI fund)
  • HHS | NIH | National Eye Institute (P30EY003790)

About these checks

Registry, retraction, Cites and statistics results are computed, not judged, with one exception: a printed reference that no index lists is read once by a model before it counts as a citation error. Claims are extracted by a model and kept only when their quote appears verbatim in the text; each cited source is then checked, with a model’s help, for whether it says what the claim relies on. Those verdicts can be wrong — read the claim’s quote and the cited source before relying on one.

Statistics and arithmetic are recomputed, not judged.

Confidence bands are shown only for fields calibrated on our annotated test set. None is calibrated yet, so no band is shown.

What counts as a claim ›How we measure confidence ›How we check this ›

Are you an author, or do you see a problem with this page? Request a review

Data sources

Bibliographic data: Semantic Scholar, OpenAlex, Crossref.

Contains information from the Semantic Scholar Academic Graph Datasets, made available under the ODC Attribution License (ODC-BY 1.0).

Semantic Scholar’s data is described in: Kinney, R., et al. (2023). The Semantic Scholar Open Data Platform. arXiv:2301.10140.