

The DOI matches its Crossref record; 101 of the 101 references it cites were found in a registry or an index.
Thirty Years of Evidence on the Efficacy of Drug Treatments for Chronic Heart Failure With Reduced Ejection Fraction: A Network Meta-Analysis
Open accessAbstract
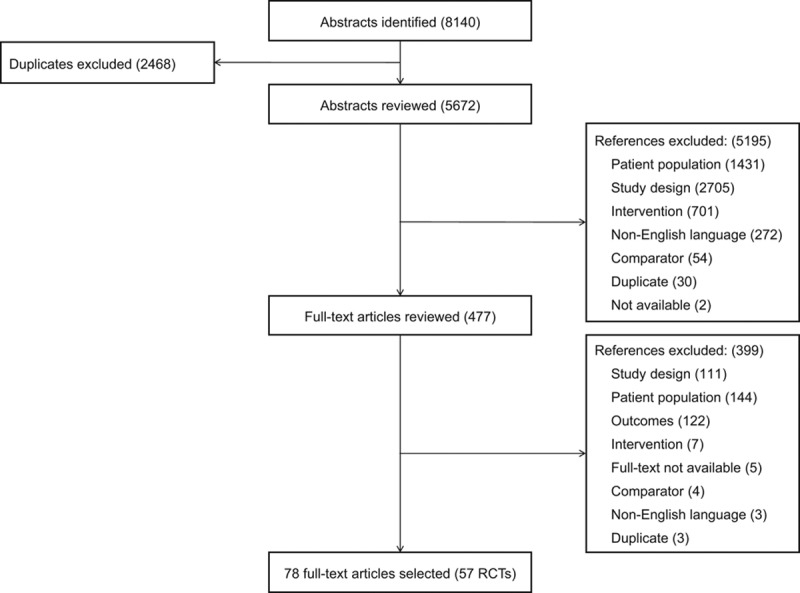
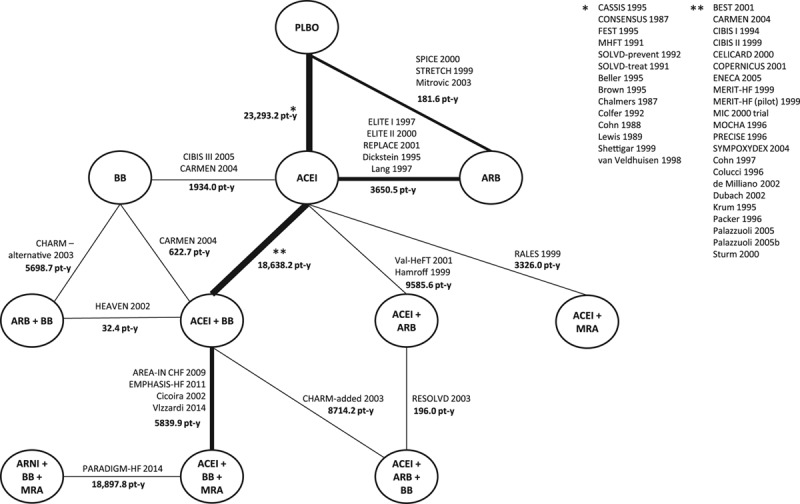
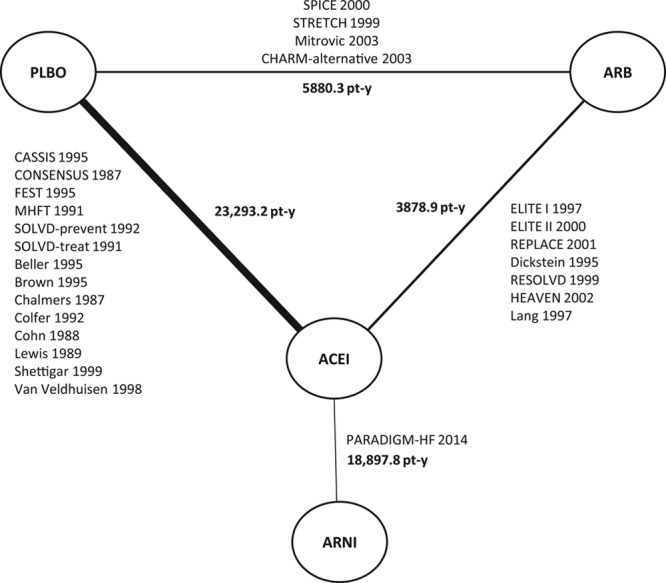
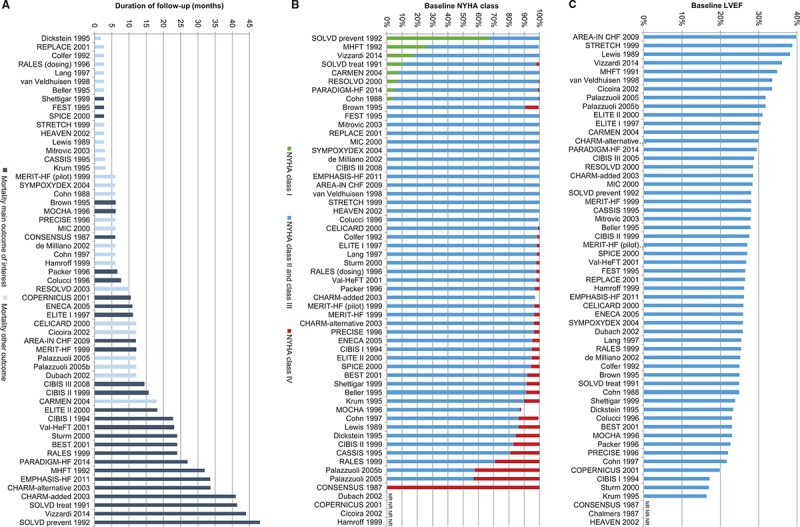
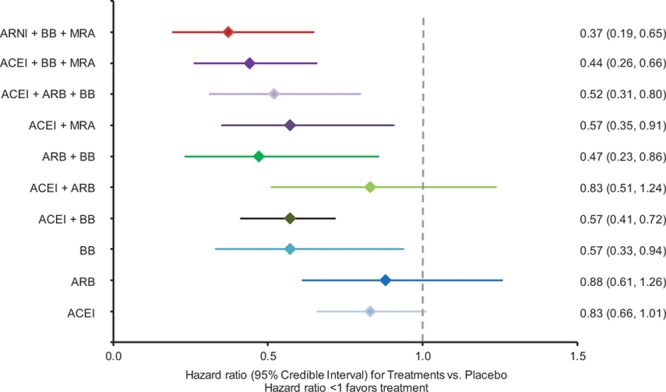
BACKGROUND: Treatments that reduce mortality and morbidity in patients with heart failure with reduced ejection fraction, including angiotensin-converting enzyme inhibitors (ACEI), angiotensin receptor blockers (ARB), β-blockers (BB), mineralocorticoid receptor antagonists (MRA), and angiotensin receptor-neprilysin inhibitors (ARNI), have not been studied in a head-to-head fashion. This network meta-analysis aimed to compare the efficacy of these drugs and their combinations regarding all-cause mortality in patients with heart failure with reduced ejection fraction. METHODS AND RESULTS: A systematic literature review identified 57 randomized controlled trials published between 1987 and 2015, which were compared in terms of study and patient characteristics, baseline risk, outcome definitions, and the observed treatment effects. Despite differences identified in terms of study duration, New York Heart Association class, ejection fraction, and use of background digoxin, a network meta-analysis was considered feasible and all trials were analyzed simultaneously. The random-effects network meta-analysis suggested that the combination of ACEI+BB+MRA was associated with a 56% reduction in mortality versus placebo (hazard ratio 0.44, 95% credible interval 0.26-0.66); ARNI+BB+MRA was associated with the greatest reduction in all-cause mortality versus placebo (hazard ratio 0.37, 95% credible interval 0.19-0.65). A sensitivity analysis that did not account for background therapy suggested that ARNI monotherapy is more efficacious than ACEI or ARB monotherapy. CONCLUSIONS: The network meta-analysis showed that treatment with ACEI, ARB, BB, MRA, and ARNI and their combinations were better than the treatment with placebo in reducing all-cause mortality, with the exception of ARB monotherapy and ARB plus ACEI. The combination of ARNI+BB+MRA resulted in the greatest mortality reduction.
Overview
The claims and statistics of this paper haven’t been checked yet.
Run the check — free, no account needed. It reads the open-access text and checks the sources it cites.
Integrity signals
Registry
Cites
Statistics
Figures
Verification
Claims the paper makes
The claims and statistics of this paper haven’t been checked yet.
Run the check — free, no account needed. It reads the open-access text and checks the sources it cites.
Claims other papers make about this one
Each is checked against this paper’s own text: does it say what the citing paper says it does?
In the citing paper
“β-Blocker therapy is known to foster numerous clinical benefits in some subjects with CVD (e.g. reduced risks of heart attack, stroke, heart failure and death (Black et al., 2010; Burnett et al., 2017; Witte et al., 2018)).”
From A Cardiovascular Disease-Linked Gut Microbial Metabolite Acts via Adrenergic Receptors (2020) · cites this paper as Burnett et al., 2017
Self-check
Percentages, sums and reported differences re-computed from the paper’s own numbers.
The self-check needs the paper’s full text.
Citations
Cites
Preferred Reporting Items for Systematic Reviews and Meta-Analyses: the PRISMA statement
Moher, D., Liberati, A., Tetzlaff, J., Altman, D. G., & for the PRISMA Group (2009) · BMJ · doi:10.1136/bmj.b2535 · Cited by 83,823
McDonagh, T. A., Metra, M., Adamo, M., Gardner, R. S., Baumbach, A., Böhm, M., Burri, H., Butler, J., Čelutkienė, J., Chioncel, O. D., et al. (2021) · PubMed · doi:10.1093/eurheartj/ehab670 · Cited by 20,604
Self-citationPreferred Reporting Items for Systematic Reviews and Meta-Analyses: The PRISMA Statement
Moher, D., Liberati, A., Tetzlaff, J., & Altman, D. G. (2009) · Journal of Clinical Epidemiology · doi:10.1016/j.jclinepi.2009.06.005 · Cited by 19,575
Ahmed, A., Jorna, T., & Bhandari, S. (2016) · The Nephron journals/Nephron journals · doi:10.1159/000447068 · Cited by 11,782
2016 ESC Guidelines for the diagnosis and treatment of acute and chronic heart failure
Ponikowski, P., Voors, A. A., Anker, S. D., Bueno, H., Cleland, J. G. F., Coats, A. J. S., Falk, V., González-Juanatey, J. R., Harjola, V.-P., Jankowska, E. A., et al. (2016) · European Heart Journal · doi:10.1093/eurheartj/ehw128 · Cited by 11,429
Self-citationThe Effect of Spironolactone on Morbidity and Mortality in Patients with Severe Heart Failure
Pitt, B., Zannad, F., Remme, W. J., Cody, R., Castaigne, A., Perez, A., Palensky, J., & Wittes, J. (1999) · New England Journal of Medicine · doi:10.1056/nejm199909023411001 · Cited by 9,214
The SOLVD Investigators* (1991) · New England Journal of Medicine · doi:10.1056/nejm199108013250501 · Cited by 8,029
Angiotensin-neprilysin inhibition versus enalapril in heart failure
McMurray, J. J. V., Packer, M., Desai, A. S., Gong, J., Lefkowitz, M. P., Rizkala, A. R., Rouleau, J. L., Shi, V. C., Solomon, S. D., Swedberg, K., et al. (2014) · New England Journal of Medicine · doi:10.1056/nejmoa1409077 · Cited by 6,957
Self-citationESC Guidelines for the diagnosis and treatment of acute and chronic heart failure 2012
Authors/Task Force Members, McMurray, J. J. V., Adamopoulos, S., Anker, S. D., Auricchio, A., Böhm, M., Dickstein, K., Falk, V., Filippatos, G., Fonseca, C., et al. (2012) · European Heart Journal · doi:10.1093/eurheartj/ehs104 · Cited by 6,879
Self-citationHeart Disease and Stroke Statistics—2010 Update: A Report From the American Heart Association
WRITING GROUP MEMBERS, Lloyd-Jones, D., Adams, R. J., Brown, T. M., Carnethon, M., Dai, S., De Simone, G., Ferguson, T. B., Ford, E., Furie, K., et al. (2010) · Circulation · doi:10.1161/circulationaha.109.192667 · Cited by 5,700
Cited by
Sorted by citations
Mancia, G., Kreutz, R., Brunström, M., Burnier, M., Grassi, G., Januszewicz, A., Muiesan, M. L., Tsioufis, K., Agabiti-Rosei, E., Algharably, E. A. E., et al. (2023) · Journal of Hypertension · doi:10.1097/hjh.0000000000003480 · Cited by 3,473
A Cardiovascular Disease-Linked Gut Microbial Metabolite Acts via Adrenergic Receptors
Nemet, I., Saha, P. P., Gupta, N., Zhu, W., Romano, K. A., Skye, S. M., Cajka, T., Mohan, M. L., Li, L., Wu, Y., et al. (2020) · Cell · doi:10.1016/j.cell.2020.02.016 · Cited by 784
Vaduganathan, M., Claggett, B. L., Jhund, P. S., Cunningham, J. W., Ferreira, J. P., Zannad, F. M., Packer, M., Fonarow, G. C., McMurray, J. J. V., & Solomon, S. D. (2020) · The Lancet · doi:10.1016/s0140-6736(20)30748-0 · Cited by 681
Self-citationAtherton, J. J., Sindone, A. P., Pasquale, C. G. D., Driscoll, A. L., Macdonald, P. S., Hopper, I., Kistler, P. M., Briffa, T. G., Wong, J., Abhayaratna, W. P., et al. (2018) · Heart Lung and Circulation · doi:10.1016/j.hlc.2018.06.1042 · Cited by 439
Tromp, J., Ouwerkerk, W., van Veldhuisen, D. J., Hillege, H. L., Richards, M., van der Meer, P., Anand, I. S., Lam, C. S. P., & Voors, A. A. (2021) · JACC Heart Failure · doi:10.1016/j.jchf.2021.09.004 · Cited by 429
Self-citation
Metadata
- Authors
- Burnett, H., Earley, A., Voors, A. A., Senni, M., McMurray, J. J. V., Deschaseaux, C., & Cope, S.
- Affiliations
- Novartis (Switzerland) (CH)
- Corresponding author
- Burnett, Heather
- Venue
- Circulation Heart Failure
- Published
- 2017-01
- Volume
- 10
- Issue
- 1
- ISSN
- 1941-3289 (ISSN-L)
- 1941-3297
- PMC
- PMC5265698
- OpenAlex
- W2577614303
- Cited by
- 238
- References
- 100
- Citations by year
- 2026: 4 · 2025: 19 · 2024: 20 · 2023: 18 · 2022: 45 · 2021: 42 · 2020: 33 · 2019: 33 · 2018: 15 · 2017: 9
- FWCI
- 19.05
- Type
- journal article
- Language
- en
- Open access
- green
- www.ncbi.nlm.nih.gov
- Licence
- cc-by-nc-nd
- Locations
- Circulation Heart Failure (publishedVersion)
- PubMed Central (publishedVersion, cc-by-nc-nd)
- PubMed (publishedVersion)
- University of Groningen research database (University of Groningen / Centre for Information Technology) (publishedVersion, cc-by-nc-nd)
- ENLIGHTEN (Jurnal Bimbingan dan Konseling Islam) (acceptedVersion)
- BOA (University of Milano-Bicocca) (submittedVersion)
- University of Groningen research database (University of Groningen / Centre for Information Technology) (submittedVersion, cc-by-nc-nd)
- Topics
- Health Sciences › Medicine › Cardiology and Cardiovascular Medicine › Heart Failure Treatment and Management
- Health Sciences › Medicine › Cardiology and Cardiovascular Medicine › Heart rate and cardiovascular health
- Health Sciences › Medicine › Cardiology and Cardiovascular Medicine › Cardiovascular Function and Risk Factors
- Keywords
- heart failure with reduced ejection fraction, all-cause mortality, ACE inhibitors, angiotensin receptor blockers, beta-blockers, mineralocorticoid receptor antagonists, angiotensin receptor-neprilysin inhibitors, combination therapy, treatment efficacy comparison
- MeSH terms
- Network Meta-Analysis, Chronic Disease, Heart Failure, Humans, Stroke Volume, Randomized Controlled Trials as Topic, Treatment Outcome, Ventricular Dysfunction, Left
About these checks
Registry, retraction, Cites and statistics results are computed, not judged, with one exception: a printed reference that no index lists is read once by a model before it counts as a citation error. Claims are extracted by a model and kept only when their quote appears verbatim in the text; each cited source is then checked, with a model’s help, for whether it says what the claim relies on. Those verdicts can be wrong — read the claim’s quote and the cited source before relying on one.
Statistics and arithmetic are recomputed, not judged.
Confidence bands are shown only for fields calibrated on our annotated test set. None is calibrated yet, so no band is shown.
What counts as a claim ›How we measure confidence ›How we check this ›
Are you an author, or do you see a problem with this page? Request a review
