

The DOI matches its Crossref record; 1 of the 1 references it cites were found in a registry or an index.
Sarilumab Plus Methotrexate in Patients With Active Rheumatoid Arthritis and Inadequate Response to Methotrexate: Results of a Phase III Study
Abstract
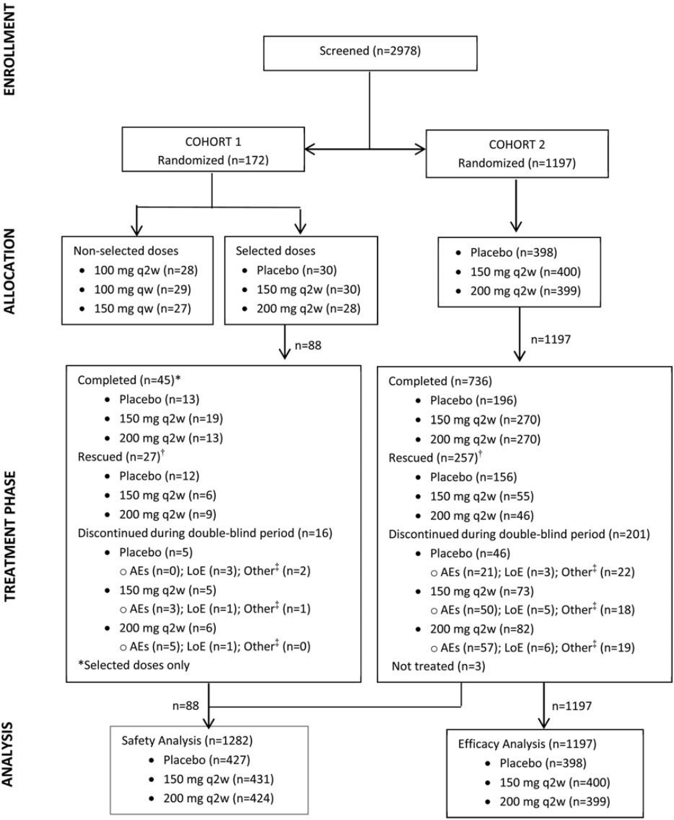
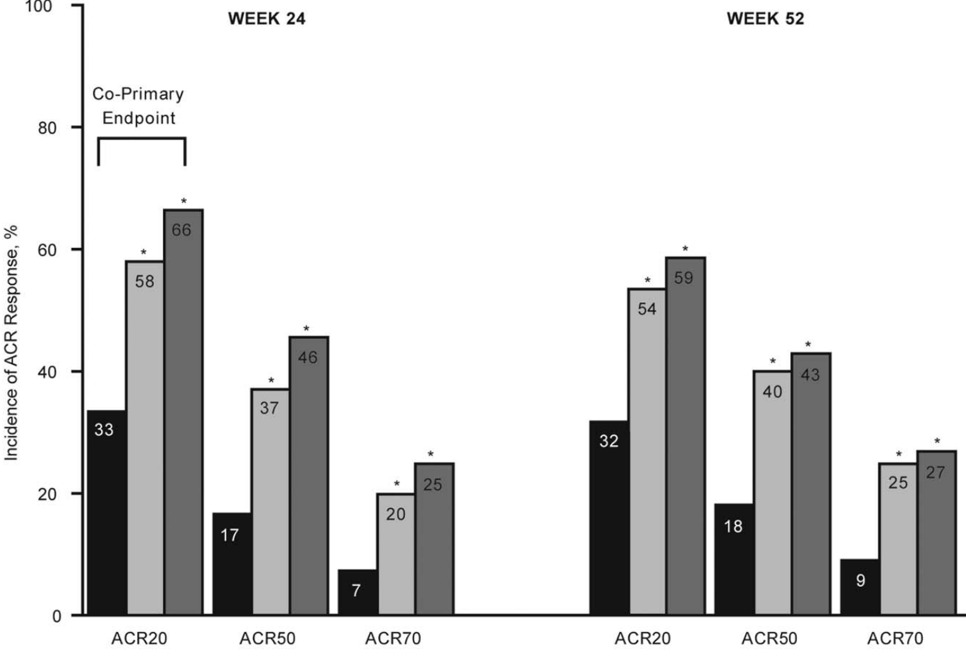
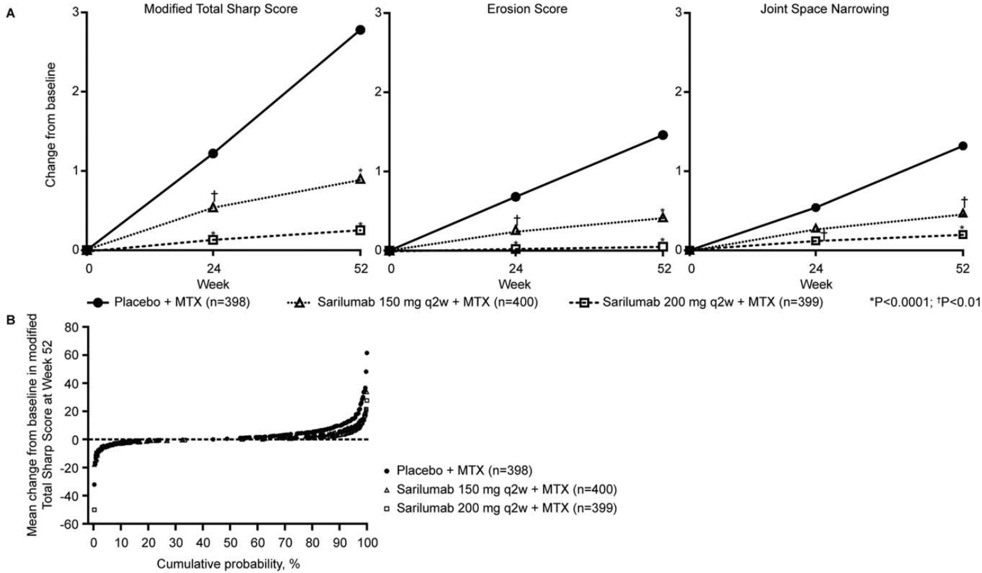
Objective: To evaluate the efficacy and safety of sarilumab in combination with methotrexate (MTX) for the treatment of rheumatoid arthritis (RA). Methods: Adults with moderate‐to‐severe RA and an inadequate response to MTX were randomized (1:1:1) to receive sarilumab (doses of 150 mg or 200 mg) or placebo every 2 weeks in conjunction with weekly MTX for 52 weeks. Co–primary end points were the proportion of patients achieving American College of Rheumatology 20% (ACR20) improvement responses at week 24, change from baseline in the Health Assessment Questionnaire (HAQ) disability index (DI) at week 16, and change from baseline in the modified Sharp/van der Heijde score (SHS) of radiographic damage at week 52. Results: Baseline characteristics were similar among the groups. For all 3 co–primary end points, the sarilumab 150 mg and 200 mg groups demonstrated statistically significant improvements as compared with the placebo group (ACR20 response rate at week 24, 58.0%, 66.4%, and 33.4%, respectively [P < 0.0001]; least squares mean change in HAQ DI at week 16, −0.53, −0.55, and −0.29, respectively [P < 0.0001]; and mean change in SHS at week 52, 0.90, 0.25, and 2.78, respectively [P < 0.0001]). The most common treatment‐emergent adverse event was infection. In the sarilumab 150 mg, sarilumab 200 mg, and placebo groups, the incidence of serious infections was 2.6%, 4.0%, and 2.3%, respectively. Elevations in alanine aminotransferase levels >3‐fold the upper limit of normal occurred in 9.5%, 8.0%, and 2.1% of patients, respectively; in 24 patients, this led to discontinuation of treatment. Elevated total cholesterol levels were observed in 36.8%, 43.0%, and 18.3% of patients, respectively. In patients receiving 150 mg and 200 mg sarilumab, neutrophil counts of 0.5 to <1.0 × 10 9/liter were observed in 5.1% and 7.8% of patients, respectively, while neutrophil counts of <0.5 × 10 9/liter were observed in 0.9% and 0.7% of patients, respectively; none of the patients receiving placebo experienced changes in neutrophil counts. Conclusion: In RA patients treated with sarilumab (150 mg or 200 mg every 2 weeks) in combination with MTX, both doses provided sustained clinical efficacy, as shown by significant improvements in symptomatic, functional, and radiographic outcomes. Sarilumab was generally well tolerated. The adverse events observed in this study were consistent with the effects of interleukin‐6 signaling blockade.
Overview
The claims and statistics of this paper haven’t been checked yet.
Run the check — free, no account needed. It reads the open-access text and checks the sources it cites.
Integrity signals
Registry
Cites
Statistics
Figures
Verification
Claims the paper makes
The claims and statistics of this paper haven’t been checked yet.
Run the check — free, no account needed. It reads the open-access text and checks the sources it cites.
Claims other papers make about this one
Each is checked against this paper’s own text: does it say what the citing paper says it does?
The source backs part of the claim, not all of it — or backs it for a different population, condition or comparison.
In the citing paper
“Sarilumab, a fully human monoclonal antibody with 10- to 40-fold higher affinity for IL-6R than tocilizumab, was also approved for the treatment of RA in the EU and USA in 2017 (Fleischmann et al., 2017; Genovese et al., 2015”
From Targeting Interleukin-6 Signaling in Clinic (2019) · cites this paper as Genovese et al., 2015
Experimental — accuracy not yet measured
Self-check
Percentages, sums and reported differences re-computed from the paper’s own numbers.
The self-check needs the paper’s full text.
Citations
Cites
Genovese, M. C., McKay, J. D., Nasonov, E. L., Mysler, E. F., da Silva, N. A., Alecock, E., Woodworth, T., & Gomez‐Reino, J. J. (2008) · Arthritis & Rheumatism · doi:10.1002/art.23940 · Cited by 855
Self-citation
Research works printed but not linked: 44
- 10.1093/rheumatology/kes278 · DOI
- 10.1002/acr.21641 · DOI
- 10.1136/annrheumdis-2013-204573 · DOI
- 10.1093/oxfordjournals.rheumatology.a031496 · DOI
- Simsek I., 2010, TNF inhibitors: new and old agents for rheumatoid arthritis, Bull NYU Hosp Jt Dis, 68, 204
- Singh JA, 2012, Summary of AHRQ's comparative effectiveness review of drug therapy for rheumatoid arthritis (RA) in adults: an update, J Manag Care Pharm, 18, S1
- 10.1038/nrrheum.2013.8 · DOI · Paper page
- 10.1177/1759720X10378372 · DOI
- 10.1007/s00296-006-0143-2 · DOI
- 10.1097/00124743-199504000-00006 · DOI
- 10.1073/pnas.1323896111 · DOI
- 10.1073/pnas.1324022111 · DOI
- 10.1136/ard.2008.092932 · DOI · Paper page
- 10.1136/ard.2008.105197 · DOI · Paper page
- 10.1002/art.30158 · DOI
- 10.1136/annrheumdis-2011-200395 · DOI
- 10.1016/S0140-6736(08)60453-5 · DOI
- 10.1136/annrheumdis-2013-204405 · DOI
- 10.1136/annrheumdis-2013-eular.2360 · DOI
- 10.1136/annrheumdis-2013-eular.1148 · DOI
- 10.1158/1538-7445.AM2012-2723 · DOI
- 10.1002/art.1780310302 · DOI
- 10.1002/art.1780360601 · DOI
- Heijde DM, 1999, . How to read radiographs according to the Sharp/van der Heijde method [corrected and republished in J Rheumatol 2000;27:261–3], J Rheumatol, 26, 743
- 10.1002/art.1780380602 · DOI
- 10.1002/art.1780230202 · DOI
- 10.1002/art.1780380107 · DOI
- 10.1186/ar1740 · DOI
- 10.1136/annrheumdis-2013-203843 · DOI
- 10.1038/nrrheum.2011.202 · DOI
- 10.1002/art.37816 · DOI
- 10.1136/ard.2010.146043 · DOI
- Aletaha D, 2005, The Simplified Disease Activity Index (SDAI) and the Clinical Disease Activity Index (CDAI): a review of their usefulness and validity in rheumatoid arthritis, Clin Exp Rheumatol, 23, S100
- 10.1093/rheumatology/kes113 · DOI · Paper page
- 10.1016/j.semarthrit.2013.08.001 · DOI
- 10.1002/art.38779 · DOI
- 10.3899/jrheum.100717 · DOI
- 10.1001/2012.jama.10857 · DOI
- 10.1002/pst.1622 · DOI
- 10.1002/pst.1619 · DOI
- 10.1093/rheumatology/keq343 · DOI
- 10.1136/annrheumdis-2013-204760 · DOI · Paper page
- 10.1136/annrheumdis-2011-200704 · DOI
- 10.1136/annrheumdis-2013-205137 · DOI · Paper page
Cited by
Sorted by citations
Targeting Interleukin-6 Signaling in Clinic
Kang, S., Tanaka, T., Narazaki, M., & Kishimoto, T. (2019) · Immunity · doi:10.1016/j.immuni.2019.03.026 · Cited by 904
C-reactive protein and implications in rheumatoid arthritis and associated comorbidities
Pope, J. E., & Choy, E. H. (2021) · Seminars in Arthritis and Rheumatism · doi:10.1016/j.semarthrit.2020.11.005 · Cited by 320
Therapeutic Potential of Targeting the Th17/Treg Axis in Autoimmune Disorders.
Fasching, P., Stradner, M., Graninger, W., Dejaco, C., & Fessler, J. (2017) · Molecules · doi:10.3390/molecules22010134 · Cited by 254
IL-6 Revisited: From Rheumatoid Arthritis to CAR T Cell Therapy and COVID-19
Kishimoto, T., & Kang, S. (2022) · Annual Review of Immunology · doi:10.1146/annurev-immunol-101220-023458 · Cited by 140
Metadata
- Authors
- Genovese, M. C., Fleischmann, R., Kivitz, A. J., Rell‐Bakalarska, M., Martincova, R., Fiore, S., Rohane, P., van Hoogstraten, H., Garg, A., Fan, C., van Adelsberg, J., Weinstein, S. P., Graham, N. M. H., Stahl, N., Yancopoulos, G. D., Huizinga, T. W. J., & van der Heijde, D.
- Affiliations
- Stanford University Medical Center Palo Alto California
- Metroplex Clinical Research Center Dallas Texas
- Altoona Center for Clinical Research Duncansville Pennsylvania
- Rheumatology and Osteoporosis Outpatient Clinic Warsaw Poland
- Sanofi Prague Czech Republic
- Sanofi Bridgewater New Jersey
- Regeneron Pharmaceuticals Tarrytown New York
- Leiden University Medical Centre Leiden The Netherlands
- Venue
- Arthritis & Rheumatology
- Publisher
- Wiley
- Published
- 2015-05-25
- Volume
- 67
- Issue
- 6
- Pages
- 1424-1437
- ISSN
- 2326-5191
- 2326-5205
- Cited by
- 219
- References
- 1
- Language
- en
- Funders
- Sanofi
- Regeneron
About these checks
Registry, retraction, Cites and statistics results are computed, not judged, with one exception: a printed reference that no index lists is read once by a model before it counts as a citation error. Claims are extracted by a model and kept only when their quote appears verbatim in the text; each cited source is then checked, with a model’s help, for whether it says what the claim relies on. Those verdicts can be wrong — read the claim’s quote and the cited source before relying on one.
Statistics and arithmetic are recomputed, not judged.
Confidence bands are shown only for fields calibrated on our annotated test set. None is calibrated yet, so no band is shown.
What counts as a claim ›How we measure confidence ›How we check this ›
Are you an author, or do you see a problem with this page? Request a review
How to cite
Cite CoChat for the checks on this page, and the paper for its own findings.
- This page
- CoChat. (2026). Citation check: Sarilumab Plus Methotrexate in Patients With Active Rheumatoid Arthritis and Inadequate Response to Methotrexate: Results of a Phase III Study. https://app.cochat.ai/papers/10.1002/art.39093
- The paper
- Genovese, M. C., Fleischmann, R., Kivitz, A. J., Rell‐Bakalarska, M., Martincova, R., Fiore, S., Rohane, P., van Hoogstraten, H., Garg, A., Fan, C., van Adelsberg, J., Weinstein, S. P., Graham, N. M. H., Stahl, N., Yancopoulos, G. D., Huizinga, T. W. J., & van der Heijde, D. (2015). Sarilumab Plus Methotrexate in Patients With Active Rheumatoid Arthritis and Inadequate Response to Methotrexate: Results of a Phase III Study. Arthritis & Rheumatology. https://doi.org/10.1002/art.39093
