

The DOI matches its Crossref record; 18 of the 18 references it cites were found in a registry or an index.
Resmetirom for nonalcoholic fatty liver disease: a randomized, double-blind, placebo-controlled phase 3 trial
Open accessAbstract
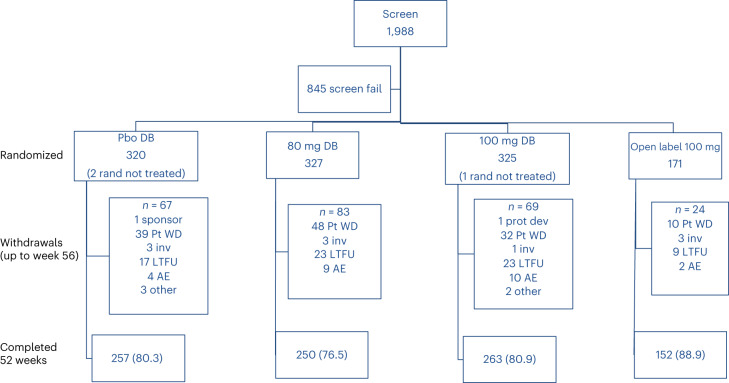
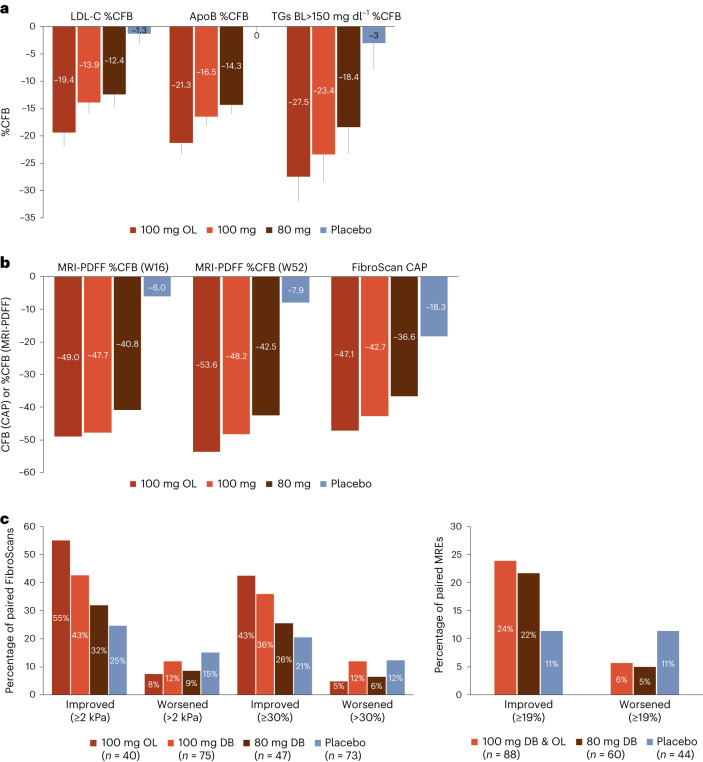
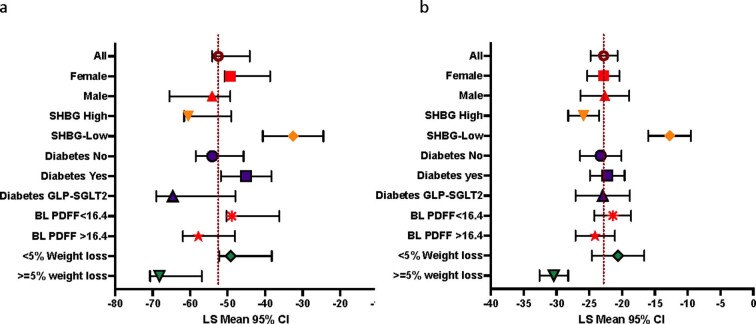
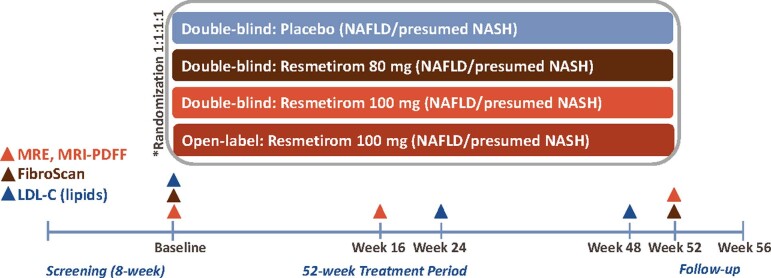
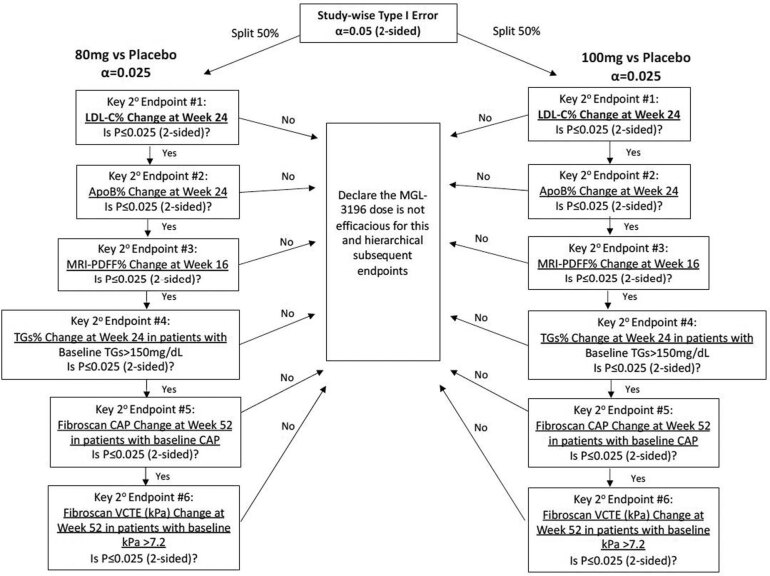
Nonalcoholic steatohepatitis (NASH) is a progressive liver disease with no approved treatment. MAESTRO-NAFLD-1 was a 52-week randomized, double-blind, placebo-controlled phase 3 trial evaluating the safety of resmetirom in adults with nonalcoholic fatty liver disease and presumed NASH. Patients were randomized to three double-blind arms (100 mg resmetirom (n = 325), 80 mg resmetirom (n = 327) or placebo (n = 320)) or open-label 100 mg resmetirom (n = 171). The primary end point was incidence of treatment-emergent adverse events (TEAEs) over 52 weeks and key secondary end points were LDL-C, apoB, triglycerides (over 24 weeks), hepatic fat (over 16 and 52 weeks) and liver stiffness (over 52 weeks). Resmetirom was safe and well tolerated. TEAEs occurred in 86.5% (open-label 100 mg resmetirom), 86.1% (100 mg resmetirom), 88.4% (80 mg resmetirom) and 81.8% (placebo) of patients. TEAEs in excess of placebo included diarrhea and nausea at the initiation of treatment. Key secondary end points included least square means difference from placebo at 80 mg, 100 mg resmetirom: LDL-C (-11.1%, -12.6%), apoB (-15.6%, -18.0%), triglycerides (-15.4%, -20.4%), 16-week hepatic fat (-34.9%, -38.6%), (P < 0.0001) and liver stiffness (-1.02, -1.70) and 52-week hepatic fat (-28.8, -33.9). These findings demonstrate resmetirom was safe and well tolerated in adults with presumed NASH, supporting a role for further clinical development. (ClinicalTrials.gov identifier NCT04197479 ).
Overview
The claims and statistics of this paper haven’t been checked yet.
Run the check — free, no account needed. It reads the open-access text and checks the sources it cites.
Integrity signals
Registry
Cites
Statistics
Figures
Verification
Claims the paper makes
The claims and statistics of this paper haven’t been checked yet.
Run the check — free, no account needed. It reads the open-access text and checks the sources it cites.
Claims other papers make about this one
Each is checked against this paper’s own text: does it say what the citing paper says it does?
The source backs part of the claim, not all of it — or backs it for a different population, condition or comparison.
In the citing paper
“Further, the highest dose achieved a greater NAS reduction compared to placebo while body weight remained unchanged [210] (Table 1).”
From Obesity and MASLD: Is weight loss the (only) key to treat metabolic liver disease? (2024) · cites this paper as [210]
Experimental — accuracy not yet measuredThe source backs part of the claim, not all of it — or backs it for a different population, condition or comparison.
In the citing paper
“Resmetirom, a THRβ agonist, showed antisteatogenic potential in a 36-week phase 2 RCT in people with biopsy-confirmed MASH and fibrosis, accompanied by a rise in circulating adiponectin and improved plasma lipid profile [210,211].”
From Obesity and MASLD: Is weight loss the (only) key to treat metabolic liver disease? (2024) · cites this paper as [210]
Experimental — accuracy not yet measuredThe source backs part of the claim, not all of it — or backs it for a different population, condition or comparison.
In the citing paper
“| Harrison et al. | Resmetirom (36 weeks) | NASH | PDFF -5.3 %; | ↔ | ↔ | TG ↓; LDL ↓ | ↔ |”
From Obesity and MASLD: Is weight loss the (only) key to treat metabolic liver disease? (2024) · cites this paper as [210]
Experimental — accuracy not yet measuredThe source backs part of the claim, not all of it — or backs it for a different population, condition or comparison.
In the citing paper
“| | | (histology) | NASH resolution ↑; fibrosis ↔; | | | | |”
From Obesity and MASLD: Is weight loss the (only) key to treat metabolic liver disease? (2024) · cites this paper as [210]
Experimental — accuracy not yet measuredThe source backs part of the claim, not all of it — or backs it for a different population, condition or comparison.
In the citing paper
“| Harrison et al. | Resmetirom (36 weeks) | NASH | PDFF -5.3 %; | ↔ | ↔ | TG ↓; LDL ↓ | ↔ |”
From Obesity and MASLD: Is weight loss the (only) key to treat metabolic liver disease? (2024) · cites this paper as [210]
Experimental — accuracy not yet measured
The source backs part of the claim, not all of it — or backs it for a different population, condition or comparison.
In the citing paper
“| | | (histology) | NASH resolution ↑; fibrosis ↔; | | | | |”
From Obesity and MASLD: Is weight loss the (only) key to treat metabolic liver disease? (2024) · cites this paper as [210]
Experimental — accuracy not yet measuredThe source backs part of the claim, not all of it — or backs it for a different population, condition or comparison.
In the citing paper
“| (2019) [210] | | F1-F3 | NAS ↓; | | | | |”
From Obesity and MASLD: Is weight loss the (only) key to treat metabolic liver disease? (2024) · cites this paper as [210]
Experimental — accuracy not yet measuredThe source backs part of the claim, not all of it — or backs it for a different population, condition or comparison.
In the citing paper
“Notably, resmetirom signi fi cantly improved MRIPDFF and liver stiffness measurements in the MAESTRO- NAFLD phase III trial that did not require a liver biopsy for study inclusion.”
From EASL-EASD-EASO Clinical Practice Guidelines on the management of metabolic dysfunction-associated steatotic liver disease (MASLD). (2024) · cites this paper as [362]
Experimental — accuracy not yet measuredThe check wasn’t confident either way, so it gives no verdict — never disputed.
In the citing paper
“Further, recently published results from phase 2 studies with histological endpoints suggested fibrosis regression in people with MASH-induced cirrhosis with efruxifermin but also pegozafermin treatment [205,206], which position FGF 21 analogs as a potential future pharmacological treatment option for advanced metabolic liver disease.”
From Obesity and MASLD: Is weight loss the (only) key to treat metabolic liver disease? (2024) · cites this paper as [206]
Experimental — accuracy not yet measured
Self-check
Percentages, sums and reported differences re-computed from the paper’s own numbers.
The self-check needs the paper’s full text.
Citations
Cites
Younossi, Z. M., Koenig, A. B., Abdelatif, D., Fazel, Y., Henry, L., & Wymer, M. (2016) · Hepatology · doi:10.1002/hep.28431 · Cited by 10,781
Mach, F., Baigent, C., Catapano, A. L., Koskinas, K. C., Casula, M., Badimon, L., Chapman, M. J., De Backer, G. G., Delgado, V., Ference, B. A., et al. (2020) · European Heart Journal · doi:10.1093/eurheartj/ehz455 · Cited by 8,961
Chalasani, N., Younossi, Z., Lavine, J. E., Charlton, M., Cusi, K., Rinella, M., Harrison, S. A., Brunt, E. M., & Sanyal, A. J. (2018) · Hepatology · doi:10.1002/hep.29367 · Cited by 7,239
Self-citationGlobal burden of NAFLD and NASH: trends, predictions, risk factors and prevention
Younossi, Z., Anstee, Q. M., Marietti, M., Hardy, T., Henry, L., Eslam, M., George, J., & Bugianesi, E. (2018) · Nature Reviews Gastroenterology & Hepatology · doi:10.1038/nrgastro.2017.109 · Cited by 5,249
Mach, F., Baigent, C., Catapano, A. L., Koskinas, K. C., Casula, M., Badimon, L., Chapman, M. J., De Backer, G. G., Delgado, V., Ference, B. A., et al. (2019) · Atherosclerosis · doi:10.1016/j.atherosclerosis.2019.08.014 · Cited by 4,854
Estes, C., Razavi, H. A., Loomba, R. S., Younossi, Z. M., & Sanyal, A. J. (2017) · Hepatology · doi:10.1002/hep.29466 · Cited by 2,496
Younossi, Z. M., Golabi, P., de Avila, L., Paik, J. M., Srishord, M., Fukui, N., Qiu, Y., Burns, L., Afendy, A., & Nader, F. (2019) · Journal of Hepatology · doi:10.1016/j.jhep.2019.06.021 · Cited by 2,235
Risk of Cardiovascular Disease in Patients with Nonalcoholic Fatty Liver Disease
Targher, G., Day, C. P., & Bonora, E. (2010) · New England Journal of Medicine · doi:10.1056/nejmra0912063 · Cited by 1,907
Global epidemiology of NAFLD-related HCC: trends, predictions, risk factors and prevention
Huang, D. Q., El-Serag, H. B., & Loomba, R. (2021) · Nature Reviews Gastroenterology & Hepatology · doi:10.1038/s41575-020-00381-6 · Cited by 1,855
Harrison, S. A., Bashir, M. R., Guy, C. D., Zhou, R., Moylan, C. A., Frias, J. P., Alkhouri, N., Bansal, M. B., Baum, S., Neuschwander-Tetri, B. A., et al. (2019) · The Lancet · doi:10.1016/s0140-6736(19)32517-6 · Cited by 802
Self-citation
Cited by
Sorted by citations
Tacke, F., Horn, P., Wai-Sun Wong, V., Ratziu, V., Bugianesi, E., Francque, S., Zelber-Sagi, S., Valenti, L., Roden, M., Schick, F., et al. (2024) · Journal of Hepatology · doi:10.1016/j.jhep.2024.04.031 · Cited by 2,210
A phase 3, randomized, controlled trial of resmetirom in NASH with liver fibrosis
Harrison, S. A., Bedossa, P., Guy, C. D., Schattenberg, J. M., Loomba, R., Taub, R., Labriola, D., Moussa, S. E., Neff, G. W., Rinella, M. E., et al. (2024) · New England Journal of Medicine · doi:10.1056/nejmoa2309000 · Cited by 2,084
Self-citationMetabolic Dysfunction–Associated Steatotic Liver Disease
Targher, G., Valenti, L., & Byrne, C. D. (2025) · New England Journal of Medicine · doi:10.1056/nejmra2412865 · Cited by 325
Obesity and MASLD: Is weight loss the (only) key to treat metabolic liver disease?
Huttasch, M., Roden, M., & Kahl, S. (2024) · Metabolism · doi:10.1016/j.metabol.2024.155937 · Cited by 169
Kokkorakis, M., Boutari, C., Hill, M. A., Kotsis, V., Loomba, R., Sanyal, A. J., & Mantzoros, C. S. (2024) · Metabolism · doi:10.1016/j.metabol.2024.155835 · Cited by 155
Metadata
- Authors
- Harrison, S. A., Taub, R., Neff, G. W., Lucas, K. J., Labriola, D., Moussa, S. E., Alkhouri, N., & Bashir, M. R.
- Affiliations
- Pinnacle Clinical Research (US)
- Madrigal Pharmaceuticals (United States) (US)
- Lucas Research (US)
- University of Arizona (US)
- Arizona Liver Health (US)
- Duke Medical Center (US)
- Corresponding author
- Harrison, Stephen A.
- Venue
- Nature Medicine
- Published
- 2023-10-16
- Volume
- 29
- Issue
- 11
- Pages
- 2919-2928
- ISSN
- 1078-8956 (ISSN-L)
- 1546-170X
- PMC
- PMC10667098
- OpenAlex
- W4387666937
- Cited by
- 435
- References
- 18
- Citations by year
- 2026: 108 · 2025: 178 · 2024: 138 · 2023: 11
- FWCI
- 87.06
- Type
- journal article
- Language
- en
- Open access
- hybrid
- doi.org
- Locations
- Nature Medicine (publishedVersion, cc-by)
- PubMed Central (publishedVersion, cc-by)
- PubMed (publishedVersion)
- Funders
- Madrigal Pharmaceuticals
- Topics
- Health Sciences › Medicine › Hepatology › Liver Disease Diagnosis and Treatment
- Health Sciences › Medicine › Hepatology › Hepatitis C virus research
- Health Sciences › Medicine › Hepatology › Liver Diseases and Immunity
- Keywords
- resmetirom, non-alcoholic fatty liver disease, nonalcoholic steatohepatitis, liver fat, liver stiffness, LDL cholesterol, apolipoprotein B, triglycerides, treatment-emergent adverse events, drug safety and tolerability
- MeSH terms
- Adult, Apolipoproteins B, Double-Blind Method, Humans, Cholesterol, LDL, Liver, Pyridazines, Triglycerides, Uracil, Treatment Outcome, Non-alcoholic Fatty Liver Disease
About these checks
Registry, retraction, Cites and statistics results are computed, not judged, with one exception: a printed reference that no index lists is read once by a model before it counts as a citation error. Claims are extracted by a model and kept only when their quote appears verbatim in the text; each cited source is then checked, with a model’s help, for whether it says what the claim relies on. Those verdicts can be wrong — read the claim’s quote and the cited source before relying on one.
Statistics and arithmetic are recomputed, not judged.
Confidence bands are shown only for fields calibrated on our annotated test set. None is calibrated yet, so no band is shown.
What counts as a claim ›How we measure confidence ›How we check this ›
Are you an author, or do you see a problem with this page? Request a review
