

The DOI matches its Crossref record; 70 of the 71 references it cites were found in a registry or an index.
Med-BERT: pretrained contextualized embeddings on large-scale structured electronic health records for disease prediction
Open accessAbstract
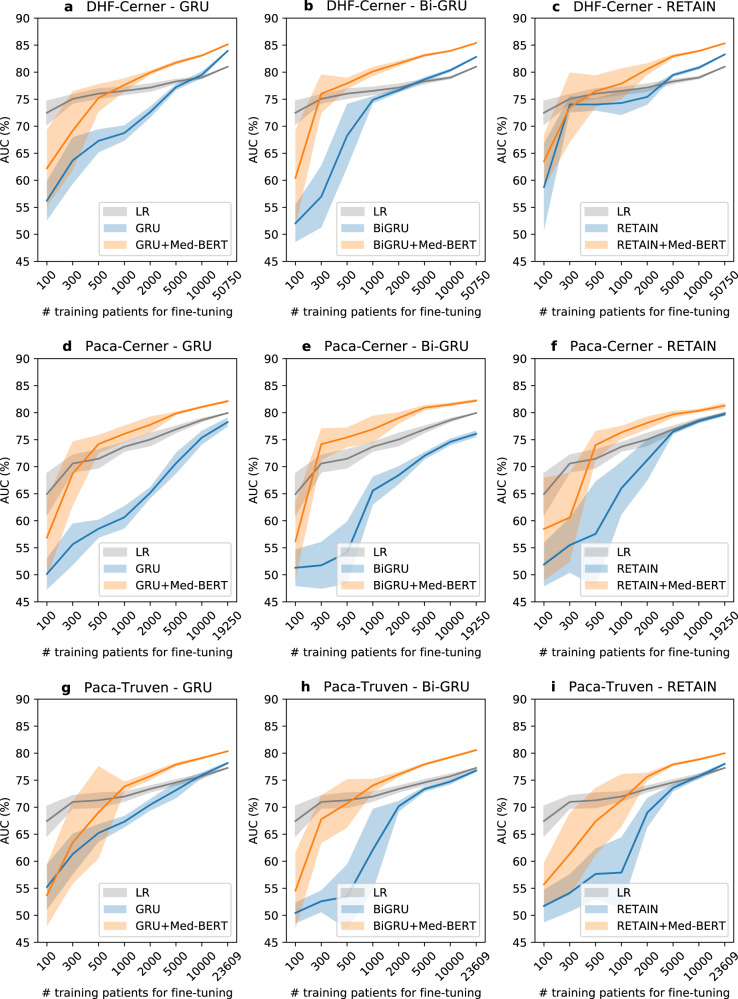
Deep learning (DL)-based predictive models from electronic health records (EHRs) deliver impressive performance in many clinical tasks. Large training cohorts, however, are often required by these models to achieve high accuracy, hindering the adoption of DL-based models in scenarios with limited training data. Recently, bidirectional encoder representations from transformers (BERT) and related models have achieved tremendous successes in the natural language processing domain. The pretraining of BERT on a very large training corpus generates contextualized embeddings that can boost the performance of models trained on smaller datasets. Inspired by BERT, we propose Med-BERT, which adapts the BERT framework originally developed for the text domain to the structured EHR domain. Med-BERT is a contextualized embedding model pretrained on a structured EHR dataset of 28,490,650 patients. Fine-tuning experiments showed that Med-BERT substantially improves the prediction accuracy, boosting the area under the receiver operating characteristics curve (AUC) by 1.21–6.14% in two disease prediction tasks from two clinical databases. In particular, pretrained Med-BERT obtains promising performances on tasks with small fine-tuning training sets and can boost the AUC by more than 20% or obtain an AUC as high as a model trained on a training set ten times larger, compared with deep learning models without Med-BERT. We believe that Med-BERT will benefit disease prediction studies with small local training datasets, reduce data collection expenses, and accelerate the pace of artificial intelligence aided healthcare.
Overview
The claims and statistics of this paper haven’t been checked yet.
Free: it reads the open-access text and checks the first 5 claims that cite a source we can check. Create a free account to check every claim.
Integrity signals
Registry
Cites
Statistics
Figures




Verification
Claims the paper makes
The claims and statistics of this paper haven’t been checked yet.
Free: it reads the open-access text and checks the first 5 claims that cite a source we can check. Create a free account to check every claim.
Claims other papers make about this one
Each is checked against this paper’s own text: does it say what the citing paper says it does?
The source backs part of the claim, not all of it — or backs it for a different population, condition or comparison.
In the citing paper
“In biomedical informatics, numerous models utilizing this approach, such as BioBERT, MedBERT, and BiomedBERT, have been developed by training models on various relevant text corpora, such as EHR data and biomedical academic literature15–17.”
From OnSIDES database: Extracting adverse drug events from drug labels using natural language processing models (2025) · cites this paper as [17]
Experimental — accuracy not yet measuredThe source backs part of the claim, not all of it — or backs it for a different population, condition or comparison.
In the citing paper
“Machine learning methods11–14, particularly deep learning, typically employ neural networks and the first generation of transformer-based large language models (e.g., BERT).”
From A critical assessment of using ChatGPT for extracting structured data from clinical notes (2024) · cites this paper as [14]
Experimental — accuracy not yet measuredThe source backs part of the claim, not all of it — or backs it for a different population, condition or comparison.
In the citing paper
“MedBERT is limited to ICD 10 codes and evaluated on a small subset of disorders, which might be insufficient for estimating general performance.”
From Foresight-a generative pretrained transformer for modelling of patient timelines using electronic health records: a retrospective modelling study (2024) · cites this paper as [6]
Experimental — accuracy not yet measuredThe cited source says what the claim attributes to it.
In the citing paper
“Med-BERT was pretrained on structured EHR data from over 28 million patients and evaluated on the prediction of pancreatic cancer, and heart failure in patients with diabetes61.”
From Orchestrating explainable artificial intelligence for multimodal and longitudinal data in medical imaging (2024) · cites this paper as [61]
The cited source says what the claim attributes to it.
In the citing paper
“Structured EHR baselines implemented embedding, based and transformer, based architectures for disease prediction from longitudinal clinical records56.”
From K-STAMM: a knowledge-enhanced spatial - temporal attention model with multimodal fusion for pneumonia prediction (2026) · cites this paper as [56]
2 more claims about this paper
Create a free account to see every claim other papers make about this one.
Self-check
Percentages, sums and reported differences re-computed from the paper’s own numbers.
The self-check needs the paper’s full text.
Citations
Cites
BERT: Pre-training of Deep Bidirectional Transformers for Language Understanding
Devlin, J., Chang, M.-W., Lee, K., & Toutanova, K. (2019) · Proceedings of the 2019 Conference of the North American Chapter of the Association for Computational Linguistics: Human Language Technologies, Volume 1 (Long and Short Papers) · doi:10.18653/v1/n19-1423 · Cited by 54,325 · cited 1×
“For pre-training we used mainly the BERT recommended parameters [29].”
MethodGlove: Global Vectors for Word Representation
Pennington, J., Socher, R., & Manning, C. (2014) · Proceedings of the 2014 Conference on Empirical Methods in Natural Language Processing (EMNLP) · doi:10.3115/v1/d14-1162 · Cited by 34,071
Pan, S. J., & Yang, Q. (2010) · IEEE Transactions on Knowledge and Data Engineering · doi:10.1109/tkde.2009.191 · Cited by 23,387 · cited 1×
“Transfer learning was developed to address the issue whereby some representations were first pretrained on large volumes of unannotated datasets and then further adapted to guide other tasks [23].”
BackgroundLanguage Models are Few-Shot Learners
Brown, T. B., Mann, B., Ryder, N., Subbiah, M., Kaplan, J., Dhariwal, P., Neelakantan, A., Shyam, P., Sastry, G., Askell, A., et al. (2020) · arXiv · doi:10.48550/arxiv.2005.14165 · Cited by 23,372
Dermatologist-level classification of skin cancer with deep neural networks
Esteva, A., Kuprel, B., Novoa, R. A., Ko, J., Swetter, S. M., Blau, H. M., & Thrun, S. (2017) · Nature · doi:10.1038/nature21056 · Cited by 14,362
Deep Contextualized Word Representations
Peters, M., Neumann, M., Iyyer, M., Gardner, M., Clark, C., Lee, K., & Zettlemoyer, L. (2018) · Proceedings of the 2018 Conference of the North American Chapter of the Association for Computational Linguistics: Human Language Technologies, Volume 1 (Long Papers) · doi:10.18653/v1/n18-1202 · Cited by 11,983 · cited 1×
“This pre-training-fine-tuning paradigm has been proven to be extremely effective in natural language processing (NLP) [24-30] and, recently, computer visions [31,32].”
Empirical Evaluation of Gated Recurrent Neural Networks on Sequence Modeling
Chung, J., Gulcehre, C., Cho, K., & Bengio, Y. (2014) · arXiv · doi:10.48550/arxiv.1412.3555 · Cited by 11,008 · cited 1×
“For Ex-1 and Ex-2, we adopted GRU [50], Bi-GRU [51], and RETAIN [12] as our base models.”
MethodA simple framework for contrastive learning of visual representations
Chen, T., Kornblith, S., Norouzi, M., & Hinton, G. (2020) · arXiv · doi:10.48550/arxiv.2002.05709 · Cited by 10,857
Enriching Word Vectors with Subword Information
Bojanowski, P., Grave, E., Joulin, A., & Mikolov, T. (2017) · Transactions of the Association for Computational Linguistics · doi:10.1162/tacl_a_00051 · Cited by 9,645
Transformers: State-of-the-Art Natural Language Processing
Wolf, T., Debut, L., Sanh, V., Chaumond, J., Delangue, C., Moi, A., Cistac, P., Rault, T., Louf, R., Funtowicz, M., et al. (2020) · Proceedings of the 2020 Conference on Empirical Methods in Natural Language Processing: System Demonstrations · doi:10.18653/v1/2020.emnlp-demos.6 · Cited by 8,741
Research works printed but not linked: 3
- Sun, C., Shrivastava, A., Singh, S. & Gupta, A. In Proceedings of the IEEE International Conference on Computer Vision, 843–852.
- Mikolov, T., Sutskever, I., Chen, K., Corrado, G. S. & Dean, J. Distributed representations of words and phrases and their compositionality. In Advances in Neural Information Processing Systems, 3111–3119 (NIPS, 2013).
- Radford, A. et al. Language models are unsupervised multitask learners. OpenAI Blog 1, 9 (2019).
Cited by
On the Opportunities and Risks of Foundation Models
Bommasani, R., Hudson, D. A., Adeli, E., Altman, R., Arora, S., von Arx, S., Bernstein, M. S., Bohg, J., Bosselut, A., Brunskill, E., et al. (2021) · arXiv · doi:10.48550/arxiv.2108.07258 · Cited by 2,676
Multimodal learning with transformers: A survey
Xu, P., Zhu, X., & Clifton, D. A. (2023) · IEEE Transactions on Pattern Analysis and Machine Intelligence · doi:10.1109/tpami.2023.3275156 · Cited by 1,072
Self-supervised learning in medicine and healthcare
Krishnan, R., Rajpurkar, P., & Topol, E. J. (2022) · Nature Biomedical Engineering · doi:10.1038/s41551-022-00914-1 · Cited by 605
Sources of bias in artificial intelligence that perpetuate healthcare disparities—A global review
Celi, L. A., Cellini, J., Charpignon, M.-L., Dee, E. C., Dernoncourt, F., Eber, R., Mitchell, W. G., Moukheiber, L., Schirmer, J., Situ, J., et al. (2022) · PLOS Digital Health · doi:10.1371/journal.pdig.0000022 · Cited by 576
Beyond the Imitation Game: Quantifying and extrapolating the capabilities of language models
Srivastava, A., Rastogi, A., Rao, A., Shoeb, A. A. M., Abid, A., Fisch, A., Brown, A. R., Santoro, A., Gupta, A., Garriga-Alonso, A., et al. (2022) · arXiv · doi:10.48550/arxiv.2206.04615 · Cited by 569
Metadata
- Authors
- Rasmy, L., Xiang, Y., Xie, Z., Tao, C., & Zhi, D.
- Affiliations
- The University of Texas Health Science Center at Houston (US)
- Peng Cheng Laboratory (CN)
- Corresponding author
- Xiang, Yang
- Zhi, Degui
- Venue
- npj Digital Medicine
- Published
- 2021-05-20
- Volume
- 4
- Issue
- 1
- Pages
- 86-86
- ISSN
- 2398-6352 (ISSN-L)
- PMC
- PMC8137882
- OpenAlex
- W3160137267
- Semantic Scholar
- 5d4de0fa45aeddc31142e6a24666d06ed7923f1e
- Cited by
- 886
- References
- 71
- Citations by year
- 2026: 184 · 2025: 226 · 2024: 196 · 2023: 146 · 2022: 90 · 2021: 41
- FWCI
- 41.96
- Type
- journal article
- Language
- en
- Open access
- gold
- doi.org
- Licence
- cc-by
- creativecommons.org/licenses/by/4.0 (tdm)
- creativecommons.org/licenses/by/4.0 (vor)
- Locations
- npj Digital Medicine (publishedVersion, cc-by)
- PubMed Central (publishedVersion, cc-by)
- PubMed (publishedVersion)
- DOAJ (DOAJ: Directory of Open Access Journals) (submittedVersion, cc-by-sa)
- Funders
- Cancer Prevention and Research Institute of Texas (RP170668, RP160015)
- American Heart Association (19GPSGC35180031)
- Topics
- Physical Sciences › Computer Science › Artificial Intelligence › Machine Learning in Healthcare
- Health Sciences › Health Professions › Health Information Management › Artificial Intelligence in Healthcare
- Health Sciences › Medicine › Health Informatics › Artificial Intelligence in Healthcare and Education
- Keywords
- BERT, contextual embeddings, disease prediction, pre-trained language models, limited training data, fine-tuning, clinical text representation
About these checks
Registry, retraction, Cites and statistics results are computed, not judged, with one exception: a printed reference that no index lists is read once by a model before it counts as a citation error. Claims are extracted by a model and kept only when their quote appears verbatim in the text; each cited source is then checked, with a model’s help, for whether it says what the claim relies on. Those verdicts can be wrong — read the claim’s quote and the cited source before relying on one.
Statistics and arithmetic are recomputed, not judged.
Confidence bands are shown only for fields calibrated on our annotated test set. None is calibrated yet, so no band is shown.
What counts as a claim ›How we measure confidence ›How we check this ›
Are you an author, or do you see a problem with this page? Request a review
How to cite
Cite CoChat for the checks on this page, and the paper for its own findings.
- This page
- CoChat. (2026). Citation check: Med-BERT: pretrained contextualized embeddings on large-scale structured electronic health records for disease prediction. https://app.cochat.ai/papers/10.1038/s41746-021-00455-y
- The paper
- Rasmy, L., Xiang, Y., Xie, Z., Tao, C., & Zhi, D. (2021). Med-BERT: pretrained contextualized embeddings on large-scale structured electronic health records for disease prediction. npj Digital Medicine. https://doi.org/10.1038/s41746-021-00455-y
Data sources
Bibliographic data: Semantic Scholar, OpenAlex, Crossref.
Contains information from the Semantic Scholar Academic Graph Datasets, made available under the ODC Attribution License (ODC-BY 1.0).
Semantic Scholar’s data is described in: Kinney, R., et al. (2023). The Semantic Scholar Open Data Platform. arXiv:2301.10140.
