

The DOI matches its Crossref record; 147 of the 147 references it cites were found in a registry or an index; none of the 168 sources its claims cite is checked for support yet.
The intersocietal IWGDF, ESVS, SVS guidelines on peripheral artery disease in people with diabetes and a foot ulcer
Open accessAbstract
Diabetes related foot complications have become a major cause of morbidity and are implicated in most major and minor amputations globally. Approximately 50% of people with diabetes and a foot ulcer have peripheral artery disease (PAD) and the presence of PAD significantly increases the risk of adverse limb and cardiovascular events. The International Working Group on the Diabetic Foot (IWGDF) has published evidence based guidelines on the management and prevention of diabetes related foot complications since 1999. This guideline is an update of the 2019 IWGDF guideline on the diagnosis, prognosis and management of peripheral artery disease in people with diabetes mellitus and a foot ulcer. For this guideline the IWGDF, the European Society for Vascular Surgery and the Society for Vascular Surgery decided to collaborate to develop a consistent suite of recommendations relevant to clinicians in all countries. This guideline is based on three new systematic reviews. Using the Grading of Recommendations, Assessment, Development, and Evaluation framework clinically relevant questions were formulated, and the literature was systematically reviewed. After assessing the certainty of the evidence, recommendations were formulated which were weighed against the balance of benefits and harms, patient values, feasibility, acceptability, equity, resources required, and when available, costs. Through this process five recommendations were developed for diagnosing PAD in a person with diabetes, with and without a foot ulcer or gangrene. Five recommendations were developed for prognosis relating to estimating likelihood of healing and amputation outcomes in a person with diabetes and a foot ulcer or gangrene. Fifteen recommendations were developed related to PAD treatment encompassing prioritisation of people for revascularisation, the choice of a procedure and post‐surgical care. In addition, the Writing Committee has highlighted key research questions where current evidence is lacking. The Writing Committee believes that following these recommendations will help healthcare professionals to provide better care and will reduce the burden of diabetes related foot complications.
Overview
CoChat Summary
TL;DR
This intersocietal IWGDF/ESVS/SVS guideline updates recommendations for diagnosing, prognosticating, and treating peripheral artery disease (PAD) in people with diabetes and a foot ulcer or gangrene, based on three new systematic reviews and GRADE. It provides 25 recommendations—5 on diagnosis, 5 on prognosis, and 15 on treatment—plus Best Practice Statements and research priorities.
Key findings
- PAD is present in approximately 50% of people with diabetes and a foot ulcer, and its presence substantially increases adverse limb and cardiovascular events; after amputation, up to 50% of people will not survive 5 years.
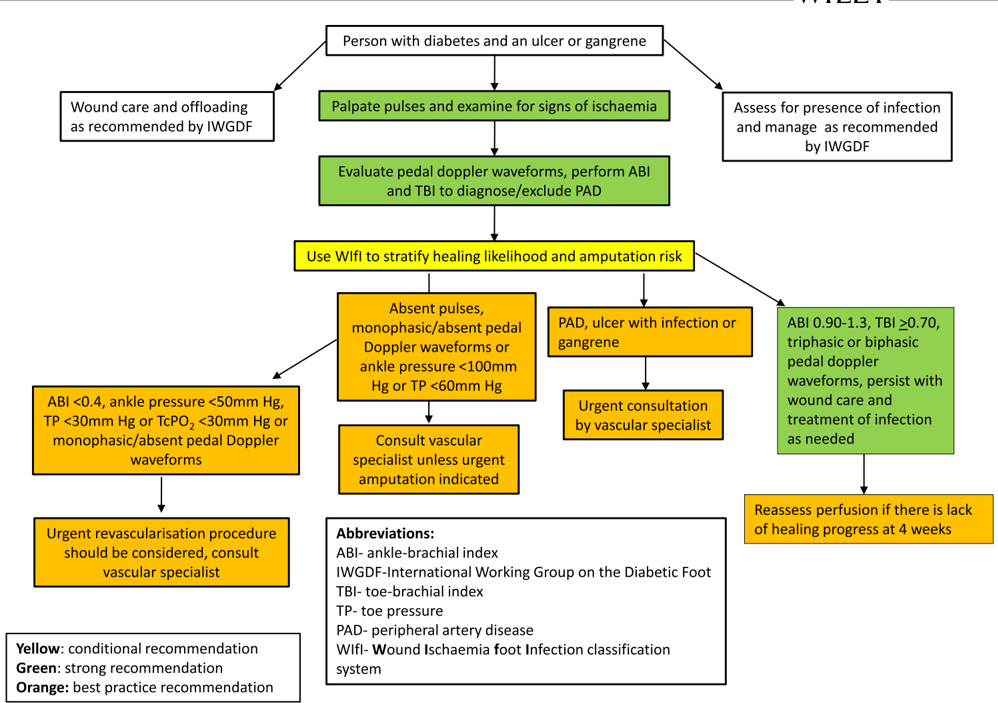
- For diagnosis, no single modality is optimal: PAD is less likely with ABI 0.9–1.3, TBI ≥0.70, and triphasic or biphasic pedal Doppler waveforms; in people with a foot ulcer or gangrene, pedal Doppler waveforms should be evaluated with ABI and TBI.
- For prognosis, toe pressure ≥30 mmHg increases the pre-test probability of healing by up to 30%, while <30 mmHg increases the pre-test probability of major amputation by approximately 20%; TcPO₂ ≥25 mmHg increases healing probability by up to 45%, and SPP ≥40 mmHg by up to 30%.
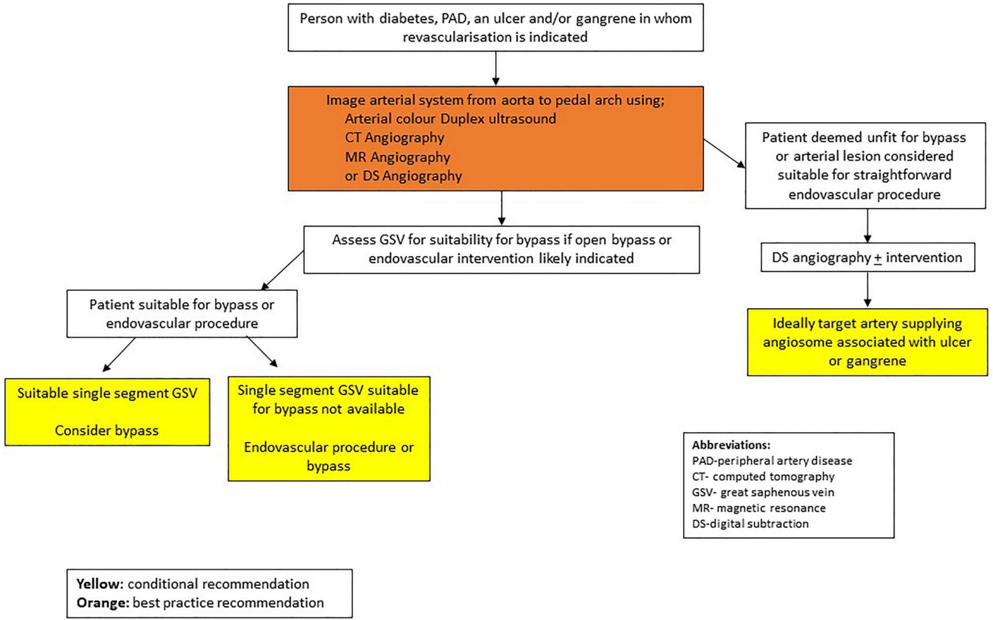
- For treatment, in people with an adequate single-segment saphenous vein and infrainguinal revascularisation indicated, bypass is preferred over endovascular therapy (conditional, moderate); in BEST-CLI, GSV bypass-first was superior for the primary outcome (HR 0.68; 95% CI 0.59–0.79; p < 0.001), with major amputation in 74/709 (10.4%) surgery vs 106/711 (14.9%) endovascular.
Methods
- The IWGDF, ESVS, and SVS collaborated using GRADE; clinical questions were formulated as PICOs, and three new systematic reviews addressed diagnosis, prognosis, and management of PAD in diabetes, following PRISMA.
- The population was people with diabetes with or without a foot ulcer or gangrene; diagnosis compared non-invasive bedside tests with objective imaging, prognosis assessed non-invasive bedside tests, and treatment compared bypass/direct revascularisation with endovascular/indirect revascularisation; outcomes included wound healing, minor and major amputation, adverse events, and limb salvage.
- Evidence quality and risk of bias were assessed with tools including QAREL, ROBINS-I, Newcastle-Ottawa Scale, and Cochrane RoB 2; certainty was rated high, moderate, low, or very low, and recommendations were graded strong or conditional with voting thresholds of ≥75% and ≥60%, respectively; Best Practice Statements were used when direct evidence was lacking.
Limitations
- The paper states a main limitation is the lack of prospective randomised trials, inconsistency of classification and outcomes reporting, and lack of separation of outcomes for people with chronic limb-threatening ischaemia with and without diabetes; high-level evidence for diagnosis and management in people with diabetes-related foot ulcer or gangrene is scarce.
- Many recommendations are based on low-certainty evidence or are ungraded Best Practice Statements/expert opinion; pharmacological recommendations were not based on a new systematic review but adapted from existing guidelines.
- The text makes evident that studies often included people with intact feet or inadequately controlled for confounders such as neuropathy, ulcer, infection, or other contributors to poor outcomes; heterogeneity prevented meta-analysis in places, and bedside tests have wide margins of error (e.g., same-rater ABI requires a change of 0.15 to be considered a true change).
Model-written summary. Check it against the paper before relying on it.
Integrity signals
Registry
Cites
Statistics
Figures
Verification
Claims the paper makes
0 Valid · 21 Not valid · 109 Not checked · 58 Own results and interpretations
The paper states this without a source or data behind it here, so there is nothing to check it against. The quote shows it is in the paper.
In the paper
“However, PAD is less likely in the presence of ABI 0.9-1.3;TBI ≥0.70; and triphasic or biphasic pedal Doppler waveforms”
- Also stated in: § 1.1.4 | Recommendation 4 · hedged
“However, PAD is less likely in the presence of ABI 0.9-1.3;TBI ≥0.70; and triphasic or biphasic pedal Doppler waveforms”
§ The intersocietal IWGDF, ESVS, SVS guidelines on peripheral artery disease in people with diabetes and a foot ulcer > 1.1.2 | Recommendation 2
hedgedstates an association- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: unclear — It is unclear why the paper says it holds.
- Also stated in: § 1.1.4 | Recommendation 4 · hedged
In the paper
“and the presence of a visual monophasic pedal Doppler waveform (compared with a biphasic or triphasic Doppler waveform where the waveform crosses the zero flow baseline and contains both forward and reverse velocity components) 54 has a moderate ability to diagnose and exclude PAD (PLR 7.09, NLR 0.19).”
§ The intersocietal IWGDF, ESVS, SVS guidelines on peripheral artery disease in people with diabetes and a foot ulcer > Rationale
What the sources say
- Not matchedcites [54]
Couldn’t be matched to a paper in Crossref, so it can’t be checked.
plainstates an association- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
- Not matched
In the paper
“Pulse palpation had a PLR of 1.38 and a NLR 0.75 for PAD in people presenting with a foot ulcer.57”
§ The intersocietal IWGDF, ESVS, SVS guidelines on peripheral artery disease in people with diabetes and a foot ulcer > Rationale
What the sources say
- Not matchedcites [57]
Couldn’t be matched to a paper in Crossref, so it can’t be checked.
plainstates an association- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
- Not matched
A result the paper states — it cites no source for it, so there is none to check. The quote shows it is in the paper.
In the paper
“An SPP ≥40 mmHg increases the pre-test probability of healing by up to 30%”
§ The intersocietal IWGDF, ESVS, SVS guidelines on peripheral artery disease in people with diabetes and a foot ulcer > 1.2.3 | Recommendation 8
plainstates a cause- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
In the paper
“it is suggested that PAD is more likely to be present in this population with an ABI <0.9 or >1.3”
§ The intersocietal IWGDF, ESVS, SVS guidelines on peripheral artery disease in people with diabetes and a foot ulcer > Rationale
What the sources say
- Not matchedcites [5]
Couldn’t be matched to a paper in Crossref, so it can’t be checked.
hedgedstates an association- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
- Not matched
101 more claims
Create a free account to see all 188 claims and every source verdict.
- It may state two separate claims as one. 57
- The quote only partly states this claim. 1
- Probably not a substantial claim. 35
Self-check
Percentages, sums and reported differences re-computed from the paper’s own numbers.
Each contradiction between two passages listed here was confirmed by an independent check.
Rated major: it would touch a result — a value a result rests on, reported and recomputed p-values on opposite sides of the significance level, two passages that conflict with no sign which is right, or a cited work retracted before this paper was published.
In the paper
“The ADA and EASD guidelines recommend in persons with diabetes and atherosclerotic cardiovascular disease an LDL target of <1.8 mmol/L (70 mmol/L).21”
§ The intersocietal IWGDF, ESVS, SVS guidelines on peripheral artery disease in people with diabetes and a foot ulcer > Lipid goals
Reported 70 · recomputed 38.888889
Rated minor: it would not touch a result — a value no result rests on, a p-value that stays on the same side of the significance level, or a conflict that is clerical, resolved elsewhere in the paper, or outside its own findings.
In the paper
§ The intersocietal IWGDF, ESVS, SVS guidelines on peripheral artery disease in people with diabetes and a foot ulcer > 2 | EXTERNAL EXPERTS, PATIENT REPRESENTATIVES AND REVIEW PROCESS
“in which six external experts, four patient representatives and guideline reviewers of the International Working Group on the Diabetic Foot (IWGDF), European Society for Vascular Surgery (ESVS) and Society for Vascular Surgery (SVS) were involved.”
§ The intersocietal IWGDF, ESVS, SVS guidelines on peripheral artery disease in people with diabetes and a foot ulcer > AUTHOR CONTRIBUTIONS
“document: Sriram Narayanan (Singapore), Rica Tanaka (Japan), Ismail Cassimjee (South Africa), Xu Jun (China), Heidi Corcoran (Hong Kong), Yamile Jubiz (Colombia), Tsvetalina Tankova (Bulgaria) and our patient representatives.”
Citations
Cites
Preferred Reporting Items for Systematic Reviews and Meta-Analyses: the PRISMA statement
Moher, D., Liberati, A., Tetzlaff, J., Altman, D. G., & for the PRISMA Group (2009) · BMJ · doi:10.1136/bmj.b2535 · Cited by 83,823
RoB 2: a revised tool for assessing risk of bias in randomised trials
Sterne, J. A. C., Savović, J., Page, M. J., Elbers, R. G., Blencowe, N. S., Boutron, I., Cates, C. J., Cheng, H.-Y., Corbett, M. S., Eldridge, S. M., et al. (2019) · BMJ · doi:10.1136/bmj.l4898 · Cited by 34,787
ROBINS-I: a tool for assessing risk of bias in non-randomised studies of interventions
Sterne, J. A., Hernán, M. A., Reeves, B. C., Savović, J., Berkman, N. D., Viswanathan, M., Henry, D., Altman, D. G., Ansari, M. T., Boutron, I., et al. (2016) · BMJ · doi:10.1136/bmj.i4919 · Cited by 20,329
(2014) · Medical Entomology and Zoology · Cited by 17,633
QUADAS-2: a revised tool for the quality assessment of diagnostic accuracy studies
Whiting, P. F., Rutjes, A. W. S., Westwood, M. E., Mallett, S., Deeks, J. J., Reitsma, J. B., Leeflang, M. M. G., Sterne, J. A. C., Bossuyt, P. M. M., & the QUADAS-2 Group* (2011) · Annals of Internal Medicine · doi:10.7326/0003-4819-155-8-201110180-00009 · Cited by 14,199
Sun, H., Saeedi, P., Karuranga, S., Pinkepank, M., Ogurtsova, K., Duncan, B. B., Stein, C., Basit, A., Chan, J. C. N., Mbanya, J. C., et al. (2022) · Diabetes Research and Clinical Practice · doi:10.1016/j.diabres.2021.109119 · Cited by 10,123
Self-citationMach, F., Baigent, C., Catapano, A. L., Koskinas, K. C., Casula, M., Badimon, L., Chapman, M. J., De Backer, G. G., Delgado, V., Ference, B. A., et al. (2020) · European Heart Journal · doi:10.1093/eurheartj/ehz455 · Cited by 8,961
(1996) · The Lancet · doi:10.1016/s0140-6736(96)09457-3 · Cited by 6,503
Cosentino, F., Grant, P. J., Aboyans, V., Bailey, C. J., Ceriello, A., Delgado, V., Federici, M., Filippatos, G., Grobbee, D. E., Hansen, T. B., et al. (2020) · European Heart Journal · doi:10.1093/eurheartj/ehz486 · Cited by 4,763
Diabetic foot ulcers and their recurrence
Armstrong, D. G., Boulton, A. J. M., & Bus, S. A. (2017) · New England Journal of Medicine · doi:10.1056/nejmra1615439 · Cited by 4,376
Research works printed but not linked: 4
- Schünemann H, 2013, The GRADE Handbook
- 10.1093/eurheartj/ehx095 · DOI · Paper page
- National Institute for Health and Care Excellence, 2023, Guidelines. Diabetic Foot Problems: Prevention and Management
- 10.1067/mva.1985.avs0020536 · DOI
Cited by
Schaper, N. C., van Netten, J. J., Apelqvist, J., Bus, S. A., Fitridge, R., Game, F., Monteiro‐Soares, M., Senneville, E., & the IWGDF Editorial Board (2024) · Diabetes/Metabolism Research and Reviews · doi:10.1002/dmrr.3657 · Cited by 583
Self-citationSenneville, É., Albalawi, Z., van Asten, S. A., Abbas, Z. G., Allison, G., Aragón‐Sánchez, J., Embil, J. M., Lavery, L. A., Alhasan, M., Oz, O., et al. (2024) · Diabetes/Metabolism Research and Reviews · doi:10.1002/dmrr.3687 · Cited by 498
Guidelines on the prevention of foot ulcers in persons with diabetes (IWGDF 2023 update)
Bus, S. A., Sacco, I. C. N., Monteiro‐Soares, M., Raspovic, A., Paton, J., Rasmussen, A., Lavery, L. A., & van Netten, J. J. (2024) · Diabetes/Metabolism Research and Reviews · doi:10.1002/dmrr.3651 · Cited by 279
12. Retinopathy, Neuropathy, and Foot Care: Standards of Care in Diabetes—2026
Bajaj, M. S., McCoy, R. G., Balapattabi, K., Bannuru, R. R., Bellini, N. J., Bennett, A. K., Beverly, E. A., Early, K. B., Callaghan, B. C., ChallaSivaKanaka, S., et al. (2025) · Diabetes Care · doi:10.2337/dc26-s012 · Cited by 175
Guidelines on the classification of foot ulcers in people with diabetes (IWGDF 2023 update).
Monteiro‐Soares, M., Hamilton, E. J., Russell, D. A., Srisawasdi, G., Boyko, E. J., Mills, J. L., Jeffcoate, W., & Game, F. (2024) · Diabetes/Metabolism Research and Reviews · doi:10.1002/dmrr.3648 · Cited by 152
Self-citation
Metadata
- Authors
- Fitridge, R., Chuter, V., Mills, J., Hinchliffe, R., Azuma, N., Behrendt, C., Boyko, E. J., Conte, M. S., Humphries, M., Kirksey, L., McGinigle, K. C., Nikol, S., Nordanstig, J., Rowe, V., Russell, D., van den Berg, J. C., Venermo, M., & Schaper, N.
- Affiliations
- Royal Adelaide Hospital (AU)
- Western Sydney University (AU)
- Baylor College of Medicine (US)
- University of Bristol (GB)
- Asahikawa Medical University (JP)
- Asklepios (DE)
- University of Washington (US)
- University of California, San Francisco (US)
- University of California Davis Medical Center (US)
- Cleveland Clinic (US)
- University of North‐Carolina Chapel Hill North Carolina USA
- Asklepios Klinik St. Georg (DE)
- Sahlgrenska University Hospital (SE)
- University of California, Los Angeles (US)
- Leeds Teaching Hospitals NHS Trust (GB)
- University Hospital of Bern (CH)
- University of Helsinki (FI)
- Maastricht University Medical Centre (NL)
- Corresponding author
- Fitridge, Robert
- ORCID
- Venue
- Diabetes/Metabolism Research and Reviews
- Publisher
- Wiley
- Published
- 2023-09-19
- Volume
- 40
- Issue
- 3
- Pages
- e3686-e3686
- ISSN
- 1520-7552 (ISSN-L)
- 1520-7560
- OpenAlex
- W4386877653
- Cited by
- 201
- References
- 147
- Citations by year
- 2026: 114 · 2025: 54 · 2024: 24 · 2023: 9
- FWCI
- 42.87
- Type
- journal article
- Language
- en
- Open access
- hybrid
- doi.org
- Licence
- Locations
- Diabetes/Metabolism Research and Reviews (publishedVersion, cc-by)
- PubMed (publishedVersion)
- BORIS (University Library Bern) (submittedVersion, cc-by)
- Research Publications (Maastricht University) (submittedVersion, cc-by)
- Työväentutkimus Vuosikirja (submittedVersion)
- Open Access CRIS of the University of Bern
- Topics
- Health Sciences › Medicine › Surgery › Peripheral Artery Disease Management
- Health Sciences › Medicine › Endocrinology, Diabetes and Metabolism › Diabetic Foot Ulcer Assessment and Management
- Health Sciences › Medicine › Pulmonary and Respiratory Medicine › Vascular Procedures and Complications
- Keywords
- peripheral arterial disease, diabetes mellitus, diabetic foot ulcer, diabetic foot complications, revascularization, amputation risk, gangrene, vascular surgery, cardiovascular risk
- MeSH terms
- Diabetes Mellitus, Gangrene, Humans, Foot Ulcer, Diabetic Foot, Lower Extremity, Peripheral Arterial Disease
About these checks
Registry, retraction, Cites and statistics results are computed, not judged, with one exception: a printed reference that no index lists is read once by a model before it counts as a citation error. Claims are extracted by a model and kept only when their quote appears verbatim in the text; each cited source is then checked, with a model’s help, for whether it says what the claim relies on. Those verdicts can be wrong — read the claim’s quote and the cited source before relying on one.
A language model drew the claims from the paper on 2026-11-13, under version 3 of the claim definition (model deepseek-v4.1-flash, prompt extract-v3).
A second model labelled each claim on 2026-11-13 (model jev-1.13-20260917, definition revision gold-guideline-v0.2).
Statistics and arithmetic are recomputed, not judged.
Confidence bands are shown only for fields calibrated on our annotated test set. None is calibrated yet, so no band is shown.
What counts as a claim ›How we measure confidence ›How we check this ›
Are you an author, or do you see a problem with this page? Request a review
Data sources
Bibliographic data: Semantic Scholar, OpenAlex, Crossref.
Contains information from the Semantic Scholar Academic Graph Datasets, made available under the ODC Attribution License (ODC-BY 1.0).
Semantic Scholar’s data is described in: Kinney, R., et al. (2023). The Semantic Scholar Open Data Platform. arXiv:2301.10140.
