

The DOI matches its Crossref record; 35 of the 35 references it cites were found in a registry or an index.
Endocrine and haemodynamic changes in resistant hypertension, and blood pressure responses to spironolactone or amiloride: the PATHWAY-2 mechanisms substudies
Open accessAbstract
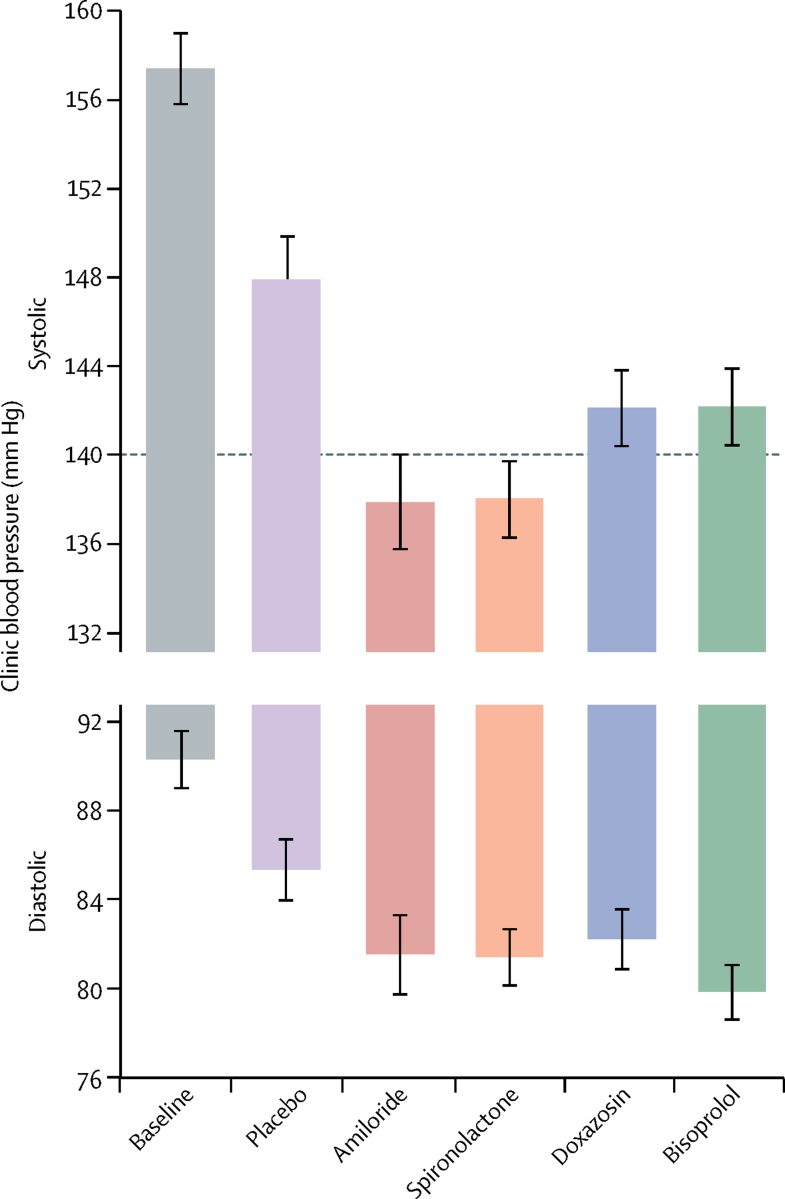
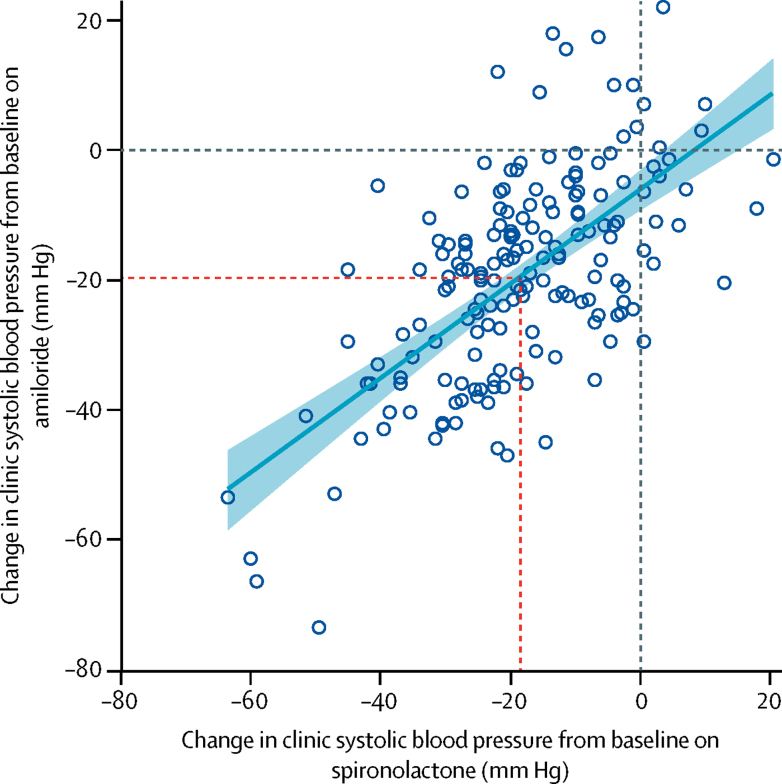
BACKGROUND: In the PATHWAY-2 study of resistant hypertension, spironolactone reduced blood pressure substantially more than conventional antihypertensive drugs. We did three substudies to assess the mechanisms underlying this superiority and the pathogenesis of resistant hypertension. METHODS: PATHWAY-2 was a randomised, double-blind crossover trial done at 14 UK primary and secondary care sites in 314 patients with resistant hypertension. Patients were given 12 weeks of once daily treatment with each of placebo, spironolactone 25-50 mg, bisoprolol 5-10 mg, and doxazosin 4-8 mg and the change in home systolic blood pressure was assessed as the primary outcome. In our three substudies, we assessed plasma aldosterone, renin, and aldosterone-to-renin ratio (ARR) as predictors of home systolic blood pressure, and estimated prevalence of primary aldosteronism (substudy 1); assessed the effects of each drug in terms of thoracic fluid index, cardiac index, stroke index, and systemic vascular resistance at seven sites with haemodynamic monitoring facilities (substudy 2); and assessed the effect of amiloride 10-20 mg once daily on clinic systolic blood pressure during an optional 6-12 week open-label runout phase (substudy 3). The PATHWAY-2 trial is registered with EudraCT, number 2008-007149-30, and ClinicalTrials.gov, number NCT02369081. FINDINGS: =0·11, p=0·00024). 42 patients had low renin concentrations (predefined as the lowest tertile of plasma renin), of which 31 had a plasma aldosterone concentration greater than the mean value for all 126 patients (250 pmol/L). Thus, 31 (25% [95% CI 17-33]) of 126 patients were deemed to have inappropriately high aldosterone concentrations. Thoracic fluid content was reduced by 6·8% from baseline (95% CI 4·0 to 8·8; p<0·0001) with spironolactone, but not other treatments. Amiloride (10 mg once daily) reduced clinic systolic blood pressure by 20·4 mm Hg (95% CI 18·3-22·5), compared with a reduction of 18·3 mm Hg (16·2-20·5) with spironolactone (25 mg once daily). No serious adverse events were recorded, and adverse symptoms were not systematically recorded after the end of the double-blind treatment. Mean plasma potassium concentrations increased from 4·02 mmol/L (95% CI 3·95-4·08) on placebo to 4·50 (4·44-4·57) on amiloride (p<0·0001). INTERPRETATION: Our results suggest that resistant hypertension is commonly a salt-retaining state, most likely due to inappropriate aldosterone secretion. Mineralocorticoid receptor blockade by spironolactone overcomes the salt retention and resistance of hypertension to treatment. Amiloride seems to be as effective an antihypertensive as spironolactone, offering a substitute treatment for resistant hypertension. FUNDING: British Heart Foundation and UK National Institute for Health Research.
Overview
The claims and statistics of this paper haven’t been checked yet.
Run the check — free, no account needed. It reads the open-access text and checks the sources it cites.
Integrity signals
Registry
Cites
Statistics
Figures
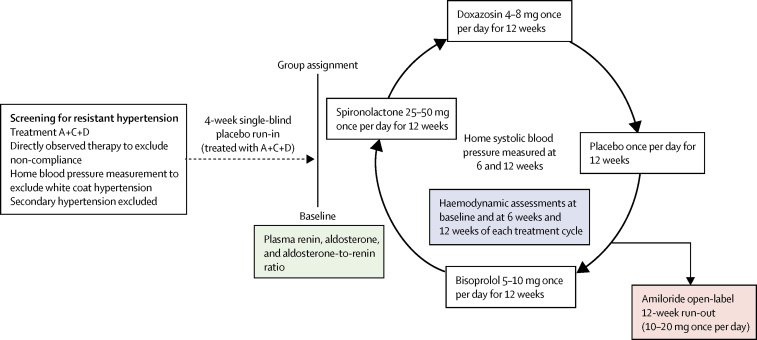
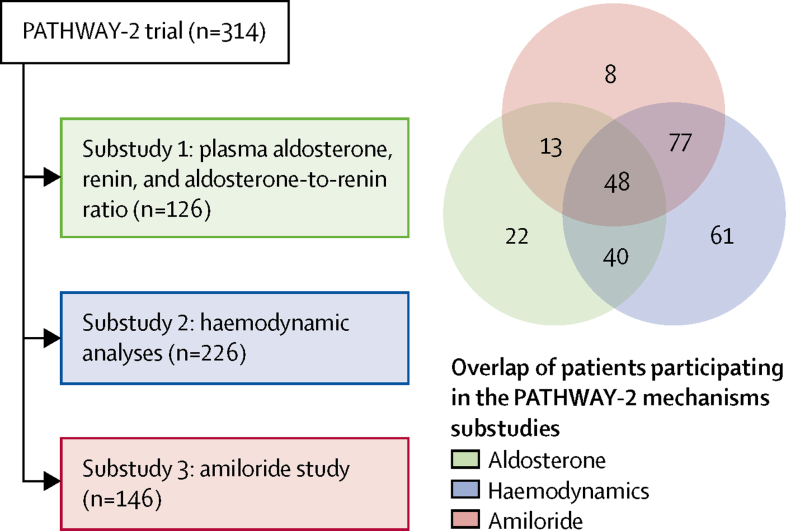
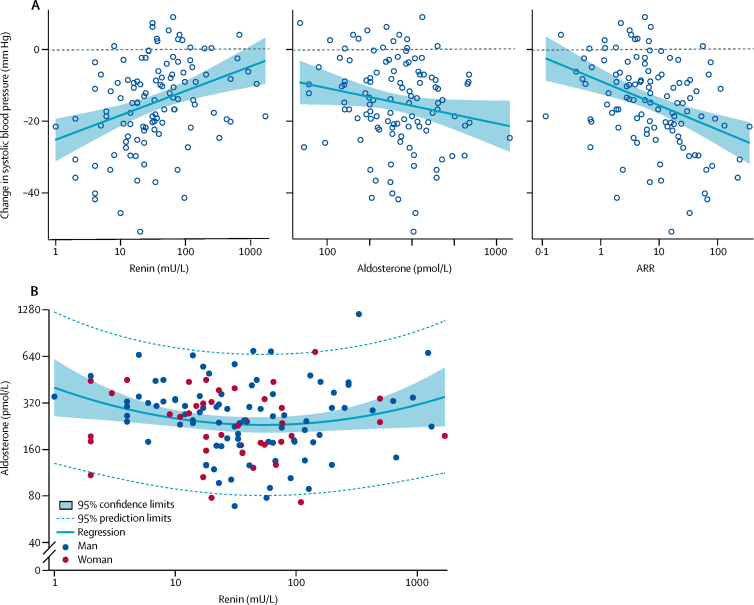
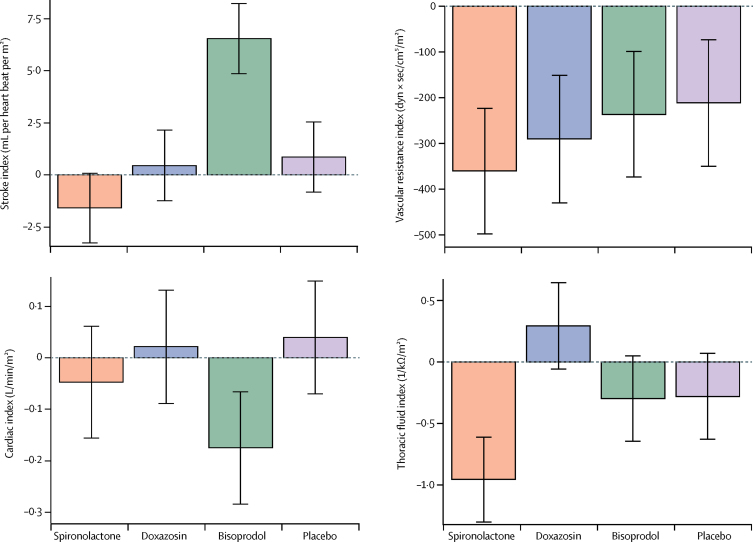
Verification
Claims the paper makes
The claims and statistics of this paper haven’t been checked yet.
Run the check — free, no account needed. It reads the open-access text and checks the sources it cites.
Claims other papers make about this one
Each is checked against this paper’s own text: does it say what the citing paper says it does?
The source backs part of the claim, not all of it — or backs it for a different population, condition or comparison.
In the citing paper
“The landmark PATHWAY-2 trial85,86 clearly established that the MR antagonist spironolactone is effective for treating patients with resistant hypertension who are usually overweight or obese and already on at least three antihypertensive drugs87.”
From Obesity, kidney dysfunction and hypertension: mechanistic links (2019) · cites this paper as [85]
Experimental — accuracy not yet measured
Self-check
Percentages, sums and reported differences re-computed from the paper’s own numbers.
The self-check needs the paper’s full text.
Citations
Cites
Funder, J. W., Carey, R. M., Mantero, F., Murad, M. H., Reincke, M., Shibata, H., Stowasser, M., & Young, W. F. (2016) · The Journal of Clinical Endocrinology & Metabolism · doi:10.1210/jc.2015-4061 · Cited by 2,925
A prospective study of the prevalence of primary aldosteronism in 1,125 hypertensive patients
Rossi, G. P., Bernini, G., Caliumi, C., Desideri, G., Fabris, B., Ferri, C., Ganzaroli, C., Giacchetti, G., Letizia, C., Maccario, M., et al. (2006) · Journal of the American College of Cardiology · doi:10.1016/j.jacc.2006.07.059 · Cited by 1,467
Williams, B., MacDonald, T. M., Morant, S., Webb, D. J., Sever, P., McInnes, G., Ford, I., Cruickshank, J. K., Caulfield, M. J., Salsbury, J., et al. (2015) · The Lancet · doi:10.1016/s0140-6736(15)00257-3 · Cited by 1,308
Self-citationEssential Hypertension: Renin and Aldosterone, Heart Attack and Stroke
Brunner, H. R., Laragh, J. H., Baer, L., Newton, M. A., Goodwin, F. T., Krakoff, L. R., Bard, R. H., & Bühler, F. R. (1972) · New England Journal of Medicine · doi:10.1056/nejm197203022860901 · Cited by 1,091
Prevalence and Clinical Manifestations of Primary Aldosteronism Encountered in Primary Care Practice
Monticone, S., Burrello, J., Tizzani, D., Bertello, C., Viola, A., Buffolo, F., Gabetti, L., Mengozzi, G., Williams, T. A., Rabbia, F., et al. (2017) · Journal of the American College of Cardiology · doi:10.1016/j.jacc.2017.01.052 · Cited by 888
Δούμα, Σ., Petidis, K., Doumas, M. N., Papaefthimiou, P., Triantafyllou, Α., Kartali, N., Papadopoulos, N., Vogiatzis, K., & Zamboulis, C. (2008) · The Lancet · doi:10.1016/s0140-6736(08)60834-x · Cited by 563
Somatic mutations in ATP1A1 and CACNA1D underlie a common subtype of adrenal hypertension
Azizan, E. A. B., Poulsen, H., Tuluc, P., Zhou, J., Clausen, M. V., Lieb, A., Maniero, C., Garg, S., Bochukova, E. G., Zhao, W., et al. (2013) · Nature Genetics · doi:10.1038/ng.2716 · Cited by 544
Self-citationTomaszewski, M., White, C., Patel, P., Masca, N., Damani, R., Hepworth, J., Samani, N. J., Gupta, P., Madira, W., Stanley, A., et al. (2014) · Heart · doi:10.1136/heartjnl-2013-305063 · Cited by 404
Self-citationOptimisation of antihypertensive treatment by crossover rotation of four major classes
Dickerson, J. E. C., Hingorani, A. D., Ashby, M. J., Palmer, C. R., & Brown, M. J. (1999) · The Lancet · doi:10.1016/s0140-6736(98)07614-4 · Cited by 343
Self-citationAldosterone-stimulating somatic gene mutations are common in normal adrenal glands
Nishimoto, K., Tomlins, S. A., Kuick, R. D., Cani, A. K., Giordano, T. J., Hovelson, D. H., Liu, C., Sanjanwala, A. R., Edwards, M. A., Gómez-Sánchez, C. E., et al. (2015) · Proceedings of the National Academy of Sciences · doi:10.1073/pnas.1505529112 · Cited by 337
Cited by
Sorted by citations
2018 ESC/ESH Guidelines for the management of arterial hypertension
Williams, B., Mancia, G., Spiering, W., Agabiti Rosei, E., Azizi, M., Burnier, M., Clement, D. L., Coca, A., de Simone, G., Dominiczak, A., et al. (2018) · European Heart Journal · doi:10.1093/eurheartj/ehy339 · Cited by 10,286
Self-citation2021 ESC Guidelines on cardiovascular disease prevention in clinical practice
Visseren, F. L. J., Mach, F., Smulders, Y. M., Carballo, D., Koskinas, K. C., Bäck, M., Benetos, A., Biffi, A., Boavida, J.-M., Capodanno, D., et al. (2021) · European Heart Journal · doi:10.1093/eurheartj/ehab484 · Cited by 6,485
Self-citation2020 International Society of Hypertension Global Hypertension Practice Guidelines
Unger, T., Borghi, C., Charchar, F., Khan, N. A., Poulter, N. R., Prabhakaran, D., Ramirez, A., Schlaich, M., Stergiou, G. S., Tomaszewski, M., et al. (2020) · Hypertension · doi:10.1161/hypertensionaha.120.15026 · Cited by 4,132
Self-citationMancia, G., Kreutz, R., Brunström, M., Burnier, M., Grassi, G., Januszewicz, A., Muiesan, M. L., Tsioufis, K., Agabiti-Rosei, E., Algharably, E. A. E., et al. (2023) · Journal of Hypertension · doi:10.1097/hjh.0000000000003480 · Cited by 3,473
Self-citationWilliams, B., Mancia, G., Spiering, W., Agabiti Rosei, E., Azizi, M., Burnier, M., Clement, D. L., Coca, A., de Simone, G., Dominiczak, A., et al. (2018) · Journal of Hypertension · doi:10.1097/hjh.0000000000001940 · Cited by 2,885
Self-citation
Metadata
- Authors
- Williams, B., MacDonald, T. M., Morant, S. V., Webb, D. J., Sever, P., McInnes, G. T., Ford, I., Cruickshank, J. K., Caulfield, M. J., Padmanabhan, S., Mackenzie, I. S., Salsbury, J., Brown, M. J., Balakrishnan, K., Burton, T., Cannon, J., Collier, D., Coughlan, C., D'Souza, R., Enobakhare, E., Findlay, E., Gardiner-Hill, C., Gupta, P., Helmy, J., Helmy, C., Hobbs, L., Hobbs, R., Hood, S., Iles, R., Kean, S., Kwok, S., Lacy, P., MacIntyre, I., Mackay, J., Markandu, N., Martin, U., McCallum, L., McCann, G., McGinnis, A., Melville, V, Muir, S., Myint, K., Nazir, S., Palmer, J., Papworth, R., Rutkowski, K., Saxena, M., Schumann, A., Soran, H., Stanley, A., Thom, S., Webb, A., White, C., Wilson, R., & Zak, A.
- Affiliations
- National Institute for Health and Care Research (GB)
- University of Dundee (GB)
- The Queen's Medical Research Institute (GB)
- Imperial College London (GB)
- University of Glasgow (GB)
- King's College London (GB)
- Queen Mary University of London (GB)
- University of London (GB)
- Corresponding author
- Brown, Morris J
- Cannon, J
- D'Souza, R
- Helmy, J
- Hobbs, R
- Iles, R
- Mackay, J
- Markandu, N
- Palmer, J
- Papworth, R
- Wilson, R
- ORCID
- Williams, Bryan
- MacDonald, Thomas M
- Morant, Steve V
- Webb, David J
- Ford, Ian
- Cruickshank, J Kennedy
- Caulfield, Mark J
- Padmanabhan, Sandosh
- Mackenzie, Isla S
- Brown, Morris J
- Burton, T
- Collier, D
- Coughlan, C
- D'Souza, R
- Gupta, P
- Hobbs, R
- Iles, R
- Kean, S
- Kwok, S
- Lacy, P
- MacIntyre, I
- Martin, U
- McCallum, L
- McCann, G
- Papworth, R
- Schumann, A
- Soran, H
- Stanley, A
- Thom, S
- Venue
- The Lancet Diabetes & Endocrinology
- Publisher
- Elsevier BV
- Published
- 2018-06
- Volume
- 6
- Issue
- 6
- Pages
- 464-475
- ISSN
- 2213-8587 (ISSN-L)
- PMC
- PMC5966620
- OpenAlex
- W2796868581
- Cited by
- 347
- References
- 35
- Citations by year
- 2026: 39 · 2025: 42 · 2024: 29 · 2023: 48 · 2022: 42 · 2021: 40 · 2020: 48 · 2019: 36 · 2018: 14
- FWCI
- 27.46
- Type
- journal article
- Language
- en
- Open access
- hybrid
- doi.org
- Licence
- Locations
- The Lancet Diabetes & Endocrinology (publishedVersion, cc-by)
- PubMed Central (publishedVersion, cc-by)
- PubMed (publishedVersion)
- Discovery Research Portal (University of Dundee) (publishedVersion, cc-by)
- Edinburgh Research Explorer (University of Edinburgh) (publishedVersion, cc-by)
- ENLIGHTEN (Jurnal Bimbingan dan Konseling Islam) (acceptedVersion, cc-by-sa)
- Research Portal (King's College London) (submittedVersion, cc-by)
- UCL Discovery (University College London) (submittedVersion)
- Queen Mary Research Online (Queen Mary University of London) (submittedVersion, cc-by)
- Queen Mary Research Online (Queen Mary University of London) (submittedVersion)
- Spiral (Imperial College London) (submittedVersion, cc-by)
- Funders
- National Institute for Health and Care Research
- British Heart Foundation (SP/08/002)
- NIHR Barts Biomedical Research Centre, Queen Mary University of London
- Topics
- Health Sciences › Medicine › Endocrinology, Diabetes and Metabolism › Hormonal Regulation and Hypertension
- Health Sciences › Medicine › Cardiology and Cardiovascular Medicine › Blood Pressure and Hypertension Studies
- Health Sciences › Medicine › Cardiology and Cardiovascular Medicine › Renin-Angiotensin System Studies
- Keywords
- resistant hypertension, spironolactone, amiloride, aldosterone, renin, aldosterone-renin ratio, primary aldosteronism, hemodynamics, systemic vascular resistance, bisoprolol, doxazosin, blood pressure response, low-renin hypertension
- MeSH terms
- Aldosterone, Amiloride, Antihypertensive Agents, Blood Pressure, Female, Hemodynamics, Humans, Hypertension, Male, Middle Aged, Spironolactone, Randomized Controlled Trials as Topic, Doxazosin, Bisoprolol
About these checks
Registry, retraction, Cites and statistics results are computed, not judged, with one exception: a printed reference that no index lists is read once by a model before it counts as a citation error. Claims are extracted by a model and kept only when their quote appears verbatim in the text; each cited source is then checked, with a model’s help, for whether it says what the claim relies on. Those verdicts can be wrong — read the claim’s quote and the cited source before relying on one.
Statistics and arithmetic are recomputed, not judged.
Confidence bands are shown only for fields calibrated on our annotated test set. None is calibrated yet, so no band is shown.
What counts as a claim ›How we measure confidence ›How we check this ›
Are you an author, or do you see a problem with this page? Request a review
