

The DOI matches its Crossref record; 122 of the 122 references it cites were found in a registry or an index; 2 of the 76 sources its claims cite were checked for support.
Diagnosis and management of treatment-refractory hypothyroidism: an expert consensus report
Open accessAbstract
There is a frequently encountered subset of hypothyroid patients who are refractory to standard thyroid hormone replacement treatment and require unexpectedly high doses of levothyroxine. In addition to clinical situations where hypothyroid patients are non-compliant, or where there is the possibility of excipient-induced disease exacerbation (gluten/celiac disease), therapeutic failure may be due to impaired absorption of the administered drug. The common approach to managing patients with unusual thyroxine needs is to escalate the dose of levothyroxine until targeted TSH levels are achieved. This approach can increase the risk for prolonged exposure to supratherapeutic doses of levothyroxine, which increase the chances of adverse outcomes. Repeated adjustments of levothyroxine can also escalate the costs of treatment, as frequent office visits and laboratory tests are required to determine and maintain the desired dose. Clinicians should take a systematic approach to managing patients whom they suspect of having treatment-refractory hypothyroidism. This may include searching for, and adjusting, occult medical conditions and/or other factors that may affect the absorption of levothyroxine, before up-titrating the dose of traditional levothyroxine therapy. Depending on the underlying pathology, another approach that may be considered is to try alternative formulations of levothyroxine that are less susceptible to intolerance issues related to excipients, or, in some cases, to malabsorption. The early discovery of these factors via a thoughtful patient work-up may avoid unnecessary thyroid medication adjustments and their consequences for both patients and clinicians.
Overview
AI snapshot
Written from the paper’s full text.
TL;DR
This expert consensus report reviews treatment-refractory hypothyroidism, defined as biochemical or clinical hypothyroidism despite levothyroxine doses beyond 1.9 μg/kg daily and/or TSH above the upper target, usually 4.5 mU/L after a 6-week interval following the last dose increase. It recommends a systematic eight-step work-up for compliance, absorption, interfering conditions, and alternative levothyroxine formulations before further dose escalation.
Key findings
- Refractory hypothyroidism is defined by TSH above the upper target (usually 4.5 mU/L after a 6-week interval after the last dosage increase) and/or unresolved hypothyroid symptoms despite levothyroxine doses beyond 1.9 μg/kg daily.
- Non-optimal thyroxine therapy is common: in five published studies, non-optimal therapy ranged from 32% to 48%; in a Brazilian multicenter study, 28% of 2292 hypothyroid patients had elevated TSH while on thyroid hormone therapy.
- Causes include non-compliance, generic levothyroxine substitution, GI disease/malabsorption (e.g., *H. pylori*, IBD, celiac disease, lactose intolerance, atrophic body gastritis, gastric bypass), PPIs, pregnancy, weight change, drugs increasing thyroxine turnover, Addison’s disease, and anti-thyroxine antibodies; 10–20% of cases remain idiopathic despite extensive work-up.
- Alternative formulations may help: in CONTROL Switch (99 patients), switching to levothyroxine gel caps reduced dose adjustments by 55% (P < 0.0001), with >85% experiencing ≤1 dose adjustment post-switch, and improved symptom control by 62% (P < 0.0001); in a liquid-formulation study of 152 patients, TSH declined at first (P < 0.05) and second control (P < 0.01), with FT4 and FT3 unchanged.
Methods
- Expert consensus report/narrative review; no systematic review, meta-analysis, or primary data collection is described. Evidence is drawn from published literature and the panel’s clinical experience.
- The paper synthesizes prior studies and proposes an eight-step diagnostic and management approach, including confirming diagnosis, assessing compliance, checking medication bottles/tablets, reviewing ingestion history, investigating malabsorption, considering increased turnover/excretion, performing a thyroxine absorption test when appropriate, and treating holistically.
Limitations
- The paper states that the prevalence of refractory hypothyroidism has not been precisely documented; the thyroxine absorption test is not standardized and should not be used routinely; and the benefits of combined T4/T3 therapy remain controversial.
- The paper notes controversy about whether long-term levothyroxine at suppressive or non-suppressive levels increases osteoporosis/fracture risk and calls for comprehensive definitive research.
- Evident from the text: this is an expert consensus report without a described systematic literature search, formal evidence grading, or prospective validation of the recommended eight-step algorithm.
Model-written summary. Check it against the paper before relying on it.
Integrity signals
Registry
Cites
Statistics
Figures
Verification
Claims the paper makes
35 Not checked yet · 9 Own interpretation · 1 Supported · 1 Partly supported · 1 No basis given · accuracy not yet measured
The cited sources support only part of this claim — read each source’s verdict below.
In the paper
“Frequently, correction of the malabsorption will normalize, or at least improve, levothyroxine absorption in patients with these disorders [10].”
§ Diagnosis and management of treatment-refractory hypothyroidism: an expert consensus report > Diagnosing and managing refractory hypothyroidism > Key principle
What the sources say
- Partly supportedcites [10] Centanni M (2013) Thyroxine treatment: absorption, malabsorption, and novel therapeutic approaches. Endocrine 43:8–9 sourceExperimental — accuracy not yet measured
The paper’s discussion of gastrointestinal disorders (section and page unavailable in our copy) says these conditions can impair levothyroxine absorption and that a different T4 formulation may improve it. It does not say that correcting the underlying malabsorption frequently normalizes or improves absorption; its proposed benefit concerns changing the formulation. (LLM, conf=0.81)
plainconditional- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
- Partly supported
Every source the paper cites for this claim was checked and supports it.
In the paper
“Among patients switched for efficacy reasons (n = 25), 64% experienced improved symptom control.”
§ Diagnosis and management of treatment-refractory hypothyroidism: an expert consensus report > Diagnosing and managing refractory hypothyroidism > Alternative levothyroxine formulations
What the sources say
- Supportedcites [122] Ernst FR, Sandulli W, Elmor R et al (2017) Retrospective study of patients switched from tablet formulations to a gel cap formulation of levothyroxine: results of the CONTROL Switch study. Drugs R D 17:103–115 source
The Results section, “Patients Switched for Efficacy Reasons Only—Symptom Control,” reports physician-reported improvement in hypothyroid symptoms for 64% (16/25) of patients switched for efficacy reasons. This matches the cited claim. (LLM, conf=0.95)
plainn = 25- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
- Supported
In the paper
“Suzuki and colleagues reported failure to identify a cause in approximately 10–20% of patients requiring greater than standard replacement doses of levothyroxine despite an extensive diagnostic work-up”
§ Diagnosis and management of treatment-refractory hypothyroidism: an expert consensus report > Unknown reasons for refractory hypothyroidism
What the sources say
- Not checked yetcites [89] Suzuki Y, Takeshita E, Kano S, Hirata S, Sato S (1982) Impaired intestinal absorption of thyroid hormone in a case of Hashimoto’s disease with anti-T3 and anti-T4 antibody. Nihon Naibunpi Gakkai Zasshi 58:1487–1497
plain- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: unclear — It is unclear whether the paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
None of the sources cited for this claim have been checked yet.
In the paper
“Even though its prevalence has not been precisely documented, non-optimal thyroxine therapy, as evidenced by TSH levels above (or below) the reference range, is common (Table 2)”
§ Diagnosis and management of treatment-refractory hypothyroidism: an expert consensus report > Background
What the sources say
- Not checked yetcites [11] Ross DS, Daniels GH, Gouveia D (1990) The use and limitations of a chemiluminescent thyrotropin assay as a single thyroid function test in an out-patient endocrine clinic. J Clin Endocrinol Metab 71:764–769 source
- Not checked yetcites [12] Parle JV, Franklyn JA, Cross KW, Jones SR, Sheppard MC (1993) Thyroxine prescription in the community: serum thyroid stimulating hormone level assays as an indicator of undertreatment or overtreatment. Br J Gen Pract 43:107–109
- Not checked yetcites [13] Canaris GJ, Manowitz NR, Mayor G, Ridgway EC (2000) The colorado thyroid disease prevalence study. Arch Intern Med 160:526–534 source
- Not checked yetcites [14] Hollowell JG, Staehling NW, Flanders WD et al (2002) Serum TSH, T(4), and thyroid antibodies in the United States population (1988–1994): National Health and Nutrition Examination Survey (NHANES III). J Clin Endocrinol Metab 87:489–499 source
- Not checked yetcites [15] Vaisman F, Coeli CM, Ward LS et al (2013) How good is the levothyroxine replacement in primary hypothyroidism patients in Brazil? Data of a multicentre study. J Endocrinol Invest 36:485–488
- Not checked yetcites [16] Hallengren B, Lantz M, Andreasson B, Grennert L (2009) Pregnant women on thyroxine substitution are often dysregulated in early pregnancy. Thyroid 19:391–394 source
- Not checked yetcites [17] Cellini M, Santaguida MG, Virili C et al (2017) Hashimoto’s thyroiditis and autoimmune gastritis. Front Endocrinol (Lausanne) 8:92 doi: 10.3389/fendo.2017.00092 source
plainn = 2,292- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
In the paper
“In CONTROL HE, a retrospective study of 454 patients receiving levothyroxine for greater than 1 year, Ernst et al. reported a significant relationship between the number of levothyroxine dose or formulation changes and increased cost of patient care including drug therapy, laboratory tests, physician visits, and other healthcare costs (P < 0.05).”
§ Diagnosis and management of treatment-refractory hypothyroidism: an expert consensus report > Discussion
What the sources say
- Not checked yetcites [104] Ernst FR, Barr P, Elmor R, Sandulli W et al (2017) The economic impact of levothyroxine dose adjustments: the CONTROL HE Study. Clin Drug Investig 37:71–83 source
plaincorrelationaln = 454 ·- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: unclear — It is unclear whether the paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
In the paper
“The most recent data supporting this finding were reported by Vaisman in a multicenter study from Brazil, in which 28% of 2292 hypothyroid patients had elevated serum TSH levels with a background of thyroid hormone therapy”
§ Diagnosis and management of treatment-refractory hypothyroidism: an expert consensus report > Background
What the sources say
- Not checked yetcites [15] Vaisman F, Coeli CM, Ward LS et al (2013) How good is the levothyroxine replacement in primary hypothyroidism patients in Brazil? Data of a multicentre study. J Endocrinol Invest 36:485–488
plainn = 2,292- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: unclear — It is unclear whether the paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
In the paper
“In a prospective study involving 100 post-thyroidectomy patients, the optimal dose of levothyroxine (µg) could be predicted using a simple formula: dose = weight (kg) − age (years) + 125”
§ Diagnosis and management of treatment-refractory hypothyroidism: an expert consensus report > Primary factors contributing to refractory hypothyroidism > Pathologic causes of refractory hypothyroidism
What the sources say
- Not checked yetcites [72] Mistry D, Atkin S, Atkinson H et al (2011) Predicting thyroxine requirements following total thyroidectomy. Clin Endocrinol (Oxf) 74:384–387 source
hedgedcorrelationaln = 100- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: unclear — It is unclear whether the paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
In the paper
“In a recent observational cohort study that examined the risk of fracture in 17,684 patients >18 years old (mean age: 60.3 females, 61.8 males) on long-term levothyroxine therapy, a twofold increase in fracture risk was reported in patients having undetectable TSH levels (≤0.03 mU/L) compared to those with TSH levels in the normal range”
§ Diagnosis and management of treatment-refractory hypothyroidism: an expert consensus report > Discussion
What the sources say
- Not checked yetcites [97] Flynn RW, Bonellie SR, Jung RT, MacDonald TM, Morris AD, Leese GP (2010) Serum thyroid-stimulating hormone concentration and morbidity from cardiovascular disease and fractures in patients on long-term thyroxine therapy. J Clin Endocrinol Metab 9:186–193 source
plaincorrelationaln = 17,684- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
In the paper
“Evidence in the clinical literature suggests that there is an increased risk of bone fracture in individuals who are exposed to supratherapeutic doses of exogenous thyroid hormone for extended periods of time.”
§ Diagnosis and management of treatment-refractory hypothyroidism: an expert consensus report > Discussion
What the sources say
- Not checked yetcites [96] Bauer DC, Ettinger B, Nevitt MC, Stone KL (2001) Study of Osteoporotic Fractures Research Group. Risk for fracture in women with low serum levels of thyroid-stimulating hormone. Ann Intern Med 134:561–568 source
hedgedconditional- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
In the paper
“FT3 measurement has somewhat limited utility, however, in the diagnosis of hypothyroidism, since FT3 values often fall in the normal range as a result of hyperstimulation of the remaining functioning thyroid tissue by elevated TSH and to up-regulation of deiodinase D2”
§ Diagnosis and management of treatment-refractory hypothyroidism: an expert consensus report > Refractory hypothyroidism—clinical and laboratory findings > FT3 testing
What the sources say
- Not checked yetcites [25] Bianco AC, Salvatore D, Gereben B, Berry MJ, Larsen PR (2002) Biochemistry, cellular and molecular biology, and physiological roles of the iodothyronine selenodeiodinases. Endocr Rev 23:38–89 source
plaindirect- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: unclear — It is unclear whether the paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
None of the sources cited for this claim have been checked yet.
In the paper
“A number of kinase inhibitors, including imatinib and sunitinib, appear to influence thyroxine requirements through what is likely a class effect [114–116].”
§ Diagnosis and management of treatment-refractory hypothyroidism: an expert consensus report > Diagnosing and managing refractory hypothyroidism > Key principle
What the sources say
- Not checked yetcites [114] de Groot JW, Zonnenberg BA, Plukker JT, van Der Graaf WT, Links TP (2005) Imatinib induces hypothyroidism in patients receiving levothyroxine. Clin Pharmacol Ther 78:433–438 source
- Not checked yetcites [115] Sherman SI, Wirth LJ, Droz JP et al (2008) Motesanib diphosphate in progressive differentiated thyroid cancer. N Engl J Med 359:31–42 source
- Not checked yetcites [116] Robinson SI, Hobday TJ, Sathananthan A, Morris JC 3rd, McWilliams RR (2007) Can sorafenib cause hypothyroidism? J Chemother 19:352–353 source
hedgedconditional- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: unclear — It is unclear whether the paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
In the paper
“The ingestion of one or more of these at, or close to, the time of levothyroxine dosing can significantly change the dose requirement in individual patients, especially when done regularly [49].”
§ Diagnosis and management of treatment-refractory hypothyroidism: an expert consensus report > Diagnosing and managing refractory hypothyroidism > Key principle
What the sources say
- Not checked yetcites [49] Liwanpo L, Hershman JM (2009) Conditions and drugs interfering with thyroxine absorption. Best Pract Res Clin Endocrinol Metab 23:781–792 source
plaindirect- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
None of the sources cited for this claim have been checked yet.
In the paper
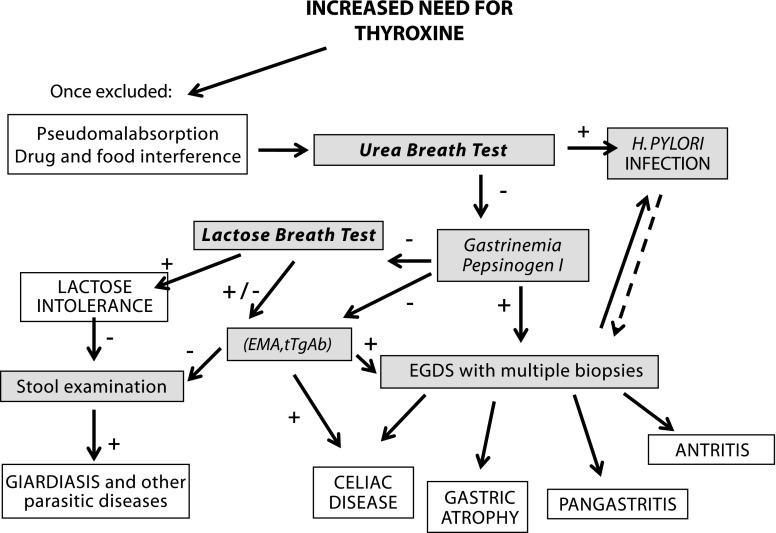
“Levothyroxine absorption can be limited by a number of diseases of the gastrointestinal (GI) tract, including: Helicobacter pylori infection, inflammatory bowel disease (IBD), celiac disease, lactose intolerance, atrophic body gastritis (ABG), gastric bypass, biliary pancreatic diversion, and gastroparesis, among others”
§ Diagnosis and management of treatment-refractory hypothyroidism: an expert consensus report > Primary factors contributing to refractory hypothyroidism > Pathologic causes of refractory hypothyroidism
What the sources say
- Not checked yetcites [5] Centanni M, Gargano L, Canettieri G et al (2006) Thyroxine in goiter, Helicobacter pylori infection, and chronic gastritis. N Engl J Med 354:1787–1795 source
- Not checked yetcites [10] Centanni M (2013) Thyroxine treatment: absorption, malabsorption, and novel therapeutic approaches. Endocrine 43:8–9 source
- Not checked yetcites [17] Cellini M, Santaguida MG, Virili C et al (2017) Hashimoto’s thyroiditis and autoimmune gastritis. Front Endocrinol (Lausanne) 8:92 doi: 10.3389/fendo.2017.00092 source
- Not checked yetcites [52] Ruchala M, Szczepanek-Parulska E, Zybek A (2012) The influence of lactose intolerance and other gastro-intestinal tract disorders on l-thyroxine absorption. Endokrynol Pol 63:318–323
- Not checked yetcites [63] Fallahi P, Ferrari SM, Camastra S et al (2017) TSH normalization in bariatric surgery patients after the switch from l-thyroxine in tablet to an oral liquid formulation. Obes Surg 27:78–82 source
plainconditional- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
None of the sources cited for this claim have been checked yet.
In the paper
“As a result, TSH may be a poor indicator of peripheral thyroid levels in the presence of such conditions.”
§ Diagnosis and management of treatment-refractory hypothyroidism: an expert consensus report > Refractory hypothyroidism—clinical and laboratory findings > TSH vs. FT3 testing
What the sources say
- Not checked yetcites [29] Peeters RP, van der Geyten S, Wouters PJ et al (2005) Tissue thyroid hormone levels in critical illness. J Clin Endocrinol Metab 12:6498–6507 source
- Not checked yetcites [30] Peeters RP, Wouters PJ, van Toor H, Kaptein E, Visser TJ et al (2005) Serum 3,3′,5′-triiodothyronine (rT3) and 3,5,3′-triiodothyronine/rT3 are prognostic markers in critically ill patients and are associated with postmortem tissue deiodinase activities. J Clin Endocrinol Metab 90:4559–4565 source
- Not checked yetcites [31] Docter R, Krenning EP, de Jong M, Hennemann G (1993) The sick euthyroid syndrome: changes in thyroid hormone serum parameters and hormone metabolism. Clin Endocrinol (Oxf) 39:499–518 source
- Not checked yetcites [32] Fliers E, Alkemade A, Wiersinga WM (2001) The hypothalamic-pituitary-thyroid axis in critical illness. Best Pract Res Clin Endocrinol Metab 15:453–464 source
- Not checked yetcites [33] Chopra IJ (1997) Euthyroid sick syndrome: is it a misnomer? J Clin Endocrinol Metab 82:329–334 source
- Not checked yetcites [34] Nagaya T, Fujieda M, Otsuka G, Yang JP, Okamoto T, Seo H (2000) A potential role of activated NF-Kappa B in the pathogenesis of euthyroid sick syndrome. J Clin Invest 106:393–402 source
- Not checked yetcites [35] van der Poll T, Romijn JA, Wiersinga WM, Sauerwein HP (1990) Tumor necrosis factor: a putative mediator of the sick euthyroid syndrome in man. J Clin Endocrinol Metab 71:1567–1572 source
- Not checked yetcites [36] Stouthard JM, van der Poll T, Endert E et al (1994) Effects of acute and chronic interleukin-6 administration on thyroid hormone metabolism in humans. J Clin Endocrinol Metab 79:1342–1346
- Not checked yetcites [37] Corssmit EP, Heyligenberg R, Endert E, Sauerwein HP, Romijn JA (1995) Acute effects of interferon-alpha administration on thyroid hormone metabolism in healthy men. Clin Endocrinol Metab 80:3140–3144
hedgedconditional- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
None of the sources cited for this claim have been checked yet.
In the paper
“Since levothyroxine is the first-line treatment for hypothyroidism”
§ Diagnosis and management of treatment-refractory hypothyroidism: an expert consensus report > Background
What the sources say
- Not checked yetcites [18] Jonklaas J, Bianco AC, Bauer AJ et al (2014) Guidelines for the treatment of hypothyroidism: prepared by the American Thyroid Association Task Force on thyroid hormone replacement. Thyroid 24:1670–1751 source
- Not checked yetcites [19] Biondi B, Bartalena L, Chiovato L et al (2016) Recommendations for treatment of hypothyroidism with levothyroxine and levotriiodothyronine: a 2016 position statement of the Italian Society of Endocrinology and the Italian Thyroid Association. J Endocrinol Invest 39:1465–1474 source
plain- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
In the paper
“More than 85% of patients experienced ≤1 dose adjustment post-switch.”
§ Diagnosis and management of treatment-refractory hypothyroidism: an expert consensus report > Diagnosing and managing refractory hypothyroidism > Alternative levothyroxine formulations
What the sources say
- Not checked yetcites [122] Ernst FR, Sandulli W, Elmor R et al (2017) Retrospective study of patients switched from tablet formulations to a gel cap formulation of levothyroxine: results of the CONTROL Switch study. Drugs R D 17:103–115 source
plainn = 99- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
None of the sources cited for this claim have been checked yet.
In the paper
“Using a high-dose levothyroxine, absorption test can play an important role in the differential diagnosis of pseudomalabsorption (which is a most common source of difficulties in obtaining euthyreosis in hypothyroid patients) and actual levothyroxine malabsorption [117, 118].”
§ Diagnosis and management of treatment-refractory hypothyroidism: an expert consensus report > Diagnosing and managing refractory hypothyroidism > Key principle
What the sources say
- Not checked yetcites [117] Srinivas V, Oyibo SO (2010) Levothyroxine pseudomalabsorption and thyroxine absorption testing with use of high-dose levothyroxine: case report and discussion. Endocr Pract 16:1012–1015 source
- Not checked yetcites [118] Müssig K, Mörike K, Klein R (2009) Hypothyroidism due to pseudo-malabsorption of levothyroxine—case 12/2009. Dtsch Med Wochenschr 134:2514 source
plainconditional- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
In the paper
“Significant improvement in hypothyroid symptom control; +62% (P < 0.0001).”
§ Diagnosis and management of treatment-refractory hypothyroidism: an expert consensus report > Diagnosing and managing refractory hypothyroidism > Alternative levothyroxine formulations
What the sources say
- Not checked yetcites [122] Ernst FR, Sandulli W, Elmor R et al (2017) Retrospective study of patients switched from tablet formulations to a gel cap formulation of levothyroxine: results of the CONTROL Switch study. Drugs R D 17:103–115 source
plaindirectn = 99 ·- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
In the paper
“As a last resort in those with continuing poor compliance, administration of thyroxine once weekly can be successful [119].”
§ Diagnosis and management of treatment-refractory hypothyroidism: an expert consensus report > Diagnosing and managing refractory hypothyroidism > Key principle
What the sources say
- Not checked yetcites [119] Grebe SK, Cooke RR, Ford HC et al (1997) Treatment of hypothyroidism with once weekly thyroxine. J Clin Endocrinol Metab 82:870–875
plainconditional- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
In the paper
“Moreover, patients with nephrotic syndrome who excrete large quantities of albumin may also have increased thyroxine requirements as a result of the binding of levothyroxine to the excreted albumin [87].”
§ Diagnosis and management of treatment-refractory hypothyroidism: an expert consensus report > Diagnosing and managing refractory hypothyroidism > Key principle
What the sources say
- Not checked yetcites [87] Junglee NA, Scanlon MF, Rees DA (2006) Increasing thyroxine requirements in primary hypothyroidism: don’t forget the urinalysis! J Postgrad Med 52:201–203
hedgedconditional- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: unclear — It is unclear whether the paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
A conclusion the paper draws from its own results — it cites no other source for it, so there is none to check. The quote shows it is in the paper.
In the paper
“Repeated adjustments of levothyroxine can also escalate the costs of treatment, as frequent office visits and lab tests are required to determine and maintain the desired dose.”
§ Diagnosis and management of treatment-refractory hypothyroidism: an expert consensus report > Conclusions
plaindirect- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: unclear — It is unclear whether the paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
None of the sources cited for this claim have been checked yet.
In the paper
“pseudomalabsorption (which is a most common source of difficulties in obtaining euthyreosis in hypothyroid patients)”
§ Diagnosis and management of treatment-refractory hypothyroidism: an expert consensus report > Diagnosing and managing refractory hypothyroidism > Key principle
What the sources say
- Not checked yetcites [117] Srinivas V, Oyibo SO (2010) Levothyroxine pseudomalabsorption and thyroxine absorption testing with use of high-dose levothyroxine: case report and discussion. Endocr Pract 16:1012–1015 source
- Not checked yetcites [118] Müssig K, Mörike K, Klein R (2009) Hypothyroidism due to pseudo-malabsorption of levothyroxine—case 12/2009. Dtsch Med Wochenschr 134:2514 source
plaindirect- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
A conclusion the paper draws from its own results — it cites no other source for it, so there is none to check. The quote shows it is in the paper.
In the paper
“Recent evidence suggests that either the softgel or liquid alternatives may eliminate a number of factors that contribute to levothyroxine tablet failure and refractory hypothyroidism.”
§ Diagnosis and management of treatment-refractory hypothyroidism: an expert consensus report > Diagnosing and managing refractory hypothyroidism > Alternative levothyroxine formulations
hedgedconditional- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
None of the sources cited for this claim have been checked yet.
In the paper
“Studies have demonstrated that even intermittent oversuppression of TSH using levothyroxine can result in increased bone loss, cardiovascular, and other more serious medical conditions [97, 99, 101].”
§ Diagnosis and management of treatment-refractory hypothyroidism: an expert consensus report > Conclusions
What the sources say
- Not checked yetcites [97] Flynn RW, Bonellie SR, Jung RT, MacDonald TM, Morris AD, Leese GP (2010) Serum thyroid-stimulating hormone concentration and morbidity from cardiovascular disease and fractures in patients on long-term thyroxine therapy. J Clin Endocrinol Metab 9:186–193 source
- Not checked yetcites [99] Shomon M The thyroid treatment/osteoporosis controversy: does thyroid treatment contribute to loss of bone density? http://www.thyroid-info.com/articles/osteoporosis.htm . Accessed 1 Oct 2016
- Not checked yetcites [101] Lindner H Thyroid hormone: T3. http://www.hormonerestoration.com/thyroid.html . Accessed 1 Oct 2016
boosteddirect- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
In the paper
“In particular, Santaguida et al. [121] have shown that most patients with definite gastric disorders benefited by changing from the traditional tablet formulations to the softgel levothyroxine preparation at a reduced dose.”
§ Diagnosis and management of treatment-refractory hypothyroidism: an expert consensus report > Diagnosing and managing refractory hypothyroidism > Alternative levothyroxine formulations
What the sources say
- Not checked yetcites [121] Santaguida MG, Virili C, Del Duca SC, Cellini M, Gatto I, Brusca N et al (2015) Thyroxine softgel capsule in patients with gastric-related T4 malabsorption. Endocrine 49:51–57 source
boosteddirect- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
A conclusion the paper draws from its own results — it cites no other source for it, so there is none to check. The quote shows it is in the paper.
In the paper
“There is a frequently encountered subset of hypothyroid patients who are refractory to standard thyroid hormone replacement treatment and require unexpectedly high doses of levothyroxine or who have erratic control of hypothyroidism, alternating between over-replacement and under-replacement.”
§ Diagnosis and management of treatment-refractory hypothyroidism: an expert consensus report > Conclusions
plain- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: unclear — It is unclear why the paper says it holds.
In the paper
“Following the switch to the liquid formulation, TSH levels among patients significantly declined compared to the basal value at both the first control (P < 0.05) and the second control (P < 0.01).”
§ Diagnosis and management of treatment-refractory hypothyroidism: an expert consensus report > Diagnosing and managing refractory hypothyroidism > Alternative levothyroxine formulations
What the sources say
- Not checked yetcites [123] Fallahi P, Ferrari SM, Antonelli A (2016) Oral l-thyroxine liquid versus tablets in patients with hypothyroidism without malabsorption: a prospective study. Endocrine 52:597–601 source
plaindirectn = 152 ·- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
None of the sources cited for this claim have been checked yet.
In the paper
“As mentioned above, during normal pregnancy, women experience increased thyroxine requirements that may approach 50% [41, 60].”
§ Diagnosis and management of treatment-refractory hypothyroidism: an expert consensus report > Diagnosing and managing refractory hypothyroidism > Key principle
What the sources say
- Not checked yetcites [41] Morris JC (2009) How do you approach the problem of TSH elevation in a patient on high-dose thyroid hormone replacement? Clin Endocrinol 70:671–673 source
- Not checked yetcites [60] Alexander EK, Marqusee E, Lawrence J, Jarolim P, Fischer GA, Larsen PR (2004) Timing and magnitude of increases in levothyroxine requirements during pregnancy in women with hypothyroidism. N Engl J Med 351:241–249 source
hedgedconditional- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: unclear — It is unclear whether the paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
In the paper
“Levels of both FT4 and FT3 were not significantly changed [123].”
§ Diagnosis and management of treatment-refractory hypothyroidism: an expert consensus report > Diagnosing and managing refractory hypothyroidism > Alternative levothyroxine formulations
What the sources say
- Not checked yetcites [123] Fallahi P, Ferrari SM, Antonelli A (2016) Oral l-thyroxine liquid versus tablets in patients with hypothyroidism without malabsorption: a prospective study. Endocrine 52:597–601 source
plainn = 152- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: unclear — It is unclear whether the paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
In the paper
“switching primarily from either branded or generic levothyroxine tablets to levothyroxine gel caps resulted in:Significant reduction in dose adjustments; −55% (P < 0.0001).”
§ Diagnosis and management of treatment-refractory hypothyroidism: an expert consensus report > Diagnosing and managing refractory hypothyroidism > Alternative levothyroxine formulations
What the sources say
- Not checked yetcites [122] Ernst FR, Sandulli W, Elmor R et al (2017) Retrospective study of patients switched from tablet formulations to a gel cap formulation of levothyroxine: results of the CONTROL Switch study. Drugs R D 17:103–115 source
plaindirectn = 99 ·- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
A conclusion the paper draws from its own results — it cites no other source for it, so there is none to check. The quote shows it is in the paper.
In the paper
“In addition to clinical situations where hypothyroid patients are non-compliant, or where there is the possibility of excipient-induced disease exacerbation (gluten/celiac disease), therapeutic failure may be due to impaired absorption of the administered drug.”
§ Diagnosis and management of treatment-refractory hypothyroidism: an expert consensus report > Conclusions
hedgedconditional- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
A conclusion the paper draws from its own results — it cites no other source for it, so there is none to check. The quote shows it is in the paper.
In the paper
“This is often the result of either patient pathophysiology (GI disease), the effects of other therapeutic agents, or diet (timing of ingestion relative to meals and beverages, including coffee).”
§ Diagnosis and management of treatment-refractory hypothyroidism: an expert consensus report > Conclusions
plaindirect- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: unclear — It is unclear why the paper says it holds.
- It may state two separate claims as one. 7
- The quote only partly states this claim. 1
- Probably not a substantial claim. 9
In the paper
“More than 21% reported taking thyroxine less than the recommended 30 min before eating, a practice that may significantly contribute to less-than-optimal drug absorption”
§ Diagnosis and management of treatment-refractory hypothyroidism: an expert consensus report > Primary factors contributing to refractory hypothyroidism > Non-pathologic causes of refractory hypothyroidism
What the sources say
- Not checked yetcites [42] McMillan M, Rotenberg KS, Vora K et al (2016) Comorbidities, concomitant medications, and diet as factors affecting levothyroxine therapy: results of the CONTROL Surveillance Project. Drugs R D 16:53–68 source
hedgedconditionaln = 925- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: unclear — It is unclear whether the paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
In the paper
“Overall patient satisfaction with treatment was 44% lower among patients experiencing levothyroxine dose changes versus those without such changes (P < 0.001).”
§ Diagnosis and management of treatment-refractory hypothyroidism: an expert consensus report > Discussion
What the sources say
- Not checked yetcites [105] McMillan M, Sterman A, Engelken D, Sandulli W (2016) Levothyroxine dose changes and hypothyroid patient satisfaction—results of the CONTROL TS Study. Abstract. 86th Annual Meeting of the American Thyroid Association, Denver source
plaincorrelationaln = 300- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: unclear — It is unclear whether the paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
The quote only partly states this claim.
In the paper
“The researchers concluded that there was an increased risk of cardiovascular disease, dysrhythmias, and fractures in patients having high or suppressed TSH, but not in patients with low, but unsuppressed, TSH levels”
§ Diagnosis and management of treatment-refractory hypothyroidism: an expert consensus report > Discussion
What the sources say
- Not checked yetcites [97] Flynn RW, Bonellie SR, Jung RT, MacDonald TM, Morris AD, Leese GP (2010) Serum thyroid-stimulating hormone concentration and morbidity from cardiovascular disease and fractures in patients on long-term thyroxine therapy. J Clin Endocrinol Metab 9:186–193 source
plaincorrelational- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
Probably not a substantial claim. It may state two separate claims as one.
In the paper
“It has been suggested that a genetic variation in deiodinase D2 (also called type 2 deiodinase, or 5′-deiodinase) may help to explain why some patients who fail to achieve control of hypothyroidism with a background of levothyroxine therapy respond to natural desiccated thyroid or to the combined therapy of levothyroxine and synthetic T3”
§ Diagnosis and management of treatment-refractory hypothyroidism: an expert consensus report > Primary factors contributing to refractory hypothyroidism > Pathologic causes of refractory hypothyroidism
What the sources say
- Not checked yetcites [74] Bowthorpe J Is there a genetic reason many of us do lousy on T4? http://www.stopthethyroidmadness.com/2009/10/28/is-there-a-genetic-reason-many-of-us-do-lousy-on-t4 . Accessed 1 Oct 2016
hedgedconditional- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: fails — The paper’s conclusions may not depend on it.
- Based: passes — The paper gives a reason why it holds.
Probably not a substantial claim. The paper’s conclusions may not depend on it.
In the paper
“According to the most recent guidelines from the American Thyroid Association (ATA), “TSH is the most reliable marker of adequacy of replacement treatment, and a value within the reference range (0.4–4.0 mIU/L) should be considered the therapeutic target””
§ Diagnosis and management of treatment-refractory hypothyroidism: an expert consensus report > Refractory hypothyroidism—clinical and laboratory findings > TSH testing
What the sources say
- Not checked yetcites [18] Jonklaas J, Bianco AC, Bauer AJ et al (2014) Guidelines for the treatment of hypothyroidism: prepared by the American Thyroid Association Task Force on thyroid hormone replacement. Thyroid 24:1670–1751 source
plain- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: fails — The paper’s conclusions may not depend on it.
- Based: passes — The paper gives a reason why it holds.
Probably not a substantial claim. The paper’s conclusions may not depend on it. It may state two separate claims as one.
None of the sources cited for this claim have been checked yet.
In the paper
“While serum T3 levels may decline by 30%, which is significant, but still within the so-called “normal range”, tissue T3 may decline by 70–80%, resulting in profound cellular hypothyroidism with normal serum TSH, FT4, and FT3 levels”
§ Diagnosis and management of treatment-refractory hypothyroidism: an expert consensus report > Refractory hypothyroidism—clinical and laboratory findings > TSH vs. FT3 testing
What the sources say
- Not checked yetcites [29] Peeters RP, van der Geyten S, Wouters PJ et al (2005) Tissue thyroid hormone levels in critical illness. J Clin Endocrinol Metab 12:6498–6507 source
- Not checked yetcites [30] Peeters RP, Wouters PJ, van Toor H, Kaptein E, Visser TJ et al (2005) Serum 3,3′,5′-triiodothyronine (rT3) and 3,5,3′-triiodothyronine/rT3 are prognostic markers in critically ill patients and are associated with postmortem tissue deiodinase activities. J Clin Endocrinol Metab 90:4559–4565 source
- Not checked yetcites [31] Docter R, Krenning EP, de Jong M, Hennemann G (1993) The sick euthyroid syndrome: changes in thyroid hormone serum parameters and hormone metabolism. Clin Endocrinol (Oxf) 39:499–518 source
- Not checked yetcites [32] Fliers E, Alkemade A, Wiersinga WM (2001) The hypothalamic-pituitary-thyroid axis in critical illness. Best Pract Res Clin Endocrinol Metab 15:453–464 source
- Not checked yetcites [33] Chopra IJ (1997) Euthyroid sick syndrome: is it a misnomer? J Clin Endocrinol Metab 82:329–334 source
- Not checked yetcites [34] Nagaya T, Fujieda M, Otsuka G, Yang JP, Okamoto T, Seo H (2000) A potential role of activated NF-Kappa B in the pathogenesis of euthyroid sick syndrome. J Clin Invest 106:393–402 source
- Not checked yetcites [35] van der Poll T, Romijn JA, Wiersinga WM, Sauerwein HP (1990) Tumor necrosis factor: a putative mediator of the sick euthyroid syndrome in man. J Clin Endocrinol Metab 71:1567–1572 source
- Not checked yetcites [36] Stouthard JM, van der Poll T, Endert E et al (1994) Effects of acute and chronic interleukin-6 administration on thyroid hormone metabolism in humans. J Clin Endocrinol Metab 79:1342–1346
- Not checked yetcites [37] Corssmit EP, Heyligenberg R, Endert E, Sauerwein HP, Romijn JA (1995) Acute effects of interferon-alpha administration on thyroid hormone metabolism in healthy men. Clin Endocrinol Metab 80:3140–3144
- Not checked yetcites [38] Chopra IJ, Chopra U, Smith SR, Reza M, Solomon DH (1975) Reciprocal changes in serum concentrations of 3,3′,5-triiodothyronine (T3) in systemic illnesses. J Clin Endocrinol Metab 41:1043–1049 source
hedgedconditional- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
None of the sources cited for this claim have been checked yet.
In the paper
“Primary hypothyroidism is considered to be refractory to oral thyroxine when there is biochemical or clinical evidence of hypothyroidism [serum level of thyroid-stimulating hormone (TSH) above the upper target level, usually 4.5 mU/L following a 6-week interval after the dosage was last increased] and/or unresolved hypothyroid symptoms, despite increasing dosages of levothyroxine beyond 1.9 μg/kg”
§ Diagnosis and management of treatment-refractory hypothyroidism: an expert consensus report > Introduction
What the sources say
- Not checked yetcites [1] Lips DJ, van Reisen MT, Voigt V, Venekamp W (2004) Diagnosis and treatment of levothyroxine pseudomalabsorption. Neth J Med 62:114–118
- Not checked yetcites [2] Virili C, Bassotti G, Santaguida MG et al (2012) Atypical celiac disease as cause of increased need for thyroxine: a systematic study. J Clin Endocrinol Metab 97:E419–E422 source
- Not checked yetcites [3] Cellini M, Santaguida MG, Gatto I et al (2014) Systematic appraisal of lactose intolerance as cause of increased need for oral thyroxine. J Clin Endocrinol Metab 99:E1454–E1458 source
plain- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
Probably not a substantial claim.
In the paper
“For many years, poor compliance with the daily dosing of levothyroxine was reputed to be the most common reason for unusually high doses of thyroid replacement therapy”
§ Diagnosis and management of treatment-refractory hypothyroidism: an expert consensus report > Primary factors contributing to refractory hypothyroidism > Non-pathologic causes of refractory hypothyroidism
What the sources say
- Not checked yetcites [1] Lips DJ, van Reisen MT, Voigt V, Venekamp W (2004) Diagnosis and treatment of levothyroxine pseudomalabsorption. Neth J Med 62:114–118
hedged- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: fails — The paper’s conclusions may not depend on it.
- Based: passes — The paper gives a reason why it holds.
Probably not a substantial claim. The paper’s conclusions may not depend on it.
The paper states this without a source or data behind it here, so there is nothing to check it against. The quote shows it is in the paper.
In the paper
“By laboratory definition, frank primary hypothyroidism requires low levels of thyroid hormones (free–FT4 and FT3) as well as elevated TSH.”
§ Diagnosis and management of treatment-refractory hypothyroidism: an expert consensus report > Diagnosing and managing refractory hypothyroidism > Key principle
plaincorrelational- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: fails — The paper may give no reason why it holds.
Probably not a substantial claim. The paper may give no reason why it holds.
None of the sources cited for this claim have been checked yet.
In the paper
“Because it is not standardized, and unlikely to be associated with a specific etiology, the absorption test should not be used routinely [9, 41, 51].”
§ Diagnosis and management of treatment-refractory hypothyroidism: an expert consensus report > Diagnosing and managing refractory hypothyroidism > Key principle
What the sources say
- Not checked yetcites [9] Benvenga S (2013) When thyroid hormone replacement is ineffective? Curr Opin Endocrinol Diabetes Obes 20:467–477 source
- Not checked yetcites [41] Morris JC (2009) How do you approach the problem of TSH elevation in a patient on high-dose thyroid hormone replacement? Clin Endocrinol 70:671–673 source
- Not checked yetcites [51] Ward LS (2010) The difficult patient: drug interaction and the influence of concomitant diseases on the treatment of hypothyroidism. Arq Brasil Endocrinol Metab 54:435–442 source
plaincorrelational- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
A conclusion the paper draws from its own results — it cites no other source for it, so there is none to check. The quote shows it is in the paper.
In the paper
“This approach can increase the risk for prolonged exposure to supratherapeutic doses of levothyroxine which increase the chances of adverse outcomes.”
§ Diagnosis and management of treatment-refractory hypothyroidism: an expert consensus report > Conclusions
plaindirect- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
A conclusion the paper draws from its own results — it cites no other source for it, so there is none to check. The quote shows it is in the paper.
In the paper
“The early discovery of these factors via a thoughtful patient work-up may avoid unnecessary thyroid medication adjustments and their consequences for patients, clinicians, and the healthcare system.”
§ Diagnosis and management of treatment-refractory hypothyroidism: an expert consensus report > Conclusions
hedgedconditional- Asserted: passes — The authors put it forward as true.
- Checkable: fails — It may be too vague to check against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
Probably not a substantial claim. It may be too vague to check against evidence.
A conclusion the paper draws from its own results — it cites no other source for it, so there is none to check. The quote shows it is in the paper.
In the paper
“Significant swings in weight may also cause treatment-refractory hypothyroidism.”
§ Diagnosis and management of treatment-refractory hypothyroidism: an expert consensus report > Conclusions
hedgedconditional- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: fails — The paper may give no reason why it holds.
Probably not a substantial claim. The paper may give no reason why it holds.
A conclusion the paper draws from its own results — it cites no other source for it, so there is none to check. The quote shows it is in the paper.
In the paper
“This holistic approach acknowledges that treatment-refractory hypothyroidism is a condition that exists within the context of other important factors—GI disease, concomitant drug use, diet, and patient habits—whose presence may adversely affect thyroid replacement therapy.”
§ Diagnosis and management of treatment-refractory hypothyroidism: an expert consensus report > Conclusions
hedgedconditional- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
Probably not a substantial claim.
In the paper
“CONTROL Switch, a recent retrospective study involving 99 hypothyroid patients being treated by endocrinologists, suggested that a strategy of switching therapy from the traditional levothyroxine tablets to levothyroxine gel caps may preclude or reduce the need for levothyroxine dose or formulation changes, while improving hypothyroid symptom control, in some patients [122].”
§ Diagnosis and management of treatment-refractory hypothyroidism: an expert consensus report > Diagnosing and managing refractory hypothyroidism > Alternative levothyroxine formulations
What the sources say
- Not checked yetcites [122] Ernst FR, Sandulli W, Elmor R et al (2017) Retrospective study of patients switched from tablet formulations to a gel cap formulation of levothyroxine: results of the CONTROL Switch study. Drugs R D 17:103–115 source
hedgedconditionaln = 99 ·- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
The paper relies on this without support.
The eight-step approach to diagnosing and managing refractory hypothyroidism has been validated through empirical use.
“We recommend the following eight-step approach, which has been validated through empirical use and should be considered as an alternative to the standard practice of escalating doses of levothyroxine”
The paper relies on this without support.
Early discovery of factors affecting levothyroxine absorption via a thoughtful patient work-up may avoid unnecessary thyroid medication adjustments and their consequences for patients and clinicians.
“The early discovery of these factors via a thoughtful patient work-up may avoid unnecessary thyroid medication adjustments and their consequences for both patients and clinicians.”
The paper relies on this without support.
Inter-individual variability in the efficiency of GI absorption is large and accounts for most of the range of dose requirements among compliant patients after adjustment for body size.
“Inter-individual variability in the efficiency of GI absorption is rather large, and such variability accounts for most of the range of dose requirements seen among compliant patients following adjustment for body size.”
The paper relies on this without support.
The first sign of malabsorption syndrome can be the need for unexpectedly high doses of levothyroxine in replacement therapy; malabsorption syndrome is frequently oligosymptomatic and previously undiagnosed.
“The first sign of malabsorption syndrome, which is frequently oligosymptomatic and previously undiagnosed, can be the need for unexpectedly high doses of levothyroxine in replacement therapy.”
The paper relies on this without support.
Phenytoin, carbamazepine, and rifampin increase turnover or excretion of thyroid hormone.
“These medications include phenytoin, carbamazepine, and rifampin.”
The paper relies on this without support.
Switching to generic levothyroxine products is correlated with sub-optimal outcomes.
“Switching to generic levothyroxine products has also been correlated with sub-optimal outcomes.”
The paper relies on this without support.
The common approach to managing patients with unusual thyroxine needs is to escalate the dose of levothyroxine until targeted TSH levels are achieved.
“The common approach to managing patients with unusual thyroxine needs is to escalate the dose of levothyroxine until targeted TSH levels are achieved.”
The paper relies on this without support.
A clinical test for estimating the absorption of thyroxine may have utility in some patients who have unexpectedly high thyroxine requirements.
“Although not standardized, a clinical test for estimating the absorption of thyroxine may have utility in some patients who have unexpectedly high thyroxine requirements.”
Claims other papers make about this one
Each is checked against this paper’s own text: does it say what the citing paper says it does?
The source backs part of the claim, not all of it — or backs it for a different population, condition or comparison.
In the citing paper
“Furthermore, the use of calcium salts in the post-operative period in patients with transient or permanent hypocalcemia results in interference with LT4 absorption (13, 14).”
From ETA guidelines for the use of levothyroxine sodium preparations in monotherapy to optimize the treatment of hypothyroidism (2025) · cites this paper as [13]
Experimental — accuracy not yet measuredThe source backs part of the claim, not all of it — or backs it for a different population, condition or comparison.
In the citing paper
“In an attempt to overcome the above-mentioned issues with gastrointestinal absorption (such as intake interference, drug interference, and pH dependence), non-tablet LT4 formulations, i.e., liquid solution (LS) and softgel capsule (SG), have been manufactured and commercialized for clinical practice, although they are not available in every country (13, 107).”
From ETA guidelines for the use of levothyroxine sodium preparations in monotherapy to optimize the treatment of hypothyroidism (2025) · cites this paper as [13]
Experimental — accuracy not yet measuredThe source backs part of the claim, not all of it — or backs it for a different population, condition or comparison.
In the citing paper
“In clinical practice, the levothyroxine absorption test is part of the workup of patients with “refractory hypothyroidism” to differentiate true malabsorption from nonadherence or pseudo-malabsorption [3, 6].”
From Levothyroxine Absorption Test With the Daily Levothyroxine Dose in Patients With “Refractory Hypothyroidism” (2025) · cites this paper as [3]
Experimental — accuracy not yet measuredThe cited source says what the claim attributes to it.
In the citing paper
“Nowadays, we know that other causes may be equally relevant, as in the case of nutritional, pharmacological or pathological interferences (12, 13, 14).”
From ETA guidelines for the use of levothyroxine sodium preparations in monotherapy to optimize the treatment of hypothyroidism (2025) · cites this paper as [13]
The cited source says what the claim attributes to it.
In the citing paper
“The use of drugs interacting and/or interfering with the different formulations of levothyroxine may represent a significant issue when treating patients in a ‘real life’ setting.”
From ETA guidelines for the use of levothyroxine sodium preparations in monotherapy to optimize the treatment of hypothyroidism (2025) · cites this paper as [13]
The cited source says what the claim attributes to it.
In the citing paper
“Despite a daily levothyroxine dose of more than 1.9 µg/kg/day, between 15% and 20% of levothyroxine-treated patients present hypothyroid symptoms or have TSH levels above the upper limit of the reference range [3, 4].”
From Levothyroxine Absorption Test With the Daily Levothyroxine Dose in Patients With “Refractory Hypothyroidism” (2025) · cites this paper as [3]
In the citing paper
“Pathological causes include obesity and gastrointestinal disorders responsible for LT4 malabsorption, as well as other rare conditions such as nephrotic syndrome, Addison's disease, and cystic fibrosis.4,17”
From Refractory hypothyroidism: unraveling the complexities of diagnosis and management (2023) · cites this paper as [4]
In the citing paper
“Studies indicate that in 10% to 20% of patients with RH, no identifiable cause is found, which is referred to as”
From Refractory hypothyroidism: unraveling the complexities of diagnosis and management (2023) · cites this paper as [4]
In the citing paper
“In 2017, it was suggested to classify the main causes of RH as either pathological or nonpathological.4”
From Refractory hypothyroidism: unraveling the complexities of diagnosis and management (2023) · cites this paper as [4]
Self-check
Percentages, sums and reported differences re-computed from the paper’s own numbers.
Each contradiction between two passages listed here was confirmed by an independent check.
Rated major: it would touch a result — a value a result rests on, reported and recomputed p-values on opposite sides of the significance level, two passages that conflict with no sign which is right, or a cited work retracted before this paper was published.
In the paper
§ Diagnosis and management of treatment-refractory hypothyroidism: an expert consensus report > Diagnosing and managing refractory hypothyroidism > Key principle
“By laboratory definition, frank primary hypothyroidism requires low levels of thyroid hormones (free–FT4 and FT3) as well as elevated TSH.”
§ Diagnosis and management of treatment-refractory hypothyroidism: an expert consensus report > Refractory hypothyroidism—clinical and laboratory findings > FT3 testing
“FT3 values often fall in the normal range as a result of hyperstimulation of the remaining functioning thyroid tissue by elevated TSH and to up-regulation of deiodinase D2, the enzyme that converts T4 to T3 [25].”
Citations
Cites
Hollowell, J. G., Staehling, N. W., Flanders, W. D., Hannon, W. H., Gunter, E. W., Spencer, C. A., & Braverman, L. E. (2002) · The Journal of Clinical Endocrinology & Metabolism · doi:10.1210/jc.87.2.489 · Cited by 4,279
The Colorado Thyroid Disease Prevalence Study
Canaris, G. J., Manowitz, N. R., Mayor, G., & Ridgway, E. C. (2000) · Archives of Internal Medicine · doi:10.1001/archinte.160.4.526 · Cited by 2,824
Jonklaas, J., Bianco, A. C., Bauer, A. J., Burman, K. D., Cappola, A. R., Celi, F. S., Cooper, D. S., Kim, B. W., Peeters, R. P., Rosenthal, M. S., et al. (2014) · Thyroid® · doi:10.1089/thy.2014.0028 · Cited by 1,928
Bianco, A. C., Salvatore, D., Gereben, B., Berry, M. J., & Larsen, P. R. (2002) · Endocrine Reviews · doi:10.1210/edrv.23.1.0455 · Cited by 1,853 · cited 1×
“FT3 measurement has somewhat limited utility, however, in the diagnosis of hypothyroidism, since FT3 values often fall in the normal range as a result of hyperstimulation of the remaining functioning thyroid tissue by elevated TSH and to up-regulation of deiodinase D2, the enzyme that converts T4 to T3 [25].”
BackgroundGarber, J. R., Cobin, R. H., Gharib, H., Hennessey, J. V., Klein, I., Mechanick, J. I., Pessah-Pollack, R., Singer, P. A., & Woeber, K. A. (2012) · Endocrine Practice · doi:10.4158/ep12280.gl · Cited by 1,567 · cited 14×
“1 3 hyperthyroid based on low serum TSH levels over many weeks or months [21].”
BackgroundMethodInfluentialGarber, J. R., Cobin, R. H., Gharib, H., Hennessey, J. V., Klein, I., Mechanick, J. I., Pessah-Pollack, R., Singer, P. A., & Woeber for the American Association, K. A. (2012) · Thyroid · doi:10.1089/thy.2012.0205 · Cited by 1,053
Fasano, A., & Catassi, C. (2012) · New England Journal of Medicine · doi:10.1056/nejmcp1113994 · Cited by 721
Alexander, E. K., Marqusee, E., Lawrence, J., Jarolim, P., Fischer, G. A., & Larsen, P. R. (2004) · New England Journal of Medicine · doi:10.1056/nejmoa040079 · Cited by 633
IMS Institute for Healthcare Informatics
Evans, R. G. (2014) · Nursing Standard · doi:10.7748/ns2014.04.28.32.30.s36 · Cited by 590
Motesanib Diphosphate in Progressive Differentiated Thyroid Cancer
Sherman, S. I., Wirth, L. J., Droz, J.-P., Hofmann, M., Bastholt, L., Martins, R. G., Licitra, L., Eschenberg, M. J., Sun, Y.-N., Juan, T., et al. (2008) · New England Journal of Medicine · doi:10.1056/nejmoa075853 · Cited by 470
Cited by
Sorted by citations
Gastrointestinal malabsorption of thyroxine
Virili, C., Antonelli, A., Santaguida, M. G., Benvenga, S., & Centanni, M. (2019) · Endocrine Reviews · doi:10.1210/er.2018-00168 · Cited by 164
Self-citationNew Formulations of Levothyroxine in the Treatment of Hypothyroidism: Trick or Treat?
Nagy, E. V., Perros, P., Papini, E., Katkó, M., & Hegedűs, L. D. (2020) · Thyroid · doi:10.1089/thy.2020.0515 · Cited by 67
“Dose adjustments may be triggered by patient non-adherence, concomitant medications, gastrointestinal co-morbidities, switching between generic and branded LT4 products, diet, and alterations in body weight (10).”
Virili, C., Giovanella, L., Fallahi, P., Antonelli, A., Santaguida, M. G., Centanni, M., & Trimboli, P. (2018) · Frontiers in Endocrinology · doi:10.3389/fendo.2018.00010 · Cited by 61
“, chronic atrophic gastritis, Helicobacter pylori infection) (7, 14), and concomitant intake of some drugs or ingestion of food or beverages (15, 16) can interfere with the LT4 absorption, thus reducing its efficacy.”
BackgroundSelf-citationThyro-entero-gastric autoimmunity: Pathophysiology and implications for patient management
Lahner, E., Conti, L., Cicone, F., Capriello, S., Cazzato, M. T., Centanni, M., Annibale, B., & Virili, C. (2019) · Best Practice & Research Clinical Endocrinology & Metabolism · doi:10.1016/j.beem.2019.101373 · Cited by 61
Self-citationLevothyroxine therapy in gastric malabsorptive disorders
Virili, C., Brusca, N., Capriello, S., & Centanni, M. (2021) · Frontiers in Endocrinology · doi:10.3389/fendo.2020.621616 · Cited by 52
“In clinical practice, the timing of food intake and the interval before and after thyroxine ingestion seems not negligible for the subsequent intestinal absorption (31, 32).”
BackgroundSelf-citation
Metadata
- Authors
- Centanni, M., Benvenga, S., & Sachmechi, I.
- Affiliations
- Sapienza University of Rome (IT)
- University of Messina (IT)
- Queens Hospital Center (US)
- Corresponding author
- Centanni, M.
- Venue
- Journal of Endocrinological Investigation
- Published
- 2017-07-10
- Volume
- 40
- Issue
- 12
- Pages
- 1289-1301
- ISSN
- 0391-4097 (ISSN-L)
- 1720-8386
- PMC
- PMC5680379
- OpenAlex
- W2734775767
- Semantic Scholar
- f7773e0f970a425911f864880f74f948e65cc28f
- Cited by
- 113
- References
- 122
- Citations by year
- 2026: 9 · 2025: 19 · 2024: 13 · 2023: 8 · 2022: 11 · 2021: 18 · 2020: 9 · 2019: 16 · 2018: 9
- FWCI
- 7.35
- Type
- journal article
- Language
- en
- Open access
- hybrid
- doi.org
- Locations
- Journal of Endocrinological Investigation (publishedVersion, cc-by)
- Europe PMC (PubMed Central) (publishedVersion, cc-by)
- PubMed Central (publishedVersion, cc-by)
- PubMed (publishedVersion)
- IRIS Research product catalog (Sapienza University of Rome) (submittedVersion, cc-by)
- Funders
- Akrimax Pharmaceuticals, LLC
- Topics
- Health Sciences › Medicine › Endocrinology, Diabetes and Metabolism › Thyroid Disorders and Treatments
- Health Sciences › Medicine › Surgery › Thyroid and Parathyroid Surgery
- Health Sciences › Medicine › Endocrinology, Diabetes and Metabolism › Adrenal Hormones and Disorders
- Keywords
- levothyroxine, thyroid hormone replacement, drug malabsorption, celiac disease, TSH monitoring, dose escalation, medication adherence
- MeSH terms
- Drug Resistance, Humans, Hypothyroidism, Disease Management, Hormone Replacement Therapy
About these checks
Registry, retraction, Cites and statistics results are computed, not judged, with one exception: a printed reference that no index lists is read once by a model before it counts as a citation error. Claims are extracted by a model and kept only when their quote appears verbatim in the text; each cited source is then checked, with a model’s help, for whether it says what the claim relies on. Those verdicts can be wrong — read the claim’s quote and the cited source before relying on one.
A language model drew the claims from the paper on 2026-10-07, under version 3 of the claim definition (model deepseek-v4.1-flash, prompt extract-v3).
A second model labelled each claim on 2026-10-07 (model jev-1.13-20260917, definition revision gold-guideline-v0.2).
Cited sources are checked with a language model’s help (gpt-6-sol).
Statistics and arithmetic are recomputed, not judged.
Confidence bands are shown only for fields calibrated on our annotated test set. None is calibrated yet, so no band is shown.
What counts as a claim ›How we measure confidence ›How we check this ›
Are you an author, or do you see a problem with this page? Request a review
