

The DOI matches its Crossref record; 68 of the 68 references it cites were found in a registry or an index; none of the 19 sources its claims cite is checked for support yet.
Federated learning for computational pathology on gigapixel whole slide images
Open accessAbstract
Deep Learning-based computational pathology algorithms have demonstrated profound ability to excel in a wide array of tasks that range from characterization of well known morphological phenotypes to predicting non human-identifiable features from histology such as molecular alterations. However, the development of robust, adaptable and accurate deep learning-based models often rely on the collection and time-costly curation large high-quality annotated training data that should ideally come from diverse sources and patient populations to cater for the heterogeneity that exists in such datasets. Multi-centric and collaborative integration of medical data across multiple institutions can naturally help overcome this challenge and boost the model performance but is limited by privacy concerns among other difficulties that may arise in the complex data sharing process as models scale towards using hundreds of thousands of gigapixel whole slide images. In this paper, we introduce privacy-preserving federated learning for gigapixel whole slide images in computational pathology using weakly-supervised attention multiple instance learning and differential privacy. We evaluated our approach on two different diagnostic problems using thousands of histology whole slide images with only slide-level labels. Additionally, we present a weakly-supervised learning framework for survival prediction and patient stratification from whole slide images and demonstrate its effectiveness in a federated setting. Our results show that using federated learning, we can effectively develop accurate weakly-supervised deep learning models from distributed data silos without direct data sharing and its associated complexities, while also preserving differential privacy using randomized noise generation. We also make available an easy-to-use federated learning for computational pathology software package: http://github.com/mahmoodlab/HistoFL.
Overview
AI snapshot
Written from the paper’s full text.
TL;DR
This paper presents a privacy-preserving federated learning framework for gigapixel whole slide images in computational pathology, combining weakly-supervised attention multiple instance learning with differential privacy via Gaussian noise. It evaluates the approach on breast and renal cancer subtyping and clear cell renal cell carcinoma survival prediction, showing federated models can be competitive with centralized training while avoiding direct data sharing.
Key findings
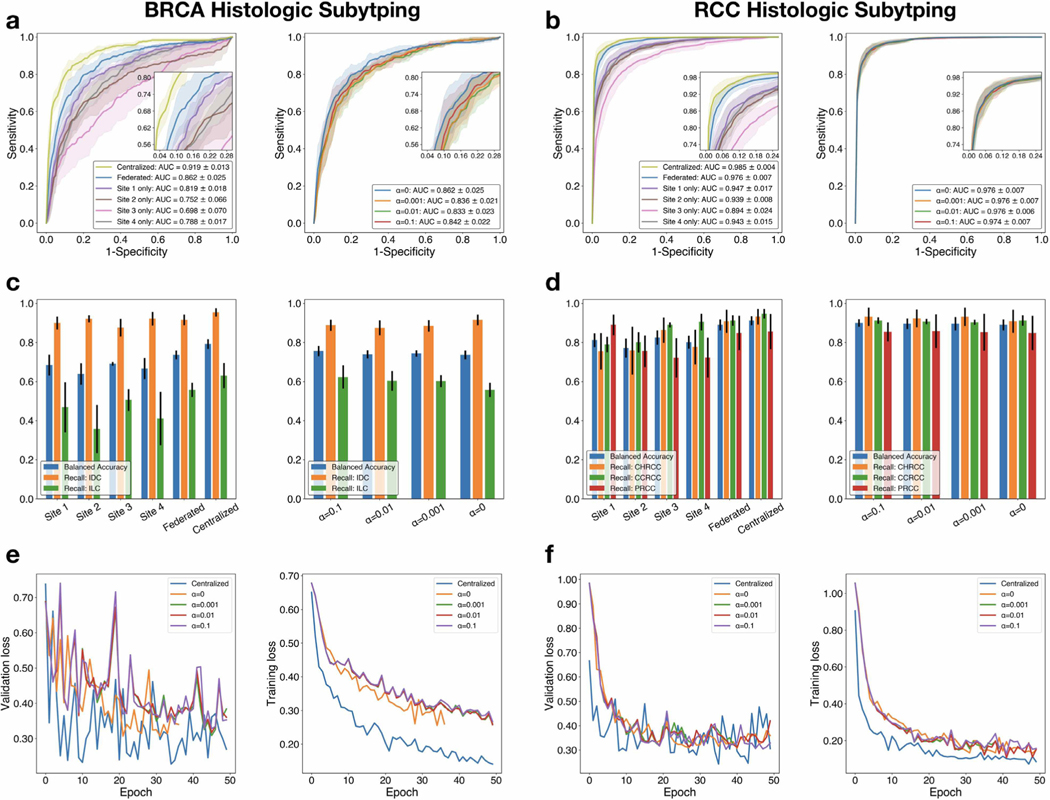
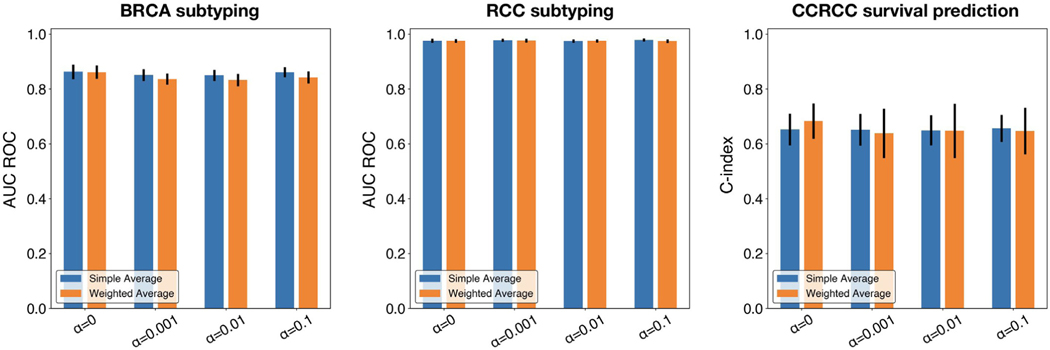
- Federated learning benefited from multi-institutional data compared with single-institution training and was generally competitive with centralized training. For BRCA subtyping, mean test AUC ranged from 0.833 to 0.862 for noise levels α ∈ {0, 0.001, 0.01, 0.1}; for RCC subtyping, macro-averaged test AUC ranged from 0.974 to 0.976.
- Model performance significantly deteriorated when α was set too high (e.g., α = 1), indicating a trade-off between model performance and privacy protection.
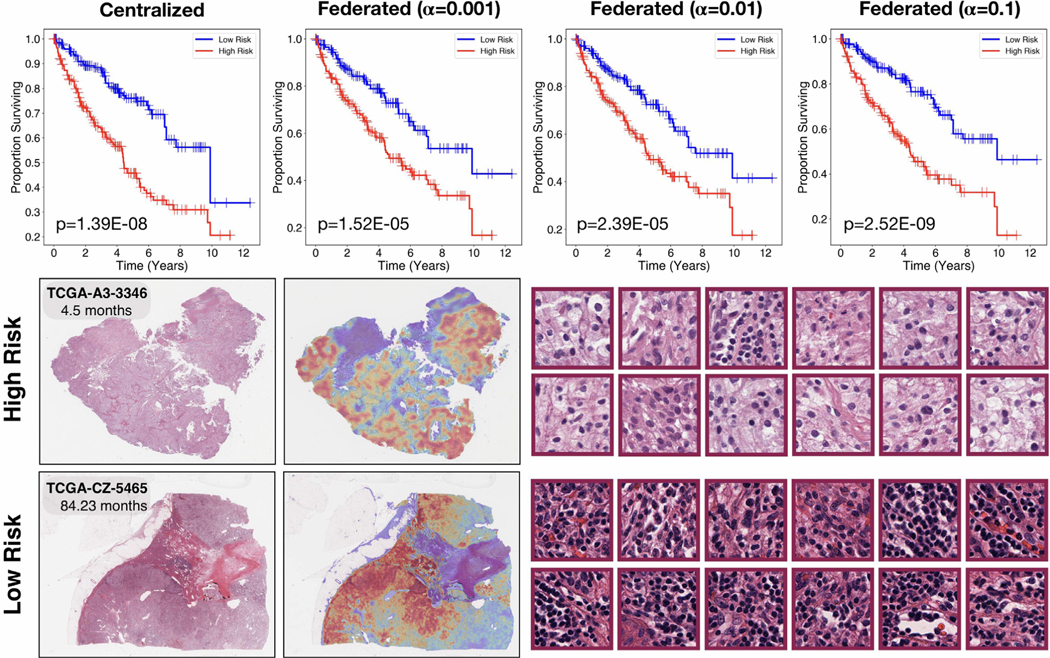
- For CCRCC survival prediction, all federated models except α = 1 achieved statistical significance (p < 0.05) and reasonable c-Index and average cumulative/dynamic AUC; when trained on single-institution data, only 1 of 3 institutions yielded a model that could stratify patients into distinct survival groups.
- For survival prediction, R = 8 performed best among R ∈ {2, 4, 6, 8}; a Cox proportional hazard model based on nuclear grade lagged behind the weakly-supervised deep learning approach and only matched its performance when combined with age and gender. Less frequent communication decreased survival c-indices by around 2–3% for E = 4 and E = 8, while weighted versus simple federated averaging showed minimal differences.
Methods
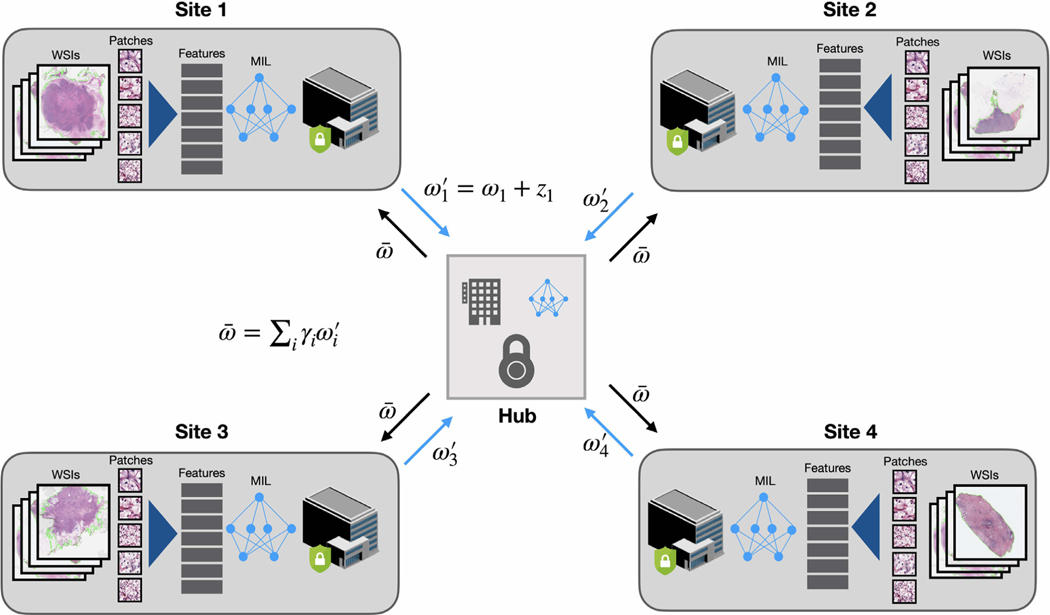
- The framework used a master-server federated averaging architecture: each participating institution trained a local attention-based MIL model, uploaded trainable parameters each epoch, and the central server averaged them and sent updated weights back. Differential privacy was implemented by adding Gaussian noise to shared weights, with α varied over {0, 0.001, 0.01, 0.1, 1.0}; communication frequency E was varied over {1, 2, 4, 8}, and weighted versus uniform averaging was compared.
- Data included TCGA and Brigham and Women’s Hospital in-house WSIs. BRCA subtyping used 2126 breast WSIs (369 lobular, 1757 ductal); RCC subtyping used 1184 kidney WSIs (703 CCRCC, 337 PRCC, 144 CHRCC); CCRCC survival prediction used 511 patient cases from TCGA-KIRC. Classification used four simulated institutional sites (BWH plus three TCGA tissue-source-site partitions); survival prediction used three simulated sites. Data were split 70/15/15% for training/validation/test per site, repeated with 5 random seeds, with stratified sampling.
- WSIs were processed at 20× magnification using the CLAM pipeline to segment tissue and extract 256×256 patches, embedded as 1024-dimensional feature vectors via a pretrained ResNet50 encoder truncated after the third residual block. Models used gated attention MIL with a projection to 512 dimensions, 256-dimensional attention hidden layers, dropout p = 0.25, and either cross-entropy for classification or a discrete-time hazard loss for survival prediction with R bins and β = 0.15.
Limitations
- The paper does not include a dedicated limitations section. Stated caveats include a trade-off between model performance and privacy protection when α is too high, and dataset-size imbalance among participating institutions, where single sites with insufficient data may not yield meaningful generalizable models.
- The text makes evident that federated learning was simulated by partitioning TCGA and in-house data into institutional sites rather than deploying across actual independent institutions.
- The differential privacy analysis assumes Δ₂(f) = 1 because computing sensitivity for a multi-layer neural network is intractable, and the privacy guarantee is linked to an adjustable noise parameter rather than a formal end-to-end accounting in the experiments.
Model-written summary. Check it against the paper before relying on it.
Integrity signals
Registry
Cites
Statistics
Figures
Verification
Claims the paper makes
14 Own result · 13 Own interpretation · 8 Not checked yet · 5 No basis given
The paper states this without a source or data behind it here, so there is nothing to check it against. The quote shows it is in the paper.
In the paper
“Notably, we observed that the model trained using data local to site 3 delivered performance comparable to that of centralized training and using federated learning.”
§ Federated learning for computational pathology on gigapixel whole slide images > Experiments and results > Experimental results
plainn = 331- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: unclear — It is unclear whether the paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
A result the paper reports from its own data — it cites no other source for it, so there is none to check. The quote shows it is in the paper.
In the paper
“We found that the model performance benefited significantly from training on multi-institutional data using federated learning, compared to learning from data within a single institution.”
§ Federated learning for computational pathology on gigapixel whole slide images > Experiments and results > Experimental results
boosteddirect- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
A result the paper reports from its own data — it cites no other source for it, so there is none to check. The quote shows it is in the paper.
In the paper
“we found that federated learning can overcome this challenge as all models trained in the federated framework (with the exception of when using α = 1) resulted in statistical significance (p-value < 0.05) and produced reasonable performance both in terms of c-Index values and average cumulative/dynamic AUC.”
§ Federated learning for computational pathology on gigapixel whole slide images > Experiments and results > Experimental results
plain- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
A result the paper reports from its own data — it cites no other source for it, so there is none to check. The quote shows it is in the paper.
In the paper
“In fact, we found the models trained using federated learning to be generally competitive in performance even when compared to scenario 2), where model is trained by first centralizing (sharing) all training data from each institution.”
§ Federated learning for computational pathology on gigapixel whole slide images > Experiments and results > Experimental results
plain- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
A result the paper reports from its own data — it cites no other source for it, so there is none to check. The quote shows it is in the paper.
In the paper
“When trained using data from a single institution, only 1 out of 3 institutions was able to yield a model that can stratify patients into distinct survival groups based on predicted risk scores.”
§ Federated learning for computational pathology on gigapixel whole slide images > Experiments and results > Experimental results
plain- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
A result the paper reports from its own data — it cites no other source for it, so there is none to check. The quote shows it is in the paper.
In the paper
“we found that the model performance significantly deteriorated when α was set too high (e.g., α = 1)”
§ Federated learning for computational pathology on gigapixel whole slide images > Experiments and results > Experimental results
plaindirect- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
A result the paper reports from its own data — it cites no other source for it, so there is none to check. The quote shows it is in the paper.
In the paper
“For α∈{0,0.001,0.01,0.1}, for BRCA subtyping, the mean test AUC ranged from 0.833 to 0.862 when using federated learning for different levels of random noise”
§ Federated learning for computational pathology on gigapixel whole slide images > Experiments and results > Experimental results
plain- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
A result the paper reports from its own data — it cites no other source for it, so there is none to check. The quote shows it is in the paper.
In the paper
“we found that federated learning can overcome this challenge as all models trained in the federated framework (with the exception of when using α = 1) resulted in statistical significance (p-value < 0.05) and produced reasonable performance both in terms of c-Index values and average cumulative/dynamic AUC.”
§ Federated learning for computational pathology on gigapixel whole slide images > Experiments and results > Experimental results
plaindirect- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
A result the paper reports from its own data — it cites no other source for it, so there is none to check. The quote shows it is in the paper.
In the paper
“and for RCC subtyping, the macro-averaged test AUC ranged from 0.974 to 0.976.”
§ Federated learning for computational pathology on gigapixel whole slide images > Experiments and results > Experimental results
plain- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
The paper states this without a source or data behind it here, so there is nothing to check it against. The quote shows it is in the paper.
In the paper
“while survival prediction a decrease in c-indices of around 2 – 3% was observed for E = 4 and E = 8 respectively.”
§ Federated learning for computational pathology on gigapixel whole slide images > Experiments and results > Ablating hyperparamter choices in federated averaging
plaincorrelational- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
- It may state two separate claims as one. 7
- Probably not a substantial claim. 7
A result the paper reports from its own data — it cites no other source for it, so there is none to check. The quote shows it is in the paper.
In the paper
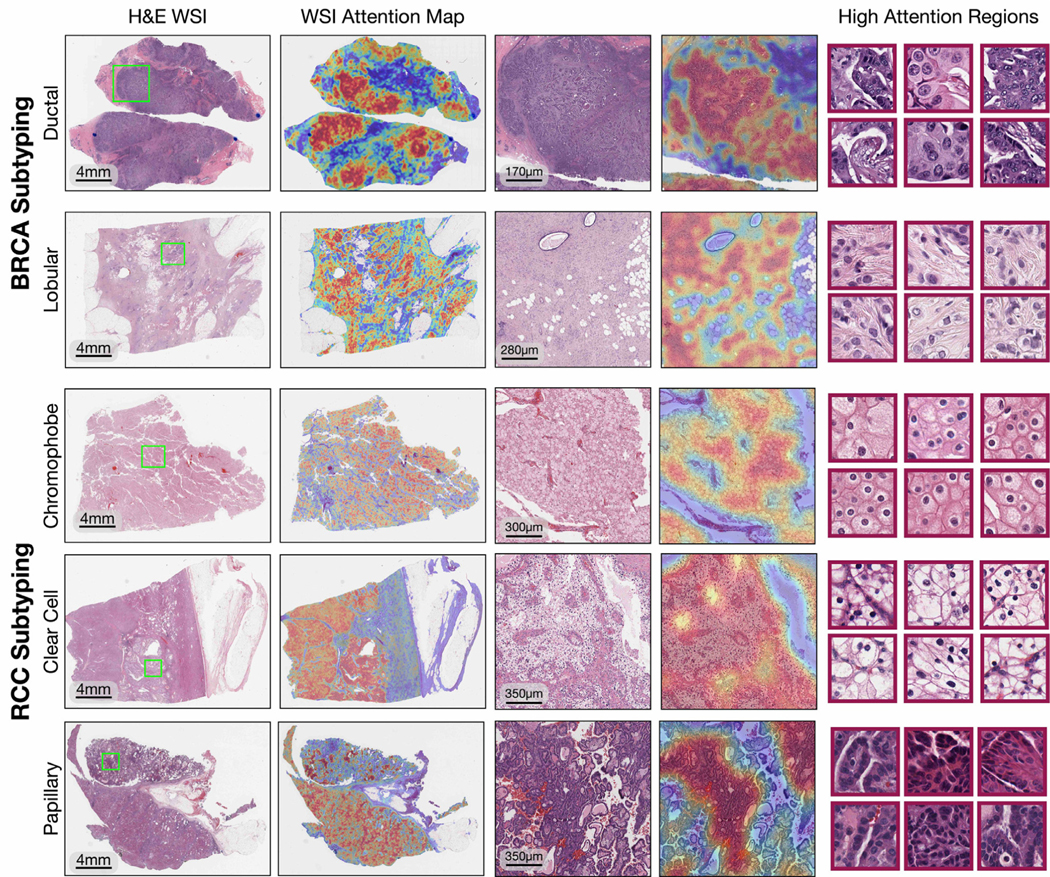
“In addition to strong performance, in Fig. 3, we also demonstrated that models trained using privacy-preserving federated learning can saliently localize regions of high diagnostic relevance and identify morphological features characteristic of each underlying tumor subtype.”
§ Federated learning for computational pathology on gigapixel whole slide images > Experiments and results > Experimental results
boosteddirect- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
A result the paper reports from its own data — it cites no other source for it, so there is none to check. The quote shows it is in the paper.
In the paper
“We observed that in general the performance difference between the deep learning model trained using different values of R are under a few percents, with R = 8 performing the best for the particular task (Table 11).”
§ Federated learning for computational pathology on gigapixel whole slide images > Experiments and results > Comparison of weakly-supervised survival prediction and existing strategies
plainn = 511- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: unclear — It is unclear whether the paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
A result the paper reports from its own data — it cites no other source for it, so there is none to check. The quote shows it is in the paper.
In the paper
“The results are shown for both classification and survival tasks and for different levels of α (Fig. 5), where minimal differences between the two design choices were observed.”
§ Federated learning for computational pathology on gigapixel whole slide images > Experiments and results > Ablating hyperparamter choices in federated averaging
plain- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: unclear — It is unclear whether the paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
A result the paper reports from its own data — it cites no other source for it, so there is none to check. The quote shows it is in the paper.
In the paper
“Additionally we note that the cox proportional hazard model based on nuclear grade lags behind the weakly- supervised deep learning-based approach, and only matches its performance when combined with additional variables including age and gender, beyond histologic features made available to the deep learning model.”
§ Federated learning for computational pathology on gigapixel whole slide images > Experiments and results > Comparison of weakly-supervised survival prediction and existing strategies
plaincorrelationaln = 511- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
A conclusion the paper draws from its own results — it cites no other source for it, so there is none to check. The quote shows it is in the paper.
In the paper
“Our results show that using federated learning, we can effectively develop accurate weakly-supervised deep learning models from distributed data silos without direct data sharing and its associated complexities, while also preserving differential privacy using randomized noise generation.”
§ Federated learning for computational pathology on gigapixel whole slide images > Abstract
plaindirect- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
None of the sources cited for this claim have been checked yet.
In the paper
“A popular strategy in the medical field is a contamination of the input data (Cheu et al., 2019) or the model parameters (Dong et al., 2019) with certain levels of noise. This de- creases the individually recognizable information while preserving the global distribution of the data (Kaissis et al., 2020).”
§ Federated learning for computational pathology on gigapixel whole slide images > Introduction
What the sources say
- Not checked yetcites Cheu et al., 2019
- Not checked yetcites Dong et al., 2019
- Not checked yetcites Kaissis et al., 2020 source
plaindirect- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: fails — The paper’s conclusions may not depend on it.
- Based: passes — The paper gives a reason why it holds.
Probably not a substantial claim. The paper’s conclusions may not depend on it.
None of the sources cited for this claim have been checked yet.
In the paper
“One of the fields that would strongly benefit from the federated framework is computational pathology (Andreux et al., 2020b, a; Rieke et al., 2020).”
§ Federated learning for computational pathology on gigapixel whole slide images > Introduction
What the sources say
- Not checked yetcites Andreux et al., 2020b
- Not checked yetcites Rieke et al., 2020 source
boostedconditional- Asserted: passes — The authors put it forward as true.
- Checkable: fails — It may be too vague to check against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
Probably not a substantial claim. It may be too vague to check against evidence.
The paper states this without a source or data behind it here, so there is nothing to check it against. The quote shows it is in the paper.
In the paper
“Furthermore, while fully-supervised approaches are burdened by the need for time-costly pixel-level annotation based on pathologist expertise, weakly-supervised approaches such as MIL simplify collaborative efforts by alleviating the requirement for such human expertise and the burden of creating pixel-level labels under unified annotation protocol in all participating institutions.”
§ Federated learning for computational pathology on gigapixel whole slide images > Introduction
plaindirect- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
Probably not a substantial claim.
None of the sources cited for this claim have been checked yet.
In the paper
“In this way, sensitive patient data are never transferred beyond the safety of institutional firewalls, and instead, the model training and validation occur locally at each institution and only the model specifics (e.g. parameters or gradients) are transferred.”
§ Federated learning for computational pathology on gigapixel whole slide images > Introduction
What the sources say
- Not checked yetcites Yang et al., 2019 source
- Not checked yetcites Konecˇny’ et al., 2016
- Not checked yetcites McMahan et al., 2017
plain- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
- Rests on an assumption: Each medical institution will not share data with other parties due to institutional policies, incompatible data sharing protocols, technical difficulties, or fear of privacy loss.
The paper states this without a source or data behind it here, so there is nothing to check it against. The quote shows it is in the paper.
In the paper
“In our federated learning setting, f involves a neural network consisting of many layers of trainable parameters making computing Δ2(f) intractable.”
§ Federated learning for computational pathology on gigapixel whole slide images > Methods > Differential privacy and federated learning
plaindirect- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: fails — The paper may give no reason why it holds.
Probably not a substantial claim. The paper may give no reason why it holds.
A conclusion the paper draws from its own results — it cites no other source for it, so there is none to check. The quote shows it is in the paper.
In the paper
“Federated learning would in principle enable deep learning models to learn from much larger and more diverse multi-institutional data sources without the challenges associated with data centralization and healthcare interoperability.”
§ Federated learning for computational pathology on gigapixel whole slide images > Introduction
hedgedconditional- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: fails — The paper may give no reason why it holds.
Probably not a substantial claim. The paper may give no reason why it holds.
- Rests on an assumption: Model accuracy and robustness can be significantly increased by incorporating diverse data reflecting variations in underlying patient populations, as well as data collection and preparation protocols.
A conclusion the paper draws from its own results — it cites no other source for it, so there is none to check. The quote shows it is in the paper.
In the paper
“Our proposed framework opens the possibility for multiple institutions to integrate their WSI datasets and train a more robust model that tends to generalize better on unseen data than models developed on data from a single institution, while also allowing participating institutions to preserve differential privacy via a randomized mechanism.”
§ Federated learning for computational pathology on gigapixel whole slide images > Conclusion
hedgedconditional- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
- Rests on an assumption: The development and validation of AI algorithms in pathology have been mainly limited to single-institutional datasets.
- Rests on an assumption: Single-institutional datasets may not generalize at deployment time due to variations in the underlying patient population, staining protocols, and scanner hardware.
- Rests on an assumption: Dataset-size imbalance among different participating institutions frequently occurs in the real world.
A conclusion the paper draws from its own results — it cites no other source for it, so there is none to check. The quote shows it is in the paper.
In the paper
“This could potentially be explained by the smaller training set sizes available for the task, which makes it easier for client models to overfit on their local training data when a longer communication pace is used.”
§ Federated learning for computational pathology on gigapixel whole slide images > Experiments and results > Ablating hyperparamter choices in federated averaging
hedgedconditional- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: fails — The paper’s conclusions may not depend on it.
- Based: passes — The paper gives a reason why it holds.
Probably not a substantial claim. The paper’s conclusions may not depend on it.
A conclusion the paper draws from its own results — it cites no other source for it, so there is none to check. The quote shows it is in the paper.
In the paper
“while also allowing participating institutions to preserve differential privacy via a randomized mechanism.”
§ Federated learning for computational pathology on gigapixel whole slide images > Conclusion
plaindirect- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: fails — The paper may give no reason why it holds.
Probably not a substantial claim. The paper may give no reason why it holds.
- Rests on an assumption: The randomized mechanism (Gaussian noise) used in federated averaging preserves differential privacy.
The authors state this as an assumption.
The l2 sensitivity of the neural network function, Δ2(f), is 1.
“However, without loss of generality, if we assume Δ2(f)=1, we see that for a given level of δ, increasing σ will enable a smaller ε to be satisfied.”
The paper relies on this without support.
Each medical institution will not share data with other parties due to institutional policies, incompatible data sharing protocols, technical difficulties, or fear of privacy loss.
“Since each medical institution will not share data with other parties due to various issues (e.g. institutional policies, incompatible data sharing protocols, technical difficulties associated with sharing large amount of data or fear of privacy loss), we cannot pool together their data and train a single deep learning model fcentralized for solving the desired task.”
The authors state this as an assumption.
The global model is hosted on a central server hub.
“In this paper, we adapted a master-server architecture, where each client node, representing each medical institution, locally utilizes the same deep learning architecture as one another and the global model, which we assume to be hosted on a central server hub.”
The paper relies on this without support.
Model accuracy and robustness can be significantly increased by incorporating diverse data reflecting variations in underlying patient populations, as well as data collection and preparation protocols.
“As in all machine learning affairs, the model’s accuracy and robustness can be significantly increased by incorporating diverse data reflecting variations in underlying patient populations, as well as data collection and preparation protocols.”
The paper relies on this without support.
Whole slide images used for computational analysis exhibit immense heterogeneity arising from patient group, tissue preparation, fixation and staining protocols, and scanner hardware.
“Specifically, in pathology, whole slide images (WSIs) used for computational analysis can exhibit immense heterogeneity. Such diversities arise from not only the patient group corresponding to the histology specimens and variations in the tissue preparation, fixation and staining protocols, but also different scanner hardware that are used for digitization.”
The paper relies on this without support.
Histology data might allow indirect patient identification, e.g., in the case of rare diseases.
“Even though histology data do not hold such a direct link with patient identity, it might still allow an indirect patient identification e.g. in the case of rare diseases.”
The paper relies on this without support.
The development and validation of AI algorithms in pathology have been mainly limited to single-institutional datasets.
“Despite these breakthroughs, the development and validation in AI algorithms in pathology have been mainly limited to single-institutional datasets”
The paper relies on this without support.
Single-institutional datasets may not generalize at deployment time due to variations in the underlying patient population, staining protocols, and scanner hardware.
“which may not generalize at deployment time due to variations in the underlying patient population, staining protocols, and scanner hardware.”
The paper relies on this without support.
Dataset-size imbalance among different participating institutions frequently occurs in the real world.
“Similar dataset-size imbalance among different participating institutions frequently occurs in the real-world and is also reflected in the imbalanced distribution of patient cases among the original tissue source sites in the TCGA.”
The paper relies on this without support.
The randomized mechanism (Gaussian noise) used in federated averaging preserves differential privacy.
“while also allowing participating institutions to preserve differential privacy via a randomized mechanism.”
Claims other papers make about this one
Each is checked against this paper’s own text: does it say what the citing paper says it does?
In the citing paper
“Despite less annotation requirements, the above UDA approaches need access to both source and target data [33], [34].”
From Memory-aware curriculum federated learning for breast cancer classification (2023) · cites this paper as [33]
In the citing paper
“Simulations show that the FL approach can achieve the balanced accuracy of disease detection up to 90% in various parameter settings”
From Federated learning for smart healthcare: A survey (2023) · cites this paper as [106]
Self-check
Percentages, sums and reported differences re-computed from the paper’s own numbers.
Each contradiction between two passages listed here was confirmed by an independent check.
Rated minor: it would not touch a result — a value no result rests on, a p-value that stays on the same side of the significance level, or a conflict that is clerical, resolved elsewhere in the paper, or outside its own findings.
In the paper
§ Federated learning for computational pathology on gigapixel whole slide images > Methods > Weakly-supervised learning on WSIs
“By rewriting P(Tj=r∣hbagj)=fhazard(r∣hbagj)fsurv(r∣hbagj), the loss we minimize based on the log likelihood function (Zadeh and Schmid, 2020) can be expressed as:”
§ Federated learning for computational pathology on gigapixel whole slide images > Methods > Weakly-supervised learning on WSIs
“(10) L=−l=−cj⋅log(fsurv(Yj∣hbagj))−(1−cj)⋅log(fsurv(Yj−1∣hbagj))−(1−cj)⋅log(fhazard(Yj∣hbagj))”
Rated minor: it would not touch a result — a value no result rests on, a p-value that stays on the same side of the significance level, or a conflict that is clerical, resolved elsewhere in the paper, or outside its own findings.
In the paper
§ Federated learning for computational pathology on gigapixel whole slide images > Methods > Weakly-supervised learning on WSIs
“(8) fsurv(r∣hbagj)=P(Tj>r∣hbagj)=∏u=1r(1−fhazard(u∣hbagj))”
§ Federated learning for computational pathology on gigapixel whole slide images > Methods > Weakly-supervised learning on WSIs
“Since we consider the label set Tj∈{0,…,R−1} to be the support of the hazard function”
Citations
Cites
ImageNet: A large-scale hierarchical image database
Deng, J., Dong, W., Socher, R., Li, L.-J., Li, K., & Fei-Fei, L. (2009) · 2009 IEEE Conference on Computer Vision and Pattern Recognition · doi:10.1109/cvpr.2009.5206848 · Cited by 65,333
Communication-Efficient Learning of Deep Networks from Decentralized Data
McMahan, H. B., Moore, E., Ramage, D., Hampson, S., & Arcas, B. A. Y. (2016) · arXiv · doi:10.48550/arxiv.1602.05629 · Cited by 14,215
Advances and Open Problems in Federated Learning
Kairouz, P., McMahan, H. B., Avent, B., Bellet, A., Bennis, M., Bhagoji, A. N., Bonawitz, K., Charles, Z., Cormode, G., Cummings, R., et al. (2019) · arXiv · doi:10.48550/arxiv.1912.04977 · Cited by 7,857
Advances and Open Problems in Federated Learning
Kairouz, P., & McMahan, H. B. (2021) · Foundations and Trends in Machine Learning · doi:10.1561/2200000083 · Cited by 7,772
Deep Learning with Differential Privacy
Abadi, M., Chu, A., Goodfellow, I., McMahan, H. B., Mironov, I., Talwar, K., & Zhang, L. (2016) · Proceedings of the 2016 ACM SIGSAC Conference on Computer and Communications Security · doi:10.1145/2976749.2978318 · Cited by 6,578
Federated Machine Learning: Concept and Applications
Yang, Q., Liu, Y., Chen, T., & Tong, Y. (2019) · ACM Transactions on Intelligent Systems and Technology · doi:10.1145/3298981 · Cited by 6,322
Self-citationFederated learning: Challenges, methods, and future directions
Li, T., Sahu, A. K., Talwalkar, A., & Smith, V. (2020) · IEEE Signal Processing Magazine · doi:10.1109/msp.2020.2975749 · Cited by 6,210
The Algorithmic Foundations of Differential Privacy
Dwork, C., & Roth, A. (2014) · Foundations and Trends® in Theoretical Computer Science · doi:10.1561/0400000042 · Cited by 5,557
The future of digital health with federated learning
Rieke, N., Hancox, J., Li, W., Milletarì, F., Roth, H. R., Albarqouni, S., Bakas, S., Galtier, M. N., Landman, B. A., Maier-Hein, K., et al. (2020) · npj Digital Medicine · doi:10.1038/s41746-020-00323-1 · Cited by 4,015 · cited 1×
“Federated learning (Yang et al., 2019; Konečnỳ et al., 2016; McMahan et al., 2017; Rieke et al., 2020) offers means to mitigate these challenges by enabling algorithms to learn from de-centralized data distributed across various institutions.”
BackgroundFederated Learning: Strategies for Improving Communication Efficiency
Konečný, J., McMahan, H. B., Yu, F. X., Richtárik, P., Suresh, A. T., & Bacon, D. (2016) · arXiv · doi:10.48550/arxiv.1610.05492 · Cited by 3,766
Coudray, N., Ocampo, P. S., Sakellaropoulos, T., Narula, N., Snuderl, M., Fenyö, D., Moreira, A. L., Razavian, N., & Tsirigos, A. (2018) · Nature Medicine · doi:10.1038/s41591-018-0177-5 · Cited by 2,930
Privacy-preserving deep learning
Shokri, R., & Shmatikov, V. (2015) · Proceedings of the 22nd ACM SIGSAC Conference on Computer and Communications Security · doi:10.1145/2810103.2813687 · Cited by 2,356
Data-efficient and weakly supervised computational pathology on whole-slide images
Lu, M. Y., Williamson, D. F. K., Chen, T. Y., Chen, R. J., Barbieri, M., & Mahmood, F. (2021) · Nature Biomedical Engineering · doi:10.1038/s41551-020-00682-w · Cited by 2,282
Self-citationZhu, L., & Han, S. (2020) · Lecture Notes in Computer Science · doi:10.1007/978-3-030-63076-8_2 · Cited by 1,906
Our Data, Ourselves: Privacy Via Distributed Noise Generation
Dwork, C., Kenthapadi, K., McSherry, F., Mironov, I., & Naor, M. (2006) · Lecture Notes in Computer Science · doi:10.1007/11761679_29 · Cited by 1,835
Artificial intelligence in digital pathology — new tools for diagnosis and precision oncology
Bera, K., Schalper, K. A., Rimm, D. L., Velcheti, V., & Madabhushi, A. (2019) · Nature Reviews Clinical Oncology · doi:10.1038/s41571-019-0252-y · Cited by 1,698
Secure, privacy-preserving and federated machine learning in medical imaging
Kaissis, G. A., Makowski, M. R., Rückert, D., & Braren, R. F. (2020) · Nature Machine Intelligence · doi:10.1038/s42256-020-0186-1 · Cited by 1,676 · cited 2×
“The design of countermeasures for increasing differential privacy is thus a very active field of research (Kaissis et al., 2020; Kairouz et al., 2019).”
BackgroundHover-Net: Simultaneous segmentation and classification of nuclei in multi-tissue histology images
Graham, S., Vu, Q. D., Raza, S. E. A., Azam, A. S., Tsang, Y. W., Kwak, J. T., & Rajpoot, N. (2019) · Medical Image Analysis · doi:10.1016/j.media.2019.101563 · Cited by 1,516
Attention-based Deep Multiple Instance LearningPreprint
Ilse, M., Tomczak, J. M., & Welling, M. (2018) · arXiv (Cornell University) · doi:10.48550/arxiv.1802.04712 · Cited by 1,428
Deep Models Under the GAN: Information Leakage from Collaborative Deep Learning
Hitaj, B., Ateniese, G., & Perez-Cruz, F. (2017) · Proceedings of the 2017 ACM SIGSAC Conference on Computer and Communications Security · doi:10.1145/3133956.3134012 · Cited by 1,377
Digital pathology and artificial intelligence
Niazi, M. K. K., Parwani, A. V., & Gurcan, M. N. (2019) · The Lancet Oncology · doi:10.1016/s1470-2045(19)30154-8 · Cited by 1,232
Predicting cancer outcomes from histology and genomics using convolutional networks
Mobadersany, P., Yousefi, S., Amgad, M., Gutman, D. A., Barnholtz-Sloan, J. S., Velázquez Vega, J. E., Brat, D. J., & Cooper, L. A. D. (2018) · Proceedings of the National Academy of Sciences · doi:10.1073/pnas.1717139115 · Cited by 1,084
Comprehensive and Integrated Genomic Characterization of Adult Soft Tissue Sarcomas
Abeshouse, A., Adebamowo, C., Adebamowo, S. N., Akbani, R., Akeredolu, T., Ally, A., Anderson, M. L., Anur, P., Appelbaum, E. L., Armenia, J., et al. (2017) · Cell · doi:10.1016/j.cell.2017.10.014 · Cited by 1,069
FedHealth: A Federated Transfer Learning Framework for Wearable Healthcare
Chen, Y., Qin, X., Wang, J., Yu, C., & Gao, W. (2020) · IEEE Intelligent Systems · doi:10.1109/mis.2020.2988604 · Cited by 1,005
Federated learning of predictive models from federated Electronic Health Records
Brisimi, T. S., Chen, R., Mela, T., Olshevsky, A., Paschalidis, I. C., & Shi, W. (2018) · International Journal of Medical Informatics · doi:10.1016/j.ijmedinf.2018.01.007 · Cited by 997 · cited 1×
“These include large-scale multicenter studies of genomics (Mandl et al., 2020; Rehm, 2017; Jagadeesh et al., 2017), electronic health records (Brisimi et al., 2018; Choud-hury et al., 2019a,b), or wearable health devices (Chen et al., 2020).”
BackgroundSelf-citationBeyond Inferring Class Representatives: User-Level Privacy Leakage From Federated Learning
Wang, Z., Song, M., Zhang, Z., Song, Y., Wang, Q., & Qi, H. (2019) · IEEE INFOCOM 2019 - IEEE Conference on Computer Communications · doi:10.1109/infocom.2019.8737416 · Cited by 881
Inverting Gradients -- How easy is it to break privacy in federated learning?Preprint
Geiping, J., Bauermeister, H., Dröge, H., & Moeller, M. (2020) · arXiv (Cornell University) · doi:10.48550/arxiv.2003.14053 · Cited by 848
Estimating the success of re-identifications in incomplete datasets using generative models
Rocher, L., Hendrickx, J. M., & de Montjoye, Y.-A. (2019) · Nature Communications · doi:10.1038/s41467-019-10933-3 · Cited by 816
Chen, R. J., Lu, M. Y., Wang, J., Williamson, D. F. K., Rodig, S. J., Lindeman, N. I., & Mahmood, F. (2022) · IEEE Transactions on Medical Imaging · doi:10.1109/tmi.2020.3021387 · Cited by 729
Self-citationBulten, W., Pinckaers, H., van Boven, H., Vink, R., de Bel, T., van Ginneken, B., van der Laak, J., Hulsbergen-van de Kaa, C., & Litjens, G. (2020) · The Lancet Oncology · doi:10.1016/s1470-2045(19)30739-9 · Cited by 705
histoCAT: analysis of cell phenotypes and interactions in multiplex image cytometry data
Schapiro, D., Jackson, H. W., Raghuraman, S., Fischer, J. R., Zanotelli, V. R., Schulz, D., Giesen, C., Catena, R., Varga, Z., & Bodenmiller, B. (2017) · Nature Methods · doi:10.1038/nmeth.4391 · Cited by 661
AI-based pathology predicts origins for cancers of unknown primary
Lu, M. Y., Chen, T. Y., Williamson, D. F. K., Zhao, M., Shady, M., Lipkova, J., & Mahmood, F. (2021) · Nature · doi:10.1038/s41586-021-03512-4 · Cited by 636
Self-citationYang (2019) · doi:10.1145/3339474 · Cited by 632
Sheller, M. J., Reina, G. A., Edwards, B., Martin, J., & Bakas, S. (2019) · Lecture Notes in Computer Science · doi:10.1007/978-3-030-11723-8_9 · Cited by 609
Privacy-Preserving Federated Brain Tumour Segmentation
Li, W., Milletarì, F., Xu, D., Rieke, N., Hancox, J., Zhu, W., Baust, M., Cheng, Y., Ourselin, S., Cardoso, M. J., et al. (2019) · Lecture Notes in Computer Science · doi:10.1007/978-3-030-32692-0_16 · Cited by 578
The Secret Revealer: Generative Model-Inversion Attacks Against Deep Neural Networks
Zhang, Y., Jia, R., Pei, H., Wang, W., Li, B., & Song, D. X. (2020) · IEEE Computer Society Conference on Computer Vision and Pattern Recognition/Proceedings - IEEE Computer Society Conference on Computer Vision and Pattern Recognition/Proceedings · doi:10.1109/cvpr42600.2020.00033 · Cited by 519
Li, X., Gu, Y., Dvornek, N., Staib, L. H., Ventola, P., & Duncan, J. S. (2020) · Medical Image Analysis · doi:10.1016/j.media.2020.101765 · Cited by 480
Dong, J., Roth, A., & Su, W. J. (2019) · arXiv · doi:10.48550/arxiv.1905.02383 · Cited by 389
Deep Adversarial Training for Multi-Organ Nuclei Segmentation in Histopathology Images
Mahmood, F., Borders, D., Chen, R. J., McKay, G. N., Salimian, K. J., Baras, A. S., & Durr, N. J. (2019) · IEEE Transactions on Medical Imaging · doi:10.1109/tmi.2019.2927182 · Cited by 361
Self-citationDistributed Differential Privacy via Shuffling
Cheu, A., Smith, A., Ullman, J., Zeber, D., & Zhilyaev, M. (2019) · Lecture Notes in Computer Science · doi:10.1007/978-3-030-17653-2_13 · Cited by 268
Silva, S., Gutman, B. A., Romero, E., Thompson, P. M., Altmann, A., & Lorenzi, M. (2019) · IEEE International Symposium on Biomedical Imaging (ISBI) · doi:10.1109/isbi.2019.8759317 · Cited by 225
CGC-Net: Cell Graph Convolutional Network for Grading of Colorectal Cancer Histology Images
Zhou, Y., Graham, S., Alemi Koohbanani, N., Shaban, M., Heng, P.-A., & Rajpoot, N. (2019) · 2019 IEEE/CVF International Conference on Computer Vision Workshop (ICCVW) · doi:10.1109/iccvw.2019.00050 · Cited by 225
BrainTorrent: A Peer-to-Peer Environment for Decentralized Federated Learning
Roy, A. G., Siddiqui, S., Pölsterl, S., Navab, N., & Wachinger, C. (2019) · arXiv · doi:10.48550/arxiv.1905.06731 · Cited by 212
Bias in Cross-Entropy-Based Training of Deep Survival Networks
Zadeh, S. G., & Schmid, M. C. (2020) · IEEE Transactions on Pattern Analysis and Machine Intelligence · doi:10.1109/tpami.2020.2979450 · Cited by 202
Modeling Discrete Time-to-Event Data
Tutz, G., & Schmid, M. C. (2016) · Springer series in statistics · doi:10.1007/978-3-319-28158-2 · Cited by 188
Differential privacy-enabled federated learning for sensitive health data
Choudhury, O., Gkoulalas-Divanis, A., Salonidis, T., Sylla, I., Park, Y., Hsu, G., & Das, A. (2019) · arXiv · doi:10.48550/arxiv.1910.02578 · Cited by 184
Estimation methods for time‐dependent AUC models with survival data
Hung, H., & Chiang, C. (2009) · Canadian Journal of Statistics · doi:10.1002/cjs.10046 · Cited by 181
Cellular community detection for tissue phenotyping in colorectal cancer histology images
Javed, S., Mahmood, A., Fraz, M. M., Koohbanani, N. A., Benes, K., Tsang, Y., Hewitt, K. J., Epstein, D., Snead, D. R. J., & Rajpoot, N. (2020) · Medical Image Analysis · doi:10.1016/j.media.2020.101696 · Cited by 175
Attention-based Deep Multiple Instance Learning
Ilse, M., Tomczak, J. M., & Welling, M. (2018) · UvA-DARE (University of Amsterdam) · Cited by 154
Automated acquisition of explainable knowledge from unannotated histopathology images
Yamamoto, Y., Tsuzuki, T., Akatsuka, J., Ueki, M., Morikawa, H., Numata, Y., Takahara, T., Tsuyuki, T., Tsutsumi, K., Nakazawa, R., et al. (2019) · Nature Communications · doi:10.1038/s41467-019-13647-8 · Cited by 150
Federated Transfer Learning for EEG Signal Classification
Ju, C., Gao, D., Mane, R., Tan, B., Liu, Y., & Guan, C. (2020) · Annual International Conference of the IEEE Engineering in Medicine and Biology Society (EMBC) · doi:10.1109/embc44109.2020.9175344 · Cited by 148
Evolving health care through personal genomics
Rehm, H. L. (2017) · Nature Reviews Genetics · doi:10.1038/nrg.2016.162 · Cited by 142
Deriving genomic diagnoses without revealing patient genomes
Jagadeesh, K. A., Wu, D. J., Birgmeier, J. A., Boneh, D., & Bejerano, G. (2017) · Science · doi:10.1126/science.aam9710 · Cited by 134
The Secret Sharer: Measuring Unintended Neural Network Memorization & Extracting SecretsPreprint
Carlini, N., Liu, C., Kos, J., Erlingsson, Ú., & Song, D. X. (2018) · arXiv (Cornell University) · Cited by 124
The use of digital pathology and image analysis in clinical trials
Pell, R., Oien, K. A., Robinson, M., Pitman, H., Rajpoot, N., Rittscher, J., Snead, D. R. J., & Verrill, C. L. (2019) · The Journal of Pathology Clinical Research · doi:10.1002/cjp2.127 · Cited by 113
Siloed Federated Learning for Multi-centric Histopathology Datasets
Andreux, M., du Terrail, J. O., Béguier, C., & Tramel, E. W. (2020) · Lecture notes in computer science · doi:10.1007/978-3-030-60548-3_13 · Cited by 111
Scheibner, J., Ienca, M., Kechagia, S., Troncoso-Pastoriza, J. R., Raisaro, J. L., Hubaux, J., Fellay, J., & Vayena, E. (2020) · Journal of Law and the Biosciences · doi:10.1093/jlb/lsaa010 · Cited by 101
Predicting Adverse Drug Reactions on Distributed Health Data using Federated Learning.
Choudhury, O., Park, Y., Salonidis, T., Gkoulalas-Divanis, A., Sylla, I., & Das, A. K. (2019) · PubMed Central · Cited by 89
Lu, M. Y., Chen, R. J., Wang, J., Dillon, D., & Mahmood, F. (2019) · arXiv (Cornell University) · doi:10.48550/arxiv.1910.10825 · Cited by 80
Self-citationWeakly Supervised Prostate Tma Classification Via Graph Convolutional Networks
Wang, J., Chen, R. J., Lu, M. Y., Baras, A. S., & Mahmood, F. (2020) · IEEE International Symposium on Biomedical Imaging (ISBI) · doi:10.1109/isbi45749.2020.9098534 · Cited by 69
Self-citationHistographs: graphs in histopathology
Anand, D., Gadiya, S., & Sethi, A. (2020) · Medical Imaging 2020: Digital Pathology · doi:10.1117/12.2550114 · Cited by 53
Lu, M. Y., Chen, R. J., & Mahmood, F. (2020) · SPIE Medical Imaging: Digital Pathology · doi:10.1117/12.2549627 · Cited by 49
Self-citationMandl, K. D., Glauser, T. A., Krantz, I. D., Avillach, P., Bartels, A., Beggs, A. H., Biswas, S., Bourgeois, F. T., Corsmo, J. J., Dauber, A. N., et al. (2019) · Genetics in Medicine · doi:10.1038/s41436-019-0646-3 · Cited by 43
Can pathology diagnostic services for cancer be stratified and serve global health?
Anglade, F., Milner, D. A., & Brock, J. E. (2020) · Cancer · doi:10.1002/cncr.32872 · Cited by 38
Unsupervised Subtyping of Cholangiocarcinoma Using a Deep Clustering Convolutional Autoencoder
Hassan, M., Sigel, C., Campanella, G. S. V., Boerner, T., Pak, L. M., Büttner, S., IJzermans, J. N. M., Koerkamp, B. G., Doukas, M., Jarnagin, W. R., et al. (2019) · Lecture notes in computer science · doi:10.1007/978-3-030-32239-7_67 · Cited by 34
Federated Survival Analysis with Discrete-Time Cox ModelsPreprint
Andreux, M., Manoel, A., Menuet, R., Saillard, C., & Simpson, C. (2020) · arXiv (Cornell University) · doi:10.48550/arxiv.2006.08997 · Cited by 20
Artificial intelligence can augment global pathology initiatives
Nabi, J. (2018) · The Lancet · doi:10.1016/s0140-6736(18)32209-8 · Cited by 11
Censoring-Aware Deep Ordinal Regression for Survival Prediction from Pathological Images
Xiao, L., Yu, J.-G., Liu, Z., Ou, J., Deng, S., Yang, Z., & Li, Y. (2020) · Lecture notes in computer science · doi:10.1007/978-3-030-59722-1_43 · Cited by 10
Research works printed but not linked: 1
- Carlini, N., Liu, C., Erlingsson, Ú., Kos, J. and Song, D., 2019. The secret sharer: Evaluating and testing unintended memorization in neural networks. In 28th {USENIX} Security Symposium ({USENIX} Security 19) (pp. 267-284).
Cited by
Sorted by citations
Federated learning for smart healthcare: A survey
Nguyen, D. C., Pham, Q.-V., Pathirana, P. N., Ding, M., Seneviratne, A., Lin, Z., Dobre, O., & Hwang, W.-J. (2023) · ACM Computing Surveys · doi:10.1145/3501296 · Cited by 827
Algorithmic fairness in artificial intelligence for medicine and healthcare
Chen, R. J., Wang, J. J., Williamson, D. F. K., Chen, T. Y., Lipkova, J., Lu, M. Y., Sahai, S., & Mahmood, F. (2023) · Nature Biomedical Engineering · doi:10.1038/s41551-023-01056-8 · Cited by 750
Self-citationFederated learning for medical image analysis: A survey
Guan, H., Yap, P.-T., Bozoki, A., & Liu, M. (2024) · Pattern Recognition · doi:10.1016/j.patcog.2024.110424 · Cited by 518
End-to-end privacy preserving deep learning on multi-institutional medical imaging
Kaissis, G., Ziller, A., Passerat-Palmbach, J., Ryffel, T., Usynin, D., Trask, A., Lima, I., Mancuso, J., Jungmann, F., Steinborn, M.-M., et al. (2021) · Nature Machine Intelligence · doi:10.1038/s42256-021-00337-8 · Cited by 513
Federated Learning and Differential Privacy for Medical Image Analysis
Adnan, M., Kalra, S., Cresswell, J. C., Taylor, G. W., & Tizhoosh, H. (2021) · doi:10.21203/rs.3.rs-1005694/v1 · Cited by 464
Metadata
- Authors
- Lu, M. Y., Chen, R. J., Kong, D., Lipkova, J., Singh, R., Williamson, D. F. K., Chen, T. Y., & Mahmood, F.
- Affiliations
- Broad Institute (US)
- Brigham and Women's Hospital (US)
- Northwell Health (US)
- Corresponding author
- Mahmood, Faisal
- Venue
- Medical Image Analysis
- Publisher
- Elsevier BV
- Published
- 2022-02
- Volume
- 76
- Pages
- 102298
- ISSN
- 1361-8415 (ISSN-L)
- PMC
- PMC9340569
- OpenAlex
- W3089056520
- Semantic Scholar
- f979f3571772b7ee16c24a1c135e1a87e86ba043
- Cited by
- 267
- References
- 65
- Citations by year
- 2026: 52 · 2025: 62 · 2024: 60 · 2023: 49 · 2022: 36
- FWCI
- 13.47
- Type
- journal article
- Language
- en
- Open access
- hybrid
- doi.org
- Licence
- Locations
- Medical Image Analysis (publishedVersion, cc-by-nc-nd)
- PubMed (publishedVersion)
- PubMed Central (acceptedVersion, cc-by-nc-nd)
- arXiv (Cornell University) (submittedVersion)
- arXiv (Cornell University)
- Funders
- Brigham and Women's Hospital
- National Institutes of Health
- National Human Genome Research Institute
- National Science Foundation
- National Institute of General Medical Sciences (R35GM138216)
- Topics
- Physical Sciences › Computer Science › Artificial Intelligence › AI in cancer detection
- Physical Sciences › Computer Science › Artificial Intelligence › Privacy-Preserving Technologies in Data
- Health Sciences › Medicine › Radiology, Nuclear Medicine and Imaging › Radiomics and Machine Learning in Medical Imaging
- Keywords
- federated learning, computational pathology, whole slide images, differential privacy, weakly supervised learning, survival prediction, patient stratification, privacy-preserving data sharing, histology, multicenter collaboration
- MeSH terms
- Algorithms, Histological Techniques, Humans, Privacy
About these checks
Registry, retraction, Cites and statistics results are computed, not judged, with one exception: a printed reference that no index lists is read once by a model before it counts as a citation error. Claims are extracted by a model and kept only when their quote appears verbatim in the text; each cited source is then checked, with a model’s help, for whether it says what the claim relies on. Those verdicts can be wrong — read the claim’s quote and the cited source before relying on one.
A language model drew the claims from the paper on 2026-10-09, under version 3 of the claim definition (model deepseek-v4.1-flash, prompt extract-v3).
A second model labelled each claim on 2026-10-09 (model jev-1.13-20260917, definition revision gold-guideline-v0.2).
Statistics and arithmetic are recomputed, not judged.
Confidence bands are shown only for fields calibrated on our annotated test set. None is calibrated yet, so no band is shown.
What counts as a claim ›How we measure confidence ›How we check this ›
Are you an author, or do you see a problem with this page? Request a review
