

The DOI matches its Crossref record; 214 of the 214 references it cites were found in a registry or an index; none of the 289 sources its claims cite is checked for support yet.
AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury
Open accessAbstract
INTRODUCTION There are currently more than 1000 prescription medications available for use in the United States and more than 100,000 over‐the‐counter herbal and dietary supplements (HDS) available for purchase in retail stores and online. In addition, the average adult American receives more than six prescription medications per year.1,2 Many of these drugs and HDS products have been implicated as causes of DILI. Furthermore, DILI is a leading reason for regulatory actions regarding drugs in development as well as those in the marketplace.1 Confidently establishing a diagnosis of DILI is difficult because of the need to exclude more common competing causes of liver injury, the protean clinical manifestations from an individual agent, and the lack of a validated diagnostic biomarker.3–5 This guidance was developed with the support and oversight of the American Association for the Study of Liver Diseases Practice Guidelines Committee, who chose to commission a guidance, rather than a guideline, because of the paucity of randomized controlled trials on this topic. This document was developed by consensus of an expert panel and provides guidance statements based on formal review and analysis of the literature on the topics and questions related to the needs of patients with drug and supplement–induced liver injury. The aim of this practice guidance is to provide recommendations regarding the common clinical, laboratory, and histological features seen in patients with DILI based on observational and epidemiological data reported in case series or DILI registries. In addition, expert opinion–based recommendations for patient management, including risk stratification, are provided to assist patients and practitioners. DILI classification DILI can be mechanistically classified as being either direct (i.e., dose‐dependent, intrinsic, and predictable) or idiosyncratic (largely dose‐independent, idiosyncratic, and unpredictable) (Table 1). Direct hepatotoxins such as acetaminophen (APAP) (N‐acetyl‐para‐aminophenol) can cause liver injury in nearly all exposed individuals if a threshold dose or duration is exceeded. In contrast, idiosyncratic hepatotoxins are usually neither dose‐related nor duration‐related but rather occur at varying times during or after drug administration.6 Idiosyncratic DILI is uncommon, with most approved drugs occurring in only 1 in 1000 to 1 in a million exposed individuals. Although most patients do not have rash, eosinophilia, or other hypersensitivity features at presentation, aberrant host immunity is implicated in most instances of idiosyncratic DILI.3 TABLE 1 - Proposed classification of DILI Mechanistic classification Direct hepatotoxicity Idiosyncratic hepatotoxicity Indirect hepatotoxicity Incidence Common Rare Intermediate Dose relatedness Yes No No Predictable Yes No Partially Reproduced in animal models Yes No Not usually Latency Rapid (days) Variable (days to years) Delayed (months) Phenotypes of injury Serum AST, ALT, or ALP elevations, hepatic necrosis, acute fatty liver, nodular regeneration Mixed or cholestatic hepatitis, bland cholestasis, chronic hepatitis Immune‐mediated hepatitis, fatty liver, chronic hepatitis Examples Acetaminophen, niacin, intravenous methotrexate Amoxicillin‐clavulanate, cephalosporins, isoniazid, nitrofurantoin Immune checkpoint inhibitors, anti‐CD20 monoclonal Ab, protein kinase inhibitors Touted mechanism of injury Intrinsic hepatotoxicity that is dose‐dependent Idiosyncratic host metabolic or immune reaction Indirect effect on liver or host immunity Source: Adapted from Björnsson et al.5 A third mechanism of hepatotoxicity is called indirect DILI, which arises when the biological action of the drug affects the host immune system, leading to a secondary form of liver injury. Like idiosyncratic DILI, indirect hepatotoxins are generally independent of the dose of medication administered and have a latency of weeks to months with varying clinical manifestations. Examples of indirect hepatotoxicity include the immune‐mediated hepatitis (IMH) observed with immune checkpoint inhibitors (ICIs) and reactivation of HBV infection following rituximab infusions.7,8 Guidance statements Clinicians should be familiar with the three main types of hepatotoxicity when evaluating patients with suspected DILI. Direct hepatotoxins such as APAP can cause liver injury in nearly all exposed individuals once a threshold dose or duration of use is exceeded. Idiosyncratic DILI is largely independent of the dose and duration of medication use and characterized by a low incidence and variable drug latency and clinical and histological features. Idiosyncratic DILI is believed to arise from an aberrant adaptive host immune response to the drug and/or its metabolite(s). Indirect hepatotoxins are generally independent of the dose administered and have a variable latency and manifestations that arise from the biological action of the drug on the liver and/ or host immune system. Ep
Overview
AI snapshot
Written from the paper’s full text.
TL;DR
This AASLD practice guidance summarizes drug-, herbal-, and dietary supplement–induced liver injury (DILI), covering classification, epidemiology, diagnosis, causality assessment, histology, management, and monitoring. It provides consensus guidance statements because randomized controlled trial evidence is sparse.
Key findings
- Idiosyncratic DILI is uncommon, with an estimated annual incidence of 14–19 per 100,000 in the general population (~60,000 US cases/year), higher in exposure-based electronic medical record studies (32.8–40 per 100,000) and up to 1.4% among medical inpatients.
- Herbal and dietary supplements (HDS) account for ~20% of adult DILI cases in the DILIN registry; in China, Korea, and Singapore, HDS account for 27%–62% of DILI cases. Amoxicillin-clavulanate is the most frequently implicated individual agent in many Western countries, whereas anti-tuberculosis agents dominate in Asian countries.
- Acetaminophen (APAP) is a dose-dependent hepatotoxin; in North America, APAP overdose is believed to cause 100,000 poison-control calls, 50,000 emergency room visits, and at least 500 deaths annually, and is the leading cause of acute liver failure among US adults.
- With drug discontinuation, ~80% of DILI patients fully recover; ~10% with severe hepatocellular DILI and jaundice are at risk of death or transplant, and spontaneous survival in DILI-related acute liver failure is only ~25%. Chronic DILI occurred in 21% of DILIN subjects at 6 months, with 10%–20% persistence beyond 6–12 months in guidance statements.
Methods
- The American Association for the Study of Liver Diseases Practice Guidelines Committee commissioned a guidance, rather than a guideline, because of the paucity of randomized controlled trials; it was developed by expert panel consensus with formal literature review and analysis.
- Evidence came largely from observational and epidemiological data in case series and DILI registries (e.g., DILIN, Spanish, Iceland, Latin America, China, India), supplemented by expert opinion for management and risk stratification.
- The document synthesizes guidance statements, diagnostic algorithms, and tables on DILI classification, etiologies, genetic associations, histologic phenotypes, causality assessment instruments, prognostic indices, and monitoring/management.
Limitations
- Stated in the paper: there is a paucity of randomized controlled trials on DILI, no validated diagnostic biomarker, and diagnosis remains difficult because it requires excluding more common competing causes of liver injury.
- Stated in the paper: causality assessment tools have important limitations—RUCAM weighting and risk factors are not evidence-based, RECAM has not been tested in regions with different DILI spectra, in HDS-induced injury, or in cases with more than one suspect drug, and DILIN expert opinion requires specialized expertise that limits generalizability.
- Stated in the paper and evident from the text: insufficient data exist to confirm age, sex, and race/ethnicity as reliable DILI susceptibility risk factors; HDS compositional complexity, adulteration, mislabeling, and batch variability confound assessment; and many recommendations rely on observational data and expert consensus rather than controlled trials.
Model-written summary. Check it against the paper before relying on it.
Integrity signals
Registry
Cites
Statistics
Figures
Verification
Claims the paper makes
186 Not checked yet · 71 No basis given · 23 Own interpretation · 1 Sources not found · 1 Own result
The paper states this without a source or data behind it here, so there is nothing to check it against. The quote shows it is in the paper.
In the paper
“The characteristic laboratory profile of APAP hepatotoxicity includes very high aminotransferase levels with low bilirubin.”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > Management of APAP overdose
plaincorrelational- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: unclear — It is unclear whether the paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
None of the sources cited for this claim have been checked yet.
In the paper
“Recent studies have shown that patients with HDS hepatoxicity leading to liver failure are more likely to die or undergo transplantation compared to patients with drug hepatoxicity.133,134”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > HDS hepatotoxicity, susceptibility factors, and outcomes
What the sources say
- Not checked yetcites [133] Kesar V Channen L Masood U Grewal P Ahmad J Roth NC. Liver transplantation for acute liver injury in asians is more likely due to herbal and dietary supplements. Liver Transpl. 2022; 28: 188– 99. 34370392 PMC8792150
- Not checked yetcites [134] Ghabril M Ma J Patidar KR Nephew L Desai AP Orman E. Eight fold increase in the dietary supplement related liver failure leading to transplant waitlisting over the last quarter century in the US. Liver Transpl. 2022; 28: 169– 79. 34331346
plaincorrelational- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: unclear — It is unclear whether the paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
In the paper
“If NAC is administered within 12 h of ingestion, it virtually assures that the liver damage will be minimal.”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > Management of APAP overdose
What the sources say
- Not checked yetcites [167] Prescott LF Critchley JA. The treatment of acetaminophen poisoning. Annu Rev Pharmacol Toxicol. 1983; 23: 87– 101. 6347057
boosteddirect- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: unclear — It is unclear whether the paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
The paper states this without a source or data behind it here, so there is nothing to check it against. The quote shows it is in the paper.
In the paper
“Development of signs and symptoms of liver failure (encephalopathy, primarily) are concerning, and once they are present, nearly one‐third of patients either die or require a liver transplant.”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > Management of APAP overdose
plaincorrelational- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: unclear — It is unclear whether the paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
None of the sources cited for this claim have been checked yet.
In the paper
“Outcomes have also generally improved over the past two decades, likely because of improvements in intensive care, with only 8% of patients undergoing transplantation.168,169”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > Prognosis
What the sources say
- Not checked yetcites [168] Koch DG Tillman H Durkalski V Lee WM Reuben A. Development of a model to predict transplant‐free survival of patients with acute liver failure. Clin Gastroenterol Hepatol. 2016; 14: 1199– 206. 27085756 PMC6055510
- Not checked yetcites [169] Larson AM Polson J Fontana RJ Davern TJ Lalani E Hynan LS. Acetaminophen‐induced acute liver failure: results of a United States multicenter, prospective study. Hepatology. 2005; 42: 1364– 72. 16317692
hedgedconditional- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: unclear — It is unclear whether the paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
The paper states this without a source or data behind it here, so there is nothing to check it against. The quote shows it is in the paper.
In the paper
“The remaining patients make a full and complete recovery within 7 days.”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > Management of APAP overdose
plain- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: unclear — It is unclear whether the paper’s conclusions depend on it.
- Based: unclear — It is unclear why the paper says it holds.
In the paper
“the DILIN has shown that supplements implicated in liver injury are frequently mislabeled.130”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > HDS hepatotoxicity, susceptibility factors, and outcomes
What the sources say
- Not checked yetcites [130] Navarro V Avula B Khan I Verma M Seeff L Serrano J. The contents of herbal and dietary supplements implicated in liver injury in the United States are frequently mislabeled. Hepatol Commun. 2019; 3: 792– 4. 31168513 PMC6545864
boosted- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: unclear — It is unclear whether the paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
In the paper
“Intravenous or orally administered NAC can prevent liver injury nearly completely if given within 12 h of ingestion”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > Prognosis
What the sources say
- Not checked yetcites [167] Prescott LF Critchley JA. The treatment of acetaminophen poisoning. Annu Rev Pharmacol Toxicol. 1983; 23: 87– 101. 6347057
plaindirect- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: unclear — It is unclear whether the paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
None of the sources cited for this claim have been checked yet.
In the paper
“Several randomized controlled trials have demonstrated no significant increase in the incidence of persistently elevated serum aminotransferase levels between statin and placebo therapy, including in patients with known chronic liver disease.198–200”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > Monitoring strategies for four commonly used medications
What the sources say
- Not checked yetcites [198] Pfeffer MA Keech A Sacks FM Cobbe SM Tonkin A Byington RP. Safety and tolerability of pravastatin in long term clinical trials. Circulation. 2002; 105: 2341– 6. 12021218
- Not checked yetcites [199] Lewis JH Mortensen ME Zweig S Fusco MJ Medoff JR Belder R. Efficacy and safety of high dose pravastatin in hypercholesterolemic patients with well‐compensated chronic liver disease: results of a prospective, randomized, double‐blind, placebo‐controlled multicenter trial. Hepatology. 2007; 46: 1453– 63. 17668878
- Not checked yetcites [200] Bays H Cohen DE Chalasani N Harrison SA. The National Lipid Association's statin safety task force. An assessment by the statin liver safety task force: 2014 update. J Clin Lipidol. 2014; 8(Suppl 3): S47– 57. 24793441
boosted- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
In the paper
“Finally, reintroduction of isoniazid after a DILI episode leads to recurrent liver injury in only 10% of patients but should only be done for patients with active, drug‐resistant TB.190”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > Monitoring strategies for four commonly used medications
What the sources say
- Not checked yetcites [190] Zuberi BF Zuberi FF Bader N Alvi H Salahuddin J. Comparison of British Thoracic Society and American Thoracic Society reintroduction guidelines for anti‐tuberculous therapy induced liver injury. J Pak Med Assoc. 2014; 64: 896– 9. 25252514
plaindirect- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: unclear — It is unclear whether the paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
- Probably not a substantial claim. 84
- It may state two separate claims as one. 83
The paper states this without a source or data behind it here, so there is nothing to check it against. The quote shows it is in the paper.
In the paper
“In countries in which the over‐the‐counter sale of APAP has been restricted, the incidence of serious APAP toxicity has fallen.”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > Prognosis
plaindirect- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: fails — The paper’s conclusions may not depend on it.
- Based: fails — The paper may give no reason why it holds.
Probably not a substantial claim. The paper’s conclusions may not depend on it. The paper may give no reason why it holds.
In the paper
“A focused analysis of GTE cases enrolled in the DILIN has led to recognition of the typical presentation of GTE as being hepatocellular and sometimes fatal, with a strong genetic association with HLA‐B*35:01.72”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > HDS hepatotoxicity, susceptibility factors, and outcomes
What the sources say
- Not checked yetcites [72] Hoofnagle JH Bonkovsky HL Phillips EJ Li YJ Ahmad J Barnhart H. HLA‐B*35:01 and green tea‐induced liver injury. Hepatology. 2021; 73: 2484– 93. 32892374 PMC8052949
boostedcorrelational- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: unclear — It is unclear whether the paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
In the paper
“Based on DILIN Registry data, HDS comprise approximately 20% of all cases of liver injury encountered in adults.28”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > Epidemiology of HDS use and liver injury
What the sources say
- Not checked yetcites [28] Navarro VJ Barnhart H Bonkovsky HL Davern T Fontana RJ Grant L. Liver injury from herbals and dietary supplements in the U.S. drug‐induced liver injury network. Hepatology. 2014; 60: 1399– 408. 25043597 PMC4293199
plain- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: fails — The paper’s conclusions may not depend on it.
- Based: passes — The paper gives a reason why it holds.
Probably not a substantial claim. The paper’s conclusions may not depend on it.
In the paper
“The coagulopathy can be severe, and a prolonged INR is a bad prognostic sign.168”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > Management of APAP overdose
What the sources say
- Not checked yetcites [168] Koch DG Tillman H Durkalski V Lee WM Reuben A. Development of a model to predict transplant‐free survival of patients with acute liver failure. Clin Gastroenterol Hepatol. 2016; 14: 1199– 206. 27085756 PMC6055510
plaincorrelational- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: unclear — It is unclear whether the paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
None of the sources cited for this claim have been checked yet.
In the paper
“The apoptotic index, which incorporates full‐length serum cytokeratin 18 (CK18) and caspase‐cleaved CK18 levels, may also be more sensitive than serum ALT in detecting liver injury and also be of prognostic value.212,213”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > SUMMARY/FUTURE DIRECTIONS > DILI biomarkers
What the sources say
- Not checked yetcites [212] Thulin P Nordahl G Gry M Yimer G Aklillu E Makonnen E. Keratin‐18 and microRNA‐122 complement alanine aminotransferase as novel safety biomarkers for drug‐induced liver injury in two human cohorts. Liver Int. 2014; 34: 367– 78. 24118944
- Not checked yetcites [213] Rutherford A King LY Hynan LS Vedvyas C Lin W Lee WM. Development of an accurate index for predicting outcomes of patients with acute liver failure. Gastroenterology. 2012; 143: 1237– 43. 22885329 PMC3480539
hedgedcorrelational- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: unclear — It is unclear whether the paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
In the paper
“The DILIN tested a multiplex lymphocyte proliferation assay but did not obtain informative results.217”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > SUMMARY/FUTURE DIRECTIONS > DILI biomarkers
What the sources say
- Not checked yetcites [217] Whritenour J Ko M Zong Q Wang J Tartaro K Schneider P. Development of a modified lymphocyte transformation test for diagnosing drug induced liver injury associated with an adaptive immune response. J Immunotoxicol. 2017; 14: 28– 31. PMC5505862 28121193
plain- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: unclear — It is unclear whether the paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
The paper states this without a source or data behind it here, so there is nothing to check it against. The quote shows it is in the paper.
In the paper
“Rarely, ICI‐related sclerosing cholangitis can present with a cholestatic pattern of liver test elevations.”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > Monitoring strategies for four commonly used medications
plaincorrelational- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: fails — The paper’s conclusions may not depend on it.
- Based: fails — The paper may give no reason why it holds.
Probably not a substantial claim. The paper’s conclusions may not depend on it. The paper may give no reason why it holds.
In the paper
“Fatalities arise in < 1% of patients with IMH and almost exclusively occur in those with jaundice.207”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > Monitoring strategies for four commonly used medications
What the sources say
- Not checked yetcites [207] Schneider BJ Naidoo J Santomasso BD Lacchetti C Adkins S Anadkat M. Management of immune‐related adverse events in patients treated with immune checkpoint inhibitor therapy: ASCO guideline update. J Clin Oncol. 2021; 39: 4073– 126. 34724392
plaincorrelational- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: fails — The paper’s conclusions may not depend on it.
- Based: passes — The paper gives a reason why it holds.
Probably not a substantial claim. The paper’s conclusions may not depend on it. It may state two separate claims as one.
In the paper
“In general, statins are safe to administer, but myalgias and myopathy may lead to early dose reduction or termination in up to 10% of treated patients.197”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > Monitoring strategies for four commonly used medications
What the sources say
- Not checked yetcites [197] Zhang H Plutzky J Skentzos S Morrison F Mar P Shubina M. Discontinuation of statins in routine care settings: a cohort study. Ann Intern Med. 2013; 158: 526– 34. 23546564 PMC3692286
hedgedconditional- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: unclear — It is unclear whether the paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
The paper states this without a source or data behind it here, so there is nothing to check it against. The quote shows it is in the paper.
In the paper
“Although many medications have been associated with liver‐related fatalities, only a minority carry a black box warning for hepatotoxicity.”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > Early detection of DILI in clinical practice
plain- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: fails — The paper’s conclusions may not depend on it.
- Based: passes — The paper gives a reason why it holds.
Probably not a substantial claim. The paper’s conclusions may not depend on it.
None of the sources cited for this claim have been checked yet.
In the paper
“Underreporting and poor adherence to American Thoracic Society guidelines are common in cases of isoniazid hepatotoxicity and are associated with hospitalization, death, and liver transplantation.187,188”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > Monitoring strategies for four commonly used medications
What the sources say
- Not checked yetcites [187] Singanayagam A Sridhar S Dhariwal J Abdel‐Aziz D Munro K Connell DW. A comparison between two strategies for monitoring hepatic function during antituberculous therapy. Am J Respir Crit Care Med. 2012; 185: 653– 9. 22198973
- Not checked yetcites [188] Hayashi PH Fontana RJ Chalasani NP Stolz AA Talwalkar JA Navarro VJ. Under‐reporting and poor adherence to monitoring guidelines for severe cases of isoniazid hepatotoxicity. Clin Gastroenterol Hepatol. 2015; 13: 1676– 82.e1. 25724701 PMC4653068
plaincorrelational- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: unclear — It is unclear whether the paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
None of the sources cited for this claim have been checked yet.
In the paper
“Other groups are exploring the development of in vitro test systems derived from circulating macrophages and human liver organoids, but further validation is needed.218,219”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > SUMMARY/FUTURE DIRECTIONS > DILI biomarkers
What the sources say
- Not checked yetcites [218] Benesic A Rotter I Dragoi D Weber S Buchholtz ML Gerbes AL. Development and validation of a test to identify drugs that cause idiosyncratic drug‐induced liver injury. Clin Gastroenterol Hepatol. 2018; 16: 1488– 94. 29723689
- Not checked yetcites [219] Shinozawa T Kimura M Cai Y Saiki N Yoneyama Y Ouchi R. High‐fidelity drug‐induced liver injury screen using human pluripotent stem cell‐derived organoids. Gastroenterology. 2021; 160: 831– 46.e10. 33039464 PMC7878295
plain- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: fails — The paper’s conclusions may not depend on it.
- Based: passes — The paper gives a reason why it holds.
Probably not a substantial claim. The paper’s conclusions may not depend on it. It may state two separate claims as one.
None of the sources cited for this claim have been checked yet.
In the paper
“Although the incidence of severe DILI appears to be lower than previously appreciated,180 isoniazid continues to be a leading cause of DILI‐related ALF in the United States and worldwide (Table 2).181–184”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > Monitoring strategies for four commonly used medications
What the sources say
- Not checked yetcites [180] Jiang F Yan H Liang L Du J Jin S Yang S. Incidence and risk factors of anti‐tuberculosis drug induced liver injury (DILI): large cohort study involving 4652 Chinese adult tuberculosis patients. Liver Int. 2021; 41: 1565– 75. 33866661
- Not checked yetcites [181] Nolan CM Goldberg SV Buskin SE. Hepatotoxicity associated with isoniazid preventative therapy. A 7‐year survey from a public health tuberculosis clinic. JAMA. 1999; 281: 1014– 8. 10086436
- Not checked yetcites [182] Sotgiu G Matteelli A Getahun H Girardi E Sañé Schepisi M Centis R. Monitoring toxicity in individuals receiving treatment for latent tuberculosis infection: a systematic review versus expert opinion. Eur Respir J. 2015; 45: 1170– 3. 25700378 PMC4391659
- Not checked yetcites [183] Saukkonen JJ Cohn DL Jasmer RM Schenker S Jereb JA Nolan CM. An official ATS statement: hepatotoxicity of antituberculosis therapy. Am J Respir Crit Care Med. 2006; 174: 935– 52. 17021358
- Not checked yetcites [184] Joint Tuberculosis Committee of the British Thoracic Society. Chemotherapy and management of tuberculosis in the United Kingdom: recommendations 1998. Thorax. 1998; 53: 536– 48. 9797751 PMC1745276
hedgeddirect- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: unclear — It is unclear whether the paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
In the paper
“Recent studies suggest that bona fide DILI is only responsible for 30% of cases of demonstrable liver injury in patients with advanced cancer, whereas hepatic metastases, sepsis, and other causes of liver disease account for the remainder, emphasizing the importance of contrast‐enhanced CT and MR scanning in evaluation of these patients.205”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > Monitoring strategies for four commonly used medications
What the sources say
- Not checked yetcites [205] Tsung I Dolan R Lao CD Fecher L Riggenbach K Yeboah‐Korang A. Liver injury is most commonly due to hepatic metastases rather than drug hepatotoxicity during pembrolizumab immunotherapy. Aliment Pharmacol Ther. 2020; 50: 800– 8. 31309615
hedged- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: unclear — It is unclear whether the paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
None of the sources cited for this claim have been checked yet.
In the paper
“They are prescribed to more than 50% of oncology patients with advanced solid organ tumors.8,203”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > Monitoring strategies for four commonly used medications
What the sources say
- Not checked yetcites [8] Lombardi A Mondelli MU. Review article: immune checkpoint inhibitors and the liver, from therapeutic efficacy to side effects. Aliment Pharm Ther. 2019; 50: 872– 84. 31378985
- Not checked yetcites [203] Haslam A Prasad V. Estimation of the percentage of us patients with cancer who are eligible for and respond to checkpoint inhibitor immunotherapy drugs. JAMA Net Open. 2019; 2: e192535. PMC6503493 31050774
plain- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: fails — The paper’s conclusions may not depend on it.
- Based: passes — The paper gives a reason why it holds.
Probably not a substantial claim. The paper’s conclusions may not depend on it.
The paper states this without a source or data behind it here, so there is nothing to check it against. The quote shows it is in the paper.
In the paper
“DILI biomarkers in development are currently being directed toward improved DILI diagnosis and prognosis as well as to provide mechanistic insight into DILI pathogenesis.”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > SUMMARY/FUTURE DIRECTIONS > DILI biomarkers
plain- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: fails — The paper’s conclusions may not depend on it.
- Based: passes — The paper gives a reason why it holds.
Probably not a substantial claim. The paper’s conclusions may not depend on it. It may state two separate claims as one.
The paper states this without a source or data behind it here, so there is nothing to check it against. The quote shows it is in the paper.
In the paper
“Currently available serum markers of liver injury (i.e., AST, ALT, ALP) are neither sensitive nor specific enough to detect early DILI, nor are they able to reliably predict clinical outcomes.”
- Also stated in: § DILI biomarkers · plain
“Currently available serum markers of liver injury such as serum AST, ALT, and ALP levels are not sensitive or specific enough to detect early DILI.”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > SUMMARY/FUTURE DIRECTIONS > DILI biomarkers
plain- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: unclear — It is unclear why the paper says it holds.
It may state two separate claims as one.
- Also stated in: § DILI biomarkers · plain
In the paper
“In addition, other studies have suggested that statins in patients with compensated chronic liver disease and cirrhosis may even reduce the risk of hepatocellular cancer and decompensation.201”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > Monitoring strategies for four commonly used medications
What the sources say
- Not checked yetcites [201] Athyros VG Boutari C Stavropoulos K Anagnostis P Imprialos KP Doumas M. Statins: an under‐appreciated asset for the prevention and treatment of NAFLD and NASH and the related cardiovascular risk. Cur Vasc Pharmacol. 2018; 16: 246– 53. 28676019
hedgedconditional- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: fails — The paper’s conclusions may not depend on it.
- Based: passes — The paper gives a reason why it holds.
Probably not a substantial claim. The paper’s conclusions may not depend on it.
None of the sources cited for this claim have been checked yet.
In the paper
“For example, the incidence appears to be higher in exposure‐based studies using electronic medical records (32.8 per 100,000 adult patients who received one of the top implicated drugs in the United States and 40 per 100,000 patients at a pediatric hospital).11,12”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > Epidemiology of idiosyncratic DILI
What the sources say
- Not checked yetcites [11] Shin J Hunt CM Suzuki A Papay JI Beach KJ Cheetham TC. Characterizing phenotypes and outcomes of drug‐associated liver injury using electronic medical record data. Pharmacoepidemiol Drug Saf. 2013; 22: 190– 8. 23258383
- Not checked yetcites [12] Sandritter TL Goldman JL Habiger CJ Daniel JF Lowry J Fischer RT. An electronic medical records‐based approach to identify idiosyncratic drug‐induced liver injury in children. Sci Rep. 2019; 9: 18090. 31792283 PMC6888850
hedgedcorrelational- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: fails — The paper’s conclusions may not depend on it.
- Based: passes — The paper gives a reason why it holds.
Probably not a substantial claim. The paper’s conclusions may not depend on it.
The paper states this without a source or data behind it here, so there is nothing to check it against. The quote shows it is in the paper.
In the paper
“DILI can be mechanistically classified as being either direct (i.e., dose‐dependent, intrinsic, and predictable) or idiosyncratic (largely dose‐independent, idiosyncratic, and unpredictable) (Table 1).”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > DILI classification
plain- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: fails — The paper’s conclusions may not depend on it.
- Based: passes — The paper gives a reason why it holds.
Probably not a substantial claim. The paper’s conclusions may not depend on it.
None of the sources cited for this claim have been checked yet.
In the paper
“A third mechanism of hepatotoxicity is called indirect DILI, which arises when the biological action of the drug affects the host immune system, leading to a secondary form of liver injury.”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > DILI classification
What the sources say
- Not checked yetcites [7] Loomba R Liang TJ. Hepatitis B reactivation associated with immune suppressive and biological modifier therapies: current concepts, management strategies, and future directions. Gastroenterology. 2017; 152: 1297– 309. 28219691 PMC5501983
- Not checked yetcites [8] Lombardi A Mondelli MU. Review article: immune checkpoint inhibitors and the liver, from therapeutic efficacy to side effects. Aliment Pharm Ther. 2019; 50: 872– 84. 31378985
plaindirect- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: fails — The paper’s conclusions may not depend on it.
- Based: passes — The paper gives a reason why it holds.
Probably not a substantial claim. The paper’s conclusions may not depend on it.
None of the sources cited for this claim have been checked yet.
In the paper
“Examples of indirect hepatotoxicity include the immune‐mediated hepatitis (IMH) observed with immune checkpoint inhibitors (ICIs) and reactivation of HBV infection following rituximab infusions.7,8”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > DILI classification
What the sources say
- Not checked yetcites [7] Loomba R Liang TJ. Hepatitis B reactivation associated with immune suppressive and biological modifier therapies: current concepts, management strategies, and future directions. Gastroenterology. 2017; 152: 1297– 309. 28219691 PMC5501983
- Not checked yetcites [8] Lombardi A Mondelli MU. Review article: immune checkpoint inhibitors and the liver, from therapeutic efficacy to side effects. Aliment Pharm Ther. 2019; 50: 872– 84. 31378985
plaindirect- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: unclear — It is unclear whether the paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
None of the sources cited for this claim have been checked yet.
In the paper
“The incidence of idiosyncratic DILI is even higher in hospitalized patients, being reported as high as 1.4% among medical inpatients.13–16”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > Epidemiology of idiosyncratic DILI
What the sources say
- Not checked yetcites [13] Meier Y Cavallaro M Roos M Pauli‐Magnus C Folkers G Meier PJ. Incidence of drug‐induced liver injury in medical inpatients. Eur J Clin Pharmacol. 2005; 61: 135– 43. 15726344
- Not checked yetcites [14] Xu H Chen Y Xu J Zhou Q. Drug‐induced liver injury in hospitalized patients with notably elevated alanine aminotransferase. World J Gastroenterol. 2012; 18: 5972– 8. 23139615 PMC3491606
- Not checked yetcites [15] Björnsson HK Olafsson S Bergmann OM Björnsson ES. A prospective study on the causes of notably raised alanine aminotransferase (ALT). Scand J Gastroenterol. 2016; 51: 594– 600. 26653080
- Not checked yetcites [16] Sistanizad M Peterson GM. Drug‐induced liver injury in the Australian setting. J Clin Pharm Ther. 2013; 38: 115– 20. 23350857
plaincorrelational- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: fails — The paper’s conclusions may not depend on it.
- Based: passes — The paper gives a reason why it holds.
Probably not a substantial claim. The paper’s conclusions may not depend on it.
None of the sources cited for this claim have been checked yet.
In the paper
“Like idiosyncratic DILI, indirect hepatotoxins are generally independent of the dose of medication administered and have a latency of weeks to months with varying clinical manifestations.”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > DILI classification
plain- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: unclear — It is unclear whether the paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
None of the sources cited for this claim have been checked yet.
In the paper
“Idiosyncratic DILI is uncommon, with an estimated annual incidence in the general population of 14 to 19 events per 100,000 inhabitants or 60,000 cases per year in the general US population.9,10”
- Also stated in: § Leading causes of idiosyncratic DILI worldwide · hedged
“The estimated annual incidence of idiosyncratic DILI in the general population is low (14–19/100,000) but higher in exposure‐based studies using electronic medical record data (33–40/100,000).”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > Epidemiology of idiosyncratic DILI
What the sources say
- Not checked yetcites [9] Björnsson ES Bergmann OM Björnsson HK Kvaran RB Olafsson S. Incidence, presentation, and outcomes in patients with drug‐induced liver injury in the general population of Iceland. Gastroenterology. 2013; 144: 1419– 25. 23419359
- Not checked yetcites [10] Sgro C Clinard F Ouazir K Chanay H Allard C Guilleminet C. Incidence of drug‐induced hepatic injuries: a French population‐based study. Hepatology. 2002; 36: 451– 5. 12143055
hedgedn = 60,000- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: fails — The paper’s conclusions may not depend on it.
- Based: passes — The paper gives a reason why it holds.
Probably not a substantial claim. The paper’s conclusions may not depend on it. It may state two separate claims as one.
- Also stated in: § Leading causes of idiosyncratic DILI worldwide · hedged
None of the sources cited for this claim have been checked yet.
In the paper
“For instance, HDS products surpass pharmaceuticals in China, Korea, and Singapore, accounting for 27%–62% of their DILI cases.22,25,26”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > Leading causes of idiosyncratic DILI worldwide
What the sources say
- Not checked yetcites [22] Shen T Liu Y Shang J Xie Q Li J Yan M. Incidence and etiology of drug‐induced liver injury in mainland China. Gastroenterology. 2019; 156: 2230– 41.e11. 30742832
- Not checked yetcites [25] Suk KT Kim DJ Kim CH Park SH Yoon JH Kim YS. A prospective nationwide study of drug‐induced liver injury in Korea. Am J Gastroenterol. 2012; 107: 1380– 7. 22733303
- Not checked yetcites [26] Wai CT. Presentation of drug‐induced liver injury in Singapore. Singapore Med J. 2006; 47: 116– 20. 16435052
plaincorrelational- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: unclear — It is unclear whether the paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
In the paper
“Histologic features typically observed in AIH, such as interface hepatitis, emperipolesis (the presence of an intact cell within the cytoplasm of another), and rosette formation, are also observed among DILI cases (89%, 34%, and 40%, respectively, in DILI cases) and are not pathognomonic for AIH.89”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > Approach to liver biopsy interpretation
What the sources say
- Not checked yetcites [89] Suzuki A Brunt EM Kleiner DE Miquel R Smyrk TC Andrade RJ. The use of liver biopsy evaluation in discrimination of idiopathic autoimmune hepatitis versus drug‐induced liver injury. Hepatology. 2011; 54: 931– 939. 21674554 PMC3192933
plain- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
The paper states this without a source or data behind it here, so there is nothing to check it against. The quote shows it is in the paper.
In the paper
“Although DILI is often attributed to repeated exposure to an oral agent, it is important to recognize that exposure to an intravenous agent, such as monoclonal antibodies, may also cause DILI.”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > Medication history
hedgedconditional- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: fails — The paper’s conclusions may not depend on it.
- Based: fails — The paper may give no reason why it holds.
Probably not a substantial claim. The paper’s conclusions may not depend on it. The paper may give no reason why it holds.
A conclusion the paper draws from its own results — it cites no other source for it, so there is none to check. The quote shows it is in the paper.
In the paper
“Insufficient data exist to confirm subject age, sex, and race and ethnicity as reliable risk factors for DILI susceptibility. However, some drugs are more likely to cause DILI in older individuals (e.g., amoxicillin‐clavulanate, isoniazid), whereas others are more commonly implicated in children (valproate, minocycline).”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > Leading causes of idiosyncratic DILI worldwide
hedgedcorrelational- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: unclear — It is unclear whether the paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
- Rests on an assumption: The available observational and epidemiological data from case series and DILI registries are adequate to support recommendations on the clinical, laboratory, and histological features of DILI.
In the paper
“DI‐AIH may show more portal neutrophilic infiltrates and be accompanied by cholestasis, whereas sporadic AIH may show a chronic “hepatitis” pattern, and the interface hepatitis will be dominated by plasma cells.89”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > Approach to liver biopsy interpretation
What the sources say
- Not checked yetcites [89] Suzuki A Brunt EM Kleiner DE Miquel R Smyrk TC Andrade RJ. The use of liver biopsy evaluation in discrimination of idiopathic autoimmune hepatitis versus drug‐induced liver injury. Hepatology. 2011; 54: 931– 939. 21674554 PMC3192933
hedgedcorrelational- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
The paper states this without a source or data behind it here, so there is nothing to check it against. The quote shows it is in the paper.
In the paper
“However, topical formulations of medications to the skin, eyes, or ears rarely, if ever, cause DILI because of the low dose of medication absorbed.”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > Medication history
plaindirect- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: fails — The paper’s conclusions may not depend on it.
- Based: passes — The paper gives a reason why it holds.
Probably not a substantial claim. The paper’s conclusions may not depend on it.
The paper states this without a source or data behind it here, so there is nothing to check it against. The quote shows it is in the paper.
In the paper
“Patients with recent hypotension, sepsis, or heart failure are at risk for ischemic liver injury, usually characterized by rapid and a marked increase in serum aminotransferase values followed by rapid decline with normal or near‐normal bilirubin levels.”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > Competing causes of liver injury
plainconditional- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: fails — The paper’s conclusions may not depend on it.
- Based: passes — The paper gives a reason why it holds.
Probably not a substantial claim. The paper’s conclusions may not depend on it. It may state two separate claims as one.
None of the sources cited for this claim have been checked yet.
In the paper
“Noticeable differences also exist between sexes, with women experiencing more frequent and severe hepatotoxicity.44,45”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > Leading causes of idiosyncratic DILI worldwide
What the sources say
- Not checked yetcites [44] Zopf Y Rabe C Neubert A Gassmann KG Rascher W Hahn EG. Women encounter ADRs more often than do men. Eur J Clin Pharmacol. 2008; 64: 999– 1004. 18604529
- Not checked yetcites [45] George N Chen M Yuen N Hunt CM Suzuki A. Interplay of gender, age and drug properties on reporting frequency of drug‐induced liver injury. Regul Toxicol Pharmacol. 2018; 94: 101– 7. 29407200
plaincorrelational- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: unclear — It is unclear whether the paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
In the paper
“Although standardized DILI incidence increases with patient age, this may be explained, in part, by greater medication use with increasing age.9”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > Leading causes of idiosyncratic DILI worldwide
What the sources say
- Not checked yetcites [9] Björnsson ES Bergmann OM Björnsson HK Kvaran RB Olafsson S. Incidence, presentation, and outcomes in patients with drug‐induced liver injury in the general population of Iceland. Gastroenterology. 2013; 144: 1419– 25. 23419359
hedgeddirect- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: unclear — It is unclear whether the paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
None of the sources cited for this claim have been checked yet.
In the paper
“The Drug‐Induced Liver Injury Network (DILIN) has demonstrated that trimethoprim‐sulfamethoxazole is the most common suspect drug among African Americans, whereas amoxicillin‐clavulanate is the leading cause in White populations.”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > Leading causes of idiosyncratic DILI worldwide
What the sources say
- Not checked yetcites [48] Fontana RJ Hayashi PH Gu J Reddy KR Barnhart H Watkins PB. Idiosyncratic drug‐induced liver injury is associated with substantial morbidity and mortality within 6 months from onset. Gastroenterology. 2014; 147: 96– 108.e4. 24681128 PMC4285559
- Not checked yetcites [49] Chalasani N Reddy KRK Fontana RJ Barnhart H Gu J Hayashi PH. Idiosyncratic drug induced liver injury in African‐Americans is associated with greater morbidity and mortality compared to Caucasians. Am J Gastroenterol. 2017; 112: 1382– 8. 28762375 PMC5667647
boosteddirect- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: unclear — It is unclear whether the paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
None of the sources cited for this claim have been checked yet.
In the paper
“In some instances, dose escalation may also increase the risk of developing idiosyncratic DILI as seen with azathioprine, whereas dose reduction or increasing the dosing interval may improve tolerability.35–37”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > Leading causes of idiosyncratic DILI worldwide
What the sources say
- Not checked yetcites [35] Carrascosa MF Salcines‐Caviedes JR Lucena MI Andrade RJ. Acute liver failure following atorvastatin dose escalation: is there a threshold dose for idiosyncratic hepatotoxicity? J Hepatol. 2015; 62: 751– 2. 25463547
- Not checked yetcites [36] Seki N Uematsu K Shibakuki R Eguchi K. Promising new treatment schedule for gefitinib responders after severe hepatotoxicity with daily administration. J Clin Oncol. 2006; 24: 3213– 5. 16809744
- Not checked yetcites [37] Otani K Kaneko S Tasaki H Fukushima Y. Hepatic injury caused by mianserin. BMJ. 1989; 299: 519. PMC1837346 2507056
hedgedconditional- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: unclear — It is unclear whether the paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
The paper states this without a source or data behind it here, so there is nothing to check it against. The quote shows it is in the paper.
In the paper
“In contrast, hypersensitivity reactions can have very short latency periods of only 24–72 h.”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > Medication history
plain- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: fails — The paper’s conclusions may not depend on it.
- Based: fails — The paper may give no reason why it holds.
Probably not a substantial claim. The paper’s conclusions may not depend on it. The paper may give no reason why it holds.
None of the sources cited for this claim have been checked yet.
In the paper
“In addition, African Americans were more likely to have adverse outcomes and develop chronic DILI.48,49”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > Leading causes of idiosyncratic DILI worldwide
What the sources say
- Not checked yetcites [48] Fontana RJ Hayashi PH Gu J Reddy KR Barnhart H Watkins PB. Idiosyncratic drug‐induced liver injury is associated with substantial morbidity and mortality within 6 months from onset. Gastroenterology. 2014; 147: 96– 108.e4. 24681128 PMC4285559
- Not checked yetcites [49] Chalasani N Reddy KRK Fontana RJ Barnhart H Gu J Hayashi PH. Idiosyncratic drug induced liver injury in African‐Americans is associated with greater morbidity and mortality compared to Caucasians. Am J Gastroenterol. 2017; 112: 1382– 8. 28762375 PMC5667647
plaincorrelational- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: unclear — It is unclear whether the paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
The paper states this without a source or data behind it here, so there is nothing to check it against. The quote shows it is in the paper.
In the paper
“Patients with pre‐existing liver disease are at increased risk of developing liver injury with selected drugs (e.g., methotrexate, anti‐TB therapy). In addition, subjects with pre‐existing liver disease are at increased risk of poor outcomes with a DILI episode.”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > Leading causes of idiosyncratic DILI worldwide
plaindirect- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: unclear — It is unclear why the paper says it holds.
It may state two separate claims as one.
- Rests on an assumption: The available observational and epidemiological data from case series and DILI registries are adequate to support recommendations on the clinical, laboratory, and histological features of DILI.
None of the sources cited for this claim have been checked yet.
In the paper
“The predominant histological pattern in ICI DILI is hepatocellular injury, with approximately 70% showing panlobular hepatitis and approximately 20% with centrilobular coagulative necrosis on liver biopsy.95–97”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > Approach to liver biopsy interpretation
What the sources say
- Not checked yetcites [95] Sawada K Hayashi H Nakajima S Hasebe T Fujiya M Okumura T. Non‐alcoholic fatty liver disease is a potential risk factor for liver injury caused by immune checkpoint inhibitor. J Gastroenterol Hepatol. 2020; 35: 1042– 8. 31752049
- Not checked yetcites [96] Zen Y Yeh MM. Checkpoint inhibitor‐induced liver injury: a novel form of liver disease emerging in the era of cancer immunotherapy. Semin Diagn Pathol. 2019; 36: 434– 440. 31358424
- Not checked yetcites [97] Zen Y Chen YY Jeng YM Tsai HW Yeh MM. Immune‐related adverse reactions in the hepatobiliary system: second‐generation check‐point inhibitors highlight diverse histological changes. Histopathology. 2020; 76: 470– 80. 31550390
plain- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: unclear — It is unclear whether the paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
A conclusion the paper draws from its own results — it cites no other source for it, so there is none to check. The quote shows it is in the paper.
In the paper
“In general, the identified HLA alleles have low positive predictive value, because of the low incidence of DILI in the general population, but a high negative predictive value.”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > Leading causes of idiosyncratic DILI worldwide
plaindirect- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
None of the sources cited for this claim have been checked yet.
In the paper
“Antimicrobials, central nervous system agents, and anti‐inflammatory agents are the most commonly implicated agents in the DILI series worldwide. However, HDS are most commonly implicated in some Asian countries and are increasingly implicated in Western countries as well.”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > Leading causes of idiosyncratic DILI worldwide
plaincorrelational- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: unclear — It is unclear whether the paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
- Rests on an assumption: The available observational and epidemiological data from case series and DILI registries are adequate to support recommendations on the clinical, laboratory, and histological features of DILI.
A conclusion the paper draws from its own results — it cites no other source for it, so there is none to check. The quote shows it is in the paper.
In the paper
“Furthermore, there are limited data exploring the impact of diet, tobacco use, and coffee consumption on DILI susceptibility.”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > Leading causes of idiosyncratic DILI worldwide
plain- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: fails — The paper’s conclusions may not depend on it.
- Based: passes — The paper gives a reason why it holds.
Probably not a substantial claim. The paper’s conclusions may not depend on it.
None of the sources cited for this claim have been checked yet.
In the paper
“In contrast, HDS products represent only a minority of cases in Japan, the United States, and Spain but with an increasing incidence over time.23,27–31”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > Leading causes of idiosyncratic DILI worldwide
What the sources say
- Not checked yetcites [23] Takikawa H Murata Y Horiike N Fukui H Onji M. Drug‐induced liver injury in Japan: an analysis of 1676 cases between 1997 and 2006. Hepatol Res. 2009; 39: 427– 31. 19207579
- Not checked yetcites [27] Andrade RJ Medina‐Caliz I Gonzalez‐Jimenez A Garcia‐Cortes M Lucena ML. Hepatic damage by natural remedies. Semin Liver Dis. 2018; 38: 21– 40. 29471563
- Not checked yetcites [28] Navarro VJ Barnhart H Bonkovsky HL Davern T Fontana RJ Grant L. Liver injury from herbals and dietary supplements in the U.S. drug‐induced liver injury network. Hepatology. 2014; 60: 1399– 408. 25043597 PMC4293199
- Not checked yetcites [29] Stephens C Robles‐Diaz M Medina‐Caliz I Garcia‐Cortes M Ortega‐Alonso A Sanabria‐Cabrera J. Comprehensive analysis and insights gained from long‐term experience of the Spanish DILI registry. J Hepatol. 2021; 75: 86– 97. 33539847
- Not checked yetcites [30] Chalasani N Bonkovsky HL Fontana RJ Lee W Stolz A Talwalkar J. Features and outcomes of 899 patients with drug‐induced liver injury: the DILIN prospective study. Gastroenterology. 2015; 148: 1340– 52.e7. 25754159 PMC4446235
- Not checked yetcites [31] Devarbhavi H Joseph T Kumar NS Rathi C Thomas V Singh SP. The Indian network of drug‐induced liver injury: etiology, clinical features, outcome and prognostic markers in 1288 patients. J Clin Exp Hepatol. 2021; 11: 288– 98. 33994711 PMC8103312
plaincorrelational- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: unclear — It is unclear whether the paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
None of the sources cited for this claim have been checked yet.
In the paper
“Medical comorbidities such as obesity and diabetes are associated with increased incidence and severity of DILI with specific drugs. However, the role of alcohol, tobacco, and diet in DILI susceptibility is not established.”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > Leading causes of idiosyncratic DILI worldwide
plaincorrelational- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: unclear — It is unclear whether the paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
- Rests on an assumption: The available observational and epidemiological data from case series and DILI registries are adequate to support recommendations on the clinical, laboratory, and histological features of DILI.
In the paper
“However, DILI caused by anti‐TB therapy has been associated with abnormal baseline serum aminotransferases, showing a stronger dose‐dependent association with the severity of liver enzyme elevation than older age.55”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > Leading causes of idiosyncratic DILI worldwide
What the sources say
- Not checked yetcites [55] Gray EL Goldberg HF. Baseline abnormal liver function tests are more important than age in the development of isoniazid‐induced hepatoxicity for patients receiving preventive therapy for latent tuberculosis infection. Intern Med J. 2016; 46: 281– 7. 26648478
plaincorrelational- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: unclear — It is unclear whether the paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
None of the sources cited for this claim have been checked yet.
In the paper
“Therefore, pretreatment HLA testing will likely not prove useful in most circumstances to prevent DILI, but HLA testing may be helpful in DILI diagnosis and causality assessment.59,60”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > Leading causes of idiosyncratic DILI worldwide
What the sources say
- Not checked yetcites [59] Kullak‐Ublick GA Andrade RJ Merz M End P Benesic A Gerbes AL. Drug‐induced liver injury: recent advances in diagnosis and risk assessment. Gut. 2017; 66: 1154– 64. 28341748 PMC5532458
- Not checked yetcites [60] Koido M Kawakami E Fukumura J Noguchi Y Ohori M Nio Y. Polygenic architecture informs potential vulnerability to drug‐induced liver injury. Nat Med. 2020; 26: 1541– 8. 32895570 PMC8482794
hedged- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
The paper states this without a source or data behind it here, so there is nothing to check it against. The quote shows it is in the paper.
In the paper
“Moreover, a given drug may be associated with more than one clinical profile.”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > Initial laboratory assessment
hedgedcorrelational- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: fails — The paper’s conclusions may not depend on it.
- Based: fails — The paper may give no reason why it holds.
Probably not a substantial claim. The paper’s conclusions may not depend on it. The paper may give no reason why it holds.
In the paper
“Although DILI may present with lower levels of laboratory abnormalities, up to 20% of individuals in the general population have mildly increased liver biochemistries because of NAFLD, alcohol, and other common conditions.74”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > Diagnostic approach to DILI
What the sources say
- Not checked yetcites [74] Fontana RJ Watkins PB Bonkovsky HL Chalasani N Davern T Serrano J. Drug‐induced liver injury network (DILIN) prospective study: rationale, design and conduct. Drug Saf. 2009; 32: 55– 68. 19132805 PMC3637941
plaindirect- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: fails — The paper’s conclusions may not depend on it.
- Based: passes — The paper gives a reason why it holds.
Probably not a substantial claim. The paper’s conclusions may not depend on it.
In the paper
“The LiverTox website provides a brief synopsis of the clinical features of idiosyncratic DILI due to more than 1000 prescription drugs and 60 HDS that are culled from the world's literature.”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > Competing causes of liver injury
What the sources say
- Not checked yetcites [5] Björnsson ES Hoofnagle JH. Categorization of drugs implicated in causing liver injury: critical assessment based on published case reports. Hepatology. 2016; 63: 590– 603. 26517184
plain- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: fails — The paper’s conclusions may not depend on it.
- Based: passes — The paper gives a reason why it holds.
Probably not a substantial claim. The paper’s conclusions may not depend on it.
The paper states this without a source or data behind it here, so there is nothing to check it against. The quote shows it is in the paper.
In the paper
“In addition, LiverTox provides a likelihood scale summarizing how many reports of bona fide hepatotoxicity have been attributed to a product as follows: category A, 50 or more reports; category B, 12–49 cases; category C, 4–11 cases; category D, 1–3 plausible cases; category E, no reports of liver injury; and category X, newly approved agents.”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > Competing causes of liver injury
plain- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: fails — The paper’s conclusions may not depend on it.
- Based: passes — The paper gives a reason why it holds.
Probably not a substantial claim. The paper’s conclusions may not depend on it.
The paper states this without a source or data behind it here, so there is nothing to check it against. The quote shows it is in the paper.
In the paper
“Amoxicillin‐clavulanate is the most frequently implicated individual agent in many western countries, whereas anti‐tuberculosis (TB) agents dominate in Asian countries (Table 2).”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > Leading causes of idiosyncratic DILI worldwide
plaincorrelational- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: unclear — It is unclear whether the paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
None of the sources cited for this claim have been checked yet.
In the paper
“In addition, older subjects appear to be at increased risk of isoniazid and amoxicillin‐clavulanate hepatotoxicity, whereas younger individuals are more prone to develop DILI from anticonvulsants and minocycline.45,46”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > Leading causes of idiosyncratic DILI worldwide
What the sources say
- Not checked yetcites [45] George N Chen M Yuen N Hunt CM Suzuki A. Interplay of gender, age and drug properties on reporting frequency of drug‐induced liver injury. Regul Toxicol Pharmacol. 2018; 94: 101– 7. 29407200
- Not checked yetcites [46] Fountain FF Tolley E Chrisman CR Self TH. Isoniazid hepatotoxicity associated with treatment of latent tuberculosis infection: a 7‐year evaluation from a public health tuberculosis clinic. Chest. 2005; 128: 116– 23. 16002924
hedgedcorrelational- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: unclear — It is unclear whether the paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
In the paper
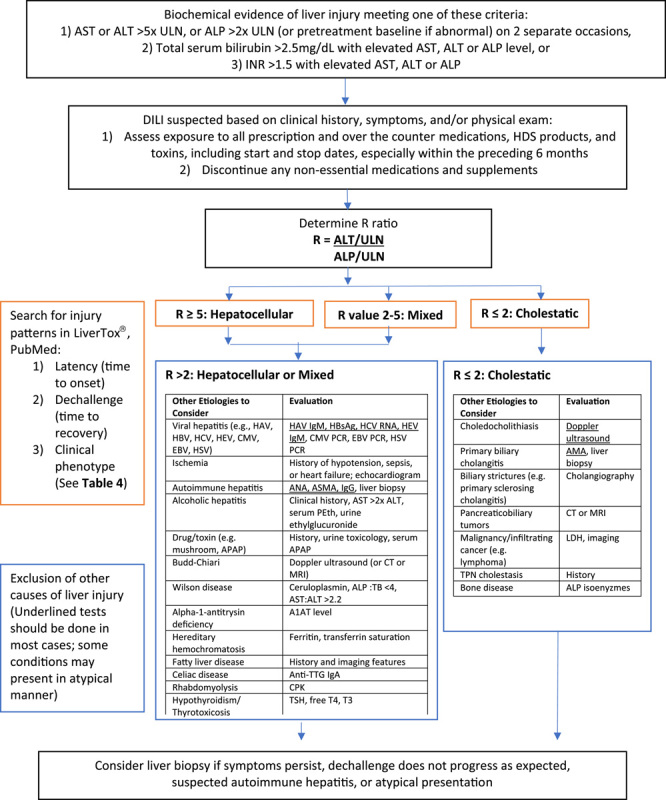
“The R‐value is best calculated at the time of presentation, but the pattern of injury can change as the condition progresses.77”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > Initial laboratory assessment
What the sources say
- Not checked yetcites [77] Benichou C Danan G Flahault A. Causality assessment of adverse reactions to drugs. Part II: an original model for validation of drug causality assessment methods: case reports with positive rechallenge. J Clin Epidemiol. 1993; 46: 1331– 6. 8229111
plain- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: unclear — It is unclear whether the paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
The paper states this without a source or data behind it here, so there is nothing to check it against. The quote shows it is in the paper.
In the paper
“Typically, DILI appears within 6 months of starting a new medication, although certain drugs have longer latency periods (e.g., nitrofurantoin, methotrexate).”
- Also stated in: § Competing causes of liver injury · plain
“Most hepatotoxic drugs cause liver injury within the first 6 months of use but occasionally have longer latency intervals or may even present after drug discontinuation (e.g., amoxicillin‐clavulanate).”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > Medication history
plaindirect- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: unclear — It is unclear whether the paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
- Also stated in: § Competing causes of liver injury · plain
None of the sources cited for this claim have been checked yet.
In the paper
“A French population‐based study showed that the standardized DILI incidence was more than 2 times higher in women than men older than 50 years, although no sex differences were noted under age 50.9,10”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > Leading causes of idiosyncratic DILI worldwide
What the sources say
- Not checked yetcites [9] Björnsson ES Bergmann OM Björnsson HK Kvaran RB Olafsson S. Incidence, presentation, and outcomes in patients with drug‐induced liver injury in the general population of Iceland. Gastroenterology. 2013; 144: 1419– 25. 23419359
- Not checked yetcites [10] Sgro C Clinard F Ouazir K Chanay H Allard C Guilleminet C. Incidence of drug‐induced hepatic injuries: a French population‐based study. Hepatology. 2002; 36: 451– 5. 12143055
plaincorrelational- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: unclear — It is unclear whether the paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
None of the sources cited for this claim have been checked yet.
In the paper
“Being overweight, having diabetes, alcohol use, and chronic viral hepatitis have also been associated with progressive fibrosis in methotrexate‐treated patients.51,52”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > Leading causes of idiosyncratic DILI worldwide
What the sources say
- Not checked yetcites [51] Laharie D Seneschal J Schaeverbeke T Doutre MS Longy‐Boursier M Pellegrin JL. Assessment of liver fibrosis with transient elastography and FibroTest in patients treated with methotrexate for chronic inflammatory diseases: a case‐control study. J Hepatol. 2010; 53: 1035– 40. 20801541
- Not checked yetcites [52] Rosenberg P Urwitz H Johannesson A Ros AM Lindholm J Kinnman N. Psoriasis patients with diabetes type 2 are at high risk of developing liver fibrosis during methotrexate treatment. J Hepatol. 2007; 46: 1111– 8. 17399848
plaincorrelational- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: unclear — It is unclear whether the paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
In the paper
“The Maria‐Victorino Clinical Diagnostic Scale (CDS)109 uses similar variables to the RUCAM but excludes concomitant medications and includes points for extrahepatic manifestations.”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > Models of causality assessment
What the sources say
- Not checked yetcites [109] Maria VA Victorino RM. Development and validation of a clinical scale for the diagnosis of drug‐induced hepatitis. Hepatology. 1997; 26: 664– 9. 9303497
plain- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: fails — The paper’s conclusions may not depend on it.
- Based: passes — The paper gives a reason why it holds.
Probably not a substantial claim. The paper’s conclusions may not depend on it. It may state two separate claims as one.
The paper states this without a source or data behind it here, so there is nothing to check it against. The quote shows it is in the paper.
In the paper
“Notwithstanding, RECAM has yet to be tested in regions of the world where the spectrum of DILI agents differs from that seen in the United States and Spain (Table 2) or in cases with more than a single suspect drug.”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > Limitations of causality assessment in DILI
plain- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: unclear — It is unclear whether the paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
In the paper
“This semiautomated, computerized platform has a dynamic range of −6 to +20 points and performs at least as well as the RUCAM in independent data sets.113”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > Models of causality assessment
What the sources say
- Not checked yetcites [113] Hayashi PH Lucena MI Fontana RJ Bjornsson E Aithal GP Barnhart H. A revised electronic version of RUCAM for the diagnosis of drug induced liver injury. Hepatology. 2022; 76: 18– 31. 35014066 PMC9233102
plain- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: unclear — It is unclear whether the paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
In the paper
“Although the DDW‐J was shown to be superior to the original RUCAM in Japanese patients, it is not currently used outside of Japan because of the lack of widely available and reproducible DLST assays.112”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > Models of causality assessment
What the sources say
- Not checked yetcites [112] Hanatani T Sai K Tohkin M Segawa K Kimura M Hori K. A detection algorithm for drug‐induced liver injury in medical information databases using the Japanese diagnostic scale and its comparison with the Council for International Organizations of medical sciences/the Roussel Uclaf causality assessment method scale. Pharmacoepidemiol Drug Saf. 2014; 23: 984– 8. 24596340
plaindirect- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: unclear — It is unclear whether the paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
The paper states this without a source or data behind it here, so there is nothing to check it against. The quote shows it is in the paper.
In the paper
“The updated RUCAM also provides more specific guidance in ascertaining the hepatotoxicity profile of the suspect drug”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > Limitations of causality assessment in DILI
plaindirect- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: fails — The paper’s conclusions may not depend on it.
- Based: passes — The paper gives a reason why it holds.
Probably not a substantial claim. The paper’s conclusions may not depend on it.
None of the sources cited for this claim have been checked yet.
In the paper
“specifies criteria for rechallenge”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > Limitations of causality assessment in DILI
What the sources say
- Not checked yetcites [108] Danan G Teschke R. RUCAM in drug and herb induced liver injury: the update. Int J Mol Sci. 2016; 27: 14– 30. PMC4730261 26712744
- Not checked yetcites [119] Teschke R Frenzel C Schulze J Eickhoff A. Herbal hepatotoxicity: challenges and pitfalls of causality assessment methods. World J Gastroenterol. 2013; 19: 2864– 82. 23704820 PMC3660812
plain- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: fails — The paper’s conclusions may not depend on it.
- Based: passes — The paper gives a reason why it holds.
Probably not a substantial claim. The paper’s conclusions may not depend on it.
In the paper
“In the acute cholestatic type, cholestasis without accompanying inflammation (so‐called bland cholestasis) may be the sole histological presentation and manifests as bile present in dilated canaliculi and within the hepatocyte cytoplasm.98”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > Approach to liver biopsy interpretation
What the sources say
- Not checked yetcites [98] Zhang X Ouyang J Thung SN. Histopathologic manifestations of drug‐induced hepatotoxicity. Clin Liver Dis. 2013; 17: 547– 64. 24099017
hedged- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: unclear — It is unclear whether the paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
The paper states this without a source or data behind it here, so there is nothing to check it against. The quote shows it is in the paper.
In the paper
“The RECAM is a newly developed, computerized causality assessment instrument”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > Limitations of causality assessment in DILI
plain- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: fails — The paper’s conclusions may not depend on it.
- Based: passes — The paper gives a reason why it holds.
Probably not a substantial claim. The paper’s conclusions may not depend on it.
In the paper
“contemporary HDS are commonly multi‐ingredient products that are marketed under the guise of delivering some improvement in appearance, performance, or sense of well‐being.124”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > HDS hepatotoxicity
What the sources say
- Not checked yetcites [124] Huang YS Chang TT Peng CY Lo GH Hsu CW Hu CT. Herbal and dietary supplement‐induced liver injury in Taiwan: comparison with conventional drug‐induced liver injury. Hepatol Int. 2021; 15: 1456– 65. 34382132
plain- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: fails — The paper’s conclusions may not depend on it.
- Based: passes — The paper gives a reason why it holds.
Probably not a substantial claim. The paper’s conclusions may not depend on it.
A conclusion the paper draws from its own results — it cites no other source for it, so there is none to check. The quote shows it is in the paper.
In the paper
“Advantages of expert opinion include the ability to account for atypical cases, interrupted drug exposure, and synthesis of subtle clues including liver histology in relationship to published literature.”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > Models of causality assessment
plaindirect- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: fails — The paper’s conclusions may not depend on it.
- Based: passes — The paper gives a reason why it holds.
Probably not a substantial claim. The paper’s conclusions may not depend on it.
In the paper
“Overall, jaundice and liver failure are rare in DILI because of ICI, and approximately a third of those with severe grades of DILI may even regress spontaneously.97”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > Approach to liver biopsy interpretation
What the sources say
- Not checked yetcites [97] Zen Y Chen YY Jeng YM Tsai HW Yeh MM. Immune‐related adverse reactions in the hepatobiliary system: second‐generation check‐point inhibitors highlight diverse histological changes. Histopathology. 2020; 76: 470– 80. 31550390
hedged- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: unclear — It is unclear whether the paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
The paper states this without a source or data behind it here, so there is nothing to check it against. The quote shows it is in the paper.
In the paper
“The RECAM is currently available online.”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > Models of causality assessment
plain- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: fails — The paper’s conclusions may not depend on it.
- Based: passes — The paper gives a reason why it holds.
Probably not a substantial claim. The paper’s conclusions may not depend on it.
None of the sources cited for this claim have been checked yet.
In the paper
“Structured expert opinion: The semiquantitative scale developed by DILIN categorizes the likelihood of DILI into five probability groups that vary from < 25% to > 95% probability (Table 6).74,116,117”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > Models of causality assessment
What the sources say
- Not checked yetcites [74] Fontana RJ Watkins PB Bonkovsky HL Chalasani N Davern T Serrano J. Drug‐induced liver injury network (DILIN) prospective study: rationale, design and conduct. Drug Saf. 2009; 32: 55– 68. 19132805 PMC3637941
- Not checked yetcites [116] Tillmann HL Suzuki A Barnhart HX Serrano J Rockey DC. Tools for causality assessment in drug‐induced liver disease. Curr Opin Gastroenterol. 2019; 35: 183– 90. 30865042 PMC6452904
- Not checked yetcites [117] Hayashi PH Barnhart HX Fontana RJ Chalasani N Davern TJ Talwalkar JA. Reliability of causality assessment for drug, herbal and dietary supplement hepatotoxicity in the drug‐induced liver injury network (DILIN). Liver Int. 2015; 35: 1623– 32. 24661785 PMC4305346
plain- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: fails — The paper’s conclusions may not depend on it.
- Based: passes — The paper gives a reason why it holds.
Probably not a substantial claim. The paper’s conclusions may not depend on it.
The paper states this without a source or data behind it here, so there is nothing to check it against. The quote shows it is in the paper.
In the paper
“and its interrater and intrarater reliability needs to be determined.”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > Limitations of causality assessment in DILI
plain- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: fails — The paper’s conclusions may not depend on it.
- Based: passes — The paper gives a reason why it holds.
Probably not a substantial claim. The paper’s conclusions may not depend on it.
In the paper
“Peliosis hepatis appears as blood‐filled lacunar spaces, and its development is associated with androgens and oral contraceptive agents.102”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > Approach to liver biopsy interpretation
What the sources say
- Not checked yetcites [102] Tsirigotis P Sella T Shapira MY Bitan M Bloom A Kiselgoff D. Peliosis hepatis following treatment with androgen‐steroids in patients with bone marrow failure syndromes. Haematologica. 2007; 92: e106– 10. 18024386
plaincorrelational- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: fails — The paper’s conclusions may not depend on it.
- Based: passes — The paper gives a reason why it holds.
Probably not a substantial claim. The paper’s conclusions may not depend on it. It may state two separate claims as one.
In the paper
“Causality assessment by expert opinion addresses the unique clinical features of a particular patient along with knowledge of the hepatotoxic potential of the suspect agent versus other causes of liver injury.122”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > Limitations of causality assessment in DILI
What the sources say
- Not checked yetcites [122] Rochon J Protiva P Seeff LB Fontana RJ Liangpunsakul S Watkins PB. Reliability of the Roussel Uclaf causality assessment method for assessing causality in drug‐induced liver injury. Hepatology. 2008; 48: 1175– 83. 18798340 PMC3618289
plaindirect- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
Probably not a substantial claim.
In the paper
“more than 50% of adults over the age of 20 used dietary supplements in the preceding 30 days in a 2017–2018 study.123”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > HDS hepatotoxicity
What the sources say
- Not checked yetcites [123] Mishra S Stierman B Gahche JJ Potischman N. Dietary supplement use among adults: United States, 2017–2018. NCHS Data Brief. 2021; 399: 1– 8. 33663653
plain- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: fails — The paper’s conclusions may not depend on it.
- Based: passes — The paper gives a reason why it holds.
Probably not a substantial claim. The paper’s conclusions may not depend on it.
None of the sources cited for this claim have been checked yet.
In the paper
“The Digestive Disease Week–Japan 2004 (DDW‐J) score is a modification of the RUCAM with the inclusion of drug‐lymphocyte stimulation test (DLST) results and peripheral eosinophilia.111,112”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > Models of causality assessment
What the sources say
- Not checked yetcites [111] Takikawa H Takamori Y Kumagi T Onji M Watanabe M Shibuya A. Assessment of 287 Japanese cases of drug induced liver injury by the diagnostic scale of the international consensus meeting. Hepatol Res. 2003; 27: 192– 5. 14585395
- Not checked yetcites [112] Hanatani T Sai K Tohkin M Segawa K Kimura M Hori K. A detection algorithm for drug‐induced liver injury in medical information databases using the Japanese diagnostic scale and its comparison with the Council for International Organizations of medical sciences/the Roussel Uclaf causality assessment method scale. Pharmacoepidemiol Drug Saf. 2014; 23: 984– 8. 24596340
plain- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: fails — The paper’s conclusions may not depend on it.
- Based: passes — The paper gives a reason why it holds.
Probably not a substantial claim. The paper’s conclusions may not depend on it.
The paper states this without a source or data behind it here, so there is nothing to check it against. The quote shows it is in the paper.
In the paper
“The semiquantitative expert opinion causality assessment scale developed by the DILIN is frequently used in clinical practice and in prospective research studies”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > Limitations of causality assessment in DILI
plain- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: fails — The paper’s conclusions may not depend on it.
- Based: passes — The paper gives a reason why it holds.
Probably not a substantial claim. The paper’s conclusions may not depend on it.
None of the sources cited for this claim have been checked yet.
In the paper
“The updated RUCAM has improved user instructions and more complete diagnostic evaluation compared with the original RUCAM”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > Limitations of causality assessment in DILI
plaindirect- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: fails — The paper’s conclusions may not depend on it.
- Based: passes — The paper gives a reason why it holds.
Probably not a substantial claim. The paper’s conclusions may not depend on it.
The paper states this without a source or data behind it here, so there is nothing to check it against. The quote shows it is in the paper.
In the paper
“Intentional suspect drug rechallenge is rarely undertaken in clinical practice”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > Limitations of causality assessment in DILI
plain- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: fails — The paper’s conclusions may not depend on it.
- Based: fails — The paper may give no reason why it holds.
Probably not a substantial claim. The paper’s conclusions may not depend on it. The paper may give no reason why it holds.
The paper states this without a source or data behind it here, so there is nothing to check it against. The quote shows it is in the paper.
In the paper
“There are five likelihood categories, but the dynamic range of possible scores is more compressed compared with the RUCAM and the Revised Electronic Causality Assessment Method (RECAM).”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > Models of causality assessment
plain- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: fails — The paper’s conclusions may not depend on it.
- Based: passes — The paper gives a reason why it holds.
Probably not a substantial claim. The paper’s conclusions may not depend on it. It may state two separate claims as one.
In the paper
“The updated RUCAM score was published in 2016 and has several modifications that generates a score ranging from −9 to +14 points with the same five likelihood categories.108”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > Models of causality assessment
What the sources say
- Not checked yetcites [108] Danan G Teschke R. RUCAM in drug and herb induced liver injury: the update. Int J Mol Sci. 2016; 27: 14– 30. PMC4730261 26712744
plain- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: fails — The paper’s conclusions may not depend on it.
- Based: passes — The paper gives a reason why it holds.
Probably not a substantial claim. The paper’s conclusions may not depend on it. It may state two separate claims as one.
In the paper
“In contrast, a liver biopsy defines chronic liver disease when there is significant fibrosis or even cirrhosis noted on histology.104”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > DILI severity and prognosis
What the sources say
- Not checked yetcites [104] Kleiner DE. Liver histology in the diagnosis and prognosis of drug‐induced liver injury. Clin Liver Dis (Hoboken). 2014; 4: 12– 6. 30992912 PMC6448725
plain- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: fails — The paper’s conclusions may not depend on it.
- Based: passes — The paper gives a reason why it holds.
Probably not a substantial claim. The paper’s conclusions may not depend on it.
None of the sources cited for this claim have been checked yet.
In the paper
“The updated RUCAM has improved user instructions and more complete diagnostic evaluation compared with the original RUCAM”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > Limitations of causality assessment in DILI
plaindirect- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: fails — The paper’s conclusions may not depend on it.
- Based: passes — The paper gives a reason why it holds.
Probably not a substantial claim. The paper’s conclusions may not depend on it.
None of the sources cited for this claim have been checked yet.
In the paper
“According to DILIN, chronic DILI is the perpetuation of liver damage after 6 months from DILI onset, independent of the pattern of liver injury, whereas the Spanish DILI Group considers 1 year as the best cutoff point.48,106”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > DILI severity and prognosis
What the sources say
- Not checked yetcites [48] Fontana RJ Hayashi PH Gu J Reddy KR Barnhart H Watkins PB. Idiosyncratic drug‐induced liver injury is associated with substantial morbidity and mortality within 6 months from onset. Gastroenterology. 2014; 147: 96– 108.e4. 24681128 PMC4285559
- Not checked yetcites [106] Medina‐Caliz I Robles‐Diaz M Garcia‐Munoz B Stephens C Ortega‐Alonso A Garcia‐Cortes M. Definition and risk factors for chronicity following acute idiosyncratic drug‐induced liver injury. J Hepatol. 2016; 65: 532– 42. 27184533 PMC7458366
plain- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: fails — The paper’s conclusions may not depend on it.
- Based: passes — The paper gives a reason why it holds.
Probably not a substantial claim. The paper’s conclusions may not depend on it. It may state two separate claims as one.
None of the sources cited for this claim have been checked yet.
In the paper
“It provides a score varying from −10 to +14 points and groups the scores into five likelihood categories with stratification by hepatocellular versus cholestatic/mixed injury.”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > Models of causality assessment
What the sources say
- Not checked yetcites [75] Danan G Benichou C. Causality assessment of adverse reactions to drugs. Part I: a novel method based on the conclusions of international consensus meetings: application to drug‐induced liver injuries. J Clin Epidemiol. 1993; 46: 1323– 30. 8229110
- Not checked yetcites [77] Benichou C Danan G Flahault A. Causality assessment of adverse reactions to drugs. Part II: an original model for validation of drug causality assessment methods: case reports with positive rechallenge. J Clin Epidemiol. 1993; 46: 1331– 6. 8229111
plain- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: fails — The paper’s conclusions may not depend on it.
- Based: passes — The paper gives a reason why it holds.
Probably not a substantial claim. The paper’s conclusions may not depend on it. It may state two separate claims as one.
None of the sources cited for this claim have been checked yet.
In the paper
“HDS are used widely around the world on a daily basis.”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > HDS hepatotoxicity
plain- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: fails — The paper’s conclusions may not depend on it.
- Based: passes — The paper gives a reason why it holds.
Probably not a substantial claim. The paper’s conclusions may not depend on it.
The paper states this without a source or data behind it here, so there is nothing to check it against. The quote shows it is in the paper.
In the paper
“NRH and OPV may clinically present insidiously, whereas SOS may manifest as either acute or chronic disease.”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > Approach to liver biopsy interpretation
hedged- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: unclear — It is unclear whether the paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
The paper states this without a source or data behind it here, so there is nothing to check it against. The quote shows it is in the paper.
In the paper
“Structured causality assessment instruments incorporate the dose, duration, and timing of suspect drug and other concomitant drug or HDS product use; an assessment of the laboratory, radiological, and histological features at presentation; and exclusion of competing causes of liver injury.”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > Limitations of causality assessment in DILI
plain- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: fails — The paper’s conclusions may not depend on it.
- Based: passes — The paper gives a reason why it holds.
Probably not a substantial claim. The paper’s conclusions may not depend on it.
The paper states this without a source or data behind it here, so there is nothing to check it against. The quote shows it is in the paper.
In the paper
“Although most marketed supplements are safe”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > HDS hepatotoxicity
plain- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: fails — The paper’s conclusions may not depend on it.
- Based: fails — The paper may give no reason why it holds.
Probably not a substantial claim. The paper’s conclusions may not depend on it. The paper may give no reason why it holds.
In the paper
“Steatosis may be purely microvesicular, which is primarily related to mitochondrial injury, mixed microvesicular and macrovesicular, or purely macrovesicular.100”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > Approach to liver biopsy interpretation
What the sources say
- Not checked yetcites [100] Rabinowich L Shibolet O. Drug induced steatohepatitis: an uncommon culprit of a common disease. Biomed Res Int. 2015; 2015: 168905. 26273591 PMC4529891
hedgedconditional- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: unclear — It is unclear whether the paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
None of the sources cited for this claim have been checked yet.
In the paper
“but retains risk factors of age, alcohol, and pregnancy that are of unclear value.”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > Limitations of causality assessment in DILI
plain- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: fails — The paper’s conclusions may not depend on it.
- Based: passes — The paper gives a reason why it holds.
Probably not a substantial claim. The paper’s conclusions may not depend on it.
The paper states this without a source or data behind it here, so there is nothing to check it against. The quote shows it is in the paper.
In the paper
“The RECAM removed several risk factors and has an expanded list of competing causes to exclude, and diagnostic testing is categorical and menu‐driven to reduce interobserver variability.”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > Models of causality assessment
plaindirect- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: unclear — It is unclear whether the paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
In the paper
“This approach has been shown to be as useful as the RUCAM, although expert opinion is rarely available in routine clinical practice.117”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > Models of causality assessment
What the sources say
- Not checked yetcites [117] Hayashi PH Barnhart HX Fontana RJ Chalasani N Davern TJ Talwalkar JA. Reliability of causality assessment for drug, herbal and dietary supplement hepatotoxicity in the drug‐induced liver injury network (DILIN). Liver Int. 2015; 35: 1623– 32. 24661785 PMC4305346
plain- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: unclear — It is unclear whether the paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
None of the sources cited for this claim have been checked yet.
In the paper
“Phospholipidosis is another form of DILI seen as hepatocytes with foamy granular cytoplasm. Similar to induction hepatocytes, phospholipidosis represents an adaptive response to cationic amphophilic drugs like amiodarone and antimalarial agents, via the inhibition of lysosome‐specific phospholipase A2.100,101”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > Approach to liver biopsy interpretation
What the sources say
- Not checked yetcites [100] Rabinowich L Shibolet O. Drug induced steatohepatitis: an uncommon culprit of a common disease. Biomed Res Int. 2015; 2015: 168905. 26273591 PMC4529891
- Not checked yetcites [101] Bessone F Dirchwolf M Rodil MA Razori MV Roma MG. Review article: drug‐induced liver injury in the context of nonalcoholic fatty liver disease—a physiopathological and clinical integrated view. Aliment Pharmacol Ther. 2018; 48: 892– 913. 30194708
plaindirect- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: unclear — It is unclear whether the paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
The paper states this without a source or data behind it here, so there is nothing to check it against. The quote shows it is in the paper.
In the paper
“but is not intended for use in patients with chronic liver disease.”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > Limitations of causality assessment in DILI
plain- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: fails — The paper’s conclusions may not depend on it.
- Based: passes — The paper gives a reason why it holds.
Probably not a substantial claim. The paper’s conclusions may not depend on it.
A conclusion the paper draws from its own results — it cites no other source for it, so there is none to check. The quote shows it is in the paper.
In the paper
“The presence of eosinophils and granulomas on a liver biopsy in a patient with suspected DILI is associated with a more favorable outcome, whereas those who have necrosis or fibrosis have poorer outcomes.”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > DILI severity and prognosis
plaincorrelational- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: unclear — It is unclear whether the paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
None of the sources cited for this claim have been checked yet.
In the paper
“Generic causality assessment models include the World Health Organization Collaborating Center for International Drug Monitoring system by the Uppsala Monitoring Center, which have not gained traction in DILI research or clinical practice because of their lack of liver specificity.114,115”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > Models of causality assessment
What the sources say
- Not checked yetcites [114] The use of the WHO–UMC system for standardised case causality assessment. 2021. [cited 2021 Sep 29]. Available from: http://www.who‐umc.org/graphics/4409.pdf
- Not checked yetcites [115] Naranjo CA Busto U Sellers EM Sandor P Ruiz I Roberts EA. A method for estimating the probability of adverse drug reactions. Clin Pharmacol Ther. 1981; 30: 239– 45. 7249508
plaindirect- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: unclear — It is unclear whether the paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
None of the sources cited for this claim have been checked yet.
In the paper
“Scores range from −5 to +17 points.”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > Models of causality assessment
What the sources say
- Not checked yetcites [111] Takikawa H Takamori Y Kumagi T Onji M Watanabe M Shibuya A. Assessment of 287 Japanese cases of drug induced liver injury by the diagnostic scale of the international consensus meeting. Hepatol Res. 2003; 27: 192– 5. 14585395
- Not checked yetcites [112] Hanatani T Sai K Tohkin M Segawa K Kimura M Hori K. A detection algorithm for drug‐induced liver injury in medical information databases using the Japanese diagnostic scale and its comparison with the Council for International Organizations of medical sciences/the Roussel Uclaf causality assessment method scale. Pharmacoepidemiol Drug Saf. 2014; 23: 984– 8. 24596340
plain- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: fails — The paper’s conclusions may not depend on it.
- Based: passes — The paper gives a reason why it holds.
Probably not a substantial claim. The paper’s conclusions may not depend on it.
The paper states this without a source or data behind it here, so there is nothing to check it against. The quote shows it is in the paper.
In the paper
“Currently there are three commonly used causality assessment methods”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > Limitations of causality assessment in DILI
plain- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: fails — The paper’s conclusions may not depend on it.
- Based: passes — The paper gives a reason why it holds.
Probably not a substantial claim. The paper’s conclusions may not depend on it.
The paper states this without a source or data behind it here, so there is nothing to check it against. The quote shows it is in the paper.
In the paper
“and each has its own strengths and limitations.”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > Limitations of causality assessment in DILI
plain- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: fails — The paper’s conclusions may not depend on it.
- Based: passes — The paper gives a reason why it holds.
Probably not a substantial claim. The paper’s conclusions may not depend on it.
None of the sources cited for this claim have been checked yet.
In the paper
“Unlike AIH, plasma cell infiltration is not predominant, and the inflammatory infiltrate consists mostly of T lymphocytes, with CD8+ cells being greater in number than CD4+ cells.”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > Approach to liver biopsy interpretation
What the sources say
- Not checked yetcites [95] Sawada K Hayashi H Nakajima S Hasebe T Fujiya M Okumura T. Non‐alcoholic fatty liver disease is a potential risk factor for liver injury caused by immune checkpoint inhibitor. J Gastroenterol Hepatol. 2020; 35: 1042– 8. 31752049
- Not checked yetcites [96] Zen Y Yeh MM. Checkpoint inhibitor‐induced liver injury: a novel form of liver disease emerging in the era of cancer immunotherapy. Semin Diagn Pathol. 2019; 36: 434– 440. 31358424
- Not checked yetcites [97] Zen Y Chen YY Jeng YM Tsai HW Yeh MM. Immune‐related adverse reactions in the hepatobiliary system: second‐generation check‐point inhibitors highlight diverse histological changes. Histopathology. 2020; 76: 470– 80. 31550390
plain- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: unclear — It is unclear whether the paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
In the paper
“In chronic cholestasis, the cholestasis persists and may have severe bile duct injury or progress to bile duct loss.88”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > Approach to liver biopsy interpretation
What the sources say
- Not checked yetcites [88] Kleiner DE Chalasani NP Lee WM Fontana RJ Bonkovsky HL Watkins PB. Hepatic histological findings in suspected drug‐induced liver injury: systematic evaluation and clinical associations. Hepatology. 2014; 59: 661– 70. 24037963 PMC3946736
hedgedconditional- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: unclear — It is unclear whether the paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
A conclusion the paper draws from its own results — it cites no other source for it, so there is none to check. The quote shows it is in the paper.
In the paper
“A broad spectrum of histological patterns has been reported in patients with DILI, and a given drug may be associated with more than a single histopathological signature.”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > DILI severity and prognosis
hedgedcorrelational- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: unclear — It is unclear whether the paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
In the paper
“Of note, microvesicular steatosis usually does not lead to increased echogenicity on ultrasound, nor does it manifest with hepatomegaly, and only liver biopsy can confirm its presence.101”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > Approach to liver biopsy interpretation
What the sources say
- Not checked yetcites [101] Bessone F Dirchwolf M Rodil MA Razori MV Roma MG. Review article: drug‐induced liver injury in the context of nonalcoholic fatty liver disease—a physiopathological and clinical integrated view. Aliment Pharmacol Ther. 2018; 48: 892– 913. 30194708
plain- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: unclear — It is unclear whether the paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
The paper states this without a source or data behind it here, so there is nothing to check it against. The quote shows it is in the paper.
In the paper
“Cholestatic DILI histology includes acute cholestasis, chronic cholestasis, and acute cholestatic hepatitis.”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > Approach to liver biopsy interpretation
plain- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: fails — The paper’s conclusions may not depend on it.
- Based: passes — The paper gives a reason why it holds.
Probably not a substantial claim. The paper’s conclusions may not depend on it.
The paper states this without a source or data behind it here, so there is nothing to check it against. The quote shows it is in the paper.
In the paper
“Marketed supplements comprise single‐ingredient products as well as mixtures of many different ingredients that may be both natural and synthetic.”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > HDS hepatotoxicity
plain- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: fails — The paper’s conclusions may not depend on it.
- Based: passes — The paper gives a reason why it holds.
Probably not a substantial claim. The paper’s conclusions may not depend on it. It may state two separate claims as one.
None of the sources cited for this claim have been checked yet.
In the paper
“which stratifies causality assessment by the R‐value”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > Limitations of causality assessment in DILI
What the sources say
- Not checked yetcites [108] Danan G Teschke R. RUCAM in drug and herb induced liver injury: the update. Int J Mol Sci. 2016; 27: 14– 30. PMC4730261 26712744
- Not checked yetcites [119] Teschke R Frenzel C Schulze J Eickhoff A. Herbal hepatotoxicity: challenges and pitfalls of causality assessment methods. World J Gastroenterol. 2013; 19: 2864– 82. 23704820 PMC3660812
plaindirect- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: fails — The paper’s conclusions may not depend on it.
- Based: passes — The paper gives a reason why it holds.
Probably not a substantial claim. The paper’s conclusions may not depend on it.
In the paper
“The degree of necrosis and presence of prominent ductular reaction are associated with poor outcome, whereas the presence of eosinophils and granulomas is associated with better outcome.104”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > DILI severity and prognosis
What the sources say
- Not checked yetcites [104] Kleiner DE. Liver histology in the diagnosis and prognosis of drug‐induced liver injury. Clin Liver Dis (Hoboken). 2014; 4: 12– 6. 30992912 PMC6448725
plaincorrelational- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: unclear — It is unclear whether the paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
A conclusion the paper draws from its own results — it cites no other source for it, so there is none to check. The quote shows it is in the paper.
In the paper
“Genetic polymorphisms in the HLA region and the conditions under which a product is consumed may influence the likelihood of an individual patient developing HDS hepatotoxicity.”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > HDS hepatotoxicity, susceptibility factors, and outcomes
hedgedconditional- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: unclear — It is unclear whether the paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
None of the sources cited for this claim have been checked yet.
In the paper
“In some instances, a short course of corticosteroids (i.e., 1–3 months) with rapid tapering may be of benefit in patients with autoimmune features on biopsy as well as for patients with DILI from ICIs and tyrosine kinase inhibitors (Table 9).153,154”
- Also stated in: § Medical management of idiosyncratic patients with DILI · hedged
“Corticosteroids given for 1–3 months may be of benefit in selected patients with idiosyncratic DILI, including those with severe hypersensitivity features, DRESS, and autoimmune features on liver biopsy.”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > Medical management of idiosyncratic patients with DILI
What the sources say
- Not checked yetcites [153] Hu PF Wang PQ Chen H Hu XF Xie QP Shi J. Beneficial effect of corticosteroids for patients with severe drug‐induced liver injury. J Dig Dis. 2016; 17: 618– 27. 27426618
- Not checked yetcites [154] Wree A Dechêne A Herzer K Hilgard P Syn WK Gerken G. Steroid and ursodesoxycholic acid combination therapy in severe drug‐induced liver injury. Digestion. 2011; 84: 54– 9. 21304237
hedgedconditional- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
- Also stated in: § Medical management of idiosyncratic patients with DILI · hedged
The paper states this without a source or data behind it here, so there is nothing to check it against. The quote shows it is in the paper.
In the paper
“An example is the inclusion of sildenafil in products marketed for sexual performance.”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > Special considerations in the diagnosis of HDS‐associated liver injury
plain- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: fails — The paper’s conclusions may not depend on it.
- Based: passes — The paper gives a reason why it holds.
Probably not a substantial claim. The paper’s conclusions may not depend on it.
The paper states this without a source or data behind it here, so there is nothing to check it against. The quote shows it is in the paper.
In the paper
“the composition of HDS may change over time as a result of varying growing conditions, leading to batch‐to‐batch variability.”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > Special considerations in the diagnosis of HDS‐associated liver injury
hedgedconditional- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: fails — The paper’s conclusions may not depend on it.
- Based: fails — The paper may give no reason why it holds.
Probably not a substantial claim. The paper’s conclusions may not depend on it. The paper may give no reason why it holds.
In the paper
“Recent data suggest that APAP hepatotoxicity may occur even when therapeutic doses are used, but particularly in association with these other cofactors.165”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > APAP hepatotoxicity
What the sources say
- Not checked yetcites [165] Louvet A Wandji LCN Lemaître E Khaldi M Lafforgue C Artru F. Acute liver injury with therapeutic doses of acetaminophen: a prospective study. Hepatology. 2021; 73: 1634– 6. 33306215
hedgedcorrelational- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: unclear — It is unclear whether the paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
The paper states this without a source or data behind it here, so there is nothing to check it against. The quote shows it is in the paper.
In the paper
“latency of exposure to a product before the onset of injury can be quite variable because of the accumulation of product within the body.”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > Special considerations in the diagnosis of HDS‐associated liver injury
plaindirect- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: fails — The paper’s conclusions may not depend on it.
- Based: fails — The paper may give no reason why it holds.
Probably not a substantial claim. The paper’s conclusions may not depend on it. The paper may give no reason why it holds.
The paper states this without a source or data behind it here, so there is nothing to check it against. The quote shows it is in the paper.
In the paper
“it is well known that supplements are vulnerable to intentional or inadvertent inclusion of ingredients.”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > Special considerations in the diagnosis of HDS‐associated liver injury
boosted- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: fails — The paper may give no reason why it holds.
Probably not a substantial claim. The paper may give no reason why it holds.
In the paper
“Ursodeoxycholic acid may improve symptoms of pruritus and hasten DILI recovery, but large, randomized controlled trials are needed to determine the optimal dose and duration.155”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > Medical management of idiosyncratic patients with DILI
What the sources say
- Not checked yetcites [155] Lang SM Ortmann J Rostig S Schiffl H. Ursodeoxycholic acid attenuates hepatotoxicity of multidrug treatment of mycobacterial infections: a prospective pilot study. Int J Mycobacterol. 2019; 8: 89– 92. 30860185
hedgedconditional- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
In the paper
“Another randomized trial of 102 patients with antitubercular DILI also demonstrated a shorter length of stay but no survival benefit with NAC.149”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > Medical management of idiosyncratic patients with DILI
What the sources say
- Not checked yetcites [149] Moosa MS Maartens G Gunter H Allie S Chughlay MF Setshedi M. A randomized controlled trial of intravenous N‐acetylcysteine in the management of anti‐tuberculosis drug‐induced liver injury. Clin Infect Dis. 2021; 73: e3377– 83. 32845997
boosteddirectn = 102- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: unclear — It is unclear whether the paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
In the paper
“More recently, detection of serum APAP‐protein adducts has been proposed as a more specific way to diagnose APAP hepatotoxicity particularly in patients presenting late or with an unintentional overdose, but this assay is not commercially available.166”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > APAP hepatotoxicity
What the sources say
- Not checked yetcites [166] James LP Letzig L Simpson PM Capparelli E Roberts DW Hinson JA. Pharmacokinetics of acetaminophen‐protein adducts in adults with acetaminophen overdose and acute liver failure. Drug Metab Dispos. 2009; 37: 1779– 84. 19439490 PMC2712440
plain- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: unclear — It is unclear whether the paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
In the paper
“Most adults and children with idiosyncratic DILI present with a drug latency of 2–24 weeks, although some drugs have an ultrashort (< 7 days) latency.30”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > Natural history and management of idiosyncratic DILI
What the sources say
- Not checked yetcites [30] Chalasani N Bonkovsky HL Fontana RJ Lee W Stolz A Talwalkar J. Features and outcomes of 899 patients with drug‐induced liver injury: the DILIN prospective study. Gastroenterology. 2015; 148: 1340– 52.e7. 25754159 PMC4446235
plain- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: unclear — It is unclear whether the paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
In the paper
“when the veracity of a report is verified, regulatory actions can be taken against the manufacturer”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > Epidemiology of HDS use and liver injury
What the sources say
- Not checked yetcites [128] MedWatch: the FDA safety information and adverse event reporting program. US Food and Drug Administration. [cited 2021 Sep 19]. Available from: https://www.fda.gov/safety/medwatch‐fda‐safety‐information‐and‐adverse‐event‐reporting‐program
plaindirect- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: fails — The paper’s conclusions may not depend on it.
- Based: passes — The paper gives a reason why it holds.
Probably not a substantial claim. The paper’s conclusions may not depend on it.
In the paper
“in the European Union, the allowance of a product on the market requires a demonstrated history of safe use, along with periodic chemical verification of the labeled ingredients.”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > Epidemiology of HDS use and liver injury
What the sources say
- Not checked yetcites [127] Food supplements. European Commission website. 2021. [cited 2021 Sep 19]. Available from: https://ec.europa.eu/food/safety/labelling‐and‐nutrition/food‐supplements_en
plain- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: fails — The paper’s conclusions may not depend on it.
- Based: passes — The paper gives a reason why it holds.
Probably not a substantial claim. The paper’s conclusions may not depend on it. It may state two separate claims as one.
In the paper
“The reason for this widespread toxicity is that, unlike drugs associated with idiosyncrasy, APAP is a dose‐related hepatotoxin, with all mammalian species susceptible to liver injury in doses only 2 to 3 times therapeutic dosing.161”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > APAP hepatotoxicity
What the sources say
- Not checked yetcites [161] Rumack BH. Acetaminophen hepatotoxicity: the first 35 years. J Toxicol Clin Toxicol. 2002; 40: 3– 20. 11990202
plaindirect- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
The paper states this without a source or data behind it here, so there is nothing to check it against. The quote shows it is in the paper.
In the paper
“Botanical ingredients include plant parts and other herbs that are not listed on the product label.”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > Special considerations in the diagnosis of HDS‐associated liver injury
plain- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: fails — The paper’s conclusions may not depend on it.
- Based: fails — The paper may give no reason why it holds.
Probably not a substantial claim. The paper’s conclusions may not depend on it. The paper may give no reason why it holds.
In the paper
“American consumers spent more than $9.6 billion on herbal products in 2019.125”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > Epidemiology of HDS use and liver injury
What the sources say
- Not checked yetcites [125] US herbal supplement sales increase by 8.6% in 2019, record‐breaking sales predicted for 2020. 2020. [cited 2021 Sep 19]. Available from: http://herbalgram.org/news/press‐releases/2020/us‐herbal‐supplement‐sales‐2019/
plain- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: fails — The paper’s conclusions may not depend on it.
- Based: passes — The paper gives a reason why it holds.
Probably not a substantial claim. The paper’s conclusions may not depend on it.
The paper states this without a source or data behind it here, so there is nothing to check it against. The quote shows it is in the paper.
In the paper
“Nonbotanical ingredients include chemicals, pesticides, and heavy metals.”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > Special considerations in the diagnosis of HDS‐associated liver injury
plain- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: fails — The paper’s conclusions may not depend on it.
- Based: passes — The paper gives a reason why it holds.
Probably not a substantial claim. The paper’s conclusions may not depend on it.
A conclusion the paper draws from its own results — it cites no other source for it, so there is none to check. The quote shows it is in the paper.
In the paper
“This may be due to delayed recognition of the product as the cause of liver injury or reluctance of HDS consumers to seek medical care.”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > HDS hepatotoxicity, susceptibility factors, and outcomes
hedgedconditional- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: fails — The paper’s conclusions may not depend on it.
- Based: passes — The paper gives a reason why it holds.
Probably not a substantial claim. The paper’s conclusions may not depend on it.
In the paper
“The regulatory environment in non‐US markets varies, as summarized in a recent review.127”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > Epidemiology of HDS use and liver injury
What the sources say
- Not checked yetcites [127] Food supplements. European Commission website. 2021. [cited 2021 Sep 19]. Available from: https://ec.europa.eu/food/safety/labelling‐and‐nutrition/food‐supplements_en
plain- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: fails — The paper’s conclusions may not depend on it.
- Based: passes — The paper gives a reason why it holds.
Probably not a substantial claim. The paper’s conclusions may not depend on it.
None of the sources cited for this claim have been checked yet.
In the paper
“A diagnosis of APAP hepatotoxicity relies on a history of excessive APAP ingestion, detection of an elevated serum APAP level following single‐time‐point ingestion, and exclusion of competing causes of acute hepatocellular liver injury.”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > Prognosis
plain- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: unclear — It is unclear whether the paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
The paper states this without a source or data behind it here, so there is nothing to check it against. The quote shows it is in the paper.
In the paper
“HDS are commonly used worldwide”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > HDS hepatotoxicity, susceptibility factors, and outcomes
plain- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: fails — The paper’s conclusions may not depend on it.
- Based: passes — The paper gives a reason why it holds.
Probably not a substantial claim. The paper’s conclusions may not depend on it.
In the paper
“including withdrawal of a product from the market in the most extreme circumstance.”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > Epidemiology of HDS use and liver injury
What the sources say
- Not checked yetcites [128] MedWatch: the FDA safety information and adverse event reporting program. US Food and Drug Administration. [cited 2021 Sep 19]. Available from: https://www.fda.gov/safety/medwatch‐fda‐safety‐information‐and‐adverse‐event‐reporting‐program
plain- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: fails — The paper’s conclusions may not depend on it.
- Based: passes — The paper gives a reason why it holds.
Probably not a substantial claim. The paper’s conclusions may not depend on it.
The paper states this without a source or data behind it here, so there is nothing to check it against. The quote shows it is in the paper.
In the paper
“the lack of knowledge and awareness of potential liver injury from these widely used, over‐the‐counter supplements may cause the injury to go unrecognized by patients and providers.”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > Special considerations in the diagnosis of HDS‐associated liver injury
hedgedconditional- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: fails — The paper’s conclusions may not depend on it.
- Based: fails — The paper may give no reason why it holds.
Probably not a substantial claim. The paper’s conclusions may not depend on it. The paper may give no reason why it holds.
In the paper
“The incidence of chronic DILI in 598 subjects enrolled into the DILIN was 21% at 6 months, with African Americans and patients with a cholestatic liver injury at presentation being at increased risk.147”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > Natural history and management of idiosyncratic DILI
What the sources say
- Not checked yetcites [147] Fontana RJ Hayashi PH Barnhart H Kleiner DE Reddy KR Chalasani N. Persistent liver biochemistry abnormalities are more common in older patients and those with cholestatic drug‐induced liver injury. Am J Gastroenterol. 2015; 110: 1450– 9. 26346867 PMC4784423
plaincorrelationaln = 598- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: unclear — It is unclear whether the paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
None of the sources cited for this claim have been checked yet.
In the paper
“Supplements can cause severe hepatotoxicity that can have variable clinical, laboratory, and histological phenotypes.”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > HDS hepatotoxicity, susceptibility factors, and outcomes
plaindirect- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
The paper states this without a source or data behind it here, so there is nothing to check it against. The quote shows it is in the paper.
In the paper
“Intentional adulteration usually results from the inclusion of substances, usually pharmaceuticals, to achieve some pharmacodynamic effect in keeping with the supplement's marketed purpose for use.”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > Special considerations in the diagnosis of HDS‐associated liver injury
plaindirect- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: fails — The paper’s conclusions may not depend on it.
- Based: fails — The paper may give no reason why it holds.
Probably not a substantial claim. The paper’s conclusions may not depend on it. The paper may give no reason why it holds.
A conclusion the paper draws from its own results — it cites no other source for it, so there is none to check. The quote shows it is in the paper.
In the paper
“The polyphenolic backbone of the catechins is exploited for its antioxidant potential but is likely also responsible for liver injury.”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > HDS hepatotoxicity, susceptibility factors, and outcomes
hedgedconditional- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: unclear — It is unclear whether the paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
None of the sources cited for this claim have been checked yet.
In the paper
“Several cases of liver injury due to GTE have been published, with the most convincing cases being those in which injury recurred following rechallenge.131,132”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > HDS hepatotoxicity, susceptibility factors, and outcomes
What the sources say
- Not checked yetcites [131] Bonkovsky HL. Hepatotoxicity associated with supplements containing Chinese green tea (Camellia sinensis). Ann Intern Med. 2006; 144: 68– 71. 16389263
- Not checked yetcites [132] Oketch‐Rabah HA Roe AL Rider CV Bonkovsky HL Giancaspro GI Navarro V. United States Pharmacopeia (USP) comprehensive review of the hepatotoxicity of green tea extracts. Toxicol Rep. 2020; 7: 386– 402. 32140423 PMC7044683
plaindirect- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: unclear — It is unclear whether the paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
In the paper
“Allegations of injury attributable to a dietary supplement can be reported by consumers and providers to the US Food and Drug Administration (FDA), through the MedWatch passive reporting system.128”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > Epidemiology of HDS use and liver injury
What the sources say
- Not checked yetcites [128] MedWatch: the FDA safety information and adverse event reporting program. US Food and Drug Administration. [cited 2021 Sep 19]. Available from: https://www.fda.gov/safety/medwatch‐fda‐safety‐information‐and‐adverse‐event‐reporting‐program
plain- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: fails — The paper’s conclusions may not depend on it.
- Based: passes — The paper gives a reason why it holds.
Probably not a substantial claim. The paper’s conclusions may not depend on it.
The paper states this without a source or data behind it here, so there is nothing to check it against. The quote shows it is in the paper.
In the paper
“The DILIN's current efforts are being directed to understand the toxicity that may result from specific ingredients that are sold individually or as ingredients in product mixtures (Table 7).”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > HDS hepatotoxicity, susceptibility factors, and outcomes
hedgedconditional- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: fails — The paper’s conclusions may not depend on it.
- Based: passes — The paper gives a reason why it holds.
Probably not a substantial claim. The paper’s conclusions may not depend on it.
In the paper
“These reports are investigated by the FDA's Center for Food Safety and Applied Nutrition”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > Epidemiology of HDS use and liver injury
What the sources say
- Not checked yetcites [128] MedWatch: the FDA safety information and adverse event reporting program. US Food and Drug Administration. [cited 2021 Sep 19]. Available from: https://www.fda.gov/safety/medwatch‐fda‐safety‐information‐and‐adverse‐event‐reporting‐program
plaindirect- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: fails — The paper’s conclusions may not depend on it.
- Based: passes — The paper gives a reason why it holds.
Probably not a substantial claim. The paper’s conclusions may not depend on it.
In the paper
“Other risk factors for APAP toxicity include fasting and malnutrition, which can lead to depletion of intrahepatic glutathione stores, as well as use of alcohol and other medications that can induce the cytochrome P‐450 system and lead to enhanced production of the toxic metabolite, N‐acetyl‐p‐benzoquinone imine.164”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > APAP hepatotoxicity
What the sources say
- Not checked yetcites [164] Whitcomb DC Block GD. Association of acetaminophen hepatotoxicity with fasting and ethanol use. JAMA. 1994; 272: 1845– 50. 7990219
plaindirect- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: unclear — It is unclear whether the paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
The paper states this without a source or data behind it here, so there is nothing to check it against. The quote shows it is in the paper.
In the paper
“HLA‐B 35:01 has been associated with hepatotoxicity attributed to GTE in White populations and P. multiflorum hepatotoxicity in Asian populations.”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > HDS hepatotoxicity, susceptibility factors, and outcomes
plaincorrelational- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: unclear — It is unclear whether the paper’s conclusions depend on it.
- Based: unclear — It is unclear why the paper says it holds.
It may state two separate claims as one.
In the paper
“The 1994 Dietary Supplement Health and Education Act provides the current regulatory framework for supplement manufacturing and distribution in the United States.126”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > Epidemiology of HDS use and liver injury
What the sources say
- Not checked yetcites [126] Roytman MM Poerzgen P Navarro V. Botanicals and hepatotoxicity. Clin Pharm Ther. 2018; 104: 458– 69. 29920648
plain- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: fails — The paper’s conclusions may not depend on it.
- Based: passes — The paper gives a reason why it holds.
Probably not a substantial claim. The paper’s conclusions may not depend on it.
A conclusion the paper draws from its own results — it cites no other source for it, so there is none to check. The quote shows it is in the paper.
In the paper
“The key to preventing clinically significant liver injury from DILI is early detection of the signal event before it becomes symptomatic or severe.”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > Early detection of DILI in clinical practice
plaindirect- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: fails — The paper may give no reason why it holds.
Probably not a substantial claim. The paper may give no reason why it holds.
The paper states this without a source or data behind it here, so there is nothing to check it against. The quote shows it is in the paper.
In the paper
“DILI biomarkers in development broadly fall into four categories: (A) dynamic liver injury markers that quantify the extent or severity of hepatocyte damage; (B) mechanistic biomarkers that aim to elucidate the intracellular pathways of liver injury; (C) prognostic biomarkers; and (D) diagnostic biomarkers including single‐nucleotide polymorphisms.”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > SUMMARY/FUTURE DIRECTIONS > DILI biomarkers
plain- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: fails — The paper’s conclusions may not depend on it.
- Based: passes — The paper gives a reason why it holds.
Probably not a substantial claim. The paper’s conclusions may not depend on it.
None of the sources cited for this claim have been checked yet.
In the paper
“International Classification of Diseases, Tenth Revision codes and natural language processing algorithms may help identify DILI cases from administrative databases, but further refinement is needed.208,209”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > SUMMARY/FUTURE DIRECTIONS
What the sources say
- Not checked yetcites [208] Yeboah‐Korang A Louissant J Tsung I Prabhu S Fontana RJ. Utility of computerized ICD‐10 algorithm to identify idiosyncratic drug‐induced liver injury cases in the electronic medical record. Drug Saf. 2020; 43: 371– 7. 31916081 PMC8487619
- Not checked yetcites [209] Heidemann L Law J Fontana RJ. A text searching tool to identify patients with idiosyncratic drug‐induced liver injury. Dig Dis Sci. 2017; 62: 615– 25. 26597192 PMC4877288
hedgedconditional- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: unclear — It is unclear whether the paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
In the paper
“In the United States, an estimated 13 million individuals have latent TB, but > 10,000 individuals are treated for active TB each year.179”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > Monitoring strategies for four commonly used medications
What the sources say
- Not checked yetcites [179] Talwar A Tsang CA Price SF Pratt RH Walker WL Schmit KM. Tuberculosis– United States 2018. MMWR Morb Mortal Wkly Rep. 2019; 68: 257– 62.30897076
hedged- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: fails — The paper’s conclusions may not depend on it.
- Based: passes — The paper gives a reason why it holds.
Probably not a substantial claim. The paper’s conclusions may not depend on it. It may state two separate claims as one.
In the paper
“Whereas the treatment for active TB still consists of isoniazid, rifamycin, pyrazinamide, and ethambutol, alternative strategies are now available that depend on various individual patient characteristics.186”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > Monitoring strategies for four commonly used medications
What the sources say
- Not checked yetcites [186] Nahid P Dorman SE Alipanah N Barry PM Brozek JL Cattamanchi A. Official American Thoracic Society/Centers for Disease Control and Prevention/Infectious Diseases Society of America clinical practice guidelines: treatment of drug‐susceptible tuberculosis. Clin Infect Dis. 2016; 63: e147– 95. 27516382 PMC6590850
plain- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: fails — The paper’s conclusions may not depend on it.
- Based: passes — The paper gives a reason why it holds.
Probably not a substantial claim. The paper’s conclusions may not depend on it. It may state two separate claims as one.
The paper states this without a source or data behind it here, so there is nothing to check it against. The quote shows it is in the paper.
In the paper
“Over the past 40 years, various recommendations for laboratory monitoring while receiving isoniazid have been proposed that begin with baseline liver assessments for all patients.”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > Monitoring strategies for four commonly used medications
plain- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: fails — The paper’s conclusions may not depend on it.
- Based: passes — The paper gives a reason why it holds.
Probably not a substantial claim. The paper’s conclusions may not depend on it.
In the paper
“In contrast, the 2020 Academy of Dermatology guidelines for managing psoriasis recommends fibrosis‐4 serologic testing and transient elastography at baseline and annually while on methotrexate therapy in patients with risk factors for hepatotoxicity.196”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > Monitoring strategies for four commonly used medications
What the sources say
- Not checked yetcites [196] Menter A Gelfand JM Connor C Armstrong AW Cordoro KM Davis DMR. Joint American Academy of Dermatology–National Psoriasis Foundation guidelines of care for the management of psoriasis with systemic nonbiologic therapies. J Am Acad Dermatol. 2020; 82: 1445– 86. 32119894
plain- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: fails — The paper’s conclusions may not depend on it.
- Based: passes — The paper gives a reason why it holds.
Probably not a substantial claim. The paper’s conclusions may not depend on it.
In the paper
“The 2008 American College of Rheumatology guidelines for the treatment of rheumatoid arthritis advises laboratory monitoring at baseline and then every 2–4 weeks with the first 3 months, every 8–12 weeks for 3–6 months, and then every 12 weeks beyond 6 months of treatment.194”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > Monitoring strategies for four commonly used medications
What the sources say
- Not checked yetcites [194] Saag KG Teng GG Patkar NM Anuntiyo J Finney C Curtis JR. American College of Rheumatology 2008 recommendations for the use of nonbiologic and biologic disease‐modifying antirheumatic drugs in rheumatoid arthritis. Arthritis Rheum. 2008; 59: 762– 84. 18512708
plain- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: fails — The paper’s conclusions may not depend on it.
- Based: passes — The paper gives a reason why it holds.
Probably not a substantial claim. The paper’s conclusions may not depend on it.
A conclusion the paper draws from its own results — it cites no other source for it, so there is none to check. The quote shows it is in the paper.
In the paper
“Areas of unmet need in DILI clinical care include the need for improved diagnostic and prognostic biomarkers, accurate and reliable causality assessment instruments, and studies of the epidemiology of DILI.”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > SUMMARY/FUTURE DIRECTIONS
plain- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
Probably not a substantial claim. It may state two separate claims as one.
A conclusion the paper draws from its own results — it cites no other source for it, so there is none to check. The quote shows it is in the paper.
In the paper
“In addition, improved understanding of the molecular pathogenesis of DILI is needed to minimize future morbidity and mortality and identify therapeutic targets for intervention.”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > SUMMARY/FUTURE DIRECTIONS
plaindirect- Asserted: passes — The authors put it forward as true.
- Checkable: fails — It may be too vague to check against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: fails — The paper may give no reason why it holds.
Probably not a substantial claim. It may be too vague to check against evidence. The paper may give no reason why it holds.
The paper relies on this without support.
The available observational and epidemiological data from case series and DILI registries are adequate to support recommendations on the clinical, laboratory, and histological features of DILI.
“The aim of this practice guidance is to provide recommendations regarding the common clinical, laboratory, and histological features seen in patients with DILI based on observational and epidemiological data reported in case series or DILI registries.”
The paper relies on this without support.
Expert opinion is an adequate basis for patient management recommendations when randomized controlled trials are lacking.
“In addition, expert opinion–based recommendations for patient management, including risk stratification, are provided to assist patients and practitioners.”
“This guidance was developed with the support and oversight of the American Association for the Study of Liver Diseases Practice Guidelines Committee, who chose to commission a guidance, rather than a guideline, because of the paucity of randomized controlled trials on this topic.”
The paper relies on this without support.
Up to 10% of patients with severe hepatocellular DILI with jaundice may be at risk of death because of their liver condition or underlying medical comorbidities.
“However, up to 10% of patients with severe hepatocellular DILI with jaundice may be at risk of death because of their liver condition or underlying medical comorbidities.”
The paper relies on this without support.
In registry studies, 10% of patients with idiosyncratic DILI are at risk for adverse hepatic outcomes including ALF, liver transplantation, and death within 6 months of onset.
“In registry studies, 10% of patients with idiosyncratic DILI are at risk for adverse hepatic outcomes including ALF, liver transplantation, and death within 6 months of onset.”
The paper relies on this without support.
Spontaneous survival in idiosyncratic DILI-related ALF is only 25%.
“Because of the low likelihood of spontaneous survival in idiosyncratic DILI-related ALF of only 25%, early transfer of these individuals to a liver transplant center is recommended.”
The paper relies on this without support.
Chronic liver injury that persists beyond 6–12 months is observed in 10%–20% of patients with DILI and may be more commonly encountered in those with cholestatic DILI.
“Chronic liver injury that persists beyond 6–12 months is observed in 10%–20% of patients with DILI and may be more commonly encountered in those with cholestatic DILI.”
The paper relies on this without support.
Individuals at increased risk for adverse outcomes include patients with DILI with severe necrosis and fibrosis on liver biopsy.
“Individuals at increased risk for adverse outcomes include patients with DILI with higher bilirubin and INR values and lower serum albumin at presentation as well as those with severe necrosis and fibrosis on liver biopsy and those with medical comorbidities and pre-existing liver disease.”
The paper relies on this without support.
Defibrotide is approved for use in adults and children undergoing hematopoietic cell transplantation with moderate to severe SOS.
“Defibrotide is a profibrolytic that is approved for use in adults and children undergoing hematopoietic cell transplantation with moderate to severe SOS.”
The paper relies on this without support.
Ursodeoxycholic acid is not an established therapy for patients with DILI but is presumably safe to administer.
“Ursodeoxycholic acid is not an established therapy for patients with DILI but is presumably safe to administer.”
The paper relies on this without support.
A diagnosis of APAP overdose is based on a history of ingestion of excessive doses (usually > 4 g as a single time point) that can lead to variable severity of acute hepatocellular liver injury with towering transaminase levels (often > 1000 U/L) within the first 24 h of observation.
“A diagnosis of APAP overdose is based on a history of ingestion of excessive doses (usually > 4 g as a single time point) that can then lead to variable severity of acute hepatocellular liver injury with towering transaminase levels (often > 1000 U/L) within the first 24 h of observation (Table 10).”
The paper relies on this without support.
Histologically, APAP toxicity is characterized by a variable degree of pericentral necrosis.
“Histologically, APAP toxicity is characterized by a variable degree of pericentral necrosis.”
Claims other papers make about this one
Each is checked against this paper’s own text: does it say what the citing paper says it does?
The source backs part of the claim, not all of it — or backs it for a different population, condition or comparison.
In the citing paper
“While this test has shown promise as a confirmatory assay in several studies, further refinement of the methodology and validation is required for its implementation in clinical practice.”
From Methods for causality assessment of idiosyncratic drug‐induced liver injury (2025) · cites this paper as [59]
Experimental — accuracy not yet measuredThe source backs part of the claim, not all of it — or backs it for a different population, condition or comparison.
In the citing paper
“Most DILIs are idiosyncratic.”
From Drug-induced liver injury. Part I: Classification, diagnosis and treatment (2025) · cites this paper as [8]
Experimental — accuracy not yet measuredThe source backs part of the claim, not all of it — or backs it for a different population, condition or comparison.
In the citing paper
“The lack of reliable diagnostic biomarkers and an evidence-based treatment paradigm has resulted in limited guidance on how to manage this aspect of DILI.2,25–27”
From Nomenclature, diagnosis and management of drug-induced autoimmune-like hepatitis (DI-ALH): An expert opinion meeting report (2023) · cites this paper as [27]
Experimental — accuracy not yet measuredThe source backs part of the claim, not all of it — or backs it for a different population, condition or comparison.
In the citing paper
“HDS constitute the majority of the idiosyncratic DILI in many Asian countries including China and Korea, while they are responsible for the minority of DILI cases in the United States (US).[2,10,14]”
From Drug-induced liver injury: Diagnosis, management and the role of liver transplantation (2025) · cites this paper as [2]
Experimental — accuracy not yet measuredThe source backs part of the claim, not all of it — or backs it for a different population, condition or comparison.
In the citing paper
“Most commonly implicated medications for idiosyncratic DILI are antimicrobials, immunomodulatory agents, and central nervous system agents.[2,10,12,13]”
From Drug-induced liver injury: Diagnosis, management and the role of liver transplantation (2025) · cites this paper as [2]
Experimental — accuracy not yet measured
The cited source says what the claim attributes to it.
In the citing paper
“They are unpredictable, largely dose-independent, and symptoms may appear after a long latency period [7, 8].”
From Drug-induced liver injury. Part I: Classification, diagnosis and treatment (2025) · cites this paper as [8]
The cited source says what the claim attributes to it.
In the citing paper
“N-acetylcysteine (NAC) is the most commonly used antidote in patients with acute paracetamol poisoning.”
From Drug-induced liver injury. Part I: Classification, diagnosis and treatment (2025) · cites this paper as [8]
The cited source says what the claim attributes to it.
In the citing paper
“Idiosyncratic hepatotoxicity is rare, largely dose-independent, unpredictable, and has variable latency.[2]”
From Drug-induced liver injury: Diagnosis, management and the role of liver transplantation (2025) · cites this paper as [2]
The cited source says what the claim attributes to it.
In the citing paper
“Direct hepatotoxicity is common, largely dose-dependent, predictable, and rapid in latency.”
From Drug-induced liver injury: Diagnosis, management and the role of liver transplantation (2025) · cites this paper as [2]
The cited source says what the claim attributes to it.
In the citing paper
“Serum APAP level after a single-time-point acute ingestion can aid in identifying patients with the highest risk of developing liver injury, and the use of the modified Rumack-Matthew nomogram is recommended in patients with single-point APAP ingestion to guide N-acetylcysteine (NAC) therapy.[2]”
From Drug-induced liver injury: Diagnosis, management and the role of liver transplantation (2025) · cites this paper as [2]
In the citing paper
“Research into DILI continues to be hampered by the lack of an objective, reliable laboratory tests that can reliably identify a specific drug or HDS as the cause of liver injury.”
From Methods for causality assessment of idiosyncratic drug‐induced liver injury (2025) · cites this paper as [59]
In the citing paper
“They occur in only a small number of exposed individuals (1 in 1000 to 1 in a million), so detection during a clinical trial is extremely difficult, and it usually occurs after the drug is marketed.”
From Drug-induced liver injury. Part I: Classification, diagnosis and treatment (2025) · cites this paper as [8]
In the citing paper
“Proper dose selection can prevent their development [7, 8].”
From Drug-induced liver injury. Part I: Classification, diagnosis and treatment (2025) · cites this paper as [8]
In the citing paper
“Symptoms appear quickly, within hours or days after exposure, and their severity depends on the drug dose taken.”
From Drug-induced liver injury. Part I: Classification, diagnosis and treatment (2025) · cites this paper as [8]
In the citing paper
“Like idiosyncratic DILI, indirect reactions are generally independent of the dose of drug administered and have a latency of weeks to months with varying clinical manifestations [7-9].”
From Drug-induced liver injury. Part I: Classification, diagnosis and treatment (2025) · cites this paper as [8]
In the citing paper
“The third, recently described, mechanism of DILI has been defined as indirect. It arises when the biological action of a drug affects the host immune system, leading to a secondary form of liver injury.”
From Drug-induced liver injury. Part I: Classification, diagnosis and treatment (2025) · cites this paper as [8]
In the citing paper
“Some cases of DILI are due to direct reaction, which is predictable, dose-dependent and occurs in nearly all exposed individuals if a threshold dose or duration is exceeded.”
From Drug-induced liver injury. Part I: Classification, diagnosis and treatment (2025) · cites this paper as [8]
In the citing paper
“The total dose of NAC is 300 mg/kg over 24 hours.”
From Drug-induced liver injury. Part I: Classification, diagnosis and treatment (2025) · cites this paper as [8]
In the citing paper
“Ursodeoxycholic acid (UDCA) may improve symptoms of pruritus and hasten DILI recovery, but large, randomized controlled trials are needed to determine the optimal dose and duration.”
From Drug-induced liver injury. Part I: Classification, diagnosis and treatment (2025) · cites this paper as [8]
In the citing paper
“those with ALF (coagulopathy and encephalopathy) should be urgently referred to a liver transplant center because of their low likelihood (~25% chance) of spontaneous recovery [8].”
From Drug-induced liver injury. Part I: Classification, diagnosis and treatment (2025) · cites this paper as [8]
In the citing paper
“The lack of a reliable diagnostic biomarker and evidence-based treatment paradigm has resulted in limited guidance on how to manage this aspect of DILI.”
From Nomenclature, diagnosis and management of drug-induced autoimmune-like hepatitis (DI-ALH): An expert opinion meeting report (2023) · cites this paper as [27]
In the citing paper
“Direct hepatotoxins such as acetaminophen (APAP) can lead to liver injury after a certain threshold dose in nearly all individuals.[2]”
From Drug-induced liver injury: Diagnosis, management and the role of liver transplantation (2025) · cites this paper as [2]
In the citing paper
“APAP causes liver injury predictably and in a dose-related manner, typically with doses exceeding 4 g/day at a single time point or with excessive doses over several days/weeks.”
From Drug-induced liver injury: Diagnosis, management and the role of liver transplantation (2025) · cites this paper as [2]
In the citing paper
“However, if patients progress to ALF, approximately one-third of the patients require LT or die.[2]”
From Drug-induced liver injury: Diagnosis, management and the role of liver transplantation (2025) · cites this paper as [2]
In the citing paper
“Approximately 80% of patients with idiosyncratic DILI have resolution without long-term sequelae, and 10% of patients with idiosyncratic DILI are at risk of severe adverse hepatic outcomes including ALF and need for LT.[2]”
From Drug-induced liver injury: Diagnosis, management and the role of liver transplantation (2025) · cites this paper as [2]
In the citing paper
“Approximately 80% of patients with idiosyncratic DILI have resolution without long-term sequelae, and 10% of patients with idiosyncratic DILI are at risk of severe adverse hepatic outcomes including ALF and need for LT.[2]”
From Drug-induced liver injury: Diagnosis, management and the role of liver transplantation (2025) · cites this paper as [2]
In the citing paper
“Idiosyncratic DILI is rare and reported to occur in 1 to 1,000–1,000,000 people.[2]”
From Drug-induced liver injury: Diagnosis, management and the role of liver transplantation (2025) · cites this paper as [2]
In the citing paper
“It is characterized by variable drug latency, clinical presentation, and liver histopathology findings, and is thought to be due to an aberrant host immune response to the drugs.[2]”
From Drug-induced liver injury: Diagnosis, management and the role of liver transplantation (2025) · cites this paper as [2]
In the citing paper
“while 40-60 mg/d prednisone taper over 1-3 months may improve normalization of liver enzyme for iDILI [82,191].”
From Chinese guideline for the diagnosis and treatment of drug-induced liver injury: an update (2024) · cites this paper as [82]
Self-check
Percentages, sums and reported differences re-computed from the paper’s own numbers.
Each contradiction between two passages listed here was confirmed by an independent check.
Rated major: it would touch a result — a value a result rests on, reported and recomputed p-values on opposite sides of the significance level, two passages that conflict with no sign which is right, or a cited work retracted before this paper was published.
In the paper
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > Models of causality assessment
“| Range of scores | −9 to +14 | −6 to 17 | −6 to +20 |”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > Models of causality assessment
“| Definite | ≥ 9 | > 17 | Highly likely/high probable ≥ 8 |”
Rated minor: it would not touch a result — a value no result rests on, a p-value that stays on the same side of the significance level, or a conflict that is clerical, resolved elsewhere in the paper, or outside its own findings.
In the paper
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > APAP hepatotoxicity
“150 mg/kg load over 15–60 min, followed by 50 mg/kg (12.5 mg/kg/h) over the next 4 h then 100 mg/kg (6.25 mg/kg/h) over 16 h thereafter”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > APAP hepatotoxicity
“(total 300 mg/kg over 24 h)”
Rated minor: it would not touch a result — a value no result rests on, a p-value that stays on the same side of the significance level, or a conflict that is clerical, resolved elsewhere in the paper, or outside its own findings.
In the paper
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > Models of causality assessment
“| Unlikely | 1–2 | 6–9 | Unlikely/excluded, < −4 |”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > Models of causality assessment
“| Excluded | ≤ 0 | ≤ 6 | Unlikely/excluded, < −4 |”
Rated minor: it would not touch a result — a value no result rests on, a p-value that stays on the same side of the significance level, or a conflict that is clerical, resolved elsewhere in the paper, or outside its own findings.
In the paper
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > Initial laboratory assessment
“An R value > 5 identifies cases of hepatocellular liver injury, whereas an R value < 2 categorizes cases of cholestatic liver injury, and an R value between 2 and 5 reflects a mixed liver injury pattern.”
§ AASLD practice guidance on drug, herbal, and dietary supplement–induced liver injury > INTRODUCTION > Competing causes of liver injury
“15Idiosyncratic DILI cases should be categorized by the R value at presentation (R = (ALT/ULN)/(ALP/ULN)) into hepatocellular (R ≥ 5), mixed (2 < R < 5), and cholestatic (R ≤ 2) profiles”
Citations
Cites
A method for estimating the probability of adverse drug reactions
Naranjo, C. A., Busto, U., Sellers, E. M., Sandor, P., Ruiz, I., Roberts, E. A., Janecek, E., Domecq, C., & Greenblatt, D. J. (1981) · Clinical Pharmacology and Therapeutics · doi:10.1038/clpt.1981.154 · Cited by 11,914 · cited 1×
“Generic causality assessment models include the World Health Organization Collaborating Center for International Drug Monitoring system by the Uppsala Monitoring Center, which have not gained traction in DILI research or clinical practice because of their lack of liver specificity.[114,115]”
MethodSchneider, B. J., Naidoo, J., Santomasso, B., Lacchetti, C., Adkins, S., Anadkat, M. J., Atkins, M. B., Brassil, K. J., Caterino, J. M., Chau, I., et al. (2021) · Journal of Clinical Oncology · doi:10.1200/jco.21.01440 · Cited by 2,536
Acetaminophen‐induced acute liver failure
Larson, A. M., Polson, J., Fontana, R. J., Davern, T. J., Lalani, E., Hynan, L. S., REISCH, J. S., Schiødt, F. V., Ostapowicz, G., Shakil, A. O., et al. (2005) · Hepatology · doi:10.1002/hep.20948 · Cited by 1,934
Self-citationNahid, P., Dorman, S. E., Alipanah, N., Barry, P. M., Brożek, J., Cattamanchi, A., Chaisson, L. H., Chaisson, R. E., Daley, C. L., Grzemska, M., et al. (2016) · Clinical Infectious Diseases · doi:10.1093/cid/ciw376 · Cited by 1,542
Danan, G., & Benichou, C. (1993) · Journal of Clinical Epidemiology · doi:10.1016/0895-4356(93)90101-6 · Cited by 1,481
Saag, K. G., Teng, G. G., Patkar, N. M., Anuntiyo, J., Finney, C., Curtis, J. R., Paulus, H. E., Mudano, A. S., Pisu, M., Melton, M. E., et al. (2008) · Arthritis Care & Research · doi:10.1002/art.23721 · Cited by 1,465
2021 American College of Rheumatology Guideline for the Treatment of Rheumatoid Arthritis
Fraenkel, L., Bathon, J. M., England, B. R., Clair, E. W. S., Arayssi, T., Carandang, K. M., Deane, K. D., Genovese, M. C., Huston, K. K., Kerr, G. S., et al. (2021) · Arthritis Care & Research · doi:10.1002/acr.24596 · Cited by 1,432
Haslam, A., & Prasad, V. (2019) · JAMA Network Open · doi:10.1001/jamanetworkopen.2019.2535 · Cited by 1,413 · cited 1×
“They are prescribed to more than 50% of oncology patients with advanced solid organ tumors.[8,203] The severity of IMH and other irAEs has been stratified into five grades according to common terminology criteria for adverse events.”
An Official ATS Statement: Hepatotoxicity of Antituberculosis Therapy
Saukkonen, J. J., Cohn, D. L., Jasmer, R. M., Schenker, S., Jereb, J., Nolan, C. M., Peloquin, C. A., Gordin, F. M., Nunes, D., Strader, D. B., et al. (2006) · American Journal of Respiratory and Critical Care Medicine · doi:10.1164/rccm.200510-1666st · Cited by 1,216
Criteria of drug-induced liver disorders
(1990) · Journal of Hepatology · doi:10.1016/0168-8278(90)90124-a · Cited by 1,106
HLA-B*5701 genotype is a major determinant of drug-induced liver injury due to flucloxacillin
study, F. T. D., Daly, A. K., Donaldson, P. T., Bhatnagar, P., Shen, Y., Pe’er, I., Floratos, A., Daly, M. J., Goldstein, D. B., John, S., et al. (2009) · Nature Genetics · doi:10.1038/ng.379 · Cited by 1,051
Features and outcomes of 899 patients with drug-induced liver injury: the DILIN Prospective Study
Chalasani, N., Bonkovsky, H. L., Fontana, R., Lee, W., Stolz, A., Talwalkar, J., Reddy, K. R., Watkins, P. B., Navarro, V., Barnhart, H., et al. (2015) · Gastroenterology · doi:10.1053/j.gastro.2015.03.006 · Cited by 925
Self-citationBjörnsson, E. S., Bergmann, O. M., Björnsson, H. K., Kvaran, R. B., & Olafsson, S. (2013) · Gastroenterology · doi:10.1053/j.gastro.2013.02.006 · Cited by 865
ACG Clinical Guideline: the diagnosis and management of idiosyncratic drug-induced liver injury
Chalasani, N. P., Hayashi, P. H., Bonkovsky, H. L., Navarro, V. J., Lee, W. M., & Fontana, R. J. (2014) · American Journal of Gastroenterology · doi:10.1038/ajg.2014.131 · Cited by 860
Self-citationANDRADE, R., LUCENA, M., FERNANDEZ, M., PELAEZ, G., PACHKORIA, K., GARCIARUIZ, E., GARCIAMUNOZ, B., GONZALEZGRANDE, R., PIZARRO, A., & DURAN, J. (2005) · Gastroenterology · doi:10.1016/j.gastro.2005.05.006 · Cited by 856
Drug-Induced Acute Liver Failure: Results of a U.S. Multicenter, Prospective Study
Reuben, A., Koch, D. G., & Lee, W. M. (2010) · Hepatology · doi:10.1002/hep.23937 · Cited by 772
Self-citationChalasani, N., Fontana, R. J., Bonkovsky, H. L., Watkins, P. B., Davern, T., Serrano, J., Yang, H., & Rochon, J. (2008) · Gastroenterology · doi:10.1053/j.gastro.2008.09.011 · Cited by 755
Self-citationRUCAM in Drug and Herb Induced Liver Injury: The Update
Danan, G., & Teschke, R. (2015) · International Journal of Molecular Sciences · doi:10.3390/ijms17010014 · Cited by 729
Incidence of drug-induced hepatic injuries: A French population-based study
Sgro, C., Clinard, F., Ouazir, K., Chanay, H., Allard, C., Guilleminet, C., Lenoir, C., Lemoine, A., & Hillon, P. (2002) · Hepatology · doi:10.1053/jhep.2002.34857 · Cited by 716
Drug-induced liver injury—types and phenotypes
Hoofnagle, J. H., & Björnsson, E. S. (2019) · New England Journal of Medicine · doi:10.1056/nejmra1816149 · Cited by 652
Loomba, R. S., & Liang, T. J. (2017) · Gastroenterology · doi:10.1053/j.gastro.2017.02.009 · Cited by 619
Incidence and Etiology of Drug-Induced Liver Injury in Mainland China
Shen, T., Liu, Y., Shang, J., Xie, Q., Li, J., Yan, M., Xu, J., Niu, J., Liu, J., Watkins, P. B., et al. (2019) · Gastroenterology · doi:10.1053/j.gastro.2019.02.002 · Cited by 615
Lee, W. M., Hynan, L. S., Rossaro, L., Fontana, R. J., Stravitz, R. T., Larson, A. M., Davern, T. J., Murray, N. G., McCashland, T., Reisch, J. S., et al. (2009) · Gastroenterology · doi:10.1053/j.gastro.2009.06.006 · Cited by 607
Self-citationDiscontinuation of Statins in Routine Care Settings: A Cohort Study
Zhang, H., Plutzky, J., Skentzos, S., Morrison, F., Mar, P., Shubina, M., & Turchin, A. (2013) · Annals of Internal Medicine · doi:10.7326/0003-4819-158-7-201304020-00004 · Cited by 548
Chemotherapy and management of tuberculosis in the United Kingdom: recommendations 1998
Joint, T. (1998) · Thorax · doi:10.1136/thx.53.7.536 · Cited by 545
Outcome and prognostic markers in severe drug‐induced liver disease†
Björnsson, E., & Olsson, R. (2005) · Hepatology · doi:10.1002/hep.20800 · Cited by 524
Sterling, T. R., Njie, G. J., Zenner, D., Cohn, D. L., Reves, R. R., Ahmed, A. I., Menzies, D., Horsburgh, C. R., Crane, C. M., Burgos, M. V., et al. (2020) · MMWR Recommendations and Reports · doi:10.15585/mmwr.rr6901a1 · Cited by 514
Benichou, C., Danan, G., & Flahault, A. (1993) · Journal of Clinical Epidemiology · doi:10.1016/0895-4356(93)90102-7 · Cited by 491
Drug-Induced Liver Injury Network (DILIN) Prospective Study: Rationale, Design and Conduct
Fontana, R. J., Watkins, P. B., Bonkovsky, H. L., Chalasani, N., Davern, T., Serrano, J., & Rochon, J. (2009) · Drug Safety · doi:10.2165/00002018-200932010-00005 · Cited by 486
Self-citationAssociation of Acetaminophen Hepatotoxicity With Fasting and Ethanol Use
Whitcomb, D. C. (1994) · JAMA: The Journal of the American Medical Association · doi:10.1001/jama.1994.03520230055038 · Cited by 470
Hepatotoxicity Associated With Isoniazid Preventive Therapy
Nolan, C. M., GOLDBERG, S. V., & Buskin, S. E. (1999) · JAMA · doi:10.1001/jama.281.11.1014 · Cited by 463
Lucena, M. I., Molokhia, M., Shen, Y., Urban, T. J., Aithal, G. P., Andrade, R. J., Day, C. P., Ruiz–Cabello, F., Donaldson, P. T., Stephens, C., et al. (2011) · Gastroenterology · doi:10.1053/j.gastro.2011.04.001 · Cited by 442
Self-citationDrug-induced liver injury: recent advances in diagnosis and risk assessment
Kullak-Ublick, G. A., Andrade, R. J., Merz, M., End, P., Benesic, A., Gerbes, A. L., & Aithal, G. P. (2017) · Gut · doi:10.1136/gutjnl-2016-313369 · Cited by 438
Drug-induced autoimmune hepatitis: clinical characteristics and prognosis
Björnsson, E., Talwalkar, J., Treeprasertsuk, S., Kamath, P. S., Takahashi, N., Sanderson, S., Neuhauser, M., & Lindor, K. (2010) · Hepatology · doi:10.1002/hep.23588 · Cited by 436
Antoine, D. J., Dear, J. W., Lewis, P. J. S., Platt, V., Coyle, J., Masson, M., Thanacoody, R. H. K., Gray, A. J., Webb, D. J., Moggs, J. G., et al. (2013) · Hepatology · doi:10.1002/hep.26294 · Cited by 434
Acetaminophen Toxicity in an Urban County Hospital
Schiødt, F. V., Rochling, F. A., Casey, D. L., & Lee, W. M. (1997) · New England Journal of Medicine · doi:10.1056/nejm199710163371602 · Cited by 422
Self-citationAcute and clinically relevant drug‐induced liver injury: a population based case‐control study
de Abajo, F. J., Montero, D., Madurga, M., & Rodríguez, L. A. G. (2004) · British Journal of Clinical Pharmacology · doi:10.1111/j.1365-2125.2004.02133.x · Cited by 419
Liver injury from herbals and dietary supplements in the U.S. Drug-Induced Liver Injury Network
Navarro, V. J., Barnhart, H., Bonkovsky, H. L., Davern, T., Fontana, R. J., Grant, L., Reddy, R. K., Seeff, L. B., Serrano, J., Sherker, A. H., et al. (2014) · Hepatology · doi:10.1002/hep.27317 · Cited by 418 · cited 1×
“[125] Based on DILIN Registry data, HDS comprise approximately 20% of all cases of liver injury encountered in adults.[28] Regulation of products in the United States is minimal: Manufacturers are not compelled to prove that their product is safe, and only need to attest to the product's safety based on historical use.”
Self-citationDrug-induced liver injury: Interactions between drug properties and host factors
Chen, M., Suzuki, A., Borlak, J. T., Andrade, R. J., & Lucena, M. I. (2015) · Journal of Hepatology · doi:10.1016/j.jhep.2015.04.016 · Cited by 415
Self-citationChen, M., Suzuki, A., Thakkar, S., Yu, K., Hu, C., & Tong, W. (2016) · Drug Discovery Today · doi:10.1016/j.drudis.2016.02.015 · Cited by 398
Self-citationLammert, C. S., Einarsson, S., Saha, C., Niklasson, A., Bjornsson, E. S., & Chalasani, N. (2008) · Hepatology · doi:10.1002/hep.22272 · Cited by 396
Kleiner, D. E., Chalasani, N. P., Lee, W. M., Fontana, R. J., Bonkovsky, H. L., Watkins, P. B., Hayashi, P. H., Davern, T. J., Navarro, V., Reddy, R., et al. (2014) · Hepatology · doi:10.1002/hep.26709 · Cited by 396
Self-citationOutcomes in Adults With Acute Liver Failure Between 1998 and 2013: An Observational Cohort Study
Reuben, A., Tillman, H., Fontana, R. J., Davern, T., McGuire, B., Stravitz, R. T., Durkalski, V., Larson, A. M., Liou, I., Fix, O., et al. (2016) · Annals of Internal Medicine · doi:10.7326/m15-2211 · Cited by 390
Self-citationMenter, A., Gelfand, J. M., Connor, C. J., Armstrong, A. W., Cordoro, K. M., Davis, D. M. R., Elewski, B. E., Gordon, K. B., Gottlieb, A. B., Kaplan, D. H., et al. (2020) · Journal of the American Academy of Dermatology · doi:10.1016/j.jaad.2020.02.044 · Cited by 389
High-Fidelity Drug-Induced Liver Injury Screen Using Human Pluripotent Stem Cell–Derived Organoids
Shinozawa, T., Kimura, M., Cai, Y., Saiki, N., Yoneyama, Y., Ouchi, R., Koike, H., Maezawa, M., Zhang, R.-R., Dunn, A., et al. (2021) · Gastroenterology · doi:10.1053/j.gastro.2020.10.002 · Cited by 378
Hy's law: predicting serious hepatotoxicity
Temple, R. (2006) · Pharmacoepidemiology and Drug Safety · doi:10.1002/pds.1211 · Cited by 354
Development and validation of a clinical scale for the diagnosis of drug-induced hepatitis
Maria, V. A., & Victorino, R. M. (1997) · Hepatology · doi:10.1002/hep.510260319 · Cited by 351
Chen, M., Borlak, J., & Tong, W. (2013) · Hepatology · doi:10.1002/hep.26208 · Cited by 348
Richardson, P. G. G., Riches, M., Kernan, N. A., Brochstein, J. A., Mineishi, S., Termuhlen, A. M., Arai, S., Grupp, S. A., Guinan, E. C., Martin, P. L., et al. (2016) · Blood · doi:10.1182/blood-2015-10-676924 · Cited by 343
Acetaminophen Hepatotoxicity: The First 35 Years
Rumack, B. H. (2002) · Journal of Toxicology Clinical Toxicology · doi:10.1081/clt-120002882 · Cited by 335
Acute Hepatitis E Infection Accounts for Some Cases of Suspected Drug-Induced Liver Injury
Davern, T. J., Chalasani, N., Fontana, R. J., Hayashi, P. H., Protiva, P., Kleiner, D. E., Engle, R. E., Nguyen, H., Emerson, S. U., Purcell, R. H., et al. (2011) · Gastroenterology · doi:10.1053/j.gastro.2011.07.051 · Cited by 329
Self-citationStandardization of nomenclature and causality assessment in drug‐induced liver injury
Fontana, R. J., Seeff, L. B., Andrade, R. J., Bjornsson, E. S., Day, C. P., Serrano, J., & Hoofnagle, J. H. (2010) · Hepatology · doi:10.1002/hep.23696 · Cited by 323
Self-citationRockey, D. C., Seeff, L. B., Rochon, J., Freston, J., Chalasani, N., Bonacini, M., Fontana, R. J., & Hayashi, P. H. (2010) · Hepatology · doi:10.1002/hep.23577 · Cited by 313
Self-citationSuzuki, A., Brunt, E. M., Kleiner, D. E., Miquel, R., Smyrk, T. C., Andrade, R. J., Lucena, I. M., Castiella, A., Lindor, K., & Björnsson, E. (2011) · Hepatology · doi:10.1002/hep.24481 · Cited by 310
Self-citationAnticonvulsant Hypersensitivity Syndrome
Knowles, S. R., Shapiro, L. E., & Shear, N. H. (1999) · Drug Safety · doi:10.2165/00002018-199921060-00005 · Cited by 309
Robles–Diaz, M., Lucena, M. I., Kaplowitz, N., Stephens, C., Medina–Cáliz, I., González–Jimenez, A., Ulzurrun, E., Gonzalez, A. F., Fernandez, M. C., Romero–Gómez, M., et al. (2014) · Gastroenterology · doi:10.1053/j.gastro.2014.03.050 · Cited by 301
Estimates of acetaminophen (paracetomal)‐associated overdoses in the United States
Nourjah, P. A., Ahmad, S. R., Karwoski, C. B., & Willy, M. E. (2005) · Pharmacoepidemiology and Drug Safety · doi:10.1002/pds.1191 · Cited by 295
Hepatotoxicity From Immune Checkpoint Inhibitors: A Systematic Review and Management Recommendation
Peeraphatdit, T. (., Wang, J., Odenwald, M. A., Hu, S., Hart, J., & Charlton, M. R. (2020) · Hepatology · doi:10.1002/hep.31227 · Cited by 264
Isoniazid Hepatotoxicity Associated With Treatment of Latent Tuberculosis Infection
Fountain, F. F., Tolley, E. A., Chrisman, C. R., & Self, T. H. (2005) · CHEST Journal · doi:10.1378/chest.128.1.116 · Cited by 256
Women encounter ADRs more often than do men
Zopf, Y., Rabe, C., Neubert, A. C., Gaßmann, K., Rascher, W., Hahn, E. G., Brune, K., & Dormann, H. (2008) · European Journal of Clinical Pharmacology · doi:10.1007/s00228-008-0494-6 · Cited by 254
Spectrum of statin hepatotoxicity: Experience of the drug-induced liver injury network
Russo, M. W., Hoofnagle, J. H., Gu, J., Fontana, R. J., Barnhart, H. X., Kleiner, D. E., Chalasani, N., & Bonkovsky, H. L. (2014) · Hepatology · doi:10.1002/hep.27157 · Cited by 253
Self-citationLewis, J. H., Mortensen, M. E., Zweig, S., Fusco, M. J., Medoff, J. R., & Belder, R. (2007) · Hepatology · doi:10.1002/hep.21848 · Cited by 248
Björnsson, E. S., & Hoofnagle, J. H. (2016) · Hepatology · doi:10.1002/hep.28323 · Cited by 245
Polymerase γ Gene POLG Determines the Risk of Sodium Valproate-Induced Liver Toxicity
Stewart, J. D., Horváth, R., Baruffini, E., Ferrero, I., Bulst, S., Watkins, P. B., Fontana, R. J., Day, C. P., & Chinnery, P. F. (2010) · Hepatology · doi:10.1002/hep.23891 · Cited by 245
Self-citationSafety and Tolerability of Pravastatin in Long-Term Clinical Trials
Pfeffer, M. A., KEECH, A. C., Sacks, F. M., Cobbe, S. M., Tonkin, A. M., Byington, R. P., Davis, B. R., Friedman, C. P., & Braunwald, E. (2002) · Circulation · doi:10.1161/01.cir.0000017634.00171.24 · Cited by 239
An assessment by the Statin Liver Safety Task Force: 2014 update
Bays, H. E., Cohen, D. E., Chalasani, N., & Harrison, S. A. (2014) · Journal of clinical lipidology · doi:10.1016/j.jacl.2014.02.011 · Cited by 235
Hepatotoxicity Associated with Supplements Containing Chinese Green Tea (Camellia sinensis)
Bonkovsky, H. L. (2006) · Annals of Internal Medicine · doi:10.7326/0003-4819-144-1-200601030-00020 · Cited by 231
Church, R. J., Kullak‐Ublick, G. A., Aubrecht, J., Bonkovsky, H. L., Chalasani, N., Fontana, R. J., Goepfert, J. C., Hackman, F., King, N. M. P., Kirby, S., et al. (2019) · Hepatology · doi:10.1002/hep.29802 · Cited by 231
Self-citationA prospective nationwide study of drug-induced liver injury in Korea
Suk, K. T., Kim, D. J., Kim, C. H., Park, S. H., Yoon, J. H., Kim, Y. S., Baik, G. H., Kim, J. B., Kweon, Y. O., Kim, B. I., et al. (2012) · American Journal of Gastroenterology · doi:10.1038/ajg.2012.138 · Cited by 221
Nicoletti, P., Aithal, G. P., Bjornsson, E. S., Andrade, R. J., Sawle, A., Arrese, M., Barnhart, H. X., Bondon-Guitton, E., Hayashi, P. H., Bessone, F., et al. (2017) · Gastroenterology · doi:10.1053/j.gastro.2016.12.016 · Cited by 221
Self-citationFontana, R. J., Hayashi, P. H., Gu, J., Reddy, K. R., Barnhart, H., Watkins, P. B., Serrano, J., Lee, W. M., Chalasani, N., Stolz, A., et al. (2014) · Gastroenterology · doi:10.1053/j.gastro.2014.03.045 · Cited by 218
Self-citationComparison of Two Clinical Scales for Causality Assessment in Hepatotoxicity
Lucena, M. I., Camargo, R., Andrade, R. J., Perez-Sanchez, C. J., & De La Cuesta, F. S. (2001) · Hepatology · doi:10.1053/jhep.2001.20645 · Cited by 212
Bakke, O. M., Manocchia, M., de Abajo, F. J., Kaitin, K. I., & Lasagna, L. C. (1995) · Clinical Pharmacology & Therapeutics · doi:10.1016/0009-9236(95)90078-0 · Cited by 205
Bruno, S., Maisonneuve, P., Castellana, P., Rotmensz, N., Rossi, S., Maggioni, M., Persico, M., Colombo, A., Monasterolo, F., Casadei-Giunchi, D., et al. (2005) · BMJ · doi:10.1136/bmj.38391.663287.e0 · Cited by 201
Devarbhavi, H., Dierkhising, R., Kremers, W. K., Sandeep, M. S., Karanth, D., & Adarsh, C. K. (2010) · American Journal of Gastroenterology · doi:10.1038/ajg.2010.287 · Cited by 195
Incidence of drug-induced liver injury in medical inpatients
Meier, Y., Cavallaro, M., Roos, M., Pauli‐Magnus, C., Folkers, G., Meier, P. J., & Fattinger, K. E. (2005) · European Journal of Clinical Pharmacology · doi:10.1007/s00228-004-0888-z · Cited by 194
Features of autoimmune hepatitis in patients with drug-induced liver injury
de Boer, Y. S., Kosinski, A. S., Urban, T. J., Zhao, Z., Long, N., Chalasani, N., Kleiner, D. E., & Hoofnagle, J. H. (2017) · Clinical Gastroenterology and Hepatology · doi:10.1016/j.cgh.2016.05.043 · Cited by 190
Rosenberg, P., Urwitz, H., Johannesson, A., Ros, A.-M., Lindholm, J., Kinnman, N., & Hultcrantz, R. (2007) · Journal of Hepatology · doi:10.1016/j.jhep.2007.01.024 · Cited by 185
Rochon, J., Protiva, P., Seeff, L. B., Fontana, R. J., Liangpunsakul, S., Watkins, P. B., Davern, T. J., & McHutchison, J. G. (2008) · Hepatology · doi:10.1002/hep.22442 · Cited by 180
Self-citationJames, L. P., Letzig, L., Simpson, P. M., Capparelli, E., Roberts, D. W., Hinson, J. A., Davern, T. J., & Lee, W. M. (2009) · Drug Metabolism and Disposition · doi:10.1124/dmd.108.026195 · Cited by 175
Self-citationHepatotoxicity of statins and other lipid‐lowering agents
Björnsson, E. S. (2017) · Liver International · doi:10.1111/liv.13308 · Cited by 173
United States Pharmacopeia (USP) comprehensive review of the hepatotoxicity of green tea extracts
Oketch-Rabah, H. A., Roe, A. L., Rider, C. V., Bonkovsky, H. L., Giancaspro, G. I., Navarro, V., Paine, M. F., Betz, J. M., Marles, R. J., Casper, S., et al. (2020) · Toxicology Reports · doi:10.1016/j.toxrep.2020.02.008 · Cited by 168
Self-citationAthyros, V. G., Boutari, C., Stavropoulos, K., Anagnostis, P. G., Imprialos, K. P., Doumas, M. N., & Karagiannis, A. I. (2018) · Current Vascular Pharmacology · doi:10.2174/1570161115666170621082910 · Cited by 160
A revised electronic version of RUCAM for the diagnosis of DILI
Hayashi, P. H., Lucena, M. I., Fontana, R. J., Bjornsson, E. S., Aithal, G. P., Barnhart, H., Gonzalez‐Jimenez, A., Yang, Q., Gu, J., Andrade, R. J., et al. (2022) · Hepatology · doi:10.1002/hep.32327 · Cited by 160
Self-citationSquires, R. H., Dhawan, A., Alonso, E., Narkewicz, M. R., Shneider, B. L., Rodriguez-Baez, N., Olio, D. D., Karpen, S., Bucuvalas, J., Lobritto, S., et al. (2013) · Hepatology · doi:10.1002/hep.26001 · Cited by 159
Bjornsson, E. S., Kalaitzakis, E., & Olsson, R. (2007) · Alimentary Pharmacology & Therapeutics · doi:10.1111/j.1365-2036.2007.03330.x · Cited by 158
The Treatment of Acetaminophen Poisoning
Prescott, L. F., & Critchley, J. (1983) · The Annual Review of Pharmacology and Toxicology · doi:10.1146/annurev.pa.23.040183.000511 · Cited by 156
Comprehensive analysis and insights gained from long-term experience of the Spanish DILI Registry
Stephens, C., Robles-Diaz, M., Medina-Caliz, I., Garcia-Cortes, M., Ortega-Alonso, A., Sanabria-Cabrera, J., Gonzalez-Jimenez, A., Alvarez-Alvarez, I., Slim, M., Jimenez-Perez, M., et al. (2021) · Journal of Hepatology · doi:10.1016/j.jhep.2021.01.029 · Cited by 148
Development of an Accurate Index for Predicting Outcomes of Patients With Acute Liver Failure
Rutherford, A., King, L. Y., Hynan, L. S., Vedvyas, C., Lin, W., Lee, W. M., & Chung, R. T. (2012) · Gastroenterology · doi:10.1053/j.gastro.2012.07.113 · Cited by 146
Self-citationDara, L., Liu, Z., & Kaplowitz, N. (2015) · Liver International · doi:10.1111/liv.12988 · Cited by 144
Definition and risk factors for chronicity following acute idiosyncratic drug-induced liver injury
Medina-Caliz, I., Robles-Diaz, M., Garcia-Muñoz, B., Stephens, C., Ortega-Alonso, A., Garcia-Cortes, M., González-Jimenez, A., Sanabria-Cabrera, J. A., Moreno, I., Fernandez, M. C., et al. (2016) · Journal of Hepatology · doi:10.1016/j.jhep.2016.05.003 · Cited by 140
Important Elements for the Diagnosis of Drug-Induced Liver Injury
Agarwal, V. K., McHutchison, J. G., & Hoofnagle, J. H. (2010) · Clinical Gastroenterology and Hepatology · doi:10.1016/j.cgh.2010.02.008 · Cited by 138
Li, C., Rao, T., Chen, X., Zou, Z., Wei, A., Tang, J., Xiong, P., Li, P., Jing, J., He, T., et al. (2019) · Hepatology · doi:10.1002/hep.30660 · Cited by 138
Bonkovsky, H. L., Kleiner, D. E., Gu, J., Odin, J. A., Russo, M. W., Navarro, V. M., Fontana, R. J., Ghabril, M. S., Barnhart, H., Hoofnagle, J. H., et al. (2017) · Hepatology · doi:10.1002/hep.28967 · Cited by 137
Self-citationA missense variant in PTPN22 is a risk factor for drug-induced liver injury
Cirulli, E. T., Nicoletti, P., Abramson, K., Andrade, R. J., Bjornsson, E. S., Chalasani, N., Fontana, R. J., Hallberg, P., Li, Y. J., Lucena, M. I., et al. (2019) · Gastroenterology · doi:10.1053/j.gastro.2019.01.034 · Cited by 137
Self-citationDevelopment of a Model to Predict Transplant-free Survival of Patients With Acute Liver Failure
Koch, D., Tillman, H., Durkalski, V., Lee, W. M., & Reuben, A. (2016) · Clinical Gastroenterology and Hepatology · doi:10.1016/j.cgh.2016.03.046 · Cited by 135
Self-citationThulin, P., Nordahl, G., Gry, M., Yimer, G., Aklillu, E., Makonnen, E., Aderaye, G., Lindquist, L., Mattsson, C. M., Ekblom, B. T., et al. (2013) · Liver International · doi:10.1111/liv.12322 · Cited by 130
Harrill, A. H., Roach, J. M., Fier, I., Eaddy, J. S., Kurtz, C. L., Antoine, D. J., Spencer, D. M., Kishimoto, T., Pisetsky, D. S., Park, B. K., et al. (2012) · Clinical Pharmacology & Therapeutics · doi:10.1038/clpt.2012.40 · Cited by 130
Björnsson, H. K., Björnsson, E. S., Avula, B., Khan, I. A., Jonasson, J. G., Ghabril, M., Hayashi, P. H., & Navarro, V. (2020) · Liver International · doi:10.1111/liv.14393 · Cited by 125
Self-citationThe Pathology of Drug-Induced Liver Injury
Kleiner, D. E. (2009) · Seminars in Liver Disease · doi:10.1055/s-0029-1240005 · Cited by 125
Urban, T. J., Nicoletti, P., Chalasani, N., Serrano, J., Stolz, A., Daly, A. K., Aithal, G. P., Dillon, J., Navarro, V., Odin, J., et al. (2017) · Journal of Hepatology · doi:10.1016/j.jhep.2017.03.010 · Cited by 124
Self-citationAcetylation Rates and Monthly Liver Function Tests during One Year of Isoniazid Preventive Therapy
Mitchell, J. R., Long, M. W., Thorgeirsson, U. P., & Jollow, D. J. (1975) · CHEST Journal · doi:10.1378/chest.68.2.181 · Cited by 123
Death and liver transplantation within 2 years of onset of drug‐induced liver injury
Hayashi, P. H., Rockey, D. C., Fontana, R. J., Tillmann, H. L., Kaplowitz, N., Barnhart, H. X., Gu, J., Chalasani, N. P., Reddy, K. R., Sherker, A. H., et al. (2017) · Hepatology · doi:10.1002/hep.29283 · Cited by 123
Self-citationOverdose pattern and outcome in paracetamol‐induced acute severe hepatotoxicity
Craig, D. G. N., Bates, C. M., Davidson, J. S., Martin, K. G., Hayes, P. C., & Simpson, K. J. (2010) · British Journal of Clinical Pharmacology · doi:10.1111/j.1365-2125.2010.03819.x · Cited by 120
Drug‐induced liver injury in Japan: An analysis of 1676 cases between 1997 and 2006
Takikawa, H., Murata, Y., Horiike, N., Fukui, H., & Onji, M. (2009) · Hepatology Research · doi:10.1111/j.1872-034x.2008.00486.x · Cited by 119
Stine, J. G., & Lewis, J. H. (2015) · Expert Review of Gastroenterology & Hepatology · doi:10.1586/17474124.2016.1127756 · Cited by 119
Drug Induced Steatohepatitis: An Uncommon Culprit of a Common Disease
Rabinowich, L., & Shibolet, O. (2015) · BioMed Research International · doi:10.1155/2015/168905 · Cited by 118
Foureau, D., Walling, T. L., Maddukuri, V. C., Anderson, W. E., Culbreath, K., Kleiner, D. E., Ahrens, W. A., Jacobs, C., Watkins, P. B., Fontana, R. J., et al. (2014) · Clinical & Experimental Immunology · doi:10.1111/cei.12558 · Cited by 116
Self-citationPTPN22: Its role in SLE and autoimmunity
Chung, S. A., & Criswell, L. A. (2007) · Autoimmunity · doi:10.1080/08916930701510848 · Cited by 113
Bessone, F., Dirchwolf, M., Rodil, M. A., Razori, M. V., & Roma, M. G. (2018) · Alimentary Pharmacology & Therapeutics · doi:10.1111/apt.14952 · Cited by 113
Prescription Drug Use Among Adults Aged 40-79 in the United States and Canada.
Hales, C. M., Servais, J., Martin, C. B., & Kohen, D. (2019) · PubMed · Cited by 113
Laharie, D., Sénéschal, J., Schaeverbeke, T., Doutre, M. ‐., Longy‐Boursier, M., Pellegrin, J., Chabrun, É., Villars, S., Zerbib, F., & de Lédinghen, V. (2010) · Journal of Hepatology · doi:10.1016/j.jhep.2010.04.043 · Cited by 111
Role of Osteopontin in Liver Diseases
Wen, Y., Jeong, S., Xia, Q., & Kong, X. (2016) · International Journal of Biological Sciences · doi:10.7150/ijbs.16445 · Cited by 111
Data Brief 399: Dietary Supplement Use Among Adults: United States, 2017–2018
Mishra, S., Stierman, B. D., Gahche, J. J., & Potischman, N. A. (2021) · doi:10.15620/cdc:101131 · Cited by 111
Fontana, R. J., Hayashi, P. H., Barnhart, H. X., Kleiner, D. E., Reddy, K. R., Chalasani, N., Lee, W. M., Stolz, A., Phillips, T. A., Serrano, J., et al. (2015) · The American Journal of Gastroenterology · doi:10.1038/ajg.2015.283 · Cited by 107
Self-citationHLA‐B*35:01 and Green Tea–Induced Liver Injury
Hoofnagle, J. H., Bonkovsky, H. L., Phillips, E. J., Li, Y., Ahmad, J., Barnhart, H. X., Durazo, F. A., Fontana, R. J., Gu, J., Khan, I. A., et al. (2020) · Hepatology · doi:10.1002/hep.31538 · Cited by 105
Self-citationL-Carnitine for Acute Valproic Acid Overdose: A Systematic Review of Published Cases
Perrott, J. L., Murphy, N. G., & Zed, P. J. (2010) · Annals of Pharmacotherapy · doi:10.1345/aph.1p135 · Cited by 100
HLA Alleles Influence the Clinical Signature of Amoxicillin-Clavulanate Hepatotoxicity
Stephens, C. M., López‐Nevot, M. Á., Ruiz‐Cabello, F., Ulzurrun, E., Soriano, G., Romero‐Gómez, M., Moreno-Casares, A., Lucena, M. I., & Andrade, R. J. (2013) · PLoS ONE · doi:10.1371/journal.pone.0068111 · Cited by 99
Nicoletti, P., Aithal, G. P., Chamberlain, T. C., Coulthard, S. A., Alshabeeb, M. A., Grove, J. I., Andrade, R. J., Bjornsson, E. S., Dillon, J. F., Hallberg, P., et al. (2019) · Clinical Pharmacology & Therapeutics · doi:10.1002/cpt.1375 · Cited by 99
Eighteen cases of liver injury following ingestion of Polygonum multiflorum
Dong, H., Slain, D., Cheng, J., Ma, W., & Liang, W. (2014) · Complementary Therapies in Medicine · doi:10.1016/j.ctim.2013.12.008 · Cited by 98
Tsung, I., Dolan, R. D., Lao, C. D., Fecher, L. A., Riggenbach, K., Yeboah‐Korang, A., & Fontana, R. J. (2019) · Alimentary Pharmacology & Therapeutics · doi:10.1111/apt.15413 · Cited by 94
Self-citationHepatotoxicity Induced by Herbal and Dietary Supplements
Lucena, M. I., & Navarro, V. J. (2014) · Seminars in Liver Disease · doi:10.1055/s-0034-1375958 · Cited by 93
Self-citationSteroid and Ursodesoxycholic Acid Combination Therapy in Severe Drug-Induced Liver Injury
Wree, A., Dechêne, A., Herzer, K., Hilgard, P., Syn, W.-K., Gerken, G., & Canbay, A. (2011) · Digestion · doi:10.1159/000322298 · Cited by 93
Teschke, R., & Danan, G. (2020) · Medicines · doi:10.3390/medicines7100062 · Cited by 91
Zen, Y., Chen, Y., Jeng, Y., Tsai, H., & Yeh, M. M. (2019) · Histopathology · doi:10.1111/his.14000 · Cited by 89
Devarbhavi, H., Joseph, T., Sunil Kumar, N., Rathi, C., Thomas, V., Prasad Singh, S., Sawant, P., Goel, A., Eapen, C. E., Rai, P., et al. (2021) · Journal of Clinical and Experimental Hepatology · doi:10.1016/j.jceh.2020.11.002 · Cited by 87
Lombardi, N., Crescioli, G., Maggini, V., Ippoliti, I., Menniti‐Ippolito, F., Gallo, E. R., Brilli, V., Lanzi, C., Mannaioni, G., Firenzuoli, F., et al. (2020) · British Journal of Clinical Pharmacology · doi:10.1111/bcp.14460 · Cited by 85
Schmajuk, G., Miao, Y., Yazdany, J., Boscardin, W. J., Daikh, D., & Steinman, M. A. (2014) · Arthritis Care & Research · doi:10.1002/acr.22294 · Cited by 84
Polygenic architecture informs potential vulnerability to drug-induced liver injury
Koido, M., Kawakami, E., Fukumura, J., Noguchi, Y., Ohori, M., Nio, Y., Nicoletti, P., Aithal, G. P., Daly, A. K., Watkins, P. B., et al. (2020) · Nature Medicine · doi:10.1038/s41591-020-1023-0 · Cited by 84
Jiang, F., Yan, H., Liang, L., Du, J., Jin, S., Yang, S., Wang, H., Hu, T., Zhu, Y., Wang, G., et al. (2021) · Liver International · doi:10.1111/liv.14896 · Cited by 84
Zen, Y., & Yeh, M. M. (2019) · Seminars in Diagnostic Pathology · doi:10.1053/j.semdp.2019.07.009 · Cited by 82
Erickson, A. R., Reddy, V., Vogelgesang, S. A., & West, S. G. (1995) · Arthritis & Rheumatism · doi:10.1002/art.1780380814 · Cited by 80
Underhill, T. J., Greene, M. K., & Dove, A. F. (1990) · Emergency Medicine Journal · doi:10.1136/emj.7.3.148 · Cited by 79
Goodman, Z. D. (2002) · Clinics in Liver Disease · doi:10.1016/s1089-3261(02)00011-9 · Cited by 78
Clinical Features, Diagnosis, and Natural History of Drug-Induced Liver Injury
Fontana, R. J., & Hayashi, P. H. (2014) · Seminars in Liver Disease · doi:10.1055/s-0034-1375955 · Cited by 77
Self-citationLi, Y., Phillips, E. J., Dellinger, A., Nicoletti, P., Schutte, R., Li, D., Ostrov, D. A., Fontana, R. J., Watkins, P. B., Stolz, A., et al. (2021) · Hepatology · doi:10.1002/hep.31258 · Cited by 76
Self-citationPerez‐Gutthann, S., & Rodeíguez, L. A. G. (1993) · Epidemiology · doi:10.1097/00001648-199311000-00004 · Cited by 75
Chalasani, N., Reddy, R. K. K., Fontana, R. J., Barnhart, H., Gu, J., Hayashi, P. H., Ahmad, J., Stolz, A., Navarro, V., & Hoofnagle, J. H. (2017) · American Journal of Gastroenterology · doi:10.1038/ajg.2017.215 · Cited by 75
Self-citationStolz, A., Navarro, V. J., Hayashi, P. H., Fontana, R. J., Barnhart, H. X., Gu, J., Chalasani, N., Vega, M., Bonkovsky, H. L., Seeff, L. B., et al. (2019) · Alimentary Pharmacology & Therapeutics · doi:10.1111/apt.15211 · Cited by 71
Self-citationHerbal hepatotoxicity: Challenges and pitfalls of causality assessment methods
Teschke, R., Frenzel, C., Schulze, J., & Eickhoff, A. (2013) · World Journal of Gastroenterology · doi:10.3748/wjg.v19.i19.2864 · Cited by 68
Takikawa, H. (2003) · Hepatology Research · doi:10.1016/s1386-6346(03)00232-8 · Cited by 68
Khoury, T., Rmeileh, A. A., Yosha, L., Benson, A. A., Daher, S., & Mizrahi, M. (2015) · Journal of Clinical and Translational Hepatology · doi:10.14218/jcth.2015.00007 · Cited by 66
Associations of Drug Lipophilicity and Extent of Metabolism with Drug-Induced Liver Injury
McEuen, K., Borlak, J. T., Tong, W., & Chen, M. (2017) · International Journal of Molecular Sciences · doi:10.3390/ijms18071335 · Cited by 66
Comedications alter drug-induced liver injury reporting frequency: Data mining in the WHO VigiBase™
Suzuki, A., Yuen, N., Ilić, K., Miller, R. T., Reese, M. J., Brown, H. R., Ambroso, J. L., Falls, J. G., & Hunt, C. M. (2015) · Regulatory Toxicology and Pharmacology · doi:10.1016/j.yrtph.2015.05.004 · Cited by 63
Self-citationAcute Liver Injury With Therapeutic Doses of Acetaminophen: A Prospective Study
Louvet, A., Ntandja Wandji, L. C., Lemaître, E., Khaldi, M., Lafforgue, C., Artru, F., Quesnel, B., Lassailly, G., Dharancy, S., & Mathurin, P. (2021) · Hepatology · doi:10.1002/hep.31678 · Cited by 63
Drug-induced autoimmune hepatitis associated with turmeric dietary supplement use
Lukefahr, A. L., McEvoy, S., Alfafara, C., & Funk, J. L. (2018) · BMJ Case Reports · doi:10.1136/bcr-2018-224611 · Cited by 61
Nicoletti, P., Devarbhavi, H., Goel, A., Venkatesan, R., Eapen, C. E., Grove, J. I., Zafer, S., Bjornsson, E., Lucena, M. I., Andrade, R. J., et al. (2021) · Clinical Pharmacology & Therapeutics · doi:10.1002/cpt.2100 · Cited by 61
Pexidartinib Long-Term Hepatic Safety Profile in Patients with Tenosynovial Giant Cell Tumors
Lewis, J. H., Gelderblom, H. A. J., van de Sande, M. A. J., Stacchiotti, S., Healey, J. H., Tap, W. D., Wagner, A. J., Pousa, A. L., Druta, M., Lin, C., et al. (2020) · The Oncologist · doi:10.1002/onco.13629 · Cited by 61
Avancini, J., Maragno, L., Santi, C. G., & Criado, P. R. (2015) · Clinical and Experimental Dermatology · doi:10.1111/ced.12682 · Cited by 60
A Comparison between Two Strategies for Monitoring Hepatic Function during Antituberculous Therapy
Singanayagam, A., Sridhar, S., Dhariwal, J., Abdelaziz, D., Munro, K., Connell, D. W., George, P. M., Molyneaux, P. L., Cooke, G., Burroughs, A. K., et al. (2011) · American Journal of Respiratory and Critical Care Medicine · doi:10.1164/rccm.201105-0850oc · Cited by 60
Sawada, K., Hayashi, H., Nakajima, S., Hasebe, T., Fujiya, M., & Okumura, T. (2019) · Journal of Gastroenterology and Hepatology · doi:10.1111/jgh.14889 · Cited by 60
Licata, A., Maida, M., Cabibi, D., Butera, G., Macaluso, F. S., Alessi, N., Caruso, C., Craxì, A., & Almasio, P. L. (2014) · Digestive and Liver Disease · doi:10.1016/j.dld.2014.08.040 · Cited by 59
Moosa, M. S., Maartens, G., Gunter, H. M., Allie, S., Chughlay, M. F., Setshedi, M., Wasserman, S. A., Stead, D., Hickman, N. E., Stewart, A., et al. (2020) · Clinical Infectious Diseases · doi:10.1093/cid/ciaa1255 · Cited by 59
Causality Assessment for Suspected DILI During Clinical Phases of Drug Development
Regev, A., Seeff, L. B., Merz, M., Ormarsdóttir, S., Aithal, G. P., Gallivan, J., & Watkins, P. B. (2014) · Drug Safety · doi:10.1007/s40264-014-0185-4 · Cited by 57
Tuberculosis — United States, 2018
Talwar, A., Tsang, C. A., Price, S. F., Pratt, R. H., Walker, W. L., Schmit, K. M., & Langer, A. J. (2019) · MMWR Morbidity and Mortality Weekly Report · doi:10.15585/mmwr.mm6811a2 · Cited by 57
Hayashi, P. H., Fontana, R. J., Chalasani, N., Stolz, A., Talwalkar, J. A., Navarro, V. J., Lee, W. M., Davern, T. J., Kleiner, D. E., Gu, J., et al. (2015) · Clinical Gastroenterology and Hepatology · doi:10.1016/j.cgh.2015.02.024 · Cited by 56
Self-citationThe role of HLA-A*33:01 in patients with cholestatic hepatitis attributed to terbinafine
Fontana, R. J., Cirulli, E. T., Gu, J., Kleiner, D. E., Ostrov, D. A., Phillips, E. J., Schutte, R. J., Barnhart, H. X., Chalasani, N., Watkins, P. B., et al. (2018) · Journal of Hepatology · doi:10.1016/j.jhep.2018.08.004 · Cited by 54
Self-citationGasmi, B., & Kleiner, D. E. (2019) · Clinics in Liver Disease · doi:10.1016/j.cld.2019.09.004 · Cited by 53
Histopathologic Manifestations of Drug-induced Hepatotoxicity
Zhang, X., Ouyang, J., & Thung, S. N. (2013) · Clinics in Liver Disease · doi:10.1016/j.cld.2013.07.004 · Cited by 52
Histopathological challenges in suspected drug‐induced liver injury
Kleiner, D. E. (2017) · Liver International · doi:10.1111/liv.13584 · Cited by 52
Benesic, A., Rotter, I., Dragoi, D., Weber, S., Buchholtz, M.-L., & Gerbes, A. L. (2018) · Clinical Gastroenterology and Hepatology · doi:10.1016/j.cgh.2018.04.049 · Cited by 52
Navarro, V., Avula, B., Khan, I., Verma, M., Seeff, L., Serrano, J., Stolz, A., Fontana, R., & Ahmad, J. (2019) · Hepatology Communications · doi:10.1002/hep4.1346 · Cited by 52
Self-citationGhabril, M., Gu, J., Yoder, L., Corbito, L., Ringel, A., Beyer, C. D., Vuppalanchi, R., Barnhart, H., Hayashi, P. H., & Chalasani, N. (2019) · Gastroenterology · doi:10.1053/j.gastro.2019.07.006 · Cited by 52
Presentation of drug-induced liver injury in Singapore.
Ct, W. (2006) · PubMed · Cited by 50
Beneficial effect of corticosteroids for patients with severe drug‐induced liver injury
Hu, P. F., Wang, P. Q., Chen, H., Hu, X. F., Xie, Q. P., Shi, J., Lin, L., & Xie, W. F. (2016) · Journal of Digestive Diseases · doi:10.1111/1751-2980.12383 · Cited by 50
Hayashi, P. H., Barnhart, H. X., Fontana, R. J., Chalasani, N., Davern, T. J., Talwalkar, J. A., Reddy, K. R., Stolz, A., Hoofnagle, J. H., & Rockey, D. C. (2014) · Liver International · doi:10.1111/liv.12540 · Cited by 49
Self-citationSuzuki, A., Yuen, N., Walsh, J. S. A., Papay, J. I., Hunt, C. M., & Diehl, A. M. (2009) · Clinical Gastroenterology and Hepatology · doi:10.1016/j.cgh.2009.03.034 · Cited by 48
Self-citationInterplay of gender, age and drug properties on reporting frequency of drug-induced liver injury
George, N. E., Chen, M., Yuen, N., Hunt, C. M., & Suzuki, A. (2018) · Regulatory Toxicology and Pharmacology · doi:10.1016/j.yrtph.2018.01.018 · Cited by 48
Self-citationVuppalanchi, R., Bonkovsky, H. L., Ahmad, J., Barnhart, H. X., Durazo, F. A., Fontana, R. J., Gu, J., Khan, I. A., Kleiner, D. E., Koh, C., et al. (2021) · Clinical Gastroenterology and Hepatology · doi:10.1016/j.cgh.2021.08.015 · Cited by 47
Self-citationTsirigotis, P. D., Sella, T., Shapira, M. Y., Bitan, M., Bloom, A. I., Kiselgoff, D., Levin, M., Libster, D., Hai, A. A., Gesundheit, B., et al. (2007) · Haematologica · doi:10.3324/haematol.11343 · Cited by 46
Carrascosa, M. F., Salcines-Caviedes, J. R., Lucena, M. I., & Andrade, R. J. (2014) · Journal of Hepatology · doi:10.1016/j.jhep.2014.11.019 · Cited by 45
Drug-induced liver injury in hospitalized patients with notably elevated alanine aminotransferase
Xu, H. (2012) · World Journal of Gastroenterology · doi:10.3748/wjg.v18.i41.5972 · Cited by 42
Roth, S. E., Avigan, M. I., Bourdet, D., Brott, D., Church, R., Dash, A., Keller, D., Sherratt, P., Watkins, P. B., Westcott‐Baker, L., et al. (2020) · Clinical Pharmacology & Therapeutics · doi:10.1002/cpt.1571 · Cited by 42
Drug-Induced Liver Injury from Statins
Meurer, L., & Cohen, S. M. (2019) · Clinics in Liver Disease · doi:10.1016/j.cld.2019.09.007 · Cited by 42
Liver histology in the diagnosis and prognosis of drug-induced liver injury
Kleiner, D. E. (2014) · Clinical Liver Disease · doi:10.1002/cld.371 · Cited by 41
Hepatic Damage by Natural Remedies
Medina-Caliz, I., Gonzalez-Jimenez, A., Garcia-Cortes, M., Lucena, M. I., & Andrade, R. (2018) · Seminars in Liver Disease · doi:10.1055/s-0038-1623518 · Cited by 40
A prospective study on the causes of notably raised alanine aminotransferase (ALT)
Björnsson, H. K., Ólafsson, S., Bergmann, O. M., & Bjornsson, E. S. (2015) · Scandinavian Journal of Gastroenterology · doi:10.3109/00365521.2015.1121516 · Cited by 39
Allopurinol hepatotoxicity is associated with human leukocyte antigen Class I alleles
Fontana, R. J., Li, Y., Phillips, E. J., Saeed, N., Barnhart, H. X., Kleiner, D. E., Hoofnagle, J. H., & the Drug Induced Liver Injury Network (2021) · Liver International · doi:10.1111/liv.14903 · Cited by 39
Self-citationShin, J., Hunt, C. M., Suzuki, A., Papay, J. I., Beach, K. J., & Cheetham, T. C. (2012) · Pharmacoepidemiology and Drug Safety · doi:10.1002/pds.3388 · Cited by 38
Self-citationBessone, F., Hernández, N., Mendizábal, M., Sánchez, A., Paraná, R., Arrese, M. A., Tagle, M., Girala, M., Lizarzábal, M., Carrera, E., et al. (2019) · Clinical Liver Disease · doi:10.1002/cld.778 · Cited by 38
Whritenour, J., Ko, M., Zong, Q., Wang, J., Tartaro, K., Schneider, P., Olson, E., Van Volkenburg, M., Serrano, J., Hayashi, P., et al. (2017) · Journal of Immunotoxicology · doi:10.1080/1547691x.2016.1254305 · Cited by 37
Self-citationDakhoul, L., Ghabril, M., Gu, J., Navarro, V., Chalasani, N., & Serrano, J. (2018) · Clinical Gastroenterology and Hepatology · doi:10.1016/j.cgh.2017.12.036 · Cited by 36
Self-citationDiPaola, F., Molleston, J. P., Gu, J., Cirulli, E. T., Chalasani, N., Barnhart, H., Kleiner, D. E., Hoofnagle, J. H., Fontana, R. J., & US Drug Induced Liver Injury Network (2019) · Journal of Pediatric Gastroenterology and Nutrition · doi:10.1097/mpg.0000000000002383 · Cited by 36
Self-citationAhmad, J., Odin, J. A., Hayashi, P. H., Fontana, R. J., Conjeevaram, H. S., Avula, B., Khan, I. A., Barnhart, H. X., Vuppalanchi, R., & Navarro, V. J. (2020) · Drug and Alcohol Dependence · doi:10.1016/j.drugalcdep.2020.108426 · Cited by 35
Self-citationDILI and Drug Development: A Regulatory Perspective
Avigan, M. (2014) · Seminars in Liver Disease · doi:10.1055/s-0034-1375961 · Cited by 34
Li, M., Sack, J. S., Bell, P., Rahma, O. E., Srivastava, A., Grover, S., & Zucker, S. D. (2021) · JAMA Oncology · doi:10.1001/jamaoncol.2021.4342 · Cited by 34
Seki, N., Uematsu, K., Shibakuki, R., & Eguchi, K. (2006) · Journal of Clinical Oncology · doi:10.1200/jco.2006.05.7109 · Cited by 33
Tools for causality assessment in drug-induced liver disease
Tillmann, H. L., Suzuki, A., Barnhart, H. X., Serrano, J., & Rockey, D. C. (2019) · Current Opinion in Gastroenterology · doi:10.1097/mog.0000000000000526 · Cited by 32
Self-citationUnintended Hepatic Adverse Events Associated with Cancer Chemotherapy
Senior, J. R. (2009) · Toxicologic Pathology · doi:10.1177/0192623309351719 · Cited by 31
Hanatani, T., Sai, K., Tohkin, M., Segawa, K., Kimura, M., Hori, K., Kawakami, J., & Saito, Y. (2014) · Pharmacoepidemiology and Drug Safety · doi:10.1002/pds.3603 · Cited by 31
Ghabril, M., Ma, J., Patidar, K. R., Nephew, L. D., Desai, A. P., Orman, E. S., Vuppalanchi, R., Kubal, C. A., & Chalasani, N. (2021) · Liver Transplantation · doi:10.1002/lt.26246 · Cited by 31
Hepatic injury caused by mianserin.
Otani, K., Kaneko, S., Tasaki, H., & Fukushima, Y. (1989) · BMJ · doi:10.1136/bmj.299.6697.519-a · Cited by 30
Roytman, M. M., Poerzgen, P., & Navarro, V. J. (2018) · Clinical Pharmacology & Therapeutics · doi:10.1002/cpt.1097 · Cited by 30
Self-citationLombardi, A., & Mondelli, M. U. (2019) · Alimentary Pharmacology & Therapeutics · doi:10.1111/apt.15449 · Cited by 30
Presentations, Causes and Outcomes of Drug-Induced Liver Injury in Egypt
Alhaddad, O., Elsabaawy, M., Abdelsameea, E., Abdallah, A. R., Shabaan, A., Ehsan, N. A., Elrefaey, A., Elsabaawy, D. M., & Salama, M. (2020) · Scientific Reports · doi:10.1038/s41598-020-61872-9 · Cited by 30
Drug-induced liver injury in the Australian setting
Sistanizad, M., & Peterson, G. M. (2013) · Journal of Clinical Pharmacy and Therapeutics · doi:10.1111/jcpt.12039 · Cited by 28
Ahmad, J., Rossi, S., Rodgers, S. K., Ghabril, M., Fontana, R. J., Stolz, A., Hayashi, P. H., Barnhart, H. X., Kleiner, D. E., & Bjornsson, E. S. (2018) · Clinical Gastroenterology and Hepatology · doi:10.1016/j.cgh.2018.06.035 · Cited by 28
Self-citationBliven, E. E., & Podewils, L. J. (2009) · PubMed · Cited by 26
Febres-Aldana, C. A., Alghamdi, S., Krishnamurthy, K., & Poppiti, R. J. (2019) · Journal of Clinical and Translational Hepatology · doi:10.14218/jcth.2018.00053 · Cited by 25
Lang, S., Ortmann, J., Rostig, S., & Schiffl, H. (2019) · International Journal of Mycobacteriology · doi:10.4103/ijmy.ijmy_159_18 · Cited by 25
Cited by
Sorted by citations
Liver diseases: epidemiology, causes, trends and predictions
Gan, C., Yuan, Y., Shen, H., Gao, J., Kong, X., Che, Z., Guo, Y., Wang, H., Dong, E., & Xiao, J. (2025) · Signal Transduction and Targeted Therapy · doi:10.1038/s41392-024-02072-z · Cited by 416
Chen, V. L., Morgan, T. R. M., Rotman, Y., Patton, H. M., Cusi, K. J., Kanwal, F., & Kim, W. R. (2024) · Hepatology · doi:10.1097/hep.0000000000001112 · Cited by 235
Mak, L., Liu, K., Chirapongsathorn, S., Yew, K. C., Tamaki, N., Rajaram, R. B., Panlilio, M. T., Lui, R. N.-S., Lee, H. W., Lai, J. C., et al. (2024) · Nature Reviews Gastroenterology & Hepatology · doi:10.1038/s41575-024-00967-4 · Cited by 206
Ge, J., Sun, S., Owens, J., Galvez, V., Gologorskaya, O., Lai, J. C., Pletcher, M. J., & Lai, K. (2024) · Hepatology · doi:10.1097/hep.0000000000000834 · Cited by 199
EASL Clinical Practice Guidelines on the management of autoimmune hepatitis
Dalekos, G., Gatselis, N., Drenth, J. P. H., Heneghan, M., Jørgensen, M., Lohse, A. W., Londoño, M., Muratori, L., Papp, M., Samyn, M., et al. (2025) · Journal of Hepatology · doi:10.1016/j.jhep.2025.03.017 · Cited by 175
Metadata
- Authors
- Fontana, R. J., Liou, I., Reuben, A., Suzuki, A., Fiel, M. I., Lee, W., & Navarro, V.
- Affiliations
- University of Michigan (US)
- University of Washington (US)
- Medical University of South Carolina (US)
- Duke University (US)
- Icahn School of Medicine at Mount Sinai (US)
- The University of Texas Southwestern Medical Center (US)
- Einstein Healthcare Network (US)
- Corresponding author
- Fontana, Robert J.
- Venue
- Hepatology
- Published
- 2023-02-17
- Volume
- 77
- Issue
- 3
- Pages
- 1036-1065
- ISSN
- 0270-9139 (ISSN-L)
- PMC
- PMC9936988
- OpenAlex
- W4288077670
- Cited by
- 340
- References
- 212
- Citations by year
- 2026: 152 · 2025: 85 · 2024: 61 · 2023: 38
- FWCI
- 27.36
- Type
- journal article
- Language
- en
- Open access
- hybrid
- doi.org
- Licence
- Locations
- Hepatology (publishedVersion, cc-by-nc)
- PubMed Central (publishedVersion, cc-by-nc)
- PubMed (publishedVersion)
- Funders
- American Association for the Study of Liver Diseases
- Gilead Sciences
- Alexion Pharmaceuticals
- Topics
- Life Sciences › Pharmacology, Toxicology and Pharmaceutics › Pharmacology › Drug-Induced Hepatotoxicity and Protection
- Health Sciences › Medicine › Complementary and alternative medicine › Complementary and Alternative Medicine Studies
- Life Sciences › Pharmacology, Toxicology and Pharmaceutics › Toxicology › Pharmacovigilance and Adverse Drug Reactions
- Keywords
- drug-induced liver injury, idiosyncratic drug-induced liver injury, acetaminophen hepatotoxicity, liver injury biomarkers, risk stratification, hepatotoxicity
- MeSH terms
- Humans, Dietary Supplements, Chemical and Drug Induced Liver Injury, Chemical and Drug Induced Liver Injury, Chronic
About these checks
Registry, retraction, Cites and statistics results are computed, not judged, with one exception: a printed reference that no index lists is read once by a model before it counts as a citation error. Claims are extracted by a model and kept only when their quote appears verbatim in the text; each cited source is then checked, with a model’s help, for whether it says what the claim relies on. Those verdicts can be wrong — read the claim’s quote and the cited source before relying on one.
A language model drew the claims from the paper on 2026-11-10, under version 3 of the claim definition (model deepseek-v4.1-flash, prompt extract-v3).
A second model labelled each claim on 2026-11-10 (model jev-1.13-20260917, definition revision gold-guideline-v0.2).
Statistics and arithmetic are recomputed, not judged.
Confidence bands are shown only for fields calibrated on our annotated test set. None is calibrated yet, so no band is shown.
What counts as a claim ›How we measure confidence ›How we check this ›
Are you an author, or do you see a problem with this page? Request a review
