

The DOI matches its Crossref record; 43 of the 44 references it cites were found in a registry or an index; none of the 92 sources its claims cite is checked for support yet.
Recommendations from the Pediatric Endocrine Society for Evaluation and Management of Persistent Hypoglycemia in Neonates, Infants, and Children
Open accessAbstract
During the first 24-48 hours of life, as normal neonates transition from intrauterine to extrauterine life, their plasma glucose (PG) concentrations are typically lower than later in life.1Cornblath M. Reisner S.H. Blood glucose in the neonate and its clinical significance.N Engl J Med. 1965; 273: 378-381Crossref PubMed Scopus (116) Google Scholar, 2Srinivasan G. Pildes R.S. Cattamanchi G. Voora S. Lilien L.D. Plasma glucose values in normal neonates: a new look.J Pediatr. 1986; 109: 114-117Abstract Full Text PDF PubMed Scopus (225) Google Scholar, 3Stanley C.A. Rozance P.J. Thornton P.S. De Leon D.D. Harris D. Haymond M.W. et al.Re-evaluating “transitional neonatal hypoglycemia”: mechanism and implications for management.J Pediatr. 2015; 166: 1520-1525Abstract Full Text Full Text PDF PubMed Scopus (128) Google Scholar Published guidelines for screening at-risk newborns and managing low PG concentrations in neonates focus on the immediate neonatal period, but do not address the diagnosis and management of disorders causing recurrent and prolonged hypoglycemia.4Canadian Paediatric SocietyScreening guidelines for newborns at risk for low blood glucose.Paediatr Child Health. 2004; 9: 723-740PubMed Google Scholar, 5Adamkin D.H. Postnatal glucose homeostasis in late-preterm and term infants.Pediatrics. 2011; 127: 575-579Crossref PubMed Scopus (424) Google Scholar, 6Wight N. Marinelli K.A. ABM clinical protocol 1: guidelines for glucose monitoring and treatment of hypoglycemia in breastfed neonates.Breastfeed Med. 2006; 1: 178-184Crossref PubMed Scopus (27) Google Scholar Distinguishing between transitional neonatal glucose regulation in normal newborns and hypoglycemia that persists or occurs for the first time beyond the first 3 days of life is important for prompt diagnosis and effective treatment to avoid serious consequences, including seizures and permanent brain injury.Moreover, the evaluation and management of pediatric hypoglycemia differ in several respects from that in adults, for whom guidelines were recently published.7Cryer P.E. Axelrod L. Grossman A.B. Heller S.R. Montori V.M. Seaquist E.R. et al.Evaluation and management of adult hypoglycemic disorders: an Endocrine Society clinical practice guideline.J Clin Endocrinol Metab. 2009; 94: 709-728Crossref PubMed Scopus (704) Google Scholar First, persistent hypoglycemia most often results from a congenital or genetic defect in regulating secretion of insulin, deficiency of cortisol and/or growth hormone, or defects in the metabolism of glucose, glycogen, and fatty acids. Second, it may be difficult to identify and distinguish newborn infants with a persistent hypoglycemia disorder from those with transitional low glucose levels in the initial 48 hours of life, as detailed in the separate document on transitional neonatal hypoglycemia prepared by our committee.3Stanley C.A. Rozance P.J. Thornton P.S. De Leon D.D. Harris D. Haymond M.W. et al.Re-evaluating “transitional neonatal hypoglycemia”: mechanism and implications for management.J Pediatr. 2015; 166: 1520-1525Abstract Full Text Full Text PDF PubMed Scopus (128) Google Scholar Third, the first few months of life are the most vulnerable period for developmental disability, which occurs in ∼25%-50% of children with congenital hyperinsulinism. Early recognition and treatment are crucial for preventing these sequelae.8Menni F. de Lonlay P. Sevin C. Touati G. Peigne C. Barbier V. et al.Neurologic outcomes of 90 neonates and infants with persistent hyperinsulinemic hypoglycemia.Pediatrics. 2001; 107: 476-479Crossref PubMed Scopus (271) Google Scholar, 9Steinkrauss L. Lipman T.H. Hendell C.D. Gerdes M. Thornton P.S. Stanley C.A. Effects of hypoglycemia on developmental outcome in children with congenital hyperinsulinism.J Pediatr Nurs. 2005; 20: 109-118Abstract Full Text Full Text PDF PubMed Scopus (71) Google Scholar, 10Meissner T. Wendel U. Burgard P. Schaetzle S. Mayatepek E. Long-term follow-up of 114 patients with congenital hyperinsulinism.Eur J Endocrinol. 2003; 149: 43-51Crossref PubMed Scopus (157) Google ScholarTo address these deficiencies, the Pediatric Endocrine Society convened an expert panel of pediatric endocrinologists and neonatologists to develop guidelines for managing hypoglycemia in neonates, infants, and children, but excluding children with diabetes. The goals of these guidelines are to help physicians recognize persistent hypoglycemia disorders, guide their expeditious diagnosis and effective treatment, and prevent brain damage in at-risk babies.MethodsEvidence Retrieval and RatingThe committee searched for existing evidence synthesis reports, systematic reviews, and meta-analyses. The committee also evaluated guidelines published by the Endocrine Society, American Academy of Pediatrics, Canadian Pediatric Society, and others, and reviewed their bibliographies.4Canadian Paediatric SocietyScreening guidelines for newborns at risk for low blood glucose.Paediatr Child Health. 2004;
Overview
AI snapshot
Written from the paper’s full text.
TL;DR
This Pediatric Endocrine Society guideline provides expert recommendations for identifying and managing persistent hypoglycemia in neonates, infants, and children, excluding children with diabetes. It emphasizes distinguishing transitional neonatal hypoglycemia from persistent disorders, confirming low plasma glucose with laboratory assays, and using age- and diagnosis-specific treatment targets.
Key findings
- For children able to communicate symptoms, evaluate/manage only when Whipple’s triad is documented (GRADE 1++++); for infants/young children unable to communicate reliably, evaluate/manage when laboratory-confirmed plasma glucose is <60 mg/dL (3.3 mmol/L) (GRADE 2+++0).
- For high-risk neonates suspected of a persistent hypoglycemia disorder, delay diagnostic evaluation until ≥48 hours of age to allow transitional glucose regulation to pass (GRADE 2++00).
- Treatment targets: maintain plasma glucose >70 mg/dL (3.9 mmol/L) in neonates with suspected congenital hypoglycemia disorder and older infants/children with confirmed disorder (GRADE 1++00); for high-risk neonates without suspected congenital disorder, target >50 mg/dL (>2.8 mmol/L) if <48 hours and >60 mg/dL (>3.3 mmol/L) if >48 hours (GRADE 2+000).
- During fasting tests, plasma glucose of 50 mg/dL (2.8 mmol/L) is sufficiently low for diagnosis; in suspected hyperinsulinism, a glucagon-induced glycemic rise >30 mg/dL (>1.7 mmol/L) is nearly pathognomonic, and inappropriately low BOHB (<1.5 mmol/L [<15 mg/dL]) and FFA (<1.0–1.5 mmol/L [<28–42 mg/dL]) support the diagnosis.
Methods
- An expert panel of pediatric endocrinologists and neonatologists convened by the Pediatric Endocrine Society developed guidelines for neonates, infants, and children, excluding children with diabetes.
- The committee searched for existing evidence synthesis reports, systematic reviews, and meta-analyses; evaluated guidelines from the Endocrine Society, American Academy of Pediatrics, Canadian Pediatric Society, and others; reviewed bibliographies; and identified additional individual studies.
- Recommendations were graded using the GRADE framework, with strong recommendations stated as “we recommend” (GRADE 1) and weak recommendations as “we suggest” (GRADE 2); a consensus process was used for technical suggestions where evidence was scarce.
Limitations
- The paper states that evidence in this area is scarce and that the committee used a consensus process for some technical suggestions.
- The paper states there is an absence of evidence on the short-term or long-term consequences of different treatment targets, so the committee focused on physiology, etiology, mechanism, and risk–benefit balance.
- The text notes controversy over whether the newborn brain has greater or lesser susceptibility to hypoglycemic injury; evident from the text, several recommendations rely on expert consensus and extrapolation from adult/older-child physiology rather than direct pediatric outcome trials.
Model-written summary. Check it against the paper before relying on it.
Integrity signals
Registry
Cites
Statistics
Figures
Verification
Claims the paper makes
52 Not checked yet · 4 Own interpretation · 1 Own method
None of the sources cited for this claim have been checked yet.
In the paper
“During the first 24–48 hours of life, as normal neonates transition from intrauterine to extrauterine life, their plasma glucose (PG) concentrations are typically lower than later in life.1–3”
What the sources say
- Not checked yetcites [1] Cornblath, 1965, Blood glucose in the neonate and its clinical significance, N Engl J Med source
- Not checked yetcites [2] Srinivasan, 1986, Plasma glucose values in normal neonates: a new look, J Pediatr source
- Not checked yetcites [3] Stanley, 2015, Re-evaluating “transitional neonatal hypoglycemia”: mechanism and implications for management, J Pediatr source
plaincorrelational- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
None of the sources cited for this claim have been checked yet.
In the paper
“Published guidelines for screening at-risk newborns and managing low PG concentrations in neonates focus on the immediate neonatal period, but do not address the diagnosis and management of disorders causing recurrent and prolonged hypoglycemia.4–6”
What the sources say
- Not checked yetcites [4] 2004, Screening guidelines for newborns at risk for low blood glucose, Paediatr Child Health source
- Not checked yetcites [5] Adamkin, 2011, Postnatal glucose homeostasis in late-preterm and term infants, Pediatrics source
- Not checked yetcites [6] Wight, 2006, ABM clinical protocol 1: guidelines for glucose monitoring and treatment of hypoglycemia in breastfed neonates, Breastfeed Med source
plain- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
In the paper
“Thus, exposure to recurrent hypoglycemia can shift the usual glucose threshold for recognition of neurogenic symptoms of 55 mg/dL (3.0 mmol/L) to a lower level.”
§ Recommendations from the Pediatric Endocrine Society for Evaluation and Management of Persistent Hypoglycemia in Neonates, Infants, and Children > Which Neonates, Infants, and Children to Evaluate for Hypoglycemia > Altered Hypoglycemia Awareness
What the sources say
- Not checked yetcites [18] Cryer, 2004, Diverse causes of hypoglycemia-associated autonomic failure in diabetes, N Engl J Med source
plaindirect- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
In the paper
“Because of their disproportionately larger brain size relative to body mass, infants and young children have a 2- to 3-fold higher glucose utilization rate (4–6 mg/kg/min) per kilogram of body weight compared with adults.13”
§ Recommendations from the Pediatric Endocrine Society for Evaluation and Management of Persistent Hypoglycemia in Neonates, Infants, and Children > Which Neonates, Infants, and Children to Evaluate for Hypoglycemia > Glucose Utilization
What the sources say
- Not checked yetcites [13] Bier, 1977, Measurement of “true” glucose production rates in infancy and childhood with 6,6-dideuteroglucose, Diabetes source
plaindirect- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
None of the sources cited for this claim have been checked yet.
In the paper
“Third, the first few months of life are the most vulnerable period for developmental disability, which occurs in ~25%–50% of children with congenital hyperinsulinism.”
What the sources say
- Not checked yetcites [8] Menni, 2001, Neurologic outcomes of 90 neonates and infants with persistent hyperinsulinemic hypoglycemia, Pediatrics source
- Not checked yetcites [9] Steinkrauss, 2005, Effects of hypoglycemia on developmental outcome in children with congenital hyperinsulinism, J Pediatr Nurs source
- Not checked yetcites [10] Meissner, 2003, Long-term follow-up of 114 patients with congenital hyperinsulinism, Eur J Endocrinol source
plain- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
In the paper
“Second, it may be difficult to identify and distinguish newborn infants with a persistent hypoglycemia disorder from those with transitional low glucose levels in the initial 48 hours of life, as detailed in the separate document on transitional neonatal hypoglycemia prepared by our committee.3”
What the sources say
- Not checked yetcites [3] Stanley, 2015, Re-evaluating “transitional neonatal hypoglycemia”: mechanism and implications for management, J Pediatr source
hedged- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
In the paper
“The changes in fuel metabolism during fasting in normal neonates after 2–3 days of age and in infants and children do not differ substantially from those in adults, except that PG concentrations decrease more rapidly and hyperketonemia develops sooner, because of the energy needs of their relatively larger brains.17”
§ Recommendations from the Pediatric Endocrine Society for Evaluation and Management of Persistent Hypoglycemia in Neonates, Infants, and Children > Which Neonates, Infants, and Children to Evaluate for Hypoglycemia > Metabolic Defenses against Hypoglycemia
What the sources say
- Not checked yetcites [17] Chaussain, 1977, Glycemic response to 24-hour fast in normal children, III: influence of age, J Pediatr source
plain- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: unclear — It is unclear whether the paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
In the paper
“Brain glucose utilization becomes limited at a PG concentration of approximately 55–65 mg/dL (3.0–3.6 mmol/L).12”
§ Recommendations from the Pediatric Endocrine Society for Evaluation and Management of Persistent Hypoglycemia in Neonates, Infants, and Children > Which Neonates, Infants, and Children to Evaluate for Hypoglycemia > Symptoms of Hypoglycemia
What the sources say
- Not checked yetcites [12] Cryer, 2013
plaindirect- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: unclear — It is unclear whether the paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
None of the sources cited for this claim have been checked yet.
In the paper
“Early recognition and treatment are crucial for preventing these sequelae.8–10”
What the sources say
- Not checked yetcites [8] Menni, 2001, Neurologic outcomes of 90 neonates and infants with persistent hyperinsulinemic hypoglycemia, Pediatrics source
- Not checked yetcites [9] Steinkrauss, 2005, Effects of hypoglycemia on developmental outcome in children with congenital hyperinsulinism, J Pediatr Nurs source
- Not checked yetcites [10] Meissner, 2003, Long-term follow-up of 114 patients with congenital hyperinsulinism, Eur J Endocrinol source
plaindirect- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
In the paper
“Moreover, the evaluation and management of pediatric hypoglycemia differ in several respects from that in adults, for whom guidelines were recently published.7”
What the sources say
- Not checked yetcites [7] Cryer, 2009, Evaluation and management of adult hypoglycemic disorders: an Endocrine Society clinical practice guideline, J Clin Endocrinol Metab source
plain- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
- It may state two separate claims as one. 15
- Probably not a substantial claim. 6
In the paper
“This leads to reduced or absent awareness of hypoglycemia and impairs hepatic glucose release, perpetuating hypoglycemia.”
§ Recommendations from the Pediatric Endocrine Society for Evaluation and Management of Persistent Hypoglycemia in Neonates, Infants, and Children > Which Neonates, Infants, and Children to Evaluate for Hypoglycemia > Altered Hypoglycemia Awareness
What the sources say
- Not checked yetcites [18] Cryer, 2004, Diverse causes of hypoglycemia-associated autonomic failure in diabetes, N Engl J Med source
plaindirect- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
In the paper
“HAAF can persist for >24 hours after a single episode of hypoglycemia or even longer after repeated episodes of hypoglycemia.”
§ Recommendations from the Pediatric Endocrine Society for Evaluation and Management of Persistent Hypoglycemia in Neonates, Infants, and Children > Which Neonates, Infants, and Children to Evaluate for Hypoglycemia > Altered Hypoglycemia Awareness
What the sources say
- Not checked yetcites [18] Cryer, 2004, Diverse causes of hypoglycemia-associated autonomic failure in diabetes, N Engl J Med source
plaindirect- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: unclear — It is unclear whether the paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
In the paper
“Previous exposure to an episode of hypoglycemia can blunt, and repeated episodes can eliminate, neurogenic responses to subsequent hypoglycemic episodes.18”
§ Recommendations from the Pediatric Endocrine Society for Evaluation and Management of Persistent Hypoglycemia in Neonates, Infants, and Children > Which Neonates, Infants, and Children to Evaluate for Hypoglycemia > Altered Hypoglycemia Awareness
What the sources say
- Not checked yetcites [18] Cryer, 2004, Diverse causes of hypoglycemia-associated autonomic failure in diabetes, N Engl J Med source
plaindirect- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
A conclusion the paper draws from its own results — it cites no other source for it, so there is none to check. The quote shows it is in the paper.
In the paper
“However, in hypoketotic conditions, such as hyperinsulinism or fatty acid oxidation disorders, ketones and lactate are not available in sufficiently high concentrations to substitute for glucose, and the risk of brain energy failure is greater.”
§ Recommendations from the Pediatric Endocrine Society for Evaluation and Management of Persistent Hypoglycemia in Neonates, Infants, and Children > Which Neonates, Infants, and Children to Evaluate for Hypoglycemia > Glucose Utilization
plaindirect- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
A conclusion the paper draws from its own results — it cites no other source for it, so there is none to check. The quote shows it is in the paper.
In the paper
“Hypoglycemia cannot be defined as a specific PG concentration, because: (1) thresholds for specific brain responses to hypoglycemia occur across a range of PG concentrations, and these thresholds can be altered by the presence of alternative fuels, such as ketones, and by recent antecedent hypoglycemia;”
§ Recommendations from the Pediatric Endocrine Society for Evaluation and Management of Persistent Hypoglycemia in Neonates, Infants, and Children > Which Neonates, Infants, and Children to Evaluate for Hypoglycemia > Clinical Definition of Hypoglycemia
plain- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
Probably not a substantial claim.
In the paper
“Point-of-care meters provide a convenient screening method for detecting hypoglycemia, but their accuracy is limited to approximately ±10–15 mg/dL (0.6–0.8 mmol/L) in the range of hypoglycemia.”
§ Recommendations from the Pediatric Endocrine Society for Evaluation and Management of Persistent Hypoglycemia in Neonates, Infants, and Children > Which Neonates, Infants, and Children to Evaluate for Hypoglycemia > Potential Artifacts in Measurements of PG Concentration
What the sources say
- Not checked yetcites [12] Cryer, 2013
plain- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
In the paper
“Although previous exposure to hypoglycemia lowers the glucose threshold for neurogenic responses, the threshold for neuroglycopenic symptoms is not altered acutely; whether adaptation occurs with repeated exposure to hypoglycemia is unknown.”
§ Recommendations from the Pediatric Endocrine Society for Evaluation and Management of Persistent Hypoglycemia in Neonates, Infants, and Children > Which Neonates, Infants, and Children to Evaluate for Hypoglycemia > Altered Hypoglycemia Awareness
What the sources say
- Not checked yetcites [18] Cryer, 2004, Diverse causes of hypoglycemia-associated autonomic failure in diabetes, N Engl J Med source
plaindirect- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: unclear — It is unclear whether the paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
In the paper
“A further reduction of PG to 65–70 mg/dL (3.6–3.9 mmol/L) elicits glucagon secretion and activation of the sympathoadrenal system (reflected by increased epinephrine concentration), which increases glucose release from liver glycogen stores to raise the PG concentration.”
§ Recommendations from the Pediatric Endocrine Society for Evaluation and Management of Persistent Hypoglycemia in Neonates, Infants, and Children > Which Neonates, Infants, and Children to Evaluate for Hypoglycemia > Neuroendocrine Defenses against Hypoglycemia
What the sources say
- Not checked yetcites [15] Cryer, 2007, Hypoglycemia, functional brain failure, and brain death, J Clin Invest source
plaindirect- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: unclear — It is unclear whether the paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
None of the sources cited for this claim have been checked yet.
In the paper
“These include not only the rare infants with genetic hypoglycemia disorders, such as congenital hyperinsulinism or hypopituitarism,31 but also those with relatively more common prolonged neonatal hyperinsulinism (also referred to as perinatal stress hyperinsulinism) associated with birth asphyxia, intrauterine growth restriction, or toxemia.27,28,30”
§ Recommendations from the Pediatric Endocrine Society for Evaluation and Management of Persistent Hypoglycemia in Neonates, Infants, and Children > Which Neonates, Infants, and Children to Evaluate for Hypoglycemia > Neonates Aged >48 Hours Who May Be at Risk for Persistent Hypoglycemia Disorders
What the sources say
- Not checked yetcites [31] Mohamed, 2012, Hyperinsulinaemic hypoglycaemia: genetic mechanisms, diagnosis and management, J Clin Res Pediatr Endocrinol source
- Not checked yetcites [27] Collins, 1984, Hyperinsulinsim in asphyxiated and small-for-dates infants with hypoglycaemia, Lancet source
- Not checked yetcites [28] Collins, 1990, Hyperinsulinaemic hypoglycaemia in small for dates babies, Arch Dis Child source
- Not checked yetcites [30] Hoe, 2006, Clinical features and insulin regulation in infants with a syndrome of prolonged neonatal hyperinsulinism, J Pediatr source
plaincorrelational- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
In the paper
“The mean PG concentration in normal newborns during the first hours after birth (~55–60 mg/dL [~3 mmol/L]) is similar to the threshold for neurogenic symptoms of hypoglycemia in older children and adults, but above the threshold for neuroglycopenic symptoms.”
§ Recommendations from the Pediatric Endocrine Society for Evaluation and Management of Persistent Hypoglycemia in Neonates, Infants, and Children > Management of Neonates, Infants, and Children with a Persistent Hypoglycemia Disorder > High-Risk Neonates without a Suspected Congenital Hypoglycemia Disorder
What the sources say
- Not checked yetcites [1] Cornblath, 1965, Blood glucose in the neonate and its clinical significance, N Engl J Med source
plain- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
A conclusion the paper draws from its own results — it cites no other source for it, so there is none to check. The quote shows it is in the paper.
In the paper
“Expeditiously identifying the specific cause of hypoglycemia, as outlined above, will enable prompt institution of appropriate treatment and decrease the risk of permanent brain injury from persistent and recurrent severe hypoglycemia.”
§ Recommendations from the Pediatric Endocrine Society for Evaluation and Management of Persistent Hypoglycemia in Neonates, Infants, and Children > Workup/Investigation of Persistent Hypoglycemia > Values
plaindirect- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
Probably not a substantial claim. It may state two separate claims as one.
None of the sources cited for this claim have been checked yet.
In the paper
“After the first 48 hours of life, PG concentration and the physiology of glucose homeostasis do not differ to any great extent with age.”
§ Recommendations from the Pediatric Endocrine Society for Evaluation and Management of Persistent Hypoglycemia in Neonates, Infants, and Children > Which Neonates, Infants, and Children to Evaluate for Hypoglycemia > Normal PG Concentrations in Neonates Aged >48 Hours, Infants, and Children
What the sources say
- Not checked yetcites [17] Chaussain, 1977, Glycemic response to 24-hour fast in normal children, III: influence of age, J Pediatr source
- Not checked yetcites [20] Bonnefont, 1990, The fasting test in paediatrics: application to the diagnosis of pathological hypo- and hyperketotic states, Eur J Pediatr source
- Not checked yetcites [21] van Veen, 2011, Metabolic profiles in children during fasting, Pediatrics source
plain- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
In the paper
“Therefore, treatment targets are generally aimed at avoiding activation of neuroendocrine responses and HAAF by maintaining PG concentration within the normal range of 70–100 mg/dL (3.9–5.6 mmol/L).7”
§ Recommendations from the Pediatric Endocrine Society for Evaluation and Management of Persistent Hypoglycemia in Neonates, Infants, and Children > Management of Neonates, Infants, and Children with a Persistent Hypoglycemia Disorder > Neonates, Infants, and Children with Hypoglycemia Disorders
What the sources say
- Not checked yetcites [7] Cryer, 2009, Evaluation and management of adult hypoglycemic disorders: an Endocrine Society clinical practice guideline, J Clin Endocrinol Metab source
plaindirect- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
Probably not a substantial claim.
None of the sources cited for this claim have been checked yet.
In the paper
“Of concern, as noted previously,3 plasma ketone levels are suppressed during hypoglycemia in high-risk neonates, making them particularly vulnerable to hypoglycemia-induced brain damage, and there is no assurance the plasma lactate level will be sufficiently elevated to compensate for low glucose.27,28,30,39”
§ Recommendations from the Pediatric Endocrine Society for Evaluation and Management of Persistent Hypoglycemia in Neonates, Infants, and Children > Management of Neonates, Infants, and Children with a Persistent Hypoglycemia Disorder > High-Risk Neonates without a Suspected Congenital Hypoglycemia Disorder
What the sources say
- Not checked yetcites [3] Stanley, 2015, Re-evaluating “transitional neonatal hypoglycemia”: mechanism and implications for management, J Pediatr source
- Not checked yetcites [27] Collins, 1984, Hyperinsulinsim in asphyxiated and small-for-dates infants with hypoglycaemia, Lancet source
- Not checked yetcites [28] Collins, 1990, Hyperinsulinaemic hypoglycaemia in small for dates babies, Arch Dis Child source
- Not checked yetcites [30] Hoe, 2006, Clinical features and insulin regulation in infants with a syndrome of prolonged neonatal hyperinsulinism, J Pediatr source
- Not checked yetcites [39] Harris, 2011, Cot-side electroencephalography monitoring is not clinically useful in the detection of mild neonatal hypoglycemia, J Pediatr source
plaindirect- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
In the paper
“As discussed previously,3 the committee’s review of available data on transitional neonatal hypoglycemia in normal newborns (ie, hypoketonemic hypoglycemia with inappropriately large glycemic responses to glucagon or epinephrine stimulation) suggests that it is a mild and transient form of hyperinsulinism in which the mean PG threshold for suppression of insulin secretion is ~55–65 mg/dL (3.0–3.6”
§ Recommendations from the Pediatric Endocrine Society for Evaluation and Management of Persistent Hypoglycemia in Neonates, Infants, and Children > Which Neonates, Infants, and Children to Evaluate for Hypoglycemia > PG Concentrations in Neonates Aged <48 Hours
What the sources say
- Not checked yetcites [3] Stanley, 2015, Re-evaluating “transitional neonatal hypoglycemia”: mechanism and implications for management, J Pediatr source
hedgeddirect- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
None of the sources cited for this claim have been checked yet.
In the paper
“Some neonates can be identified by various clinical features as being at high risk for severe hypoglycemia during the first 48 hours after delivery,16,26 and a subset of those neonates are also at increased risk for persistent hypoglycemia beyond 48 hours of life (Table).27–30”
§ Recommendations from the Pediatric Endocrine Society for Evaluation and Management of Persistent Hypoglycemia in Neonates, Infants, and Children > Which Neonates, Infants, and Children to Evaluate for Hypoglycemia > Neonates Aged >48 Hours Who May Be at Risk for Persistent Hypoglycemia Disorders
What the sources say
- Not checked yetcites [16] Koivisto, 1972, Neonatal symptomatic and asymptomatic hypoglycaemia: a follow-up study of 151 children, Dev Med Child Neurol source
- Not checked yetcites [26] Vannucci, 2001, Hypoglycemic brain injury, Semin Neonatol source
- Not checked yetcites [27] Collins, 1984, Hyperinsulinsim in asphyxiated and small-for-dates infants with hypoglycaemia, Lancet source
- Not checked yetcites [28] Collins, 1990, Hyperinsulinaemic hypoglycaemia in small for dates babies, Arch Dis Child source
- Not checked yetcites [29] Hume, 1999, Failure to detect preterm infants at risk of hypoglycemia before discharge, J Pediatr source
- Not checked yetcites [30] Hoe, 2006, Clinical features and insulin regulation in infants with a syndrome of prolonged neonatal hyperinsulinism, J Pediatr source
plaincorrelational- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
A conclusion the paper draws from its own results — it cites no other source for it, so there is none to check. The quote shows it is in the paper.
In the paper
“Failure to investigate a neonate, infant, or child with suspected hypoglycemia increases the risk of delaying a definitive diagnosis and instituting effective treatment.”
§ Recommendations from the Pediatric Endocrine Society for Evaluation and Management of Persistent Hypoglycemia in Neonates, Infants, and Children > Workup/Investigation of Persistent Hypoglycemia > Values
plaindirect- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
Probably not a substantial claim.
None of the sources cited for this claim have been checked yet.
In the paper
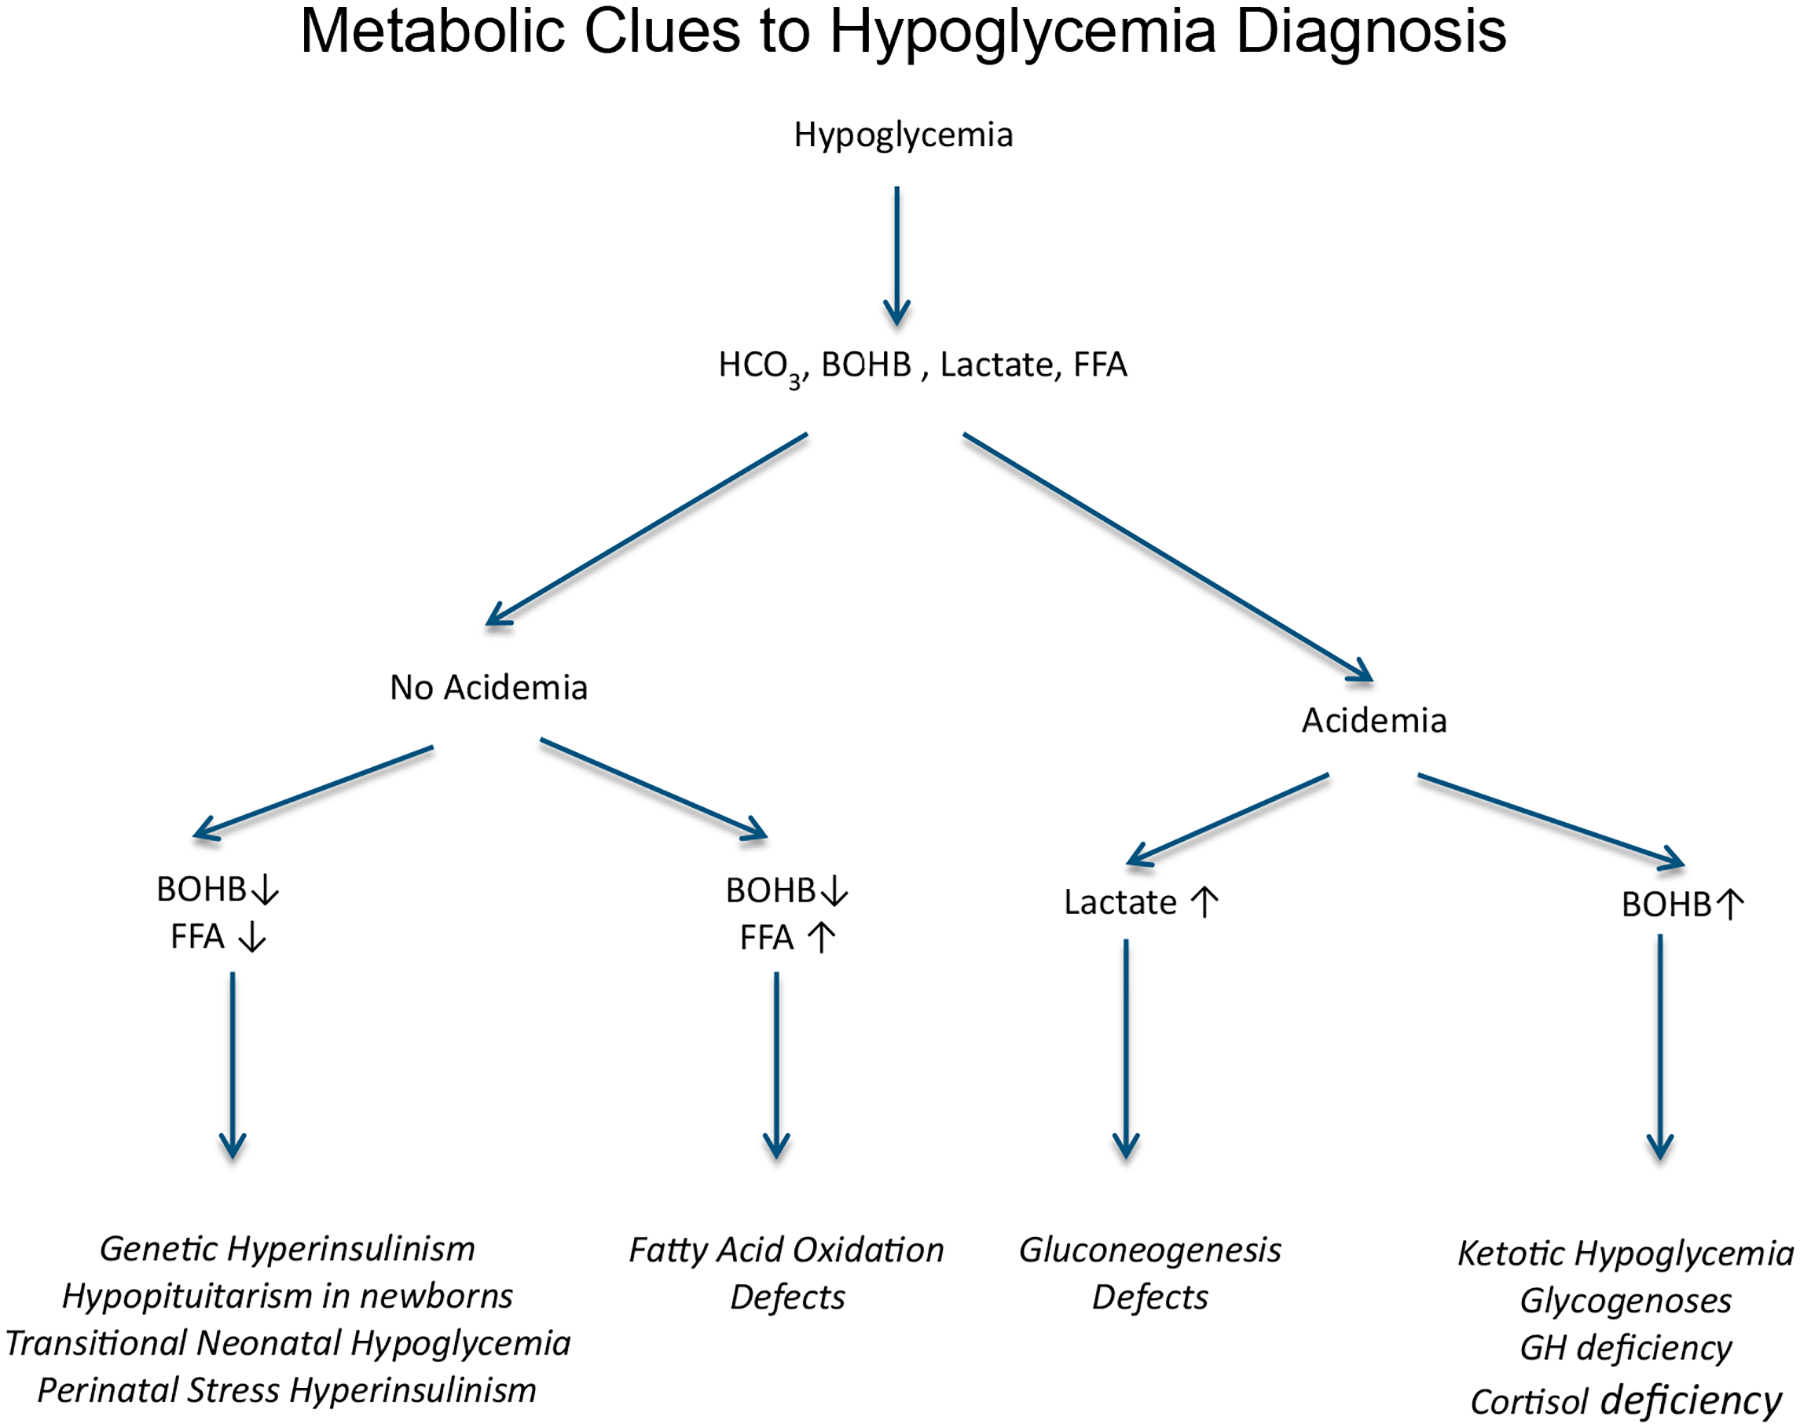
“Because plasma insulin concentration is sometimes not above the lower limit of detection,34 it is important to include the following tests when assessing the possibility of hypoglycemia due to hyperinsulinism: plasma BOHB and FFA (both inappropriately low; BOHB <1.5 mmol/L [<15 mg/dL] and FFA <1.0–1.5 mmol/L [<28–42 mg/dL]), and an increased glycemic response to glucagon.”
§ Recommendations from the Pediatric Endocrine Society for Evaluation and Management of Persistent Hypoglycemia in Neonates, Infants, and Children > Workup/Investigation of Persistent Hypoglycemia
What the sources say
- Not checked yetcites [33] Finegold, 1980, Glycemic response to glucagon during fasting hypoglycemia: an aid in the diagnosis of hyperinsulinism, J Pediatr source
- Not checked yetcites [34] De Leon, 2013, Determination of insulin for the diagnosis of hyperinsulinemic hypoglycemia, Best Pract Res Clin Endocrinol Metab source
plaincorrelational- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
What the paper did — it cites no source for this, so there is none to check. The quote shows it is in the paper.
In the paper
“To provide a practical guide and in the light of scarce evidence in this area, the committee used a consensus process to make the following technical suggestions:”
§ Recommendations from the Pediatric Endocrine Society for Evaluation and Management of Persistent Hypoglycemia in Neonates, Infants, and Children > Which Neonates, Infants, and Children to Evaluate for Hypoglycemia > Neonates Aged >48 Hours Who May Be at Risk for Persistent Hypoglycemia Disorders
plain- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
Probably not a substantial claim.
In the paper
“The committee adopted the framework of the Grading of Recommendations Assessment, Development, and Evaluation (GRADE) Working Group,11 in which guideline developers rate their confidence in the evidence as very low (+000), low (++00), moderate (+++0), or high (++++).”
§ Recommendations from the Pediatric Endocrine Society for Evaluation and Management of Persistent Hypoglycemia in Neonates, Infants, and Children > Methods > Evidence Retrieval and Rating
What the sources say
- Not checked yetcites [11] Atkins, 2004, Grading quality of evidence and strength of recommendations, BMJ source
plain- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
Probably not a substantial claim.
The paper relies on this without support.
Persistent hypoglycemia most often results from a congenital or genetic defect in regulating insulin secretion, deficiency of cortisol and/or growth hormone, or defects in the metabolism of glucose, glycogen, and fatty acids.
“First, persistent hypoglycemia most often results from a congenital or genetic defect in regulating secretion of insulin, deficiency of cortisol and/or growth hormone, or defects in the metabolism of glucose, glycogen, and fatty acids.”
The paper relies on this without support.
Hypoglycemia disorders in older infants and children are uncommon.
“Hypoglycemia disorders in older infants and children are uncommon.”
The paper relies on this without support.
Adrenal insufficiency, congenital or acquired, may manifest with hypoglycemia.
“Adrenal insufficiency, congenital or acquired, may manifest with hypoglycemia.”
The paper relies on this without support.
High plasma insulin level but low C-peptide level during hypoglycemia suggest exogenous insulin administration.
“High plasma insulin level but low C-peptide level during hypoglycemia suggest exogenous insulin administration.”
The paper relies on this without support.
The drugs most commonly associated with hypoglycemia include insulin, sulphonylureas, alcohol, beta-blockers, and salicylates.
“The drugs most commonly associated with hypoglycemia include insulin, sulphonylureas, alcohol, beta-blockers, and salicylates.”
The paper relies on this without support.
Not all commercially available insulin assays measure the insulin analogues; thus the finding of low insulin and C-peptide levels at time of hypoglycemia might not rule out surreptitious insulin administration.
“Not all commercially available insulin assays measure the insulin analogues; thus, the finding of low insulin and C-peptide levels at time of hypoglycemia might not rule out surreptitious insulin administration.”
The paper relies on this without support.
A plasma glucose concentration of 50 mg/dL is sufficiently low to elicit the metabolic and neuroendocrine responses required for diagnosis.
“A PG concentration of 50 mg/dL (2.8 mmol/L) is sufficiently low to elicit the metabolic and neuroendocrine responses required for diagnosis.”
The paper relies on this without support.
With few exceptions, blood tests performed while glucose concentrations are normal are not informative.
“With few exceptions, blood tests performed while glucose concentrations are normal are not informative.”
The paper relies on this without support.
Laboratory reference ranges for some tests (eg, insulin, BOHB) may be inappropriate for interpreting values obtained during childhood hypoglycemia.
“Laboratory reference ranges for some of these tests (eg, insulin, BOHB) may be inappropriate for interpreting values obtained during childhood hypoglycemia.”
The paper relies on this without support.
In cases of hyperinsulinism, glucagon can be expected to raise plasma glucose concentration to normal or above within 10–15 minutes and to maintain that concentration for at least 1 hour.
“In cases of hyperinsulinism, glucagon can be expected to raise PG concentration to normal or above within 10–15 minutes and to maintain that concentration for at least 1 hour.”
The paper relies on this without support.
Doses of glucagon 0.5–1.0 mg (independent of weight), given IV, intramuscularly, or subcutaneously, are usually effective; lower doses (0.03 mg/kg) may carry less risk of transient nausea and vomiting, but may be ineffective unless given IV.
“Doses of 0.5–1.0 mg (independent of weight), given IV, intramuscularly, or subcutaneously, are usually effective; lower doses (0.03 mg/kg) may carry less risk of transient nausea and vomiting, but may be ineffective unless given IV.”
The paper relies on this without support.
For disorders such as defects in glycogen metabolism and gluconeogenesis, maintenance of plasma glucose concentration in the normal range prevents metabolic acidosis and growth failure, and possibly the development of long-term complications.
“For disorders such as defects in glycogen metabolism and gluconeogenesis, maintenance of PG concentration in the normal range prevents metabolic acidosis and growth failure, and possibly the development of long-term complications.”
The paper relies on this without support.
There is no evidence that the concentration at which plasma glucose becomes limiting for brain function is different in neonates than in older children and adults.
“There is no evidence that the concentration at which PG becomes limiting for brain function is different in neonates than in older children and adults.”
Claims other papers make about this one
Each is checked against this paper’s own text: does it say what the citing paper says it does?
In the citing paper
“Prompt recognition and treatment of neonatal hypoglycemia is critical to decrease the risk of adverse neurologic outcomes.643”
From Clinical practice guidelines for the care of girls and women with Turner syndrome. (2024) · cites this paper as [643]
Citations
Cites
Grading quality of evidence and strength of recommendations
(2004) · BMJ · doi:10.1136/bmj.328.7454.1490 · Cited by 8,477 · cited 1×
“Randomized trials start as high, and observational studies start as low.(11)”
BackgroundCryer, P. E., Axelrod, L., Grossman, A. B., Heller, S. R., Montori, V. M., Seaquist, E. R., & Service, F. J. (2009) · The Journal of Clinical Endocrinology & Metabolism · doi:10.1210/jc.2008-1410 · Cited by 1,277 · cited 4×
“6 result in the development of HAAF, which increases the risk of subsequent hypoglycemia and attenuates its recognition.(7,36) Therefore, treatment targets are generally aimed at avoiding activation of neuroendocrine responses and HAAF by maintaining PG concentration within the normal range of 70-100 mg/dL (3.”
InfluentialPostnatal glucose homeostasis in late-preterm and term infants
Adamkin, D. H., & Committee on Fetus and Newborn (2011) · PEDIATRICS · doi:10.1542/peds.2010-3851 · Cited by 771
Measurement of “true” glucose production rates in infancy and childhood with 6,6-dideuteroglucose
Bier, D. M., Leake, R. D., Haymond, M. W., Arnold, K. J., Gruenke, L. D., Sperling, M. A., & Kipnis, D. M. (1977) · Diabetes · doi:10.2337/diab.26.11.1016 · Cited by 444 · cited 1×
“Because of their disproportionately larger brain size relative to body mass, infants and young children have a 2- to 3-fold higher glucose utilization rate (4-6 mg/kg/min) per kilogram of body weight compared with adults.(13) Although the brain has an obligate requirement for glucose, it also can use plasma ketones an…”
Self-citationDiverse causes of hypoglycemia-associated autonomic failure in diabetes.
Cryer, P. E. (2004) · New England Journal of Medicine · doi:10.1056/nejmra031354 · Cited by 411 · cited 3×
“This combination of events has been termed hypoglycemiaassociated autonomic failure (HAAF).(18) HAAF can persist for >24 hours after a single episode of hypoglycemia or even longer after repeated episodes of hypoglycemia.”
BackgroundInfluentialHypoglycemia, functional brain failure, and brain death.
Cryer, P. E. (2007) · Journal of Clinical Investigation · doi:10.1172/jci31669 · Cited by 363 · cited 1×
“9 mmol/L).(15) A further reduction of PG to 65-70 mg/dL (3.”
BackgroundNeurologic outcomes of 90 neonates and infants with persistent hyperinsulinemic hypoglycemia
Menni, F., de Lonlay, P., Sevin, C., Touati, G., Peigné, C., Barbier, V., Nihoul-Fékété, C., Saudubray, J.-M., & Robert, J.-J. (2001) · PEDIATRICS · doi:10.1542/peds.107.3.476 · Cited by 347
Plasma glucose values in normal neonates: a new look
Srinivasan, G., Pildes, R. S., Cattamanchi, G., Voora, S., & Lilien, L. D. (1986) · The Journal of Pediatrics · doi:10.1016/s0022-3476(86)80588-1 · Cited by 329 · cited 1×
“As the glucose stimulated-insulin secretion mechanism matures, mean PG concentration in normal newborns increases and by 72 hours of age is similar to those in older infants and children 1,2 ; therefore, the standards for normal neonates must never be extrapolated beyond 2–3 days after birth.”
Hay, W. W., Raju, T. N. K., Higgins, R. D., Kalhan, S. C., & Devaskar, S. U. (2009) · The Journal of Pediatrics · doi:10.1016/j.jpeds.2009.06.044 · Cited by 309
Re-evaluating “transitional neonatal hypoglycemia”: mechanism and implications for management
Stanley, C. A., Rozance, P. J., Thornton, P. S., De Leon, D. D., Harris, D., Haymond, M. W., Hussain, K., Levitsky, L. L., Murad, M. H., Simmons, R. A., et al. (2015) · The Journal of Pediatrics · doi:10.1016/j.jpeds.2015.02.045 · Cited by 245 · cited 1×
“Second, it may be difficult to identify and distinguish newborn infants with a persistent hypoglycemia disorder from those with transitional low glucose levels in the initial 48 hours of life, as detailed in the separate document on transitional neonatal hypoglycemia prepared by our committee.(3) Third, the first few…”
Self-citation
Cited by
Sorted by citations
Brioude, F., Kalish, J. M., Mussa, A., et al. (2018) · Nature Reviews Endocrinology · doi:10.1038/nrendo.2017.166 · Cited by 624
Self-citationNeonatal Glycaemia and Neurodevelopmental Outcomes: A Systematic Review and Meta-Analysis
Shah, R. K., Harding, J. E., Brown, J., & McKinlay, C. J. D. (2018) · Neonatology · doi:10.1159/000492859 · Cited by 244
Guideline panels should seldom make good practice statements: guidance from the GRADE Working Group
Guyatt, G. H., Alonso‐Coello, P., Schünemann, H. J., Djulbegović, B., Nothacker, M., Lange, S., Murad, M. H., & Akl, E. A. (2016) · Journal of Clinical Epidemiology · doi:10.1016/j.jclinepi.2016.07.006 · Cited by 245
Self-citationPerspective on the Genetics and Diagnosis of Congenital Hyperinsulinism Disorders
Stanley, C. A. (2016) · The Journal of Clinical Endocrinology & Metabolism · doi:10.1210/jc.2015-3651 · Cited by 239
“of infants with congenital HI and other persistent hypoglycemia disorders during the first 2 days of life (86).”
BackgroundSelf-citationWhat is a normal blood glucose?
Güemes, M., Rahman, S. A., & Hussain, K. (2015) · Archives of Disease in Childhood · doi:10.1136/archdischild-2015-308336 · Cited by 247
“The same approach has been recommended for older children who are able to describe their symptoms [9].”
BackgroundSelf-citationClinical practice guidelines for the care of girls and women with Turner syndrome.
Gravholt, C. H., Andersen, N. H., Christin-Maitre, S., Davis, S. M., Duijnhouwer, A., Gawlik, A., Maciel-Guerra, A. T., Gutmark-Little, I., Fleischer, K., Hong, D., et al. (2024) · European Journal of Endocrinology · doi:10.1093/ejendo/lvae050 · Cited by 224
Intrauterine Growth Restriction
Kesavan, K., & Devaskar, S. U. (2019) · Pediatric Clinics of North America · doi:10.1016/j.pcl.2018.12.009 · Cited by 201
Franco, E. D., Saint‐Martin, C., Brusgaard, K., Johnson, A. E. K., Aguilar‐Bryan, L., Bowman, P., Arnoux, J., Larsen, A. R., Sanyoura, M., Greeley, S. A. W., et al. (2020) · Human Mutation · doi:10.1002/humu.23995 · Cited by 181
“In 2015, the Pediatric Endocrine Society published recommendations for the evaluation and management of persistent hypoglycemia in neonates, infants, and children (Thornton et al., 2015).”
BackgroundThompson-Branch, A., & Havranek, T. (2017) · Pediatrics in Review · doi:10.1542/pir.2016-0063 · Cited by 197
Oral Dextrose Gel Reduces the Need for Intravenous Dextrose Therapy in Neonatal Hypoglycemia
Rawat, M., Chandrasekharan, P. K., Turkovich, S. J., et al. (2016) · Biomedicine Hub · doi:10.1159/000448511 · Cited by 175
Adamkin, D. H. (2016) · Seminars in Fetal and Neonatal Medicine · doi:10.1016/j.siny.2016.08.007 · Cited by 165
Therapies and outcomes of congenital hyperinsulinism‐induced hypoglycaemia
Banerjee, I., Salomon‐Estebanez, M., Shah, P., Nicholson, J., Cosgrove, K. E., & Dunne, M. J. (2018) · Diabetic Medicine · doi:10.1111/dme.13823 · Cited by 142
Hypoglycemia in the preterm neonate: etiopathogenesis, diagnosis, management and long-term outcomes
Sharma, A., Davis, A. O., & Shekhawat, P. (2017) · Translational Pediatrics · doi:10.21037/tp.2017.10.06 · Cited by 139
“A lower dextrose infusion rate of 3–5 mg/kg/min may be used for infants born to mothers with diabetes to provide minimal stimulation to their pancreas to secrete insulin (19).”
BackgroundMethodInfluentialLord, K., Radcliffe, J., Gallagher, P. R., Adzick, N. S., Stanley, C. A., & León, D. D. D. (2015) · The Journal of Clinical Endocrinology & Metabolism · doi:10.1210/jc.2015-2539 · Cited by 138
“(95% [range, 65–98] vs 65% [1–98]).”
Self-citationCostello syndrome: Clinical phenotype, genotype, and management guidelines
Gripp, K. W., Morse, L. A., Axelrad, M. E., Chatfield, K. C., Chidekel, A. S., Dobyns, W. B., Doyle, D., Kerr, B. A., Lin, A. E., Schwartz, D. D., et al. (2019) · American Journal of Medical Genetics Part A · doi:10.1002/ajmg.a.61270 · Cited by 134
Harris, D. L., Weston, P. J., Gamble, G. D., & Harding, J. E. (2020) · The Journal of Pediatrics · doi:10.1016/j.jpeds.2020.02.079 · Cited by 126
Self-citationHyperinsulinaemic hypoglycaemia in children and adults
Shah, P., Rahman, S. A., Demirbilek, H., Güemes, M., & Hussain, K. (2016) · The Lancet Diabetes & Endocrinology · doi:10.1016/s2213-8587(16)30323-0 · Cited by 126
Self-citationInternational Guidelines for the Diagnosis and Management of Hyperinsulinism
León, D. D. D., Arnoux, J. B., Banerjee, I., Bergadá, I., Bhatti, T. R., Conwell, L. S., Fu, J., Flanagan, S. E., Gillis, D. J., Meißner, T., et al. (2023) · Hormone Research in Paediatrics · doi:10.1159/000531766 · Cited by 125
“…Pediatric Endocrine Society (PES) guidelines established a treatment goal of > 70 mg/dL (3.9 mmol/L) for the management of children with hypoglycemia disorders in order to prevent hypoglycemia unawareness [95] and to have a safe margin above the threshold of hypoglycemia that causes brain damage.”
BackgroundMethodInfluentialSelf-citationLower versus Traditional Treatment Threshold for Neonatal Hypoglycemia
van Kempen, A. A. M. W., Eskes, P. F., Nuytemans, D. H. G. M., van der Lee, J. H., Dijksman, L. M., van Veenendaal, N. R., van der Hulst, F. J. P. C. M., Moonen, R. M. J., Zimmermann, L. J. I., Verlaat, E. V., et al. (2020) · New England Journal of Medicine · doi:10.1056/nejmoa1905593 · Cited by 120
The screening and management of newborns at risk for low blood glucose
Narvey, M. R., & Marks, S. D. (2019) · Paediatrics & Child Health · doi:10.1093/pch/pxz134 · Cited by 121
Neonatal Encephalopathy: Beyond Hypoxic-Ischemic Encephalopathy
Russ, J. B., Simmons, R. L., & Glass, H. C. (2021) · NeoReviews · doi:10.1542/neo.22-3-e148 · Cited by 110
Self-citationWight, N. E., & Marinelli, K. A. (2014) · Breastfeeding Medicine · doi:10.1089/bfm.2014.9986 · Cited by 104
Congenital hyperinsulinism disorders: Genetic and clinical characteristics
Rosenfeld, E., Ganguly, A. A., & León, D. D. D. (2019) · American Journal of Medical Genetics Part C Seminars in Medical Genetics · doi:10.1002/ajmg.c.31737 · Cited by 95
Self-citationOral dextrose gel for the treatment of hypoglycaemia in newborn infants
Weston, P. J., Harris, D. L., BATTIN, M. R., Brown, J., Hegarty, J. E., & Harding, J. E. (2016) · Cochrane Database of Systematic Reviews · doi:10.1002/14651858.cd011027.pub2 · Cited by 98
Self-citationMussa, A., Candia, S. D., Russo, S., et al. (2015) · European Journal of Medical Genetics · doi:10.1016/j.ejmg.2015.11.008 · Cited by 92
Neonatal Hypoglycemia Following Diet-Controlled and Insulin-Treated Gestational Diabetes Mellitus
Voormolen, D. N., de Wit, L., van Rijn, B. B., DeVries, J. H., Heringa, M. P., Franx, A., Groenendaal, F., & Ruiter, M. L.-D. (2018) · Diabetes Care · doi:10.2337/dc18-0048 · Cited by 91
Neonatal Hypoglycemia and Brain Vulnerability
Angelis, L. C. D., Brigati, G., Polleri, G., Malova, M., Parodi, A., Minghetti, D., Rossi, A., Massirio, P., Traggiai, C., Maghnie, M., et al. (2021) · Frontiers in Endocrinology · doi:10.3389/fendo.2021.634305 · Cited by 91
“PES, 2015 (14) <50 mg/dl <60 mg/dl BAPM, 2017 (15) <45 mg/dl if symptomatic”
Güemes, M., Rahman, S. A., Kapoor, R. R., Flanagan, S. E., Houghton, J., Misra, S., Oliver, N. S., Dattani, M., & Shah, P. (2020) · Reviews in Endocrine and Metabolic Disorders · doi:10.1007/s11154-020-09548-7 · Cited by 91
Evidence-Based Updates on the First Week of Exclusive Breastfeeding Among Infants ≥35 Weeks
Feldman‐Winter, L., Kellams, A. L., Peter-Wohl, S., Taylor, J. S., Lee, K. G., Terrell, M. J., Noble, L., Maynor, A. R., Meek, J. Y., & Stuebe, A. M. (2020) · PEDIATRICS · doi:10.1542/peds.2018-3696 · Cited by 84
Clinical practice guidelines for congenital hyperinsulinism
Yorifuji, T., Horikawa, R., Hasegawa, T., Adachi, M., Soneda, S., Minagawa, M., Ida, S., Yonekura, T., Kinoshita, Y., Kanamori, Y., et al. (2017) · Clinical Pediatric Endocrinology · doi:10.1297/cpe.26.127 · Cited by 74
Pinchefsky, E. F., Hahn, C. D., Kamino, D., Chau, V., Brant, R., Moore, A. M., & Tam, E. (2019) · The Journal of Pediatrics · doi:10.1016/j.jpeds.2019.02.027 · Cited by 80
Limesand, S. W., & Rozance, P. J. (2017) · The Journal of Physiology · doi:10.1113/jp273324 · Cited by 74
Self-citationWackernagel, D., Gustafsson, A., Bonamy, A. E., Reims, A., Ahlsson, F., Elfving, M., Domellöf, M., & Pupp, I. H. (2019) · Acta Paediatrica · doi:10.1111/apa.14955 · Cited by 75
Wight, N. E., Wight, N. E., Stehel, E. K., Noble, L., Bartick, M., Calhoun, S., Kair, L. R., Lappin, S., Larson, I. A., LeFort, Y., et al. (2021) · Breastfeeding Medicine · doi:10.1089/bfm.2021.29178.new · Cited by 73
Adamkin, D. H. (2016) · Current Opinion in Pediatrics · doi:10.1097/mop.0000000000000319 · Cited by 68
Wakeling, M. N., Owens, N. D. L., Hopkinson, J. R., Johnson, M. B., Houghton, J., Dastamani, A., Flaxman, C. S., Wyatt, R. C., Hewat, T. I., Hopkins, J. J., et al. (2022) · Nature Genetics · doi:10.1038/s41588-022-01204-x · Cited by 64
Čechová, A., Altassan, R., Borgel, D., Bruneel, A., Correia, J., Girard, M., Harroche, A., Kieć‐Wilk, B., Mohnike, K. L., Pascreau, T., et al. (2020) · Journal of Inherited Metabolic Disease · doi:10.1002/jimd.12241 · Cited by 68
What Happens to Blood Glucose Concentrations After Oral Treatment for Neonatal Hypoglycemia?
Harris, D. L., Gamble, G. D., Weston, P. J., & Harding, J. E. (2017) · The Journal of Pediatrics · doi:10.1016/j.jpeds.2017.06.034 · Cited by 66
“It seems likely that the underlying pathophysiology in these infants may differ from that of transitional hypoglycemia, which may be most commonly due to relative hyperinsulinism.(33) In the “other” group, a fuel deficit seems a more likely problem than hyperinsulinism and this may be reflected in the greater response…”
BackgroundSelf-citationClinical Outcomes and Modes of Death in Timothy Syndrome
Dufendach, K., Timothy, K. W., Ackerman, M. J., Blevins, B., Pflaumer, A., Etheridge, S. P., Perry, J. C., Blom, N. A., Temple, J., Chowdhury, D., et al. (2017) · JACC. Clinical electrophysiology · doi:10.1016/j.jacep.2017.08.007 · Cited by 62
Bedsharing and Breastfeeding: The Academy of Breastfeeding Medicine Protocol #6, Revision 2019
Blair, P. S., Ball, H. L., McKenna, J. J., Feldman‐Winter, L., Marinelli, K. A., Bartick, M., Young, M. A., Noble, L., Calhoun, S., Elliott-Rudder, M., et al. (2020) · Breastfeeding Medicine · doi:10.1089/bfm.2019.29144.psb · Cited by 71
Maternal obesity and cesarean section delivery: additional risk factors for neonatal hypoglycemia?
Turner, D., Monthé‐Drèze, C., Cherkerzian, S., Gregory, K. E., & Sen, S. (2019) · Journal of Perinatology · doi:10.1038/s41372-019-0404-z · Cited by 64
“Given the higher risk of c-section among obese women (3), as an exploratory analysis, we further assessed the modification by maternal BMI on the relationship between mode of delivery and NH onset by evaluating the survival functions of four groups: (1) vaginal delivery and BMI < 30 (reference), (2) vaginal delivery a…”
BackgroundMethodInfluentialIncidence of hypoglycemia in newborn infants identified as at risk
Stark, J., Simma, B., & Blassnig-Ezeh, A. (2019) · The Journal of Maternal-Fetal & Neonatal Medicine · doi:10.1080/14767058.2019.1568985 · Cited by 59
“At birth plasma glucose levels immediately fall to the lowest values in the first hours of life and reach adult levels at two or three days of age [1,2].”
BackgroundClinical Aspects of Neonatal Hypoglycemia: A Mini Review
Edwards, T., & Harding, J. E. (2021) · Frontiers in Pediatrics · doi:10.3389/fped.2020.562251 · Cited by 58
“*Occurring after or persisting for ≥3 days (27).”
BackgroundCasertano, A., Rossi, A., Fecarotta, S., Rosanio, F. M., Moracas, C., Candia, F. D., Parenti, G., Franzese, A., & Mozzillo, E. (2021) · Frontiers in Endocrinology · doi:10.3389/fendo.2021.684011 · Cited by 61
“Several algorithms with various starting points and workflow have been proposed (5, 7, 8).”
BackgroundMethodBanerjee, I., Raskin, J., Arnoux, J., León, D. D. D., WEINZIMER, S. A., Hammer, M., Kendall, D. M., & THORNTON, P. S. (2022) · Orphanet Journal of Rare Diseases · doi:10.1186/s13023-022-02214-y · Cited by 62
Self-citationNew approaches to management of neonatal hypoglycemia
Rozance, P. J., & Hay, W. W. (2016) · Maternal Health Neonatology and Perinatology · doi:10.1186/s40748-016-0031-z · Cited by 61
“glucose concentrations, clinical signs of hypoglycemia, and documentation of resolution of the hypoglycemia [4, 8].”
BackgroundInfluentialSelf-citationCongenital Hypoglycemia Disorders: New Aspects of Etiology, Diagnosis, Treatment and Outcomes
León, D. D. D., & Stanley, C. A. (2016) · Pediatric Diabetes · doi:10.1111/pedi.12453 · Cited by 61
“infusion of exendin-(9-39) increased fasting glucose in adolescents and adults with KATP HI.”
BackgroundInfluentialSelf-citationManagement and Appropriate Use of Diazoxide in Infants and Children with Hyperinsulinism
Brar, P. C., Heksch, R. A., Cossen, K., León, D. D. D., Kamboj, M. K., Marks, S. D., Marshall, B. A., Miller, R., PAGE, L. C., Stanley, T. L., et al. (2020) · The Journal of Clinical Endocrinology & Metabolism · doi:10.1210/clinem/dgaa543 · Cited by 59
“…we suggest waiting to start diazoxide for 7 to 10 days in infants suspected to have PSHI, provided their glucose levels can safely be maintained > 70mg/dL with intravenous fluids in addition to feeds and as long as the glucose infusion rate required to do so is falling (GRADE 2+) (3).”
BackgroundSelf-citationLee, K. W., Ching, S. M., Hoo, F. K., Ramachandran, V., Chong, S. C., Tusimin, M., Nordin, N. M., Devaraj, N. K., Cheong, A. T., & Chia, Y. C. (2019) · Midwifery · doi:10.1016/j.midw.2019.102586 · Cited by 55
Approach to hypoglycemia in infants and children
Gandhi, K. K. (2017) · Translational Pediatrics · doi:10.21037/tp.2017.10.05 · Cited by 59
“Among these infants, it may be necessary to perform a supervised 6–8 hours safety fast to ensure normal glucose concentrations prior to going home from the nursery or neonatal intensive care unit (NICU) (11).”
BackgroundInfluentialSzymanowski, M., Salomon‐Estebanez, M., Padidela, R., Han, B., Mosinska, K., Stevens, A., Damaj, L., Bars, F. P., Lascouts, E., Reynaud, R., et al. (2016) · The Journal of Clinical Endocrinology & Metabolism · doi:10.1210/jc.2016-2711 · Cited by 56
Incidence and Risk Factors for Hypoglycemia During Fetal-to-Neonatal Transition in Premature Infants
Mitchell, N. A., Grimbly, C., Rosolowsky, E. T., O’Reilly, M., Yaskina, M., Cheung, P., & Schmölzer, G. M. (2020) · Frontiers in Pediatrics · doi:10.3389/fped.2020.00034 · Cited by 53
Formal Neurocognitive Testing in 60 Patients with Congenital Hyperinsulinism
Ludwig, A., Enke, S., Heindorf, J., Empting, S., Meißner, T., & Mohnike, K. L. (2017) · Hormone Research in Paediatrics · doi:10.1159/000481774 · Cited by 49
Neonatal Hypoglycemia: A Review
Alsaleem, M., Saadeh, L., & Kamat, D. (2019) · Clinical Pediatrics · doi:10.1177/0009922819875540 · Cited by 46
Harding, J. E., Alsweiler, J. M., Edwards, T., & McKinlay, C. J. D. (2024) · BMJ Medicine · doi:10.1136/bmjmed-2023-000544 · Cited by 51
Hyperinsulinism in the Neonate
Lord, K., & León, D. D. D. (2017) · Clinics in Perinatology · doi:10.1016/j.clp.2017.10.007 · Cited by 49
Self-citationvan der Steen, I., van Albada, M. E., Mohnike, K. L., Christesen, H. T., Empting, S., Salomon‐Estebanez, M., Rasmussen, A. G., Stuart, A. V., van der Linde, A. A. A., Banerjee, I., et al. (2017) · Hormone Research in Paediatrics · doi:10.1159/000485184 · Cited by 49
Williams, J. E., & Pugh, Y. (2018) · Critical Care Nursing Clinics of North America · doi:10.1016/j.cnc.2018.07.001 · Cited by 49
Oral dextrose gel for the treatment of hypoglycaemia in newborn infants
Edwards, T., Liu, G. X. H., BATTIN, M. R., Harris, D. L., Hegarty, J. E., Weston, P. J., & Harding, J. E. (2022) · Cochrane Database of Systematic Reviews · doi:10.1002/14651858.cd011027.pub3 · Cited by 57
Self-citationGenetic characteristics of patients with congenital hyperinsulinism
Vajravelu, M. E., & León, D. D. D. (2018) · Current Opinion in Pediatrics · doi:10.1097/mop.0000000000000645 · Cited by 47
Self-citationRecognition, assessment and management of hypoglycaemia in childhood
Ghosh, A., Banerjee, I., & Morris, A. A. M. (2015) · Archives of Disease in Childhood · doi:10.1136/archdischild-2015-308337 · Cited by 48
“15 This glucose concentration varies from one patient to another, depending on the availability of alternative fuels and previous blood glucose concentrations, as discussed above.”
BackgroundInfluentialDiagnosis and management of hyperinsulinaemic hypoglycaemia.
Galcheva, S., Al-Khawaga, S., & Hussain, K. (2018) · Best practice & research. Clinical endocrinology & metabolism · doi:10.1016/j.beem.2018.05.014 · Cited by 33
Self-citationPiro, E., Schierz, I. A. M., Antona, V., et al. (2020) · The Italian Journal of Pediatrics/Italian journal of pediatrics · doi:10.1186/s13052-020-00902-8 · Cited by 46
Montaldo, P., Caredda, E., Pugliese, U., Zanfardino, A., Delehaye, C., Inserra, E., Capozzi, L., Chello, G., Capristo, C., del Giudice, E. M., et al. (2020) · Pediatric Research · doi:10.1038/s41390-020-0827-4 · Cited by 46
Diagnosis and management in Rubinstein-Taybi syndrome: first international consensus statement
Lacombe, D., Bloch‐Zupan, A., Bredrup, C., Cooper, E. B., Douzgou, S., García‐Miñáur, S., Kayserili, H., Larizza, L., González, V. L., Menke, L. A., et al. (2024) · Journal of Medical Genetics · doi:10.1136/jmg-2023-109438 · Cited by 51
Intrapartum Glucose Management in Women With Gestational Diabetes Mellitus
Hamel, M. S., Kanno, L., Has, P., Beninati, M. J., Rouse, D. J., & Werner, E. F. (2019) · Obstetrics and Gynecology · doi:10.1097/aog.0000000000003257 · Cited by 41
“Maternal age (y) 30 (26–33) 30 (26–34) Race White 19 (50) 23 (61) African American 9 (24) 4 (10) Other 10 (26) 11 (29) Ethnicity Hispanic 17 (45) 18 (47) Non-Hispanic 11 (29) 14 (37) Other 10 (26) 6 (16) Nulliparity 12 (32) 14 (37) BMI (kg/m2) 1st prenatal visit 30 (26–35) 33 (28–38) At delivery 34 (29–39) 36 (33–41)…”
Diagnosis and Management of Neonatal Hypoglycemia: A Comprehensive Review of Guidelines
Giouleka, S., Gkiouleka, M., Tsakiridis, I. G., Daniilidou, A., Mamopoulos, A. M., Athanasiadis, A. P., & Dagklis, T. (2023) · Children · doi:10.3390/children10071220 · Cited by 45
“In particular, six guidelines were identified from: the American Academy of Pediatrics (AAP 2011) [11], the British Association of Perinatal Medicine (BAPM 2017) [12], the European Foundation for the Care of the Newborn Infants (EFCNI 2018) [13], the Queensland Clinical Guidelines-Australia (AUS 2019) [14], the Canadi…”
BackgroundPrevalence and safety of diazoxide in the neonatal intensive care unit
Gray, K. D., Dudash, K., Escobar-Tomlienovich, C. F., Freel, C., Harrison, T., McMillan, C., Puia‐Dumitrescu, M., Cotten, C. M., Benjamin, R. W., Clark, R. H., et al. (2018) · Journal of Perinatology · doi:10.1038/s41372-018-0218-4 · Cited by 42
“The prevalence of diazoxide exposure increased over the study period and is much higher than the 1/50,000 incidence of congenital hyperinsulinism secondary to a genetic defect for which diazoxide use is approved [2, 6].”
BackgroundInfluentialStrategies to improve neurodevelopmental outcomes in babies at risk of neonatal hypoglycaemia
Alsweiler, J. M., Harris, D. L., Harding, J. E., & McKinlay, C. J. D. (2021) · The Lancet Child & Adolescent Health · doi:10.1016/s2352-4642(20)30387-4 · Cited by 36
Self-citationGestational diabetes in twin pregnancy: A predictor of adverse fetomaternal outcomes?
Monteiro, S. S., Fonseca, L., Santos, T., et al. (2022) · Acta Diabetologica · doi:10.1007/s00592-022-01874-3 · Cited by 40
van der Louw, E. J. T. M., Aldaz, V., Harvey, J., Roan, M., van den Hurk, D., Cross, J. H., Auvin, S., & Review Group (2019) · Developmental Medicine & Child Neurology · doi:10.1111/dmcn.14306 · Cited by 40
“Blood glucose should be rechecked 15–20min after treatment and if not improved a further dose is given until the glucose level is above 3mmol/L (approximately 55mg/dL).(39) The upper limit for triglycerides is 10mmol/L (approximately 387mg/dL).”
BackgroundGlucose Gel in Infants at Risk for Transitional Neonatal Hypoglycemia
Alissa, R., Dudek, C. J., Travers, L., Smotherman, C. R., Hudak, M. L., & Makker, K. (2018) · American Journal of Perinatology · doi:10.1055/s-0038-1639338 · Cited by 38
Neonatal hypoglycemia: lack of evidence for a safe management
Roeper, M., Hoermann, H., Kummer, S., & Meißner, T. (2023) · Frontiers in Endocrinology · doi:10.3389/fendo.2023.1179102 · Cited by 38
“An important aspect is also the recognition of severe hypoglycemic disorders and under which conditions these must be thought of or when one can safely discharge newborns with hypoglycemia without overlooking a persistent or transient hypoglycemic disease (7).”
BackgroundRozance, P. J., & Wolfsdorf, J. I. (2019) · Pediatric Clinics of North America · doi:10.1016/j.pcl.2018.12.004 · Cited by 40
“For infants with a known risk of a genetic or other persistent form of hypoglycemia (eg, congenital hyperinsulinism, glucose-6-phosphatase deficiency, fatty acid oxidation disorder), the safety fast should ensure that they can maintain their plasma glucose higher than 70 mg/dL.(17) After publication of the PES recomme…”
BackgroundMethodSelf-citationA Quality-Improvement Initiative to Reduce NICU Transfers for Neonates at Risk for Hypoglycemia
LeBlanc, S., Haushalter, J., Seashore, C. J., Wood, K. S., Steiner, M. J., & Sutton, A. G. (2018) · PEDIATRICS · doi:10.1542/peds.2017-1143 · Cited by 36
Hyperinsulinemic hypoglycemia in infancy: Current concepts in diagnosis and management
Vora, S., Chandran, S., Rajadurai, V. S., & Hussain, K. (2015) · Indian Pediatrics · doi:10.1007/s13312-015-0772-1 · Cited by 34
“Current consensus by world experts on hyperinsulinism states that hypoglycemia cannot be defined as a specific plasma glucose concentration due to inability to identify a single value that causes brain damage and brain responses varies by the presence of alternative fuels like ketones [11].”
BackgroundSelf-citationABM Clinical Protocol #34: Breast Cancer and Breastfeeding
Johnson, H. M., Mitchell, K. B., Young, M. A., Noble, L., Bartick, M., Calhoun, S., Carceles-Fraguas, M. V., Elliott-Rudder, M., Feldman‐Winter, L., Kair, L. R., et al. (2020) · Breastfeeding Medicine · doi:10.1089/bfm.2020.29157.hmj · Cited by 36
Neonatal Hypoglycaemia: A Never-Ending Story?
Vain, N. E., & Chiarelli, F. (2021) · Neonatology · doi:10.1159/000514711 · Cited by 32
Kayser, A., Beck, E., Hoeltzenbein, M., Zinke, S., Meister, R., Weber‐Schoendorfer, C., & Schaefer, C. (2019) · Journal of Hypertension · doi:10.1097/hjh.0000000000002256 · Cited by 37
Edwards, T., Alsweiler, J. M., Crowther, C. A., Edlin, R. P., Gamble, G. D., Hegarty, J. E., Lin, L., McKinlay, C. J. D., Rogers, J., Thompson, B. S., et al. (2022) · JAMA · doi:10.1001/jama.2022.2363 · Cited by 33
Guidelines for Management of Neonatal Hypoglycemia
Dani, C., & Corsini, I. (2020) · Archives of Pediatrics and Adolescent Medicine · doi:10.1001/jamapediatrics.2020.0632 · Cited by 33
Männistö, J. M. E., Jääskeläinen, J., Otonkoski, T., & Huopio, H. (2021) · The Journal of Clinical Endocrinology & Metabolism · doi:10.1210/clinem/dgab024 · Cited by 32
Imperfect Advice: Neonatal Hypoglycemia
Adamkin, D. H., & Polin, R. A. (2016) · The Journal of Pediatrics · doi:10.1016/j.jpeds.2016.05.051 · Cited by 33
Carlson, J. N., Schunder-Tatzber, S., Neilson, C. J., & Hood, N. (2017) · Emergency Medicine Journal · doi:10.1136/emermed-2015-205637 · Cited by 32
Neonatal Golden Hour: a review of current best practices and available evidence
Lamary, M., Bertoni, C. B., Schwabenbauer, K., & Ibrahim, J. W. (2023) · Current Opinion in Pediatrics · doi:10.1097/mop.0000000000001224 · Cited by 32
ABM Clinical Protocol #32: Management of Hyperlactation
Johnson, H. M., Eglash, A. R., Mitchell, K. B., Leeper, K., Smillie, C. M., Moore-Ostby, L., Manson, N., Simon, L., Young, M. A., Noble, L., et al. (2020) · Breastfeeding Medicine · doi:10.1089/bfm.2019.29141.hmj · Cited by 31
Drachmann, D., Hoffmann, E., Carrigg, A., Davis-Yates, B., Weaver, V. M., THORNTON, P. S., Weinstein, D. A., Petersen, J. S., Shah, P., & Christesen, H. T. (2021) · Orphanet Journal of Rare Diseases · doi:10.1186/s13023-021-01797-2 · Cited by 29
“Ketones provide 2–6% of the body’s energy requirements after an overnight fast and up to two-thirds of the brain’s energy needs after a prolonged fast or during starvation [13, 14].”
BackgroundInfluentialSelf-citationStanley, C., Thornton, P., & León, D. D. (2023) · Frontiers in Pediatrics · doi:10.3389/fped.2023.1071206 · Cited by 27
“(3) Genetic hyperinsulinism, in contrast, reflects permanent genetic defects in various steps controlling betacell insulin release, such as inactivating mutations of the KATP-channel genes.”
BackgroundMethodInfluentialSelf-citationAcademic–Practice Partnerships: A Win-Win
Phillips, J. M., Phillips, C. R. N., Kauffman, K. R., et al. (2019) · The Journal of Continuing Education in Nursing · doi:10.3928/00220124-20190516-09 · Cited by 29
Two-year outcomes after dextrose gel prophylaxis for neonatal hypoglycaemia
Griffith, R., Hegarty, J. E., Alsweiler, J. M., Gamble, G. D., May, R. W., McKinlay, C. J. D., Thompson, B. S., Wouldes, T. A., & Harding, J. E. (2020) · Archives of Disease in Childhood Fetal & Neonatal · doi:10.1136/archdischild-2020-320305 · Cited by 29
Win, M., Beckett, R., Thomson, L. M., Thankamony, A., & Beardsall, K. (2021) · The Journal of Clinical Endocrinology & Metabolism · doi:10.1210/clinem/dgab601 · Cited by 29
Maiorana, A., Manganozzi, L., Barbetti, F., Bernabei, S. M., Gallo, G., Cusmai, R., Caviglia, S., & Dionisi‐Vici, C. (2015) · Orphanet Journal of Rare Diseases · doi:10.1186/s13023-015-0342-6 · Cited by 29
“5 mmol/L [17]) associated to cold sweating, seizures and hypotonia.”
BackgroundKallem, V. R., Pandita, A., & Gupta, G. (2017) · Clinical Medicine Insights Pediatrics · doi:10.1177/1179556517748913 · Cited by 32
Type 1 diabetes: where are we in 2017?
Copenhaver, M. M., & Hoffman, R. P. (2017) · Translational Pediatrics · doi:10.21037/tp.2017.09.09 · Cited by 27
Diazoxide for Neonatal Hyperinsulinemic Hypoglycemia and Pulmonary Hypertension
Newman-Lindsay, S., Lakshminrusimha, S., & Sankaran, D. (2022) · Children · doi:10.3390/children10010005 · Cited by 28
“zoxide exposed infants [2,4,7]; however, these lacked information on baseline NEC rates or included diverse populations beyond the neonatal period.”
Dall’Asta, A., Stampalija, T., Mecacci, F., Minopoli, M., Schera, G. B. L., Cagninelli, G., Ottaviani, C., Fantasia, I., Barbieri, M., Lisi, F., et al. (2021) · Ultrasound in Obstetrics and Gynecology · doi:10.1002/uog.23714 · Cited by 30
Dextrose Gel for Neonates at Risk With Asymptomatic Hypoglycemia: A Randomized Clinical Trial
Gupta, K., Amboiram, P., Balakrishnan, U., et al. (2022) · PEDIATRICS · doi:10.1542/peds.2021-050733 · Cited by 27
Complexities in the medical management of hypoglycaemia due to congenital hyperinsulinism
Worth, C., Yau, D., Salomon‐Estebanez, M., O’Shea, E., Cosgrove, K. E., Dunne, M. J., & Banerjee, I. (2020) · Clinical Endocrinology · doi:10.1111/cen.14152 · Cited by 29
Männistö, J. M. E., Maria, M., Raivo, J., Kuulasmaa, T., Otonkoski, T., Huopio, H., & Laakso, M. (2020) · The Journal of Clinical Endocrinology & Metabolism · doi:10.1210/clinem/dgz271 · Cited by 26
Mitchell, K. B., Johnson, H. M., Eglash, A. R., Young, M. A., Noble, L., Reece-Stremtan, S., Bartick, M., Calhoun, S., Dodd, S. E., Elliott-Rudder, M., et al. (2019) · Breastfeeding Medicine · doi:10.1089/bfm.2019.29124.kjm · Cited by 26
Metadata
- Authors
- Thornton, P. S., Stanley, C. A., De Leon, D. D., Harris, D., Haymond, M. W., Hussain, K., Levitsky, L. L., Murad, M. H., Rozance, P. J., Simmons, R. A., Sperling, M. A., Weinstein, D. A., White, N. H., & Wolfsdorf, J. I.
- Affiliations
- Cook Children's Medical Center (US)
- Children's Hospital of Philadelphia (US)
- Waikato District Health Board (NZ)
- Texas Children's Hospital (US)
- Great Ormond Street Hospital (GB)
- Massachusetts General Hospital (US)
- Mayo Clinic (US)
- University of Colorado Anschutz (US)
- Children's Hospital of Pittsburgh (US)
- University of Florida Health (US)
- Washington University in St. Louis (US)
- Boston Children's Hospital (US)
- Corresponding author
- Thornton, Paul S.
- ORCID
- Venue
- The Journal of Pediatrics
- Publisher
- Elsevier BV
- Published
- 2015-08
- Volume
- 167
- Issue
- 2
- Pages
- 238-245
- ISSN
- 0022-3476 (ISSN-L)
- PMC
- PMC11891912
- OpenAlex
- W1585861318
- Semantic Scholar
- ca2bf3a8781cb222c145d47ccfb2e95c216f9c0d
- Cited by
- 625
- References
- 44
- Citations by year
- 2026: 54 · 2025: 36 · 2024: 71 · 2023: 62 · 2022: 73 · 2021: 80 · 2020: 72 · 2019: 54 · 2018: 46 · 2017: 33 · 2016: 31 · 2015: 11
- FWCI
- 40.41
- Type
- journal article
- Language
- en
- Open access
- hybrid
- doi.org
- Licence
- Locations
- The Journal of Pediatrics (publishedVersion, cc-by-nc-nd)
- PubMed (publishedVersion)
- Europe PMC (PubMed Central) (acceptedVersion, cc-by-nc-nd)
- PubMed Central (acceptedVersion, cc-by-nc-nd)
- UCL Discovery (University College London) (submittedVersion)
- Funders
- National Institute of Diabetes and Digestive and Kidney Diseases (R01DK088139, R01DK055704)
- National Institute of Environmental Health Sciences (P30ES013508)
- Topics
- Health Sciences › Medicine › Endocrinology, Diabetes and Metabolism › Pancreatic function and diabetes
- Life Sciences › Biochemistry, Genetics and Molecular Biology › Clinical Biochemistry › Metabolism and Genetic Disorders
- Health Sciences › Medicine › Endocrinology, Diabetes and Metabolism › Diabetes Management and Research
- Keywords
- persistent hypoglycemia, neonatal hypoglycemia, infants, children, plasma glucose, hypoglycemia management, hypoglycemia etiology, hypoglycemia screening, hypoglycemia treatment, hypoglycemia diagnosis, hypoglycemia
- MeSH terms
- Blood Glucose, Child, Child, Preschool, Endocrinology, Humans, Hypoglycemia, Infant, Infant, Newborn, Pediatrics, Societies, Medical
About these checks
Registry, retraction, Cites and statistics results are computed, not judged, with one exception: a printed reference that no index lists is read once by a model before it counts as a citation error. Claims are extracted by a model and kept only when their quote appears verbatim in the text; each cited source is then checked, with a model’s help, for whether it says what the claim relies on. Those verdicts can be wrong — read the claim’s quote and the cited source before relying on one.
A language model drew the claims from the paper on 2026-10-07, under version 3 of the claim definition (model deepseek-v4.1-flash, prompt extract-v3).
A second model labelled each claim on 2026-10-07 (model jev-1.13-20260917, definition revision gold-guideline-v0.2).
Statistics and arithmetic are recomputed, not judged.
Confidence bands are shown only for fields calibrated on our annotated test set. None is calibrated yet, so no band is shown.
What counts as a claim ›How we measure confidence ›How we check this ›
Are you an author, or do you see a problem with this page? Request a review
