

The DOI matches its Crossref record; 49 of the 49 references it cites were found in a registry or an index; 24 of the 45 sources its claims cite were checked for support.
The Breathing, Thinking, Functioning clinical model: a proposal to facilitate evidence-based breathlessness management in chronic respiratory disease
Open accessAbstract
Refractory breathlessness is a highly prevalent and distressing symptom in advanced chronic respiratory disease. Its intensity is not reliably predicted by the severity of lung pathology, with unhelpful emotions and behaviours inadvertently exacerbating and perpetuating the problem. Improved symptom management is possible if clinicians choose appropriate non-pharmacological approaches, but these require engagement and commitment from both patients and clinicians. The Breathing Thinking Functioning clinical model is a proposal, developed from current evidence, that has the potential to facilitate effective symptom control, by providing a rationale and focus for treatment.
Overview
AI snapshot
Written from the paper’s full text.
TL;DR
Refractory breathlessness in advanced chronic respiratory disease is not reliably predicted by lung pathology, and unhelpful emotional and behavioural reactions can perpetuate it. The authors propose the Breathing, Thinking, Functioning (BTF) clinical model as an evidence-informed, non-pharmacological framework to explain and manage breathlessness, while noting formal evaluation is still required.
Key findings
- Breathlessness severity is poorly predicted by airflow limitation: in an observational study of almost 50,000 UK patients with COPD, a third of those with stage 1 disease described moderate to severe breathlessness, while over 20% of those with stage 4 disease did not have clinically significant breathlessness. Bronchoscopic lung volume reduction improved FEV1 by 25% without relief of breathlessness.
- Single interventions have limited benefit: oxygen did not improve breathlessness in cancer patients; in COPD patients not qualifying for home oxygen, oxygen improved breathlessness by the equivalent of 0.7 cm on a 10 cm visual analogue scale on exercise only, with no benefit before exercise and no quality-of-life improvement. Benzodiazepines showed no beneficial effect, and opioids had only borderline clinical significance.
- Multi-modal non-pharmacological approaches appear most successful: pulmonary rehabilitation produces clinically significant breathlessness reduction; a cognitive-behavioural manual in 222 COPD patients significantly improved breathlessness at 6 months and reduced A&E visits by 42%; breathlessness support services improved mastery of breathlessness by an average of 16% at 6 weeks and improved survival.
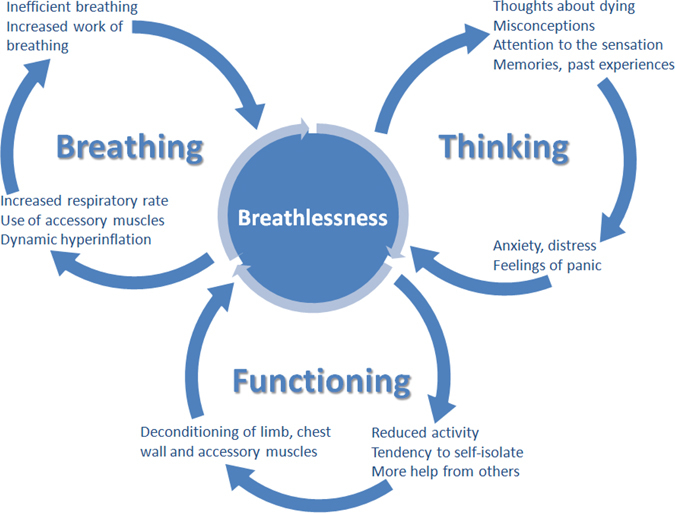
- The BTF model proposes three predominant vicious cycles—Breathing, Thinking, and Functioning—and categorises non-pharmacological interventions within these domains to focus management.
Methods
- This is a proposal/clinical model paper, not a primary empirical study. The model was developed by the Cambridge Breathlessness Intervention Service and is theoretically underpinned by a “vicious flower” maintenance model used in cognitive–behavioural therapy.
- The authors synthesise current evidence narratively, including neuroimaging, observational studies, randomised controlled trials, and Cochrane reviews, summarised in Table 1; no systematic review methods are reported.
- Planned evaluation includes mixed-methods qualitative research with in-depth interviews and focus groups, and a cluster-randomised trial in primary care for patients with COPD who remain symptomatic after, or could not complete, pulmonary rehabilitation, or who are ineligible for invasive procedures. Key outcomes will include perceived self-efficacy in symptom management, rate of primary care consultations, and out-of-hours emergency service contacts.
Limitations
- The paper states that formal research evaluation of the model is required, that a mixed-methods approach and cluster-randomised trial are planned, and that further research is required to clarify its effectiveness.
- The text states there has been no research on dysfunctional breathing patterns in other respiratory conditions such as COPD, with extensive anecdotal evidence only; service evaluations and anecdotal evidence from clinical utilisation within CBIS are described as revealing unanticipated benefits.
- Evident from the text: the BTF model itself has not yet been empirically tested in the reported work, and the supporting evidence varies in strength, including low-quality evidence for opioids and marginal or dubious clinical significance for oxygen in some contexts.
Model-written summary. Check it against the paper before relying on it.
Integrity signals
Registry
Cites
Statistics
Figures

Verification
Claims the paper makes
12 Partly supported · 11 No full text of the sources · 11 Own interpretation · 3 Supported · 3 Sources not found · accuracy not yet measured
The cited sources support only part of this claim — read each source’s verdict below.
In the paper
“Its intensity is not reliably predicted by the severity of lung pathology”
- Also stated in: § Relationship between disease and breathlessness severity · plain
“Breathlessness severity is not reliably predicted by the severity of airflow limitation in COPD.”
§ The Breathing, Thinking, Functioning clinical model: a proposal to facilitate evidence-based breathlessness management in chronic respiratory disease > Abstract
What the sources say
- Supportedcites [7] Agusti, A., Calverley, P., Celli, B., Coxson, H., Edwards, L. & Lomas, D. et al. Characteriation of COPD heterogeneity in the ECLIPSE cohort. Respir. Res. 11, 122 (2010). source
The Discussion states that airflow limitation was poorly related to the degree of breathlessness in COPD. The Results also report considerable overlap in breathlessness between GOLD stages, supporting the claim that airflow limitation does not reliably predict its severity. (LLM, conf=0.93)
- Partly supportedcites [8] Grønseth, R., Vollmer, W., Hardie, J., Ólafsdóttir, I., Lamprecht, B. & Buist, A. et al. Predictors of dyspnoea prevalence: results from the BOLD study. Eur. Respir. J. 43, 1610–1120 (2013). sourceExperimental — accuracy not yet measured
The Results report considerable overlap in lung-function measurements across dyspnoea grades, and the Discussion says adding spirometry had only a minor impact on models explaining dyspnoea. This supports the point that airflow measures do not reliably predict breathlessness intensity, but the analysis was population-based rather than specific to people with COPD, and it did not assess lung pathology beyond spirometry. (LLM, conf=0.83)
- Supportedcites [2] Mullerova, H., Chao, L., Hao, L. & Tabberer, M. Prevalence and burden of breathlessness in patients with chronic obstructive pulmonary disease managed in primary care. PLoS One 9, e85540 (2014). source
In Results (Characteristics of COPD Patients with Dyspnoea), dyspnoea severity increased as airflow limitation worsened, but the relationship was weak (Pearson r = −0.28). This supports the claim that airflow-limitation severity does not reliably predict breathlessness intensity in COPD. (LLM, conf=0.91)
- Could not verifycites [9] Zoumot, Z., Davey, C., Jordan, S., McNulty, W., Carr, D. & Hind, M. et al. A randomised controlled study of bronchoscopic lung volume reduction with endobronchial valves for patients with heterogeneous emphysema and intact interlobar fissures: the BeLieVeR-HIFi study. Effic. Mech. Eval. 2, 5 (2015). sourceExperimental — accuracy not yet measured
The Results section reports that improved FEV1 was associated with reduced breathlessness during exercise, but does not assess whether the severity of lung pathology reliably predicts breathlessness intensity. Searches for that relationship, including dyspnoea severity and airflow obstruction, found no passage addressing the claim. (LLM, conf=0.72)
plainn = 50,000- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
- Also stated in: § Relationship between disease and breathlessness severity · plain
The cited sources support only part of this claim — read each source’s verdict below.
In the paper
“Refractory breathlessness is a highly prevalent and distressing symptom in advanced chronic respiratory disease.”
- Also stated in: § Introduction · plain
“Breathlessness is prevalent in chronic respiratory disease, and primary care bears much of the burden of its management.”
§ The Breathing, Thinking, Functioning clinical model: a proposal to facilitate evidence-based breathlessness management in chronic respiratory disease > Abstract
What the sources say
- Partly supportedcites [1] Theander, K., Hasselgren, M., Luhr, K., Eckerblad, J., Unosson, M. & Karlsson, I. Symptoms and impact of symptoms on function and health in patients with chronic obstructive pulmonary disease and chronic heart failure in primary health care. Int. J. Chron. Obstruct. Pulmon. Dis. 9, 785–794 (2014). sourceExperimental — accuracy not yet measured
The Introduction reports that shortness of breath is common in COPD and that many symptoms can cause significant distress; the Discussion reports functional limitations due to dyspnea. The paper studies patients with COPD and heart failure in primary health care, but does not establish that their breathlessness was refractory or that they had advanced chronic respiratory disease. Page numbers are not available in our copy. (LLM, conf=0.88)
- Partly supportedcites [2] Mullerova, H., Chao, L., Hao, L. & Tabberer, M. Prevalence and burden of breathlessness in patients with chronic obstructive pulmonary disease managed in primary care. PLoS One 9, e85540 (2014). sourceExperimental — accuracy not yet measured
The Introduction describes dyspnoea as distressing and says that many patients with COPD continue to experience it despite available treatments. The Discussion reports that dyspnoea was highly prevalent across all stages of airflow limitation. The paper does not establish the prevalence of specifically refractory breathlessness in advanced chronic respiratory disease beyond COPD. (LLM, conf=0.86)
plain- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
- Also stated in: § Introduction · plain
The cited sources support only part of this claim — read each source’s verdict below.
In the paper
“Multiple observational studies link breathlessness with anxiety and depression.”
§ The Breathing, Thinking, Functioning clinical model: a proposal to facilitate evidence-based breathlessness management in chronic respiratory disease > Introduction
What the sources say
- Not checked — no full text of the sourcecites [4] Ho, S., O’Mahony, M., Steward, J., Breay, P., Buchalter, M. & Burr, M. Dyspnoea and quality of life in older people at home. Age and Aging 30, 155–159 (2001). source
- Partly supportedcites [5] Chavannes, N., Huiber, M., Schermer, T., Hendricks, A., van Weel, C. & Wouters, E. et al. Associations of depressive symptoms with gender, body mass index and dyspnea in primary care COPD patients. Fam. Pract. 22, 604–607 (2005). sourceExperimental — accuracy not yet measured
The Discussion (p. 4) reports an association between dyspnea and depressive symptoms in this study’s patients with mild to moderate COPD. The Methods (p. 3) describe a cross-sectional analysis but do not include an anxiety measure. Although the Introduction (p. 2) discusses studies of depression and anxiety in COPD, it does not say that multiple studies linked breathlessness with both conditions. (LLM, conf=0.87)
plaincorrelational- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
The cited sources support only part of this claim — read each source’s verdict below.
In the paper
“Patients with intractable breathlessness are commonly fatigued, which limits the capacity to retain and process new information.”
§ The Breathing, Thinking, Functioning clinical model: a proposal to facilitate evidence-based breathlessness management in chronic respiratory disease > Potential roles in supporting self-management in primary care > Facilitating and focusing management
What the sources say
- Partly supportedcites [41] Baltzan, M., Scott, A., Wolkeove, N., Bailes, S., Bernard, S. & Bourbeau, J. et al. Fatigue in COPD: prevalence and effect on outcomes in pulmonary rehabilitation. Chron. Respir. Dis. 8, 119–128 (2011). sourceExperimental — accuracy not yet measured
The Abstract and Discussion (page unavailable) report that fatigue is common among patients with COPD and that patients with high fatigue had greater dyspnea. The Introduction says fatigue may limit participation in rehabilitation activities, but the paper does not establish that it limits patients’ capacity to retain and process new information. (LLM, conf=0.85)
plaindirect- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
- Partly supported
Every source the paper cites for this claim was checked and supports it.
In the paper
“Deconditioning could, in part, explain the evidence in longitudinal studies for progression in breathlessness severity, despite stable lung function.”
§ The Breathing, Thinking, Functioning clinical model: a proposal to facilitate evidence-based breathlessness management in chronic respiratory disease > Understanding the complexity > Reactions to breathlessness
What the sources say
- Supportedcites [28] Mahler, D., Ward, D., Waterman, L. & Baird, J. Longitudinal changes in patient-reported dyspnoea in patients with COPD. COPD 9, 522–527 (2012). source
The Discussion reports worsening patient-reported dyspnea over two years while lung function remained generally stable. It also identifies deconditioning as a possible contributor to increased breathing difficulty, matching the claim’s tentative explanation. (LLM, conf=0.91)
hedgedconditional- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: unclear — It is unclear whether the paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
- Supported
The cited sources support only part of this claim — read each source’s verdict below.
In the paper
“Instead the most successful interventions appear to be multi-modal, non-pharmacological approaches that work concurrently at multiple points within the brain, respiratory and skeletal system.”
§ The Breathing, Thinking, Functioning clinical model: a proposal to facilitate evidence-based breathlessness management in chronic respiratory disease > Understanding the complexity > Neurophysiology of breathlessness
What the sources say
- Partly supportedcites [21] Howard, C. & Dupont, S. The COPD breathlessness manual’: a randomised controlled trial to test a cognitive-behavioural manual versus information booklets on health service use, mood and health status, in patients with chronic obstructive pulmonary disease. Prim. Care Respir. Med. 24, 14076. doi:14010.11038/npjpcrm.12014.14076 (2014). sourceExperimental — accuracy not yet measured
The Materials and methods section describes a non-pharmacological manual combining cognitive-behavioural strategies, breathing control and mobility exercises. But the Discussion says the study cannot identify which component was most effective and calls for trials disentangling their contributions. It does not establish that multimodal approaches are the most successful or that they act concurrently within the brain, respiratory and skeletal systems. Our copy provides section labels but no page numbers. (LLM, conf=0.88)
- Not matchedcites [22] Bausewein, C., Booth, S., Gysels, M. & Higginson, I. Non-pharmacological interventions for breathlessness in advanced stages of malignant and non-malignant diseases. Cochrane Database Syst. Rev. 2, CD005623. doi:005610.001002/14651858 (2008).
Couldn’t be matched to a paper in Crossref, so it can’t be checked.
- Partly supportedcites [23] Zwerink, M., Brusse-Keizer, M., van der Valk, P., Zielhuis, G., Monninkhof, E. & van der Palen, J. et al. Self management for patients with chronic obstructive pulmonary disease. Cochrane Database Syst. Rev. 19, CD002990 (2014). sourceExperimental — accuracy not yet measured
The Interventions section describes multicomponent self-management programmes, and the Discussion reports a statistically significant reduction in shortness of breath. But the Discussion says the studies were too different to identify the most effective combination of components. It does not establish that these approaches work concurrently on the brain, respiratory system and skeletal system. (LLM, conf=0.86)
hedgeddirect- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
- Partly supported
The cited sources support only part of this claim — read each source’s verdict below.
In the paper
“Even opioids, with most evidence to support their use, provide benefit of only borderline clinical significance.”
§ The Breathing, Thinking, Functioning clinical model: a proposal to facilitate evidence-based breathlessness management in chronic respiratory disease > Understanding the complexity > Neurophysiology of breathlessness
What the sources say
- Partly supportedcites [19] Abernethy, A., Currow, D., Frith, P., Fazekas, B., McHugh, A. & Bui, C. Randomised, double blind, placebo controlled crossover trial of sustained release morphine for the management of refractory dyspnoea. Br. Med. J. 327, 523–526 (2003). sourceExperimental — accuracy not yet measured
The Discussion reports a modest 7–10 mm improvement in breathlessness and calls it clinically significant. The Limitations section acknowledges that the clinical significance of that change may be questioned, but describes a 5–10% improvement as welcome. These passages support a modest benefit, not the categorical claim that opioids provide benefit of only borderline clinical significance. (LLM, conf=0.82)
- Supportedcites [20] Barnes P., McDonald J., Smallwood N., Manser R. Opioids for the palliation of refractory breathlessness in adults with advanced disease and terminal illness. Cochrane Database Syst. Rev. 3, CD011008 (2016). source
The Discussion (page unavailable) describes a small clinically significant benefit for oral and subcutaneous opioids, based on low-quality evidence. In Additional information (page unavailable), the authors say an estimated benefit was just at the threshold for clinical significance and that its confidence interval likely includes values that are not clinically significant. This supports the paraphrase that the benefit is borderline. (LLM, conf=0.90)
plaindirect- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: unclear — It is unclear whether the paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
- Partly supported
The cited sources support only part of this claim — read each source’s verdict below.
In the paper
“The evidence is clear that when individuals with a chronic condition, like COPD, actively participate in their own care through self-management, their medical outcomes improve.”
§ The Breathing, Thinking, Functioning clinical model: a proposal to facilitate evidence-based breathlessness management in chronic respiratory disease > Potential roles in supporting self-management in primary care > Explaining and engaging
What the sources say
- Partly supportedcites [37] Bucknall, C., Miller, G., Lloyd, S., Cleland, J., McCluskey, S. & Cotton, M. et al. Glasgow supported self-management trial (GSuST) for patients with moderate to severe COPD: a randomised controlled trial. Br. Med. J. 344, e1060 (2012). sourceExperimental — accuracy not yet measured
The Successful self management section reports fewer COPD readmissions among participants who successfully used self-management techniques. But the Conclusions section says the intervention had no overall effect on COPD readmissions or deaths; the benefit came from an exploratory subgroup analysis. The claim presents that narrower finding as a clear, general improvement in medical outcomes. (LLM, conf=0.88)
- Not checked — no full text of the sourcecites [38] Shively, M., Gardetto, G., Kodiath, M., Kelly, A., Smith, T. & Stepnowsky, C. et al. Effect of patient activation on self-management in patients with heart failure. J. Cardiovasc. Nurs. 28, 20–34 (2013). source
boosteddirect- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
- Partly supported
A conclusion the paper draws from its own results — it cites no other source for it, so there is none to check. The quote shows it is in the paper.
In the paper
“A consequence of this neural complexity is that it limits the potential for a single effective intervention, a point supported by an increasing body of literature (Table 1).”
§ The Breathing, Thinking, Functioning clinical model: a proposal to facilitate evidence-based breathlessness management in chronic respiratory disease > Understanding the complexity > Neurophysiology of breathlessness
plaindirect- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
In the paper
“Benzodiazepines are widely used, but do not improve breathlessness.”
§ The Breathing, Thinking, Functioning clinical model: a proposal to facilitate evidence-based breathlessness management in chronic respiratory disease > Understanding the complexity > Neurophysiology of breathlessness
What the sources say
- Not matchedcites [18] Simon, S., Higginson, I., Booth, S., Harding, R. & Bausewein, C. Benzodiazepines for the relief of breathlessness in advanced malignant and non-malignant diseases in adults. Cochrane Database Syst. Rev. 1, CD007354. doi:007310.001002/14651858 (2010).
Couldn’t be matched to a paper in Crossref, so it can’t be checked.
plain- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: unclear — It is unclear whether the paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
- Not matched
A claim is checked only against the cited paper’s full text, never its abstract, and none is available for its sources.
In the paper
“Neuroimaging studies over the last decade have significantly increased understanding of the neural processing of the sensation of breathlessness, and the range of factors influencing the symptom perception.”
§ The Breathing, Thinking, Functioning clinical model: a proposal to facilitate evidence-based breathlessness management in chronic respiratory disease > Understanding the complexity > Neurophysiology of breathlessness
What the sources say
- Not checked — no full text of the sourcecites [10] Banzett, R., Mulnier, H., Murphy, K., Rosen, S., Wise, R. & Adams, L. Breathlessness in humans activates insular cortex. Neuroreport 11, 2117–2120 (2000). source
- Not checked — no full text of the sourcecites [11] Evans, K., Banzett, R., Adams, L., McKay, L., Frackowiak, R. & Corfield, D. Bold fMRI indentifies limbic, paralimbic, and cerebellar activation during air hunger. J. Neurophysiol. 88, 1500–1511 (2002). source
boosteddirect- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: unclear — It is unclear whether the paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
A conclusion the paper draws from its own results — it cites no other source for it, so there is none to check. The quote shows it is in the paper.
In the paper
“with unhelpful emotions and behaviours inadvertently exacerbating and perpetuating the problem.”
- Also stated in: § Reactions to breathlessness · plain
“such emotions and behaviours can be unhelpful and inadvertently perpetuate the problem.”
§ The Breathing, Thinking, Functioning clinical model: a proposal to facilitate evidence-based breathlessness management in chronic respiratory disease > Abstract
plaindirect- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
- Rests on an assumption: Interoceptive awareness of an acute homoeostatic threat leads to avoidance behaviour motivated by emotion, which confers a survival advantage.
- Also stated in: § Reactions to breathlessness · plain
A claim is checked only against the cited paper’s full text, never its abstract, and none is available for its sources.
In the paper
“Breathlessness perception is believed to be driven by a mismatch between the two.”
§ The Breathing, Thinking, Functioning clinical model: a proposal to facilitate evidence-based breathlessness management in chronic respiratory disease > Understanding the complexity > Neurophysiology of breathlessness
What the sources say
- Not checked — no full text of the sourcecites [13] Manning, H. & Schwartzstein, R. Pathophysiology of dysnpnea. N. Engl. J. Med. 333, 1547–1553 (1995). source
- Not checked — no full text of the sourcecites [14] Schwartzstein, R., Manning, H., Weiss, J. & Weinberger, S. Dyspnoea: a sensory experience. Lung 168, 185–199 (1990). source
hedgeddirect- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
A conclusion the paper draws from its own results — it cites no other source for it, so there is none to check. The quote shows it is in the paper.
In the paper
“Optimising treatment of the underlying disease has an inconsistent impact on the symptom.”
- Also stated in: § Relationship between disease and breathlessness severity · plain
“optimising disease management alone does not guarantee good symptom control.”
§ The Breathing, Thinking, Functioning clinical model: a proposal to facilitate evidence-based breathlessness management in chronic respiratory disease > Introduction
plainconditional- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
- Also stated in: § Relationship between disease and breathlessness severity · plain
In the paper
“The more information presented in a consultation, the lower the proportion that is correctly recalled.”
§ The Breathing, Thinking, Functioning clinical model: a proposal to facilitate evidence-based breathlessness management in chronic respiratory disease > Potential roles in supporting self-management in primary care > Facilitating and focusing management
What the sources say
- Not checked — no full text of the sourcecites [42] Anderson, J., Dodman, S., Kopelman, M. & Fleming, A. Patient information recall in a rheumatology clinic. Rheumatol. Rehabil. 18, 245–255 (1979). source
plaindirect- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
In the paper
“Enhancing self-efficacy is a particularly effective way to support self-management.”
§ The Breathing, Thinking, Functioning clinical model: a proposal to facilitate evidence-based breathlessness management in chronic respiratory disease > Potential roles in supporting self-management in primary care > Explaining and engaging
What the sources say
- Not matchedcites [40] The Health Foundation. Evidence: helping people help themselves (The Health Foundation, 2011).
Couldn’t be matched to a paper in Crossref, so it can’t be checked.
boosteddirect- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: unclear — It is unclear whether the paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
- Not matched
A conclusion the paper draws from its own results — it cites no other source for it, so there is none to check. The quote shows it is in the paper.
In the paper
“The model is based on three predominant cognitive and behavioural reactions to breathlessness that, by causing vicious cycles, worsen and maintain the symptom (Fig. 1).”
§ The Breathing, Thinking, Functioning clinical model: a proposal to facilitate evidence-based breathlessness management in chronic respiratory disease > The BTF clinical model
plaindirect- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: unclear — It is unclear why the paper says it holds.
- Rests on an assumption: Anxiety increases respiratory rate and can cause muscle tension in the ventilatory pump and other skeletal muscles, further increasing work of breathing and respiratory demand.
- Rests on an assumption: There is extensive anecdotal evidence that dysfunctional breathing patterns occur in respiratory conditions such as COPD.
- Rests on an assumption: Patients intuitively understand the 'deconditioning vicious cycle'.
- Rests on an assumption: Family members and other carers can unwittingly compound the situation by doing activities that the patient might otherwise have done.
A conclusion the paper draws from its own results — it cites no other source for it, so there is none to check. The quote shows it is in the paper.
In the paper
“There is growing evidence for a further level of complexity: the human reaction to the perception of breathlessness may worsen the symptom.”
§ The Breathing, Thinking, Functioning clinical model: a proposal to facilitate evidence-based breathlessness management in chronic respiratory disease > Understanding the complexity > Reactions to breathlessness
hedgedconditional- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
- Rests on an assumption: Interoceptive awareness of an acute homoeostatic threat leads to avoidance behaviour motivated by emotion, which confers a survival advantage.
A claim is checked only against the cited paper’s full text, never its abstract, and none is available for its sources.
In the paper
“Neuroimaging studies reveal that breathlessness activates cortico-limbic areas, particularly the right anterior insula.”
§ The Breathing, Thinking, Functioning clinical model: a proposal to facilitate evidence-based breathlessness management in chronic respiratory disease > Understanding the complexity > Reactions to breathlessness
What the sources say
- Not checked — no full text of the sourcecites [10] Banzett, R., Mulnier, H., Murphy, K., Rosen, S., Wise, R. & Adams, L. Breathlessness in humans activates insular cortex. Neuroreport 11, 2117–2120 (2000). source
- Not checked — no full text of the sourcecites [11] Evans, K., Banzett, R., Adams, L., McKay, L., Frackowiak, R. & Corfield, D. Bold fMRI indentifies limbic, paralimbic, and cerebellar activation during air hunger. J. Neurophysiol. 88, 1500–1511 (2002). source
plaindirect- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
A conclusion the paper draws from its own results — it cites no other source for it, so there is none to check. The quote shows it is in the paper.
In the paper
“However, in the context of chronic perceived threats such as persistent breathlessness, such emotions and behaviours can be unhelpful and inadvertently perpetuate the problem.”
§ The Breathing, Thinking, Functioning clinical model: a proposal to facilitate evidence-based breathlessness management in chronic respiratory disease > Understanding the complexity > Reactions to breathlessness
plainconditional- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
- Rests on an assumption: Interoceptive awareness of an acute homoeostatic threat leads to avoidance behaviour motivated by emotion, which confers a survival advantage.
In the paper
“The neural processing for this feedback loop is likely to occur in the cortico-limbic areas of the brain, involved in both breathlessness perception and processing of emotion.”
§ The Breathing, Thinking, Functioning clinical model: a proposal to facilitate evidence-based breathlessness management in chronic respiratory disease > The BTF clinical model > Thinking domain
What the sources say
- Not checked — no full text of the sourcecites [34] von Leupoldt, A., Sommer, T., Kegat, S., Baumann, H., Klose, H. D., Dahme, B. & Büchel, C. The unpleasantness of perceived dyspnea is processed in the anterior insula and amygdala. Am. J. Respir. Crit. Care Med. 177, 1026–1032 (2008). source
hedgedconditional- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: unclear — It is unclear whether the paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
In the paper
“Dysfunctional breathing patterns are well recognised in breathless individuals without underlying respiratory pathology.”
§ The Breathing, Thinking, Functioning clinical model: a proposal to facilitate evidence-based breathlessness management in chronic respiratory disease > The BTF clinical model > Breathing domain
What the sources say
- Not checked — no full text of the sourcecites [29] Gardner, W. The pathophysiology of hyperventilation disorders. Chest 109, 516–534 (1996). source
boostedcorrelational- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
In the paper
“It is well-recognised that the anxiety or fear caused by breathlessness can, in turn, augment the perception of breathlessness.”
§ The Breathing, Thinking, Functioning clinical model: a proposal to facilitate evidence-based breathlessness management in chronic respiratory disease > The BTF clinical model > Thinking domain
What the sources say
- Not checked — no full text of the sourcecites [33] Livermore, N., Butler, J., Sharpe, L., BcBain, R., Gandevia, S. & McKenzie, D. Panic attacks and perception of inspiratory resistive loads in chronic obstructive pulmonary disease. Am. J. Respir. Crit. Care Med. 178, 7–12 (2008). source
boosteddirect- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
- It may state two separate claims as one. 15
- Probably not a substantial claim. 4
The cited sources support only part of this claim — read each source’s verdict below.
In the paper
“Oxygen therapy, although it reverses hypoxaemia, does not improve breathlessness in patients with cancer, and the marginal benefit seen in a meta-analysis of COPD patients is of dubious clinical significance.”
§ The Breathing, Thinking, Functioning clinical model: a proposal to facilitate evidence-based breathlessness management in chronic respiratory disease > Understanding the complexity > Neurophysiology of breathlessness
What the sources say
- Partly supportedcites [16] Uronis, H., Currow, D., McCrory, D., Samsa, G. & Abernethy, A. Oxygen for relief of dyspnoea in mildly- or non-hypoxaemic patients with cancer: a systematic review and meta-analysis. Br. J. Cancer 98, 294–299 (2008). sourceExperimental — accuracy not yet measured
The Results (Treatment efficacy; page unavailable) report that oxygen did not improve dyspnoea in mildly- or non-hypoxaemic cancer patients who would not normally qualify for home oxygen therapy. That supports the cancer finding, but not its extension to all patients with cancer. The paper says a separate review addressed COPD; it does not establish that a marginal benefit in a COPD meta-analysis was of dubious clinical significance. (LLM, conf=0.87)
- Partly supportedcites [17] Ekström, M., Ahmadi, Z., Bornefalk-Hermansson, A., Abernethy, A. & Currow, D. Oxygen for breathlessness in patients with chronic obstructive pulmonary disease who do not qualify for home oxygen therapy. Cochrane Database Syst. Rev. 11, CD006429 (2016). sourceExperimental — accuracy not yet measured
The Discussion (page not available in our copy) reports a modest reduction in COPD breathlessness during exercise and says its clinical importance is unclear; the Authors’ Conclusions likewise find no evidence of a clinically important benefit in daily life. The review does not establish the sentence’s separate claim that oxygen fails to improve breathlessness in patients with cancer. (LLM, conf=0.86)
plain- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
- Partly supported
The cited sources support only part of this claim — read each source’s verdict below.
In the paper
“Such services provide a brief, cost-effective intervention that impacts positively on distress from breathlessness, mastery, quality of life, and even survival.”
§ The Breathing, Thinking, Functioning clinical model: a proposal to facilitate evidence-based breathlessness management in chronic respiratory disease > Understanding the complexity > Neurophysiology of breathlessness
What the sources say
- Partly supportedcites [25] Farquhar, M., Prevost, A., McCrone, P., Brafman-Price, B., Bentley, A. & Higginson, I. et al. Is a specialist breathlessness service more effective and cost-effective for patients with advanced cancer and their carers than standard care? Findings of a mixed-method randomised controlled trial. BMC Med. 12, 194 (2014). sourceExperimental — accuracy not yet measured
The Results and Discussion report that the Breathlessness Intervention Service reduced distress due to breathlessness and was likely cost-effective on that outcome; participants also described greater confidence in managing breathlessness. But the Results found no significant improvement in measured mastery or quality-of-life domains, and the copy provides no evidence of improved survival (searched: survival). (LLM, conf=0.90)
- Partly supportedcites [26] Higginson, I., Bausewein, C., Reilly, C., Gao, W., Gysels, M. & Dzingina, M. et al. An integrated palliative and respiratory care service for patients with advanced disease and refractory breathlessness: a randomised controlled trial. Lancet Respir. Med. 2, 979–987 (2014). sourceExperimental — accuracy not yet measured
The Summary (p. 2) reports improved breathlessness mastery and better survival in the service group, while cautioning that the survival finding needs further investigation. The Results (pp. 6–7) report no significant between-group differences in other patient-reported outcomes, including quality of life, and no significant difference in formal care costs. The paper therefore supports mastery and an exploratory survival finding, but does not establish improved breathlessness distress or quality of life relative to usual care, or demonstrate cost-effectiveness. (LLM, conf=0.88)
- Partly supportedcites [27] Johnson, M., Kanaan, M., Richardson, G., Nabb, S., Torgerson, D. & English, A. et al. A randomised controlled trial of three or one breathing technique training sessions for breathlessness in people with malignant lung disease. BMC Med. 13, 213 (2015). sourceExperimental — accuracy not yet measured
The Background and Discussion report benefits from non-pharmacological breathlessness interventions, including improvements in distress and mastery. The Results find a single breathing-training session likely cost-effective compared with three sessions, not compared with no service. The paper does not show that a breathlessness service improves survival; its Discussion attributes improved survival to a separate early-palliative-care trial. (LLM, conf=0.88)
plaindirect- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
- Partly supported
Every source the paper cites for this claim was checked and supports it.
In the paper
“Approaches incorporating cognitive behavioural therapy ameliorate breathlessness, as well as anxiety and depression.”
§ The Breathing, Thinking, Functioning clinical model: a proposal to facilitate evidence-based breathlessness management in chronic respiratory disease > Understanding the complexity > Neurophysiology of breathlessness
What the sources say
- Supportedcites [21] Howard, C. & Dupont, S. The COPD breathlessness manual’: a randomised controlled trial to test a cognitive-behavioural manual versus information booklets on health service use, mood and health status, in patients with chronic obstructive pulmonary disease. Prim. Care Respir. Med. 24, 14076. doi:14010.11038/npjpcrm.12014.14076 (2014). source
The Results (Mood and health status; page unavailable) report greater improvements in anxiety, depression and dyspnoea with the cognitive-behavioural manual than with information booklets at six months. Dyspnoea is the study’s measure of breathlessness, so the findings support the claim in patients with COPD. (LLM, conf=0.92)
plaindirect- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
- Supported
The cited sources support only part of this claim — read each source’s verdict below.
In the paper
“Breathing pattern disorders occur in about a third of asthma patients”
§ The Breathing, Thinking, Functioning clinical model: a proposal to facilitate evidence-based breathlessness management in chronic respiratory disease > The BTF clinical model > Breathing domain
What the sources say
- Partly supportedcites [31] Thomas, M., McKinley, R., Freeman, E. & Foy, C. Prevalence of dysfunctional breathing in patients treated for asthma in primary care: cross sectional survey. Br. Med. J. 2001, 1098–1100 (2001). sourceExperimental — accuracy not yet measured
The Additional information section reports that 29% of adults treated for asthma in primary care had symptoms suggestive of dysfunctional breathing. That supports the approximate proportion, but the study screened adults in one practice; it did not establish that breathing pattern disorders occur in a third of asthma patients generally. (LLM, conf=0.85)
plain- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: fails — The paper’s conclusions may not depend on it.
- Based: passes — The paper gives a reason why it holds.
Probably not a substantial claim. The paper’s conclusions may not depend on it.
- Partly supported
The cited sources support only part of this claim — read each source’s verdict below.
In the paper
“However, inactivity leads to muscle deconditioning, with reduced oxidative capacity, muscle fibre atrophy and fibre type shift from type 1 (oxidative) to type IIb (glycolytic) fibres.”
§ The Breathing, Thinking, Functioning clinical model: a proposal to facilitate evidence-based breathlessness management in chronic respiratory disease > The BTF clinical model > Functioning domain
What the sources say
- Partly supportedcites [35] Kim, H., Mofarrahi, M. & Hussain, S. Skeletal muscle dysfunction in patients with chronic obstructive pulmonary disease. Int. J. Chron. Obstruct. Pulmon. Dis. 3, 637–658 (2008). sourceExperimental — accuracy not yet measured
The Inactivity section says physical inactivity causes deconditioning, reduced oxidative capacity, fiber atrophy, and a lower proportion of type I fibers. The Fiber type shift section reports increased type IIb fibers in patients with severe COPD, but does not establish that inactivity alone causes that specific shift; the Inactivity section cautions that inactivity does not fully explain muscle dysfunction in COPD. Page numbers were not available in our copy. (LLM, conf=0.85)
plaindirect- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
- Partly supported
Every source the paper cites for this claim was checked and supports it.
In the paper
“There is strong evidence, for example, that pulmonary rehabilitation, involving exercise, education and support over many weeks, leads to clinically significant reduction in breathlessness, as well as substantial improvements in fatigue, emotional functioning and quality of life.”
§ The Breathing, Thinking, Functioning clinical model: a proposal to facilitate evidence-based breathlessness management in chronic respiratory disease > Understanding the complexity > Neurophysiology of breathlessness
What the sources say
- Supportedcites [24] McCarthy, B., Casey, D., Devane, D., Murphy, K., Murphy, E. & Lacasse, Y. Pulmonary rehabilitation for chronic obstructive pulmonary disease. Cochrane Database Syst. Rev. 23, CD003793 (2015). source
The Authors’ Conclusions report clinically and statistically significant improvements in dyspnoea, fatigue, emotional function and other health-related quality-of-life domains for patients with COPD. The review’s results further report that the average improvement in each of these domains exceeded the minimal clinically important difference, with the dyspnoea confidence interval entirely above that threshold. (LLM, conf=0.93)
boosteddirect- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
- Supported
The cited sources support only part of this claim — read each source’s verdict below.
In the paper
“This empirical model was developed by the Cambridge Breathlessness Intervention Service (CBIS), a multidisciplinary home-based intervention of proven cost-effectiveness.”
§ The Breathing, Thinking, Functioning clinical model: a proposal to facilitate evidence-based breathlessness management in chronic respiratory disease > The BTF clinical model > Model development
What the sources say
- Partly supportedcites [25] Farquhar, M., Prevost, A., McCrone, P., Brafman-Price, B., Bentley, A. & Higginson, I. et al. Is a specialist breathlessness service more effective and cost-effective for patients with advanced cancer and their carers than standard care? Findings of a mixed-method randomised controlled trial. BMC Med. 12, 194 (2014). sourceExperimental — accuracy not yet measured
Box 1 and the Methods describe BIS as a multidisciplinary intervention delivered predominantly in patients’ homes. The Conclusions say BIS appears cost-effective compared with standard care for patients with breathlessness in advanced cancer, but the paper does not identify a BTF model or say that CBIS developed it. “Proven cost-effectiveness” also states the finding more strongly and broadly than the paper does. (LLM, conf=0.86)
plain- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: unclear — It is unclear whether the paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
- Partly supported
A claim is checked only against the cited paper’s full text, never its abstract, and none is available for its sources.
In the paper
“Neural integration occurs in cortico-limbic regions of the brain, which are influenced by thoughts and emotions, further modulating breathlessness perception.”
§ The Breathing, Thinking, Functioning clinical model: a proposal to facilitate evidence-based breathlessness management in chronic respiratory disease > Understanding the complexity > Neurophysiology of breathlessness
What the sources say
- Not checked — no full text of the sourcecites [11] Evans, K., Banzett, R., Adams, L., McKay, L., Frackowiak, R. & Corfield, D. Bold fMRI indentifies limbic, paralimbic, and cerebellar activation during air hunger. J. Neurophysiol. 88, 1500–1511 (2002). source
- Not checked — no full text of the sourcecites [15] Schon, D., Rosenkranz, M., Regelsberger, J., Dahme, B., Buchel, C. & von Leupoldt, A. Reduced perception of dyspnoea and pain after right insular cortex lesion. Am. J. Respir. Crit. Care Med. 178, 1173–1179 (2008). source
plaindirect- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
A conclusion the paper draws from its own results — it cites no other source for it, so there is none to check. The quote shows it is in the paper.
In the paper
“The BTF model has the potential to fulfil all these needs, and may be particularly relevant in community settings.”
§ The Breathing, Thinking, Functioning clinical model: a proposal to facilitate evidence-based breathlessness management in chronic respiratory disease > Conclusion
hedgedconditional- Asserted: passes — The authors put it forward as true.
- Checkable: fails — It may be too vague to check against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
Probably not a substantial claim. It may be too vague to check against evidence. It may state two separate claims as one.
- Rests on an assumption: Time-pressured clinical settings require a brief intervention that targets the specific mechanisms driving an individual's symptoms.
A conclusion the paper draws from its own results — it cites no other source for it, so there is none to check. The quote shows it is in the paper.
In the paper
“We propose that the BTF model not only explains how breathlessness perpetuates and worsens, but also provides a structure and rationale for its management—through generating the antithesis of vicious cycles, ‘cycles of improvement’—thereby engaging patients and professionals alike.”
§ The Breathing, Thinking, Functioning clinical model: a proposal to facilitate evidence-based breathlessness management in chronic respiratory disease > Conclusion
plaindirect- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
Probably not a substantial claim. It may state two separate claims as one.
- Rests on an assumption: Time-pressured clinical settings require a brief intervention that targets the specific mechanisms driving an individual's symptoms.
In the paper
“Each of the three domains is supported by research evidence, as described above, and the model is theoretically underpinned by a ‘vicious flower’ maintenance model formulation, widely used in cognitive–behavioural therapy within psychological medicine.”
§ The Breathing, Thinking, Functioning clinical model: a proposal to facilitate evidence-based breathlessness management in chronic respiratory disease > The BTF clinical model > Model development
What the sources say
- Not checked — no full text of the sourcecites [36] Moorey, S. The six cycles maintenance model: growing a ‘vicious flower’ for depression. Behav Cogn Psychol. 38, 173–184 (2010). source
plain- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
In the paper
“Apical breathing causes reliance on fatiguable accessory muscles of respiration, underutilising the efficient and relatively fatigue-resistant diaphragmatic muscle, further increasing the work of breathing and intensifying breathlessness.”
§ The Breathing, Thinking, Functioning clinical model: a proposal to facilitate evidence-based breathlessness management in chronic respiratory disease > The BTF clinical model > Breathing domain
What the sources say
- Not checked — no full text of the sourcecites [32] Dempsey, J., Romer, L., Rodman, J., Miller, J. & Smith, C. Consequences of exercise-induced respiratory muscle work. Resp. Phys. Neurobiol. 151, 242–250 (2006). source
plaindirect- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
A conclusion the paper draws from its own results — it cites no other source for it, so there is none to check. The quote shows it is in the paper.
In the paper
“This increases the demand on the respiratory system, and worsens breathlessness further.”
§ The Breathing, Thinking, Functioning clinical model: a proposal to facilitate evidence-based breathlessness management in chronic respiratory disease > The BTF clinical model > Functioning domain
plaindirect- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
In the paper
“The ‘small changes approach’, accepted as a particularly effective and feasible way of achieving behavioural change, develops the potential to generate rapid and large gains.”
§ The Breathing, Thinking, Functioning clinical model: a proposal to facilitate evidence-based breathlessness management in chronic respiratory disease > Potential roles in supporting self-management in primary care > Explaining and engaging
What the sources say
- Not checked — no full text of the sourcecites [39] Hill, J., Wyatt, H., Reed, G. & Peters, J. Obesity and the environment: where do we go from here? Science 299, 835–855 (2003). source
plaindirect- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
In the paper
“Features include apical breathing, higher ratio of inspiratory to expiratory length, absence of end-expiratory pause and frequent sighs or yawns.”
§ The Breathing, Thinking, Functioning clinical model: a proposal to facilitate evidence-based breathlessness management in chronic respiratory disease > The BTF clinical model > Breathing domain
What the sources say
- Not matchedcites [30] Chaitow L., Bardley D., Gilbert C. Multidisciplinary approaches to breathing pattern disorders. (Churchill Livingstone, London, 2002).
Couldn’t be matched to a paper in Crossref, so it can’t be checked.
plain- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
- Not matched
A conclusion the paper draws from its own results — it cites no other source for it, so there is none to check. The quote shows it is in the paper.
In the paper
“For example, attempting to avoid the perception of breathlessness by reducing activity, leads to deconditioning that, in turn, worsens breathlessness.”
§ The Breathing, Thinking, Functioning clinical model: a proposal to facilitate evidence-based breathlessness management in chronic respiratory disease > Understanding the complexity > Reactions to breathlessness
plaindirect- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
A conclusion the paper draws from its own results — it cites no other source for it, so there is none to check. The quote shows it is in the paper.
In the paper
“The wide array of potentially effective non-pharmacological interventions for breathlessness fit neatly within the three domains of the clinical model (Table 2).”
§ The Breathing, Thinking, Functioning clinical model: a proposal to facilitate evidence-based breathlessness management in chronic respiratory disease > Potential roles in supporting self-management in primary care > Facilitating and focusing management
plaincorrelational- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: fails — The paper may give no reason why it holds.
Probably not a substantial claim. The paper may give no reason why it holds.
- Rests on an assumption: Clinical experience shows that although all three vicious cycles occur to a degree in each breathless patient, one or two tend to predominate.
- Rests on an assumption: Focusing on interventions that impact the predominant cycle can increase adherence and provide early 'quick wins' that contribute to patient engagement and self-efficacy.
- Rests on an assumption: Compassionately challenging misconceptions driving a predominant vicious cycle can be highly effective and time-efficient.
The paper relies on this without support.
Interoceptive awareness of an acute homoeostatic threat leads to avoidance behaviour motivated by emotion, which confers a survival advantage.
“Interoceptive awareness of an acute homoeostatic threat leads to an avoidance behaviour motivated by emotion, which, in evolutionary terms, clearly confers a survival advantage.”
The paper relies on this without support.
Anxiety increases respiratory rate and can cause muscle tension in the ventilatory pump and other skeletal muscles, further increasing work of breathing and respiratory demand.
“In addition, anxiety increases the respiratory rate and can cause muscle tension in both the ventilatory pump and other skeletal muscles, so further increasing the work of breathing and respiratory demand.”
The paper relies on this without support.
There is extensive anecdotal evidence that dysfunctional breathing patterns occur in respiratory conditions such as COPD.
“although there has been no research in other respiratory conditions, such as COPD, there is extensive anecdotal evidence that dysfunctional breathing patterns do occur.”
The paper relies on this without support.
Patients intuitively understand the 'deconditioning vicious cycle'.
“Patients intuitively understand this ‘deconditioning vicious cycle’, being aware that less ‘fit’ people are more breathless on exertion.”
The paper relies on this without support.
Family members and other carers can unwittingly compound the situation by doing activities that the patient might otherwise have done.
“Family members and other carers can unwittingly compound the situation, by trying to help through doing activities that the patient might otherwise have done.”
The paper relies on this without support.
Non-pharmacological interventions are under-utilised because patients need commitment to make and sustain behaviour change.
“Non-pharmacological interventions are under-utilised, not least because patients need commitment to make and sustain behaviour change.”
The paper relies on this without support.
Providing a clear and logical rationale for symptom deterioration or perpetuation beyond an initial trigger can be profoundly motivating.
“Providing a clear and logical rationale for symptom deterioration, or perpetuation beyond an initial trigger, can be profoundly motivating.”
The paper relies on this without support.
Clinical experience shows that although all three vicious cycles occur to a degree in each breathless patient, one or two tend to predominate.
“Clinical experience shows that, although all three vicious cycles occur to a degree in each breathless patient, in practice, one or two tend to predominate.”
The paper relies on this without support.
Focusing on interventions that impact the predominant cycle can increase adherence and provide early 'quick wins' that contribute to patient engagement and self-efficacy.
“Focusing on those interventions which impact on the predominant cycle can increase adherence and, importantly, provide early ‘quick wins’ that further contribute to patient engagement and self-efficacy.”
The paper relies on this without support.
Compassionately challenging misconceptions driving a predominant vicious cycle can be highly effective and time-efficient.
“Simply, for example, compassionately challenging one of the misconceptions driving a predominant vicious cycle (Fig. 2) can, in itself, be highly effective and time-efficient in a busy healthcare setting.”
The paper relies on this without support.
Time-pressured clinical settings require a brief intervention that targets the specific mechanisms driving an individual's symptoms.
“Time-pressured clinical settings require a brief intervention that targets the specific mechanisms driving an individual’s symptoms.”
The paper relies on this without support.
Clinical training prioritises disease-modification over symptom control and doctors are rarely taught how to support behaviour change.
“Clinical training prioritises disease-modification over symptom control and, unlike allied health professionals, doctors are rarely taught how to support behaviour change.”
The paper relies on this without support.
Providing a rationale for why breathlessness should be amenable to intervention can be helpful for clinicians.
“Providing a rationale, not just for the presence of the symptom, but also for why it should be amenable to intervention, can be helpful for clinicians too.”
Self-check
Percentages, sums and reported differences re-computed from the paper’s own numbers.
Each contradiction between two passages listed here was confirmed by an independent check.
Rated minor: it would not touch a result — a value no result rests on, a p-value that stays on the same side of the significance level, or a conflict that is clerical, resolved elsewhere in the paper, or outside its own findings.
In the paper
§ The Breathing, Thinking, Functioning clinical model: a proposal to facilitate evidence-based breathlessness management in chronic respiratory disease > Understanding the complexity > Neurophysiology of breathlessness
“Uronis et al. 200816, 44 | Systematic review and meta-analysis of five studies evaluating oxygen for dyspnoea in mildly- or non-hypoxaemic cancer patients”
§ The Breathing, Thinking, Functioning clinical model: a proposal to facilitate evidence-based breathlessness management in chronic respiratory disease > References
“44. Uronis H McCrory D Samsa G Currow D Abernethy A Symptomatic oxygen for non-hypoxaemic chronic obstructive pulmonary disease Cochrane Database Syst. Rev. 2011 6 CD006429 21678356”
Cited works that were retracted
Works this paper cites that were later retracted, from the retraction notices publishers deposit. Major when the notice came out before this paper was published.
Rated major: it would touch a result — a value a result rests on, reported and recomputed p-values on opposite sides of the significance level, two passages that conflict with no sign which is right, or a cited work retracted before this paper was published.
In the paper
“Bausewein C Booth S Gysels M Higginson I Non-pharmacological interventions for breathlessness in advanced stages of malignant and non-malignant diseases Cochrane Database Syst. Rev. 2008 2 CD005623 18425927”
Cited work 10.1002/14651858.cd005623.pub2 · retracted 2013-11-22 · notice 10.1002/14651858.cd005623.pub3 · this paper published 2017-04-21
A note, not an issue: for example, a cited work that was retracted only after this paper was published, which its authors could not have known.
Cited work 10.1002/14651858.cd005623.pub3 · retraction date not known · this paper published 2017-04-21
Citations
Cites
2 retracted
Bausewein, C., Booth, S., Gysels, M., & Higginson, I. J. (2013) · Cochrane Database of Systematic Reviews · doi:10.1002/14651858.cd005623.pub3 · Cited by 287
Self-citationRetractedBausewein, C., Booth, S., Gysels, M., & Higginson, I. J. (2008) · Cochrane Database of Systematic Reviews · doi:10.1002/14651858.cd005623.pub2 · Cited by 210
Self-citationRetracted‘Small Changes' to Diet and Physical Activity Behaviors for Weight Management
Hills, A. P., Byrne, N. M., Lindstrom, R. C., & Hill, J. O. (2013) · Obesity Facts · doi:10.1159/000345030 · Cited by 9,526
Pulmonary rehabilitation for chronic obstructive pulmonary disease
McCarthy, B., Casey, D., Devane, D., Murphy, K., Murphy, E., & Lacasse, Y. (2015) · Cochrane Database of Systematic Reviews · doi:10.1002/14651858.cd003793.pub3 · Cited by 2,643
Obesity and the Environment: Where Do We Go from Here?
Hill, J. O., Wyatt, H. R., Reed, G. W., & Peters, J. C. (2003) · Science · doi:10.1126/science.1079857 · Cited by 2,180 · cited 1×
“The ‘small changes approach’, accepted as a particularly effective and feasible way of achieving behavioural change, develops the potential to generate rapid and large gains.(39) Enhancing selfefficacy is a particularly effective way to support selfmanagement.”
BackgroundCharacterisation of COPD heterogeneity in the ECLIPSE cohort
the Evaluation of COPD Longitudinally to Identify Predictive Surrogate Endpoints (ECLIPSE) investigators, Agusti, A., Calverley, P. M., Celli, B., Coxson, H. O., Edwards, L. D., Lomas, D. A., MacNee, W., Miller, B. E., Rennard, S., et al. (2010) · Respiratory Research · doi:10.1186/1465-9921-11-122 · Cited by 1,157
Higginson, I. J., Bausewein, C., Reilly, C. C., Gao, W., Gysels, M., Dzingina, M., McCrone, P., Booth, S., Jolley, C. J., & Moxham, J. (2014) · The Lancet Respiratory Medicine · doi:10.1016/s2213-2600(14)70226-7 · Cited by 605
Self-citationSelf management for patients with chronic obstructive pulmonary disease
Zwerink, M., Brusse-Keizer, M., van der Valk, P. D., Zielhuis, G. A., Monninkhof, E. M., van der Palen, J., Frith, P. A., & Effing, T. (2014) · Cochrane Database of Systematic Reviews · doi:10.1002/14651858.cd002990.pub3 · Cited by 572
Abernethy, A. P., Currow, D. C., Frith, P., Fazekas, B. S., McHugh, A., & Bui, C. (2003) · BMJ · doi:10.1136/bmj.327.7414.523 · Cited by 521
Abernethy, A. P., McDonald, C. F., Frith, P. A., Clark, K., Herndon, J. E., Marcello, J. E., Young, I. H., Bull, J., Wilcock, A., Booth, S., et al. (2010) · The Lancet · doi:10.1016/s0140-6736(10)61115-4 · Cited by 494
Self-citation
Cited by
Sorted by citations
The therapy of idiopathic pulmonary fibrosis: what is next?
Somogyi, V., Chaudhuri, N., Torrisi, S. E., Kahn, N. C., Müller, V., & Kreuter, M. (2019) · European Respiratory Review · doi:10.1183/16000617.0021-2019 · Cited by 276
Maddocks, M. M., Lovell, N., Booth, S., Man, W. D., & Higginson, I. J. (2017) · The Lancet · doi:10.1016/s0140-6736(17)32127-x · Cited by 238
“The following may have value for the mobile patient: increasing physical activity by means of activity pacing, mobility aids, and an individual exercise plan; use of the hand held fan or cold water spray to palliate the sensation of breathlessness;(57) breathing retraining;(58) and support for carers including educati…”
Self-citationSingh, S., Baldwin, M. M., Daynes, E., Evans, R. A., Greening, N. J., Jenkins, G. R., Lone, N., McAuley, H., Mehta, P., Newman, J. V., et al. (2023) · The Lancet Respiratory Medicine · doi:10.1016/s2213-2600(23)00159-5 · Cited by 208
Brighton, L. J., Miller, S., Farquhar, M. C., Booth, S., Yi, D., Gao, W., Bajwah, S., Man, W. D., Higginson, I. J., & Maddocks, M. M. (2018) · Thorax · doi:10.1136/thoraxjnl-2018-211589 · Cited by 153
Self-citationLiving with breathlessness: a systematic literature review and qualitative synthesis
Hutchinson, A., Barclay-Klingle, N., Galvin, K., & Johnson, M. J. (2018) · European Respiratory Journal · doi:10.1183/13993003.01477-2017 · Cited by 162
“33 Education and training for clinicians in primary and secondary care in the assessment of Breathing Space and the management of breathlessness, such as that provided around the Breathing, Thinking Functioning model,(142) could improve patients’ access to breathlessness-targeted treatments delivered by the multidisci…”
Background
Metadata
- Authors
- Spathis, A., Booth, S., Moffat, C., Hurst, R., Ryan, R., Chin, C., & Burkin, J.
- Affiliations
- University of Cambridge (GB)
- Cambridge University Hospitals NHS Foundation Trust (GB)
- Corresponding author
- Spathis, Anna
- Venue
- npj Primary Care Respiratory Medicine
- Published
- 2017-04-21
- Volume
- 27
- Issue
- 1
- Pages
- 27-27
- ISSN
- 2055-1010 (ISSN-L)
- PMC
- PMC5435098
- OpenAlex
- W2605479401
- Semantic Scholar
- ce556c7bb94ab4f38c2b81f1f3f28f4cb2d6a07d
- Cited by
- 226
- References
- 47
- Citations by year
- 2026: 15 · 2025: 29 · 2024: 28 · 2023: 37 · 2022: 25 · 2021: 24 · 2020: 23 · 2019: 22 · 2018: 15 · 2017: 8
- FWCI
- 13.86
- Type
- journal article
- Language
- en
- Open access
- gold
- doi.org
- Locations
- npj Primary Care Respiratory Medicine (publishedVersion, cc-by)
- PubMed (publishedVersion)
- Europe PMC (PubMed Central) (submittedVersion, cc-by)
- PubMed Central (submittedVersion, cc-by)
- DOAJ (DOAJ: Directory of Open Access Journals) (submittedVersion, cc-by-sa)
- Apollo (University of Cambridge) (submittedVersion, cc-by)
- Apollo (cc-by)
- Topics
- Health Sciences › Medicine › Pulmonary and Respiratory Medicine › Chronic Obstructive Pulmonary Disease (COPD) Research
- Health Sciences › Medicine › Pulmonary and Respiratory Medicine › Respiratory and Cough-Related Research
- Health Sciences › Medicine › Pulmonary and Respiratory Medicine › Asthma and respiratory diseases
- Keywords
- dyspnea, chronic respiratory disease, refractory breathlessness, symptom management, non-pharmacological treatment, clinical model, patient engagement, clinician engagement, evidence-based care
- MeSH terms
- Self-Management, Chronic Disease, Delivery of Health Care, Dyspnea, Heart Diseases, Humans, Respiratory Tract Diseases, Evidence-Based Medicine, Pulmonary Disease, Chronic Obstructive
About these checks
Registry, retraction, Cites and statistics results are computed, not judged, with one exception: a printed reference that no index lists is read once by a model before it counts as a citation error. Claims are extracted by a model and kept only when their quote appears verbatim in the text; each cited source is then checked, with a model’s help, for whether it says what the claim relies on. Those verdicts can be wrong — read the claim’s quote and the cited source before relying on one.
A language model drew the claims from the paper on 2026-10-17, under version 3 of the claim definition (model deepseek-v4.1-flash, prompt extract-v3).
A second model labelled each claim on 2026-10-17 (model jev-1.13-20260917, definition revision gold-guideline-v0.2).
Cited sources are checked with a language model’s help (gpt-6-sol).
Statistics and arithmetic are recomputed, not judged.
Confidence bands are shown only for fields calibrated on our annotated test set. None is calibrated yet, so no band is shown.
What counts as a claim ›How we measure confidence ›How we check this ›
Are you an author, or do you see a problem with this page? Request a review
