

Graphical Tools for Network Meta-Analysis in STATA
Open accessThe DOI matches its Crossref record; 51 of the 51 references it cites were found in a registry or an index.
Abstract
Network meta-analysis synthesizes direct and indirect evidence in a network of trials that compare multiple interventions and has the potential to rank the competing treatments according to the studied outcome. Despite its usefulness network meta-analysis is often criticized for its complexity and for being accessible only to researchers with strong statistical and computational skills. The evaluation of the underlying model assumptions, the statistical technicalities and presentation of the results in a concise and understandable way are all challenging aspects in the network meta-analysis methodology. In this paper we aim to make the methodology accessible to non-statisticians by presenting and explaining a series of graphical tools via worked examples. To this end, we provide a set of STATA routines that can be easily employed to present the evidence base, evaluate the assumptions, fit the network meta-analysis model and interpret its results.
Overview
The claims and statistics of this paper haven’t been checked yet.
Free: it reads the open-access text and checks the first 5 claims that cite a source we can check. Create a free account to check every claim.
Integrity signals
Registry
Cites
Statistics
Figures





Verification
Claims the paper makes
The claims and statistics of this paper haven’t been checked yet.
Free: it reads the open-access text and checks the first 5 claims that cite a source we can check. Create a free account to check every claim.
Claims other papers make about this one
Each is checked against this paper’s own text: does it say what the citing paper says it does?
The source backs part of the claim, not all of it — or backs it for a different population, condition or comparison.
In the citing paper
“We used comparisonadjusted funnel plots to assess publi cation bias.23”
From Comparative efficacy and acceptability of antidepressants, psychotherapies, and their combination for acute treatment of children and adolescents with depressive disorder: a systematic review and network meta-analysis (2020) · cites this paper as [23]
Experimental — accuracy not yet measuredThe source backs part of the claim, not all of it — or backs it for a different population, condition or comparison.
In the citing paper
“The statistical examination of the transitivity assumption was conducted using tests of local and global inconsistency 20 .”
From Psychotherapies for depression: a network meta-analysis covering efficacy, acceptability and long-term outcomes of all main treatment types (2021) · cites this paper as [20]
Experimental — accuracy not yet measuredThe source backs part of the claim, not all of it — or backs it for a different population, condition or comparison.
In the citing paper
“Small-study effects and potential publication bias were investigated by visual inspection of contour-enhanced, comparison-adjusted funnel plots, and an Egger's test.[26][27][28]”
From Comparative efficacy and tolerability of pharmacological interventions for acute bipolar depression in adults: a systematic review and network meta-analysis (2023) · cites this paper as [27]
Experimental — accuracy not yet measuredThe cited source says what the claim attributes to it.
In the citing paper
“We used comparison-adjusted funnel plots to investigate whether results in imprecise trials differ from those in more precise trials.17”
The cited source says what the claim attributes to it.
In the citing paper
“For each outcome with ≥10 studies, the comparison-adjusted funnel plot was used to assess small-study effects,17 where the overall treatment effect for each comparison was estimated under the fixed-effect meta-analysis model.”
2 more claims about this paper
Create a free account to see every claim other papers make about this one.
Self-check
Percentages, sums and reported differences re-computed from the paper’s own numbers.
The self-check needs the paper’s full text.
Citations
Cites
Bias in meta-analysis detected by a simple, graphical test
Egger, M., Smith, G. D., Schneider, M., & Minder, C. (1997) · BMJ · doi:10.1136/bmj.315.7109.629 · Cited by 56,722 · cited 1×
“It is the most common tool used to assess the presence of small-study effects in a meta-analysis [34].”
MethodMeta-analysis in clinical trials
DerSimonian, R., & Laird, N. (1986) · Controlled Clinical Trials · doi:10.1016/0197-2456(86)90046-2 · Cited by 39,552 · cited 1×
“Method of moments and restricted maximum likelihood are those most commonly used and have been implemented in STATA’s metan command along with an empirical Bayes method [32,33].”
MethodThe Handbook of Research Synthesis and Meta-Analysis
(2019) · doi:10.7758/9781610448864 · Cited by 4,553 · cited 1×
“freedom (in NMA we suggest this is set to number of studies – number of comparisons with data – 1 [41]) and m̂ is the metaanalysis summary effect.”
BackgroundSalanti, G., Ades, A. E., & Ioannidis, J. P. A. (2011) · Journal of Clinical Epidemiology · doi:10.1016/j.jclinepi.2010.03.016 · Cited by 3,766 · cited 4×
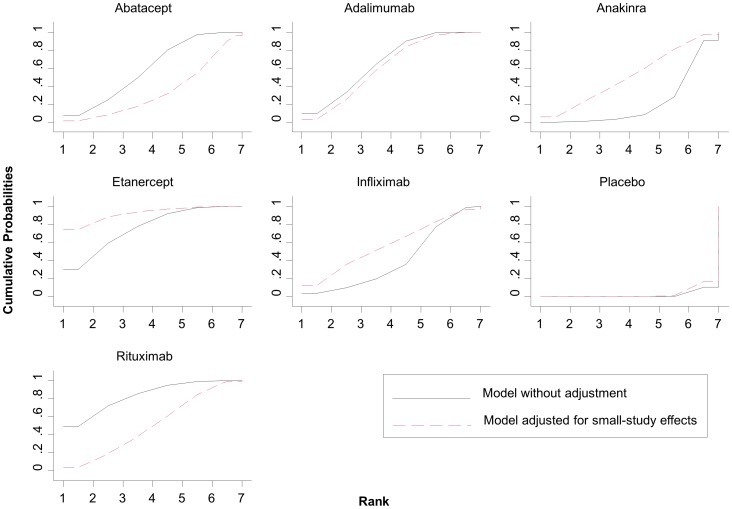
“So-called rankograms and cumulative ranking probability plots have been suggested as a reliable and comprehensive graphical way to present ranking probabilities and their uncertainty [2].”
BackgroundMethodInfluentialSelf-citationInterpretation of random effects meta-analyses
Riley, R. D., Higgins, J. P. T., & Deeks, J. J. (2011) · BMJ · doi:10.1136/bmj.d549 · Cited by 2,884 · cited 2×
“and predictive ranking probabilities (the probability that each treatment will be placed in each rank in a future study [39,40]) can be estimated with the suboption predict.”
BackgroundSelf-citationA Re-Evaluation of Random-Effects Meta-Analysis
Higgins, J. P. T., Thompson, S. G., & Spiegelhalter, D. J. (2009) · Journal of the Royal Statistical Society Series A: Statistics in Society · doi:10.1111/j.1467-985x.2008.00552.x · Cited by 2,569 · cited 2×
“and predictive ranking probabilities (the probability that each treatment will be placed in each rank in a future study [39,40]) can be estimated with the suboption predict.”
BackgroundSelf-citationChecking consistency in mixed treatment comparison meta-analysis
Dias, S., Welton, N. J., Caldwell, D. M., & Ades, A. E. (2010) · Statistics in Medicine · doi:10.1002/sim.3767 · Cited by 2,521 · cited 1×
“Several approaches have been developed to deal with inconsistency in a network of interventions [26–29].”
BackgroundCombination of direct and indirect evidence in mixed treatment comparisons
Lu, G., & Ades, A. E. (2004) · Statistics in Medicine · doi:10.1002/sim.1875 · Cited by 2,166 · cited 1×
“Thus, in the presence of multi-arm trials, researchers have often preferred to perform NMA in a Bayesian framework that offers more flexibility [21,22].”
BackgroundConsistency and inconsistency in network meta-analysis: concepts and models for multi-arm studies
Higgins, J. P. T., Jackson, D., Barrett, J. K., Lu, G., Ades, A. E., & White, I. R. (2012) · Research Synthesis Methods · doi:10.1002/jrsm.1044 · Cited by 2,098 · cited 1×
“recently described NMA as a multivariate meta-analysis model [23,24].”
MethodSelf-citationBucher, H. C., Guyatt, G. H., Griffith, L. E., & Walter, S. D. (1997) · Journal of Clinical Epidemiology · doi:10.1016/s0895-4356(97)00049-8 · Cited by 2,052 · cited 1×
“The integration of direct evidence (from studies directly comparing interventions) with indirect evidence (information about two treatments derived via a common comparator) increases the precision in the estimates and produces a relative ranking of all treatments for the studied outcome [1,2].”
Background
Cited by
Items 201–300 of 1,012
Mok, C. W., Tan, S.-M., Zheng, Q., & Shi, L. (2019) · BJS Open · doi:10.1002/bjs5.50157 · Cited by 115
Surgical procedures in the pilonidal sinus disease: a systematic review and network meta-analysis
Bi, S., Sun, K., Chen, S., & Gu, J. (2020) · Scientific Reports · doi:10.1038/s41598-020-70641-7 · Cited by 106
Wang, Y., Flórez, I. D., Morgan, R. L., Foroutan, F., Chang, Y., Crandon, H. N., Zeraatkar, D., Bała, M. M., Mao, R. Q., Tao, B. K.-L., et al. (2023) · Archives of Pediatrics and Adolescent Medicine · doi:10.1001/jamapediatrics.2023.3849 · Cited by 114
Mahil, S. K., Ezejimofor, M. C., Exton, L. S., Manounah, L., Burden, A. D., Coates, L. C., de Brito, M., McGuire, A., Murphy, R., Owen, C., et al. (2020) · British Journal of Dermatology · doi:10.1111/bjd.19325 · Cited by 115
Wang, Y., Ye, Z., Ge, L., Siemieniuk, R. A. C., Wang, X., Wang, Y., Hou, L., Ma, Z., Agoritsas, T., Vandvik, P. O., et al. (2020) · BMJ · doi:10.1136/bmj.l6744 · Cited by 112
The optimal target for acute glycemic control in critically ill patients: A network meta-analysis.
Yatabe, T., Inoue, S., Sakaguchi, M., & Egi, M. (2017) · Intensive Care Medicine · doi:10.1007/s00134-016-4558-2 · Cited by 95
“The integration of direct evidence with indirect evidence increases the precision of the estimates and produces a relative ranking of all treatments for the studied outcome [15].”
BackgroundMultiple treatment and indirect treatment comparisons: An overview of network meta-analysis
Bhatnagar, N., Lakshmi, P. V. M., & Jeyashree, K. (2014) · Perspectives in Clinical Research · doi:10.4103/2229-3485.140550 · Cited by 100
“Corp which has made the methodology of NMA accessible to the non-statisticians.[15] IE”
MethodWatt, J. A., & Giovane, C. D. (2021) · Methods in molecular biology · doi:10.1007/978-1-0716-1566-9_12 · Cited by 110
Jinatongthai, P., Kongwatcharapong, J., Foo, C. Y., Phrommintikul, A., Nathisuwan, S., Thakkinstian, A., Reid, C. M., & Chaiyakunapruk, N. (2017) · The Lancet · doi:10.1016/s0140-6736(17)31441-1 · Cited by 101
Resolve conflicting rankings of outcomes in network meta‐analysis: Partial ordering of treatments
Rücker, G., & Schwarzer, G. (2017) · Research Synthesis Methods · doi:10.1002/jrsm.1270 · Cited by 94
“We found 5 levels of treatments, and these are in decreasing order: (1) CRT-AC, (2) IC-CRT and CRT, (3) IC-RT and IC-RT-AC, (4) RT-AC, and (5) RT alone.”
MethodManagement of people with early- or very early-stage hepatocellular carcinoma
Majumdar, A., Roccarina, D., Thorburn, D., Davidson, B. R., Tsochatzis, E. A., & Gurusamy, K. S. (2017) · Cochrane Database of Systematic Reviews · doi:10.1002/14651858.cd011650.pub2 · Cited by 105
Zhang, Y. S., Weng, W. Y., Xie, B. C., Meng, Y., Hao, Y. H., Liang, Y. M., & Zhou, Z. K. (2018) · Osteoporosis International · doi:10.1007/s00198-018-4649-8 · Cited by 93
Palmer, S. C., Tunnicliffe, D. J., Singh‐Grewal, D., Mavridis, D., Tonelli, M. A., Johnson, D. W., Craig, J. C., Tong, A., & Strippoli, G. F. (2017) · American Journal of Kidney Diseases · doi:10.1053/j.ajkd.2016.12.008 · Cited by 95
Self-citationDrug Combinations Against Soil-Transmitted Helminth Infections
(2019) · Advances in Parasitology · doi:10.1016/bs.apar.2018.08.002 · Cited by 92
Mo, J., Li, J., Yang, Z., Liu, Z., & Feng, J. (2017) · Annals of Clinical and Translational Neurology · doi:10.1002/acn3.469 · Cited by 90
“Network meta-analysis (NMA) is a methodology that can synthesize direct and indirect evidence in a network of trials and rank multiple interventions according to the study outcomes.(17) The Frequentist method considers all indirect and direct evidence to determine the relative treatment effects between all interventio…”
MethodFarag, H., Yunusa, I. U., Goswami, H. H., Sultan, I., Doucette, J. A., & Eguale, T. (2022) · JAMA Network Open · doi:10.1001/jamanetworkopen.2022.12939 · Cited by 115
Cheng, P., Tan, L., Ning, P., Li, L., Gao, Y., Wu, Y., Schwebel, D. C., Chu, H., Yin, H., & Hu, G. (2018) · International Journal of Environmental Research and Public Health · doi:10.3390/ijerph15030498 · Cited by 117
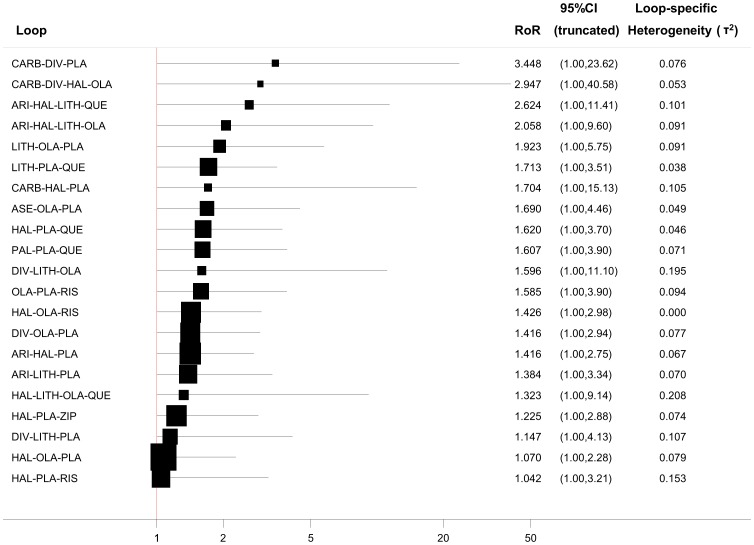
“A 95% CrI of a loop excluding zero indicates inconsistency between direct and indirect evidence [29,35].”
BackgroundMethodZaccardi, F., Htike, Z. Z., Webb, D. R., Khunti, K., & Davies, M. J. (2016) · Annals of Internal Medicine · doi:10.7326/m15-1432 · Cited by 91
Dulai, P. S., Singh, S., Marquez, E. O., Khera, R., Prokop, L. J., Limburg, P. J., Gupta, S. N., & Murad, M. H. (2016) · BMJ · doi:10.1136/bmj.i6188 · Cited by 100
Liang, K., Li, H., Bu, X., Li, X., Cao, L., Liu, J., Gao, Y., Li, B., Qiu, C., Bao, W., et al. (2021) · Translational Psychiatry · doi:10.1038/s41398-021-01453-0 · Cited by 90
Khera, R., Pandey, A., Chandar, A. K., Murad, M. H., Prokop, L. J., Neeland, I. J., Berry, J. D., Camilleri, M., & Singh, S. (2018) · Gastroenterology · doi:10.1053/j.gastro.2017.12.024 · Cited by 90
Hennessy, E. A., Tanner‐Smith, E. E., Mavridis, D., & Grant, S. (2019) · Prevention Science · doi:10.1007/s11121-018-0960-z · Cited by 100
Self-citationZhu, R., Kan, S.-L., Ning, G., Chen, L., Cao, Z., Jiang, Z., Zhang, X.-L., & Hu, W. F. (2019) · Osteoporosis International · doi:10.1007/s00198-018-4804-2 · Cited by 102
Chawla, N., Anothaisintawee, T., Charoenrungrueangchai, K., Thaipisuttikul, P., McKay, G. J., Attia, J. R., & Thakkinstian, A. (2022) · BMJ · doi:10.1136/bmj-2021-066084 · Cited by 111
Sandeep, B., Huang, X., Li, Y., Xiong, D., Zhu, B., & Xiao, Z. (2022) · International Journal of Surgery · doi:10.1016/j.ijsu.2022.106840 · Cited by 101
Mavridis, D., White, I. R., Higgins, J. P. T., Cipriani, A., & Salanti, G. (2015) · Statistics in Medicine · doi:10.1002/sim.6365 · Cited by 90
“Data are shown in Table III, and Figure 1 presents the network plot [23].”
BackgroundSelf-citationNevill, C. R., Cooper, N. J., & Sutton, A. J. (2023) · Journal of Clinical Epidemiology · doi:10.1016/j.jclinepi.2023.02.016 · Cited by 104
Wei, D., Goost, H., Lin, X., Burger, C., Paul, C., Wang, Z., Kong, F.-L., Welle, K., Jiang, Z., & Kabir, K. (2015) · British Journal of Sports Medicine · doi:10.1136/bjsports-2014-094387 · Cited by 92
Wade, R. G., Griffiths, T. T., Flather, R., Burr, N. E., Teo, M., & Bourke, G. (2020) · JAMA Network Open · doi:10.1001/jamanetworkopen.2020.24352 · Cited by 91
Jericho, B., Luo, A., & Berle, D. (2021) · Acta Psychiatrica Scandinavica · doi:10.1111/acps.13366 · Cited by 105
Canullo, L., FABBRO, M. D., Khijmatgar, S., Panda, S., Ravidà, A., Tommasato, G., Sculean, A., & Pesce, P. (2021) · Clinical Oral Investigations · doi:10.1007/s00784-021-04248-1 · Cited by 94
“However, the differences in ranking normally pertain only to the treatments that are close in rank [31].”
BackgroundZhang, R. S., Maqsood, M. H., Sharp, A. S. P., Postelnicu, R., Sethi, S. S., GRECO, A. A., Alviar, C. L., & Bangalore, S. (2023) · JACC: Cardiovascular Interventions · doi:10.1016/j.jcin.2023.07.042 · Cited by 98
Pillay, J., Gaudet, L., Saba, S., Vandermeer, B., Ashiq, A. R., Wingert, A., & Hartling, L. (2024) · Systematic Reviews · doi:10.1186/s13643-024-02681-3 · Cited by 127
Giacoppo, D., Gargiulo, G., Buccheri, S., Aruta, P., Byrne, R. A., Cassese, S., Dangas, G., Kastrati, A., Mehran, R., Tamburino, C., et al. (2017) · Circulation: Cardiovascular Interventions · doi:10.1161/circinterventions.116.004383 · Cited by 86
“PREVENT NAC NaHCO3 382 (189;193) 27 (10;17) 22 (9;13) 25 (9;16) ― 24-48hours 1.”
InfluentialFlorez, I. D., Veroniki, A.-A., Al Khalifah, R., Yepes-Nuñez, J. J., Sierra, J. M., Vernooij, R. W. M., Acosta-Reyes, J., Granados, C. M., Pérez-Gaxiola, G., Cuello-Garcia, C., et al. (2018) · PLOS ONE · doi:10.1371/journal.pone.0207701 · Cited by 87
Schwingshackl, L., Krause, M., Schmucker, C., Hoffmann, G., Rücker, G., & Meerpohl, J. J. (2019) · Nutrition, Metabolism and Cardiovascular Diseases · doi:10.1016/j.numecd.2019.07.001 · Cited by 85
Datta, S., Shah, L., Gilman, R. H., & Evans, C. A. (2017) · The Lancet Global Health · doi:10.1016/s2214-109x(17)30201-2 · Cited by 107
Network Meta-Analysis of Novel Glucose-Lowering Drugs on Risk of Acute Kidney Injury
Zhao, M., Sun, S., Huang, Z., Wang, T., & Tang, H. (2021) · Clinical Journal of the American Society of Nephrology · doi:10.2215/cjn.11220720 · Cited by 82
Snetselaar, L., Cheek, J. J., Fox, S. S., Healy, H. S., Schweizer, M. L., Bao, W., Kamholz, J. A., & Titcomb, T. J. (2022) · Neurology · doi:10.1212/wnl.0000000000201371 · Cited by 94
“We used the contribution matrix to identify the direct comparisons with greater influence in the network relative effects.(15,16) Transitivity is the fundamental assumption of indirect comparisons and NMA, and its violation threatens the validity of findings obtained from a network of studies.”
MethodDin, S., Selinger, C. P., Black, C. J., & Ford, A. C. (2022) · Alimentary Pharmacology & Therapeutics · doi:10.1111/apt.17379 · Cited by 92
Effects of Antidiabetic Drugs on Muscle Mass in Type 2 Diabetes Mellitus
Ida, S., Kaneko, R., Imataka, K., Okubo, K., Shirakura, Y., Azuma, K., Fujiwara, R., & Murata, K. (2021) · Current Diabetes Reviews · doi:10.2174/1573399816666200705210006 · Cited by 85
Al‐Moraissi, E. A., Conti, P. C. R., Alyahya, A., Alkebsi, K., Elsharkawy, A., & Christidis, N. (2021) · Oral and Maxillofacial Surgery · doi:10.1007/s10006-021-01009-y · Cited by 104
Weng, Q., Goh, S.-L., Wu, J., Persson, M. S. M., Wei, J., Sarmanova, A., Li, X., Hall, M., Doherty, M., Jiang, T., et al. (2023) · British Journal of Sports Medicine · doi:10.1136/bjsports-2022-105898 · Cited by 84
Chen, T., Traynor, V., Wang, A., Shih, C., Tu, M.-C., Chuang, C.-H., Chiu, H., & Chang, H. (2022) · International Journal of Nursing Studies · doi:10.1016/j.ijnurstu.2022.104239 · Cited by 106
Castellini, G., Pillastrini, P., Vanti, C., Bargeri, S., Giagio, S., Bordignon, E., Fasciani, F., Marzioni, F., Innocenti, T., Chiarotto, A., et al. (2022) · Journal of physiotherapy · doi:10.1016/j.jphys.2022.09.007 · Cited by 104
Zhou, J., Ma, X., Wang, T., & Zhai, S. (2016) · Osteoporosis International · doi:10.1007/s00198-016-3654-z · Cited by 88
Han, S.-B., Seo, I.-W., & Shin, Y.-S. (2020) · Arthroscopy The Journal of Arthroscopic and Related Surgery · doi:10.1016/j.arthro.2020.03.041 · Cited by 92
Palmer, S. C., Mavridis, D., Johnson, D. W., Tonelli, M. A., Ruospo, M., & Strippoli, G. F. (2020) · American Journal of Kidney Diseases · doi:10.1053/j.ajkd.2020.02.439 · Cited by 93
Self-citationOstuzzi, G., Bertolini, F., Giovane, C. D., Tedeschi, F., Bovo, C., Gastaldon, C., Nosè, M., Ogheri, F., Papola, D., Purgato, M., et al. (2021) · American Journal of Psychiatry · doi:10.1176/appi.ajp.2020.20071120 · Cited by 93
Liu, Z., Liao, Q., Wen, H., & Zhang, Y. (2021) · Autoimmunity Reviews · doi:10.1016/j.autrev.2021.102826 · Cited by 92
Papola, D., Ostuzzi, G., Tedeschi, F., Gastaldon, C., Purgato, M., Del Giovane, C., Pompoli, A., Pauley, D., Karyotaki, E., Sijbrandij, M., et al. (2023) · Psychological Medicine · doi:10.1017/s0033291722003683 · Cited by 77
“…bias by visually inspecting the funnel plot, testing for asymmetry with the Egger ’ s regression test (Egger, Davey Smith, Schneider, & Minder, 1997; Sterne et al., 2011), and investigated possible reasons for funnel plot asymmetry (Chaimani, Higgins, Mavridis, Spyridonos, & Salanti, 2013).”
Setkowski, K., Palantza, C., van Ballegooijen, W., Gilissen, R., Oud, M., Cristea, I. A., Noma, H., Furukawa, T. A., Arntz, A. R., van Balkom, A. J. L. M., et al. (2023) · Psychological Medicine · doi:10.1017/s0033291723000685 · Cited by 98
Hussein, H., Zaccardi, F., Khunti, K., Davies, M. J., Patsko, E., Dhalwani, N. N., Kloecker, D. E., Ioannidou, E., & Gray, L. J. (2020) · Diabetes, Obesity and Metabolism · doi:10.1111/dom.14008 · Cited by 82
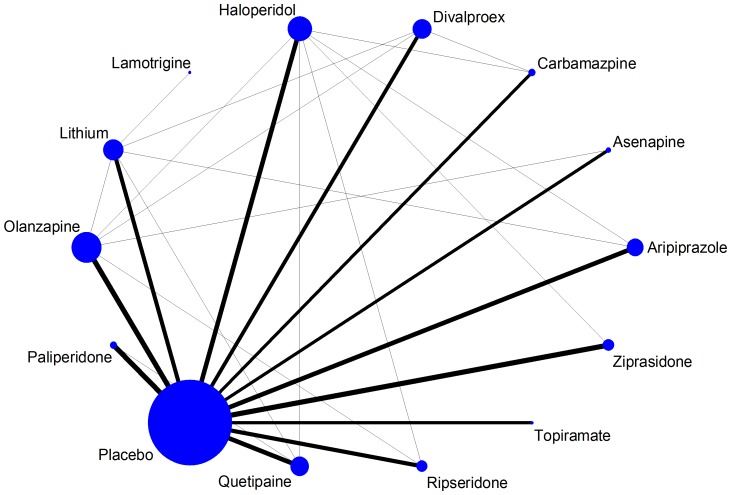
“Network plots were drawn to present the network of direct evidence available.(23) Outcomes with sparse networks (i.”
MethodLandry, E. C., Sandoval, X. C. R., Simeone, C. N., Tidball, G., Lea, J., & Westerberg, B. D. (2020) · Otology & Neurotology · doi:10.1097/mao.0000000000002472 · Cited by 82
“These results must be interpreted with caution given that the CIs negate statistical significance between most treatments (46).”
BackgroundKim, W. H., Hur, M. S., Park, S.-K., Yoo, S., Lim, T. Y., Yoon, H., Kim, J., & Bahk, J.-H. (2018) · International Journal of Obstetric Anesthesia · doi:10.1016/j.ijoa.2018.09.012 · Cited by 106
Pease, A., Lo, C., Earnest, A., Kiriakova, V., Liew, D., & Zoungas, S. (2020) · Diabetes Technology & Therapeutics · doi:10.1089/dia.2019.0417 · Cited by 83
“Network heterogeneity was considerable for non-severe hypoglycemia ( t 2 = 0.14, I 2 [95% CI] = 90% [74– 97]), and moderate to substantial for QoL ( t 2 = 0.08, I 2 [95% CI] = 54% [27–80]).”
InfluentialHenry, J. H., Amoo, M., Taylor, J., & O’Brien, D. P. (2021) · Neurosurgery · doi:10.1093/neuros/nyab180 · Cited by 96
Yang, Y., Wang, G., Zhang, S., Wang, H., Zhou, W.-S., Ren, F.-F., Liang, H., Wu, D., Ji, X., Hashimoto, M., et al. (2022) · BMC Geriatrics · doi:10.1186/s12877-022-03510-9 · Cited by 98
“We used comparison adjusted funnel plot for the primary outcome to investigate the presence of small study effect [28].”
MethodIs providing uncertainty intervals in treatment ranking helpful in a network meta-analysis?
Veroniki, A. A., Straus, S. E., Rücker, G., & Tricco, A. C. (2018) · Journal of Clinical Epidemiology · doi:10.1016/j.jclinepi.2018.02.009 · Cited by 87
Tang, H., Li, G., Zhao, Y., Wang, F., Gower, E. W., Shi, L., & Wang, T. (2018) · Diabetes, Obesity and Metabolism · doi:10.1111/dom.13232 · Cited by 78
“For indirect and mixed comparisons, a network meta-analysis with a random-effects model using the “mvmeta” command and programmed STATA routines was used to calculate ORs and 95% CIs between different interventions.(17,18) For zero-event RCTs, a 0.”
MethodYan, L., Ge, L., Dong, S., Saluja, K., Li, D., Reddy, K. S., Wang, Q., Yao, L., Li, J. J., da Costa, B. R., et al. (2023) · JAMA Network Open · doi:10.1001/jamanetworkopen.2022.53942 · Cited by 99
The treatment of post-hysterectomy vaginal vault prolapse: a systematic review and meta-analysis
Coolen, A.-L. W. M., Bui, B. N., Dietz, V., Wang, R., van Montfoort, A. P. A., Mol, B. W. J., Roovers, J.-P. W. R., & Bongers, M. Y. (2017) · International Urogynecology Journal · doi:10.1007/s00192-017-3493-2 · Cited by 80
“We created a network plot to illustrate the geometry of the network of the treatments included by using Bmvmeta^ package in Stata software (version 12.0; Stata Corp, College Station, TX, USA) [15].”
InfluentialSekercioglu, N., Thabane, L., Martinez, J. P. D., NESRALLAH, G. E., Longo, C. J., Busse, J. W., Akhtar‐Danesh, N., Agarwal, A., Khalifah, R. A. A., Iorio, A., et al. (2016) · PLoS ONE · doi:10.1371/journal.pone.0156891 · Cited by 88
“We summarized the overall network heterogeneity using the global test [28].”
BackgroundMethodCai, J., Zhao, C., Du, Y., Zhang, Y., Zhao, M., & Zhao, Q. (2018) · United European Gastroenterology Journal · doi:10.1177/2050640617736987 · Cited by 72
“Relative ranks were accessed based on surface under the cumulative ranking curve (SUCRA),(27) and the resultant rankings were presented graphically.(25) Network inconsistency was appraised by comparing the indirect and direct evidence using the design-by-treatment interaction model (Higgins model),(28) and the node-sp…”
MethodDevoe, D. J., Farris, M. S., Townes, P., & Addington, J. (2019) · Early Intervention in Psychiatry · doi:10.1111/eip.12677 · Cited by 80
“Network comparison-adjusted funnel plots (Chaimani et al., 2013) were used to evaluate publication bias by arrangement of interventions as active treatment vs controls.”
BackgroundMethodInfluentialSiemieniuk, R. A., Bartoszko, J. J., Díaz Martinez, J. P., Kum, E., Qasim, A., Zeraatkar, D., Izcovich, A., Mangala, S., Ge, L., Han, M. A., et al. (2021) · BMJ · doi:10.1136/bmj.n2231 · Cited by 79
Percutaneous Coronary Interventions for the Treatment of Stenoses in Small Coronary Arteries
Siontis, G. C. M., Piccolo, R., Praz, F., Valgimigli, M., Räber, L., Mavridis, D., Jüni, P., & Windecker, S. (2016) · JACC: Cardiovascular Interventions · doi:10.1016/j.jcin.2016.03.025 · Cited by 81
“0 63 12; 62 10 49 (67); 52 (73) 9 (12); 10 (14) 31 (42); 33 (47) 55 (74); 48 (68) 15 (20); 10 (14) 31 (42); 32 (45) 58 (74); 56 (79)”
MethodInfluentialSelf-citationDevoe, D. J., Peterson, A., & Addington, J. (2018) · Schizophrenia Bulletin · doi:10.1093/schbul/sbx139 · Cited by 80
Kossmeier, M., Tran, U. S., & Voracek, M. (2020) · BMC Medical Research Methodology · doi:10.1186/s12874-020-0911-9 · Cited by 91
Bellos, I., Karageorgiou, V., Pergialiotis, V., & Perrea, D. N. (2020) · Clinical Microbiology and Infection · doi:10.1016/j.cmi.2020.03.019 · Cited by 78
Sud, S., Friedrich, J. O., Adhikari, N. K. J., Fan, E., Ferguson, N. D., Guyatt, G. H., & Meade, M. O. (2021) · American Journal of Respiratory and Critical Care Medicine · doi:10.1164/rccm.202008-3039oc · Cited by 86
Piechotta, V., Adams, A., Haque, M., Scheckel, B., Kreuzberger, N., Monsef, I., Jordan, K., Kuhr, K., & Skoetz, N. (2021) · Cochrane Database of Systematic Reviews · doi:10.1002/14651858.cd012775.pub2 · Cited by 100
Li, K.-P., Yang, X.-S., & Wu, T. (2022) · Frontiers in Endocrinology · doi:10.3389/fendo.2022.810242 · Cited by 79
“The ranks for each outcome were also presented (26, 27).”
BackgroundAn overview of conducting systematic reviews with network meta-analysis
Caldwell, D. M. (2014) · Systematic Reviews · doi:10.1186/2046-4053-3-109 · Cited by 79
Li, F., Huang, W., & Zhang, X. (2017) · Acta Ophthalmologica · doi:10.1111/aos.13568 · Cited by 79
“It suggests no evidence of small-study effects in the network if all studies lay symmetrically around the zero line of the comparison-adjusted funnel plot (Chaimani et al. 2013).”
BackgroundMethodBest, L. M., Freeman, S. C., Sutton, A. J., Cooper, N. J., Tng, E.-L., Csenar, M., Hawkins, N., Pavlov, C. S., Davidson, B. R., Thorburn, D., et al. (2019) · Cochrane Database of Systematic Reviews · doi:10.1002/14651858.cd013103.pub2 · Cited by 93
“In addition, we will use design-bytreatment full interaction model and inconsistency factor (IF) plots to assess inconsistency (Higgins 2012; Chaimani 2013).”
InfluentialCheng, H.-Y., McGuinness, L. A., Elbers, R. G., MacArthur, G. J., Taylor, A., McAleenan, A., Dawson, S., López-López, J. A., Higgins, J. P. T., Cowlishaw, S., et al. (2020) · BMJ · doi:10.1136/bmj.m3934 · Cited by 78
Self-citationLi, J., Zheng, X., Liu, X., Zhang, L., Zhang, S., Li, Y., Zhang, W., Li, Q., Zhao, Y., Chen, X., et al. (2023) · The Science of The Total Environment · doi:10.1016/j.scitotenv.2023.167017 · Cited by 89
Kasatpibal, N., Whitney, J. D., Saokaew, S., Kengkla, K., Heitkemper, M. M., & Apisarnthanarak, A. (2017) · Clinical Infectious Diseases · doi:10.1093/cid/cix114 · Cited by 80
Bangalore, S., Toklu, B., & Feit, F. (2014) · Circulation Cardiovascular Interventions · doi:10.1161/circinterventions.114.001346 · Cited by 77
Xuan, C., Wen, Y., Wang, D., Li, C., Ma, H., Mueller, A., & Wang, J. (2021) · Anesthesia & Analgesia · doi:10.1213/ane.0000000000005640 · Cited by 84
Thadanipon, K., Anothaisintawee, T., Rattanasiri, S., Thakkinstian, A., & Attia, J. R. (2019) · Journal of the American Academy of Dermatology · doi:10.1016/j.jaad.2019.01.004 · Cited by 86
“Publication bias was assessed by using comparison-adjusted funnel plots.(16) All analyses were performed using Stata version 15.”
MethodKelley, G. A., Kelley, K. S., & Pate, R. R. (2019) · BMJ Open · doi:10.1136/bmjopen-2019-031220 · Cited by 90
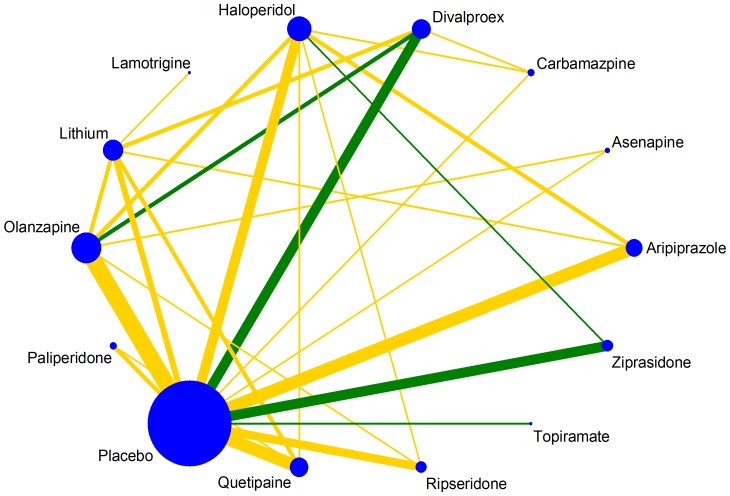
“Network (geometry) plots were used to provide a visual representation of the evidence base with nodes (circles) weighted by the number of participants randomised to each treatment and edges (lines) weighted by the number of studies evaluating each pair of treatments.(86) 87 Transitivity, that is, similarity in the dis…”
BackgroundMethodInfluentialZheng, Q., Yang, H., Sun, L., Wei, R., Fu, X., Wang, Y., Huang, Y., Liu, Y., & Liu, W. J. (2020) · Pharmacological Research · doi:10.1016/j.phrs.2020.105020 · Cited by 78
Torres-Costoso, A. I., Martínez‐Vizcaíno, V., Reina‐Gutiérrez, S., Álvarez‐Bueno, C., Guzmán‐Pavón, M. J., Pozuelo‐Carrascosa, D. P., Fernández‐Rodríguez, R., Sánchez‐López, M., & Cavero‐Redondo, I. (2021) · Archives of Physical Medicine and Rehabilitation · doi:10.1016/j.apmr.2021.08.008 · Cited by 93
Yang, W., Sun, C., He, S. Q., Chen, J. Y., Wang, Y., & Zhuo, Q. (2021) · Journal of General Internal Medicine · doi:10.1007/s11606-021-06755-z · Cited by 68
“The geometry and patterns of the network were prepared for each outcome, and the efficacy/safety hierarchy for a specific outcome was obtained via the surface under the cumulative ranking curve (SUCRA).(28) Clustered ranking plots were based on the cluster analysis of SUCRA values for two outcomes and displayed using…”
MethodD’Antonio, F., Berghella, V., Mascio, D. D., Saccone, G., Sileo, F. G., Flacco, M. E., Odibo, A. O., Liberati, M., Manzoli, L., & Khalil, A. A. (2021) · European Journal of Obstetrics & Gynecology and Reproductive Biology · doi:10.1016/j.ejogrb.2021.04.023 · Cited by 76
A selection model for accounting for publication bias in a full network meta‐analysis
Mavridis, D., Welton, N. J., Sutton, A., & Salanti, G. (2014) · Statistics in Medicine · doi:10.1002/sim.6321 · Cited by 76
“The empirical evidence about the presence of small-study effects in NMA highlights the need for developing and exploring methods specific to properly detect and account for publication bias in NMA, such as selection models [17].”
MethodSelf-citationWang, R., van Welie, N., van Rijswijk, J., JOHNSON, N. P., Norman, R. J., Dreyer, K., Mijatovic, V., & Mol, B. W. (2019) · Ultrasound in Obstetrics and Gynecology · doi:10.1002/uog.20238 · Cited by 76
Pharmacological interventions for non-alcohol related fatty liver disease (NAFLD)
Lombardi, R., Onali, S., Thorburn, D., Davidson, B. R., Gurusamy, K. S., & Tsochatzis, E. (2017) · Cochrane Database of Systematic Reviews · doi:10.1002/14651858.cd011640.pub2 · Cited by 74
Dayyani, M., Sadeghirad, B., Grotta, J. C., Zabihyan, S., Ahmadvand, S., Wang, Y., Guyatt, G. H., & Amin‐Hanjani, S. (2022) · Stroke · doi:10.1161/strokeaha.121.035699 · Cited by 90
Chen, L., Li, Y., Ning, G., Li, Y., Wu, Q., Guo, J., Shi, H., Wang, X., Zhou, Y., & Feng, S. (2015) · PLoS ONE · doi:10.1371/journal.pone.0123153 · Cited by 77
“gr) we used was fit for all kinds of networks [13, 14].”
MethodTang, H., Fang, Z., Wang, T., Cui, W., Zhai, S., & Song, Y. (2016) · The American Journal of Cardiology · doi:10.1016/j.amjcard.2016.08.061 · Cited by 75
Feng, F., Jiang, Q., Jia, H. M., Sun, H., Chai, Y., Li, X., Rong, G., Zhang, Y., & Li, Z. (2018) · Pharmacological Research · doi:10.1016/j.phrs.2018.06.021 · Cited by 75
Schwingshackl, L., Neuenschwander, M., Hoffmann, G., Buyken, A. E., & Schlesinger, S. (2020) · The American Journal of Clinical Nutrition · doi:10.1093/ajcn/nqz273 · Cited by 73
New generation antidepressants for depression in children and adolescents: a network meta-analysis
Hetrick, S. E., Meader, N., Bailey, A. P., Badcock, P. B., Moller, C. I., Cox, G., Merry, S., & McKenzie, J. E. (2020) · Cochrane Database of Systematic Reviews · doi:10.1002/14651858.cd013674 · Cited by 73
Yeo, Y. H., Shiu, S., Ho, H. J., Zou, B., Lin, J., Wu, M., Liou, J., & Wu, C. (2016) · Gut · doi:10.1136/gutjnl-2016-311868 · Cited by 73
“18 9 – 11 WinBUGS software V.1.4.3 (MRC Biostatistics Unit, Cambridge, UK) was used for estimation of effect sizes with non-informative priors.”
MethodInfluentialClarke, N. E., Doi, S. A. R., Wangdi, K., Chen, Y., Clements, A., & Nery, S. V. (2018) · Clinical Infectious Diseases · doi:10.1093/cid/ciy423 · Cited by 82
Tang, H., Li, D., Zhang, J., Li, Y., Wang, T., Zhai, S., & Song, Y. (2017) · Diabetes, Obesity and Metabolism · doi:10.1111/dom.12917 · Cited by 71
“0 using the “mvmeta” command and programmed STATA routines.(19,20) For a zeroevent RCT, a 0.”
MethodAimo, A., Pateras, K., Stamatelopoulos, K. S., Bayés‐Genís, A., Lombardi, C., Passino, C., Emdin, M., & Georgiopoulos, G. A. (2020) · Cardiovascular Drugs and Therapy · doi:10.1007/s10557-020-07099-2 · Cited by 74
Metadata
- Authors
- Chaimani, A., Higgins, J. P. T., Mavridis, D., Spyridonos, P., & Salanti, G.
- Affiliations
- University of Ioannina (GR)
- University of Bristol (GB)
- Corresponding author
- Salanti, Georgia
- Venue
- PLoS ONE
- Publisher
- Public Library of Science (PLoS)
- Published
- 2013-10-03
- Volume
- 8
- Issue
- 10
- Pages
- e76654
- ISSN
- 1932-6203 (ISSN-L)
- PMC
- PMC3789683
- OpenAlex
- W2091808438
- Semantic Scholar
- c99555607f865f8e0d32e5054195b29ccecc06cf
- Cited by
- 2,473
- References
- 51
- Citations by year
- 2026: 222 · 2025: 237 · 2024: 256 · 2023: 252 · 2022: 267 · 2021: 298 · 2020: 228 · 2019: 186 · 2018: 182 · 2017: 154 · 2016: 99 · 2015: 65 · 2014: 26 · 2013: 1
- FWCI
- 70.14
- Type
- journal article
- Language
- en
- Open access
- gold
- doi.org
- Locations
- PLoS ONE (publishedVersion, cc-by)
- Europe PMC (PubMed Central) (publishedVersion, cc-by)
- PubMed Central (publishedVersion, cc-by)
- PubMed (publishedVersion)
- RePEc: Research Papers in Economics (submittedVersion)
- DOAJ (DOAJ: Directory of Open Access Journals) (submittedVersion)
- Figshare (submittedVersion, cc-by)
- Bristol Research (University of Bristol) (submittedVersion)
- Funders
- FP7 Ideas: European Research Council (260559)
- Topics
- Social Sciences › Decision Sciences › Statistics, Probability and Uncertainty › Meta-analysis and systematic reviews
- Physical Sciences › Mathematics › Statistics and Probability › Statistical Methods in Clinical Trials
- Social Sciences › Sociology and Political Science › Delphi Technique in Research
- Keywords
- network meta-analysis, graphical tools, treatment ranking, non-statisticians
- MeSH terms
- Acute Disease, Arthritis, Rheumatoid, Bipolar Disorder, Data Interpretation, Statistical, Humans, Research Design, Meta-Analysis as Topic, Models, Statistical, Odds Ratio, Treatment Outcome, Antirheumatic Agents, Antimanic Agents
About these checks
Registry, retraction, Cites and statistics results are computed, not judged, with one exception: a printed reference that no index lists is read once by a model before it counts as a citation error. Claims are extracted by a model and kept only when their quote appears verbatim in the text; each cited source is then checked, with a model’s help, for whether it says what the claim relies on. Those verdicts can be wrong — read the claim’s quote and the cited source before relying on one.
Statistics and arithmetic are recomputed, not judged.
Confidence bands are shown only for fields calibrated on our annotated test set. None is calibrated yet, so no band is shown.
What counts as a claim ›How we measure confidence ›How we check this ›
Are you an author, or do you see a problem with this page? Request a review
Data sources
Bibliographic data: Semantic Scholar, OpenAlex, Crossref.
Contains information from the Semantic Scholar Academic Graph Datasets, made available under the ODC Attribution License (ODC-BY 1.0).
Semantic Scholar’s data is described in: Kinney, R., et al. (2023). The Semantic Scholar Open Data Platform. arXiv:2301.10140.
