

The DOI matches its Crossref record; 54 of the 54 references it cites were found in a registry or an index; none of the 78 sources its claims cite is checked for support yet.
Epidemiology of Pediatric Traumatic Brain Injury and Hypothalamic-Pituitary Disorders in Arizona
Open accessAbstract
Traumatic brain injury (TBI) in children can result in long-lasting social, cognitive, and neurological impairments. In adults, TBI can lead to endocrinopathies (endocrine system disorders), but this is infrequently reported in children. Untreated endocrinopathies can elevate risks of subsequent health issues, such that early detection in pediatric TBI survivors can initiate clinical interventions. To understand the risk of endocrinopathies following pediatric TBI, we identified patients who had experienced a TBI and subsequently developed a new-onset hypothalamic regulated endocrinopathy (n=498). We hypothesized that pediatric patients who were diagnosed with a TBI were at higher risk of being diagnosed with a central endocrinopathy than those without a prior diagnosis of TBI. In our epidemiological assessment, we identified pediatric patients enrolled in the Arizona Health Care Cost Containment System (AHCCCS) from 2008-2014 who were diagnosed with one of 330 TBI International Classification of Diseases (ICD)-9 codes and subsequently diagnosed with one of 14 central endocrinopathy ICD-9 codes. Additionally, the ICD-9 code data from over 600,000 Arizona pediatric patients afforded an estimate of the incidence, prevalence, relative risk, odds ratio, and number needed to harm, regarding the development of a central endocrinopathy after sustaining a TBI in Arizona Medicaid pediatric patients. Children with a TBI diagnosis had 3.22 times the risk of a subsequent central endocrine diagnosis compared with the general population (±0.28). Pediatric AHCCCS patients with a central endocrine diagnosis had 3.2-fold higher odds of a history of a TBI diagnosis than those without an endocrine diagnosis (±0.29). Furthermore, the number of patients with a TBI diagnosis for one patient to receive a diagnosis of a central endocrine diagnosis was 151.2 (±6.12). Female subjects were more likely to present with a central endocrine diagnosis after a TBI diagnosis compared to male subjects (64.1% vs 35.9%). These results are the first state-wide epidemiological study conducted to determine the risk of developing a hypothalamic-pituitary disorder after a TBI in the pediatric population. Our results contribute to a body of knowledge demonstrating a TBI etiology for idiopathic endocrine disorders, and thus advise physicians with regard to TBI follow-up care that includes preventive screening for endocrine disorders.
Overview
CoChat Summary
TL;DR
In Arizona Medicaid pediatric patients from 2008–2014, children with a TBI diagnosis had about 3.2 times the risk of a subsequent central endocrine diagnosis compared with those without TBI, with a number needed to harm of about 151. Female patients accounted for 64.1% of TBI-plus-endocrine cases and showed higher prevalence and earlier onset than male patients.
Key findings
- Among 498 unique patients with TBI and a subsequent central endocrine diagnosis, overall prevalence was 0.103 (±0.003 at 90% CI), incidence was 0.0014 (±0.0002), relative risk was 3.22 (±0.29), odds ratio was 3.24 (±0.29), and number needed to harm was 151.19 (±6.12).
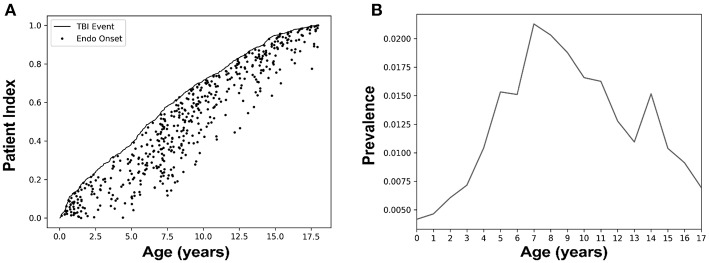
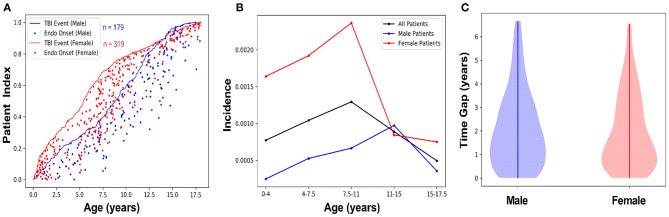
- The highest prevalence of endocrine diagnosis after TBI occurred at ages 7–11 years. Female patients (n = 319) outnumbered male patients (n = 179); female prevalence was 0.758 versus male prevalence 0.278, and female subjects were 64.06% versus male 35.94% of TBI-plus-endocrine cases.
- The predominant TBI ICD-9 code was 959.01 (head injury, unspecified), comprising ~64% of subjects by text (66.4% in Table 4). The predominant endocrine code was 259.10 (precocious sexual development and puberty, not elsewhere classified), comprising ~59% of subjects (59.4% in Table 4), followed by 253.30 (pituitary dwarfism) at 9% by text (9.5% in Table 4).
- A total of 107,458 children were diagnosed with a TBI before or at age 18; AHCCCS provided care for an average of 643,212 (±19,097 at 90% CI) pediatric patients per year.
Methods
- Retrospective epidemiological analysis of de-identified Arizona Health Care Cost Containment System (AHCCCS) Medicaid records from 2008–2014. Patients were ≤18 years old, continuously enrolled with no more than a 30-day gap in coverage per year, and had TBI diagnoses from 330 ICD-9 codes followed by central endocrine diagnoses from 14 ICD-9 codes; endocrine diagnosis prior to TBI was excluded.
- Patients were grouped into four cohorts: TBI+/Endo+, TBI+/Endo−, TBI−/Endo+, and TBI−/Endo−. Prevalence, incidence, relative risk, odds ratio, attributable risk, and number needed to harm were calculated and stratified by age and male/female sex using Python 3.7.3.
- The study protocol was approved by the Phoenix Children's Hospital Institutional Review Board (IRB 15-021) and deferred by the University of Arizona and Arizona State University; written informed consent was provided by participants' legal guardian/next of kin.
Limitations
- The authors state that the AHCCCS Medicaid sample represents a unique low-income population and may not generalize to the entire population; ICD-9 coding limitations, including the predominant unspecified head injury code 959.01, prevented meaningful analysis between TBI type/severity and endocrine disorder.
- The authors state that the dataset lacked injury severity indicators and case details/imaging, so the relationship between mode of TBI and pituitary or hypothalamic damage could not be determined; patients over age 18 were excluded, so late-teen TBI followed by later endocrine disorder may have been missed, and TBI/endocrine symptoms may be underreported.
- Evident from the text but not framed as limitations by the authors: the study is observational and cannot establish causality; sex was analyzed only as binary male/female entries; and the 18-year upper age limit creates an arbitrary ceiling effect on the data.
Model-written summary. Check it against the paper before relying on it.
Integrity signals
Registry
Cites
Statistics
Figures
Verification
Claims the paper makes
0 Valid · 0 Not valid · 32 Not checked · 49 Own results and interpretations
A result the paper reports from its own data — it cites no other source for it, so there is none to check. The quote shows it is in the paper.
In the paper
“A total of 107,458 children were diagnosed with a TBI before or at the age of 18 years.”
§ Epidemiology of Pediatric Traumatic Brain Injury and Hypothalamic-Pituitary Disorders in Arizona > Results > Prevalence of TBI and Endocrine Dysfunction Stratified by Age
plainn = 107,458- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: unclear — It is unclear whether the paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
A result the paper reports from its own data — it cites no other source for it, so there is none to check. The quote shows it is in the paper.
In the paper
“However, the prevalence of an endocrine diagnosis after a TBI diagnosis in female patients (0.758) was almost three times the prevalence in male patients (0.278; Table 3).”
§ Epidemiology of Pediatric Traumatic Brain Injury and Hypothalamic-Pituitary Disorders in Arizona > Results > Male/Female Differences With Age
plainstates an associationn = 319- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: unclear — It is unclear whether the paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
A result the paper reports from its own data — it cites no other source for it, so there is none to check. The quote shows it is in the paper.
In the paper
“The overall incidence was 0.0014 (±0.0002 at CI of 90%).”
§ Epidemiology of Pediatric Traumatic Brain Injury and Hypothalamic-Pituitary Disorders in Arizona > Results > Prevalence of TBI and Endocrine Dysfunction Stratified by Age
plainn = 498- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: unclear — It is unclear whether the paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
A result the paper reports from its own data — it cites no other source for it, so there is none to check. The quote shows it is in the paper.
In the paper
“The overall prevalence for an endocrine diagnosis after TBI was 0.103 (±0.003 at CI of 90%), with the highest prevalence of an endocrine disorder diagnosis after a TBI diagnosis occurring in the age range of 7–11 years old (Figure 1B).”
§ Epidemiology of Pediatric Traumatic Brain Injury and Hypothalamic-Pituitary Disorders in Arizona > Results > Prevalence of TBI and Endocrine Dysfunction Stratified by Age
plainn = 498- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
A result the paper reports from its own data — it cites no other source for it, so there is none to check. The quote shows it is in the paper.
In the paper
“The overall prevalence for an endocrine diagnosis after TBI was 0.103 (±0.003 at CI of 90%), with the highest prevalence of an endocrine disorder diagnosis after a TBI diagnosis occurring in the age range of 7–11 years old (Figure 1B).”
§ Epidemiology of Pediatric Traumatic Brain Injury and Hypothalamic-Pituitary Disorders in Arizona > Results > Prevalence of TBI and Endocrine Dysfunction Stratified by Age
plainstates an associationn = 498- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: unclear — It is unclear whether the paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
38 more claims
Create a free account to see all 81 claims and to verify the 78 references still open.
- It may state two separate claims as one. 26
- Probably not a substantial claim. 17
Claims other papers make about this one
Each is checked against this paper’s own text: does it say what the citing paper says it does?
In the citing paper
“The lack of clear data is probably a result of the varied design of the studies and the heterogeneity of the studied populations [7,8,9].”
From An Approach to Traumatic Brain Injury-Related Hypopituitarism: Overcoming the Pediatric Challenges (2023) · cites this paper as [7]
In the citing paper
“However, there are currently no screening guidelines specific to children or adolescents for investigating endocrine dysfunction after a TBI.10”
In the citing paper
“One study suggested that the highest rates of pituitary hormone deficiencies in children occur between 7 and 11 years of age.10”
Self-check
Percentages, sums and reported differences re-computed from the paper’s own numbers.
Each contradiction between two passages listed here was confirmed by an independent check.
Rated major: it would touch a result — a value a result rests on, reported and recomputed p-values on opposite sides of the significance level, two passages that conflict with no sign which is right, or a cited work retracted before this paper was published.
In the paper
§ Epidemiology of Pediatric Traumatic Brain Injury and Hypothalamic-Pituitary Disorders in Arizona > Results > Male/Female Differences With Age
“| Total | 100.00% (498) | 0.103 |”
§ Epidemiology of Pediatric Traumatic Brain Injury and Hypothalamic-Pituitary Disorders in Arizona > Results > Male/Female Differences With Age
“| Male | 35.94% (179) | 0.278 | | Female | 64.06% (319) | 0.758 |”
Rated major: it would touch a result — a value a result rests on, reported and recomputed p-values on opposite sides of the significance level, two passages that conflict with no sign which is right, or a cited work retracted before this paper was published.
In the paper
§ Epidemiology of Pediatric Traumatic Brain Injury and Hypothalamic-Pituitary Disorders in Arizona > Methods > Data Analysis
“Prevalence was calculated as the number of TBI patients with an endocrine diagnosis divided by those TBI patients without an endocrine diagnosis for each year (A/C).”
§ Epidemiology of Pediatric Traumatic Brain Injury and Hypothalamic-Pituitary Disorders in Arizona > Methods > Data Analysis
“with TBI and without endocrine disorder (TBI+, Endo–; B), without TBI and with endocrine disorder (TBI–, Endo+; C)”
Rated minor: it would not touch a result — a value no result rests on, a p-value that stays on the same side of the significance level, or a conflict that is clerical, resolved elsewhere in the paper, or outside its own findings.
In the paper
“The predominant TBI diagnosis code identified in the sample was 959.01 (Head Injury: Unspecified) which comprised ~64% of the subjects.”
§ Epidemiology of Pediatric Traumatic Brain Injury and Hypothalamic-Pituitary Disorders in Arizona > Results > Predominant ICD-9 Codes Used and Diagnoses Over the Years
Reported 64 · recomputed 89.72901
Citations
Cites
National Center for Injury Prevention and Control (U.S.). Division of Injury Response., Faul, M., Wald, M. M., Wu, L., & Coronado, V. G. (2010) · doi:10.15620/cdc.5571 · Cited by 3,494
Unreported Concussion in High School Football Players: Implications for Prevention
McCrea, M., Hammeke, T., Olsen, G., Leo, P., & Guskiewicz, K. (2004) · Clinical Journal of Sport Medicine · doi:10.1097/00042752-200401000-00003 · Cited by 1,220
Long-Term Consequences of Child Abuse and Neglect on Adult Economic Well-Being
Currie, J., & Spatz Widom, C. (2010) · Child Maltreatment · doi:10.1177/1077559509355316 · Cited by 753
Kelly, D. F., Gaw Gonzalo, I. T., Cohan, P., Berman, N., Swerdloff, R., & Wang, C. (2000) · Journal of Neurosurgery · doi:10.3171/jns.2000.93.5.0743 · Cited by 455
Anterior Pituitary Dysfunction in Survivors of Traumatic Brain Injury
Agha, A., Rogers, B., Sherlock, M., O’Kelly, P., Tormey, W., Phillips, J., & Thompson, C. J. (2004) · The Journal of Clinical Endocrinology & Metabolism · doi:10.1210/jc.2004-0511 · Cited by 390
Occurrence of pituitary dysfunction following traumatic brain injury
Bondanelli, M., De Marinis, L., Ambrosio, M. R., Monesi, M., Valle, D., Zatelli, M. C., Fusco, A., Bianchi, A., Farneti, M., & Degli, E. C. I. (2004) · Journal of Neurotrauma · doi:10.1089/0897715041269713 · Cited by 322
Chronic Aspects of Pediatric Traumatic Brain Injury: Review of the Literature
Babikian, T., Merkley, T., Savage, R. C., Giza, C. C., & Levin, H. (2015) · Journal of Neurotrauma · doi:10.1089/neu.2015.3971 · Cited by 276
Prevalence of Neuroendocrine Dysfunction in Patients Recovering from Traumatic Brain Injury
Lieberman, S. A. (2001) · Journal of Clinical Endocrinology & Metabolism · doi:10.1210/jc.86.6.2752 · Cited by 261
Consensus guidelines on screening for hypopituitarism following traumatic brain injury
Ghigo, E., Masel, B., Aimaretti, G., Léon-Carrión, J., Casanueva, F. F., Dominguez-Morales, M. R., Elovic, E., Perrone, K., Stalla, G., Thompson, C., et al. (2005) · Brain Injury · doi:10.1080/02699050400025315 · Cited by 261
Epidemiology and Outcomes of Pediatric Traumatic Brain Injury
Keenan, H. T., & Bratton, S. L. (2006) · Developmental Neuroscience · doi:10.1159/000094152 · Cited by 260
Catroppa, C., Anderson, V. A., Morse, S. A., Haritou, F., & Rosenfeld, J. V. (2008) · Journal of Pediatric Psychology · doi:10.1093/jpepsy/jsn006 · Cited by 260
Hypothalamic lesions following closed head injury
CROMPTON, M. R. (1971) · Brain · doi:10.1093/brain/94.1.165 · Cited by 243
Pituitary Dysfunction After Traumatic Brain Injury: A Clinical and Pathophysiological Approach
Tanriverdi, F., Schneider, H. J., Aimaretti, G., Masel, B. E., Casanueva, F. F., & Kelestimur, F. (2015) · Endocrine Reviews · doi:10.1210/er.2014-1065 · Cited by 218 · cited 1×
“2% of patients having more than one endocrine dysfunction post-TBI (16).”
BackgroundLeal‐Cerro, A., Flores, J. M., Rincon, M., Murillo, F., Pujol, M., Garcia‐Pesquera, F., Dieguez, C., & Casanueva, F. F. (2005) · Clinical Endocrinology · doi:10.1111/j.1365-2265.2005.02250.x · Cited by 199
Popovic, V., Pekic, S., Pavlovic, D., Maric, N., Jasovic-Gasic, M., Djurovic, B., Medic-Stojanoska, M., Zivkovic, V., Stojanovic, M., Doknic, M., et al. (2004) · Journal of Endocrinological Investigation · doi:10.1007/bf03345308 · Cited by 195
Macias, E. G. (1975) · The Lancet · doi:10.1016/s0140-6736(75)92165-0 · Cited by 193
The underreporting of self-reported symptoms following sports-related concussion
Meier, T. B., Brummel, B. J., Singh, R., Nerio, C. J., Polanski, D. W., & Bellgowan, P. S. F. (2015) · Journal of Science and Medicine in Sport · doi:10.1016/j.jsams.2014.07.008 · Cited by 183
Predictors of survival and severity of disability after severe brain injury in children
Michaud, L. J., Rivara, F. P., Grady, M. S., & Reay, D. T. (1992) · Neurosurgery · doi:10.1227/00006123-199208000-00010 · Cited by 180
Traumatic infarction of the anterior lobe of the pituitary gland
Daniel, P. M., Prichard, M. M. L., & Treip, C. S. (1959) · The Lancet · doi:10.1016/s0140-6736(59)91583-1 · Cited by 168
Neuroendocrine responses following graded traumatic brain injury in male adults
Cernak, V. J. S. (1999) · Brain Injury · doi:10.1080/026990599121016 · Cited by 142
Functional Recovery Ten Years after Pediatric Traumatic Brain Injury: Outcomes and Predictors
Catroppa, C., Godfrey, C., Rosenfeld, J. V., Hearps, S. J. C., & Anderson, V. A. (2012) · Journal of Neurotrauma · doi:10.1089/neu.2012.2403 · Cited by 139
Kokshoorn, N. E., Wassenaar, M. J. E., Biermasz, N. R., Roelfsema, F., Smit, J. W. A., Romijn, J. A., & Pereira, A. M. (2010) · European Journal of Endocrinology · doi:10.1530/eje-09-0601 · Cited by 129
Health-related quality of life during the first year after traumatic brain injury
McCarthy, M. L. (2006) · Archives of Pediatrics & Adolescent Medicine · doi:10.1001/archpedi.160.3.252 · Cited by 122
Einaudi, S., Matarazzo, P., Peretta, P., Grossetti, R., Giordano, F., Aitare, F., Bondone, C., Andreo, M., Ivani, G., Genitori, L., et al. (2006) · Journal of Pediatric Endocrinology and Metabolism · doi:10.1515/jpem.2006.19.5.691 · Cited by 106
Abnormalities of pituitary function after traumatic brain injury in children
Niederland, T., Makovi, H., Gál, V., Andréka, B., Ábrahám, C. S., & Kovács, J. (2007) · Journal of Neurotrauma · doi:10.1089/neu.2005.369er · Cited by 104
Magnetic resonance imaging changes in the pituitary gland following acute traumatic brain injury
Maiya, B., Newcombe, V., Nortje, J., Bradley, P., Bernard, F., Chatfield, D., Outtrim, J., Hutchinson, P., Matta, B., Antoun, N., et al. (2008) · Intensive Care Medicine · doi:10.1007/s00134-007-0902-x · Cited by 91
Endocrine dysfunction following traumatic brain injury in children
Kaulfers, A.-M. D., Backeljauw, P. F., Reifschneider, K., Blum, S., Michaud, L., Weiss, M., & Rose, S. R. (2010) · The Journal of Pediatrics · doi:10.1016/j.jpeds.2010.07.004 · Cited by 84
Schneider, H. J., Sämann, P. G., Schneider, M., Croce, C. G., Corneli, G., Sievers, C., Ghigo, E., Stalla, G. K., & Aimaretti, G. (2007) · Journal of Endocrinological Investigation · doi:10.1007/bf03346291 · Cited by 79
GH deficiency as the most common pituitary defect after TBI: clinical implications
Popovic, V. (2005) · Pituitary · doi:10.1007/s11102-006-6047-z · Cited by 68
Update of Endocrine Dysfunction following Pediatric Traumatic Brain Injury
Reifschneider, K., Auble, B., & Rose, S. (2015) · Journal of Clinical Medicine · doi:10.3390/jcm4081536 · Cited by 66 · cited 3×
“Regardless, the prevalence of endocrine dysfunction in the first 6 months after TBI [4–86%; (21, 22, 24)], and at 1–5 years after TBI [10–38%; (18, 19, 23, 37)] in children as currently reported in the literature is not instructive due to the large variability in prevalence.”
BackgroundPituitary dysfunction following traumatic brain injury: clinical perspectives
Tanriverdi, F., & Kelestimur, F. (2015) · Neuropsychiatric Disease and Treatment · doi:10.2147/ndt.s65814 · Cited by 65
Acerini, C. L., Tasker, R. C., Bellone, S., Bona, G., Thompson, C. J., & Savage, M. O. (2006) · European Journal of Endocrinology · doi:10.1530/eje.1.02284 · Cited by 65
Pituitary function in paediatric survivors of severe traumatic brain injury
Poomthavorn, P., Maixner, W., & Zacharin, M. (2008) · Archives of Disease in Childhood · doi:10.1136/adc.2007.121137 · Cited by 63
Permanent hypopituitarism is rare after structural traumatic brain injury in early childhood
Heather, N. L., Jefferies, C., Hofman, P. L., Derraik, J. G. B., Brennan, C., Kelly, P., Hamill, J. K. M., Jones, R. G., Rowe, D. L., & Cutfield, W. S. (2012) · The Journal of Clinical Endocrinology & Metabolism · doi:10.1210/jc.2011-2284 · Cited by 62 · cited 1×
“Risk factors of hypothalamic-pituitary disorders after TBI are controversial, without definitive relationships between injury factors and hypopituitarism (26, 45, 46).”
BackgroundDiffuse traumatic brain injury affects chronic corticosterone function in the rat
Rowe, R. K., Rumney, B. M., May, H. G., Permana, P., Adelson, P. D., Harman, S. M., Lifshitz, J., & Thomas, T. C. (2016) · Endocrine Connections · doi:10.1530/ec-16-0031 · Cited by 60
Self-citationKeenan, H. T., Presson, A. P., Clark, A. E., Cox, C. S., & Ewing-Cobbs, L. (2019) · Journal of Neurotrauma · doi:10.1089/neu.2018.5687 · Cited by 56
Emelifeonwu, J. A., Flower, H., Loan, J. J., McGivern, K., & Andrews, P. J. D. (2020) · Journal of Neurotrauma · doi:10.1089/neu.2018.6349 · Cited by 55
Accuracy of CPT evaluation and management coding by family physicians.
King, M. S., Sharp, L. K., & Lipsky, M. S. (2001) · PubMed · Cited by 53
The effects of repeat traumatic brain injury on the pituitary in adolescent rats
Greco, T., Hovda, D., & Prins, M. (2013) · Journal of Neurotrauma · doi:10.1089/neu.2013.2990 · Cited by 51
Evaluation of pituitary function after traumatic brain injury in childhood
Khadr, S. N., Crofton, P. M., Jones, P. A., Wardhaugh, B., Roach, J., Drake, A. J., Minns, R. A., & Kelnar, C. J. H. (2010) · Clinical Endocrinology · doi:10.1111/j.1365-2265.2010.03857.x · Cited by 47
Personnier, C., Crosnier, H., Meyer, P., Chevignard, M., Flechtner, I., Boddaert, N., Breton, S., Mignot, C., Dassa, Y., Souberbielle, J.-C., et al. (2014) · The Journal of Clinical Endocrinology & Metabolism · doi:10.1210/jc.2013-4129 · Cited by 44
Endocrine changes after pediatric traumatic brain injury
Rose, S. R., & Auble, B. A. (2012) · Pituitary · doi:10.1007/s11102-011-0360-x · Cited by 40
Hypopituitarism and growth hormone deficiency (GHD) after traumatic brain injury (TBI)
Aimaretti, G., Ambrosio, M. R., Benvenga, S., Borretta, G., De Marinis, L., De Menis, E., Di Somma, C., Faustini-Fustini, M., Grottoli, S., Gasco, V., et al. (2004) · Growth Hormone & IGF Research · doi:10.1016/j.ghir.2004.03.025 · Cited by 40
Hypopituitarism after traumatic brain injury
Fernandez-Rodriguez, E., Bernabeu, I., Castro, A. I., & Casanueva, F. F. (2015) · Endocrinology and Metabolism Clinics of North America · doi:10.1016/j.ecl.2014.10.012 · Cited by 40
Hypopituitarism in pediatric survivors of inflicted traumatic brain injury
Auble, B. A., Bollepalli, S., Makoroff, K., Weis, T., Khoury, J., Colliers, T., & Rose, S. R. (2014) · Journal of Neurotrauma · doi:10.1089/neu.2013.2916 · Cited by 38
Endocrine dysfunction following traumatic brain injury: a 5-year follow-up nationwide-based study
Yang, W.-H., Chen, P.-C., Wang, T.-C., Kuo, T.-Y., Cheng, C.-Y., & Yang, Y.-H. (2016) · Scientific Reports · doi:10.1038/srep32987 · Cited by 36
Casano‐Sancho, P., Suárez, L., Ibáñez, L., García‐Fructuoso, G., Medina, J., & Febrer, A. (2013) · Clinical Endocrinology · doi:10.1111/cen.12237 · Cited by 36
Endocrine function in children acutely following severe traumatic brain injury
Srinivas, R., Brown, S. D., Chang, Y.-F., Garcia-Fillion, P., & Adelson, P. D. (2010) · Child s Nervous System · doi:10.1007/s00381-009-1038-9 · Cited by 28
Self-citationAdolescent TBI-induced hypopituitarism causes sexual dysfunction in adult male rats
Greco, T., Hovda, D. A., & Prins, M. L. (2015) · Developmental Neurobiology · doi:10.1002/dneu.22218 · Cited by 24
The impact of traumatic brain injury on pituitary function
Sundaram, N. K., Geer, E. B., & Greenwald, B. D. (2013) · Endocrinology and Metabolism Clinics of North America · doi:10.1016/j.ecl.2013.05.003 · Cited by 22
Is routine endocrine evaluation necessary after paediatric traumatic brain injury?
Salomón-Estébanez, M. A., Grau, G., Vela, A., Rodríguez, A., Morteruel, E., Castaño, L., & Rica, I. (2014) · Journal of Endocrinological Investigation · doi:10.1007/s40618-013-0020-2 · Cited by 15
Sports-Related Repetitive Traumatic Brain Injury: A Novel Cause of Pituitary Dysfunction
Sezgin Caglar, A., Tanriverdi, F., Karaca, Z., Unluhizarci, K., & Kelestimur, F. (2019) · Journal of Neurotrauma · doi:10.1089/neu.2018.5751 · Cited by 14
Current Procedural Terminology Codes – Why Are They Important?
Eberhardt, J. M., & Harb, W. J. (2018) · Diseases of the Colon & Rectum · doi:10.1097/dcr.0000000000001190 · Cited by 3
Anterior hypopituitarism due to fracture of the sella turcica
BISTRITZER, T. (1981) · Archives of Pediatrics & Adolescent Medicine · doi:10.1001/archpedi.1981.02130340070022 · Cited by 2
Cited by
Pathophysiology of Pediatric Traumatic Brain Injury
Serpa, R. O., Ferguson, L., Larson, C., Bailard, J., Cooke, S., Greco, T., & Prins, M. L. (2021) · Frontiers in Neurology · doi:10.3389/fneur.2021.696510 · Cited by 62
Endocrine Dysfunction After Traumatic Brain Injury: An Ignored Clinical Syndrome?
Mahajan, C., Prabhakar, H., & Bilotta, F. (2023) · Neurocritical Care · doi:10.1007/s12028-022-01672-3 · Cited by 61
Doust, Y. V., Rowe, R. K., Adelson, P. D., Lifshitz, J., & Ziebell, J. M. (2021) · Frontiers in Neurology · doi:10.3389/fneur.2021.722526 · Cited by 33
Self-citationKrishna, G., Bromberg, C. E., Connell, E., Mian, E., Hu, C., Lifshitz, J., Adelson, P. D., & Thomas, T. C. (2020) · Frontiers in Neurology · doi:10.3389/fneur.2020.00749 · Cited by 30
Self-citationMild and Moderate Traumatic Brain Injury and Repeated Stress Affect Corticosterone in the Rat
Rowe, R. K., Ortiz, J. B., & Thomas, T. C. (2020) · Neurotrauma Reports · doi:10.1089/neur.2020.0019 · Cited by 29
Self-citation
Metadata
- Authors
- Ortiz, J. B., Sukhina, A., Balkan, B., Harootunian, G., Adelson, P. D., Lewis, K. S., Oatman, O., Subbian, V., Rowe, R. K., & Lifshitz, J.
- Affiliations
- Barrow Neurological Institute (US)
- University of Arizona (US)
- Arizona State University (US)
- Phoenix Children's Hospital (US)
- Corresponding author
- Lifshitz, Jonathan
- ORCID
- Venue
- Frontiers in Neurology
- Publisher
- Frontiers Media SA
- Published
- 2020-01-22
- Volume
- 10
- Pages
- 1410-1410
- ISSN
- 1664-2295 (ISSN-L)
- PMC
- PMC6988738
- OpenAlex
- W3001464871
- Cited by
- 28
- References
- 54
- Citations by year
- 2026: 3 · 2025: 2 · 2024: 3 · 2023: 9 · 2022: 2 · 2021: 4 · 2020: 3
- FWCI
- 2.29
- Type
- journal article
- Language
- en
- Open access
- gold
- doi.org
- Licence
- Locations
- Frontiers in Neurology (publishedVersion, cc-by)
- Europe PMC (PubMed Central) (publishedVersion, cc-by)
- PubMed (publishedVersion)
- PubMed Central (publishedVersion, cc-by)
- UA Campus Repository (The University of Arizona) (acceptedVersion, cc-by)
- DOAJ (DOAJ: Directory of Open Access Journals) (submittedVersion)
- Funders
- National Science Foundation (1838745)
- Science Foundation Arizona
- Arizona State University
- Topics
- Health Sciences › Medicine › Clinical Neurology › Traumatic Brain Injury and Neurovascular Disturbances
- Health Sciences › Medicine › Clinical Neurology › Traumatic Brain Injury Research
- Health Sciences › Medicine › Endocrinology, Diabetes and Metabolism › Pituitary Gland Disorders and Treatments
- Keywords
- pediatric traumatic brain injury, hypothalamic-pituitary dysfunction, incidence and prevalence, Medicaid, sex differences, endocrine screening
About these checks
Registry, retraction, Cites and statistics results are computed, not judged, with one exception: a printed reference that no index lists is read once by a model before it counts as a citation error. Claims are extracted by a model and kept only when their quote appears verbatim in the text; each cited source is then checked, with a model’s help, for whether it says what the claim relies on. Those verdicts can be wrong — read the claim’s quote and the cited source before relying on one.
A language model drew the claims from the paper on 2026-11-14, under version 3 of the claim definition (model deepseek-v4.1-flash, prompt extract-v3).
A second model labelled each claim on 2026-11-14 (model jev-1.13-20260917, definition revision gold-guideline-v0.2).
Statistics and arithmetic are recomputed, not judged.
Confidence bands are shown only for fields calibrated on our annotated test set. None is calibrated yet, so no band is shown.
What counts as a claim ›How we measure confidence ›How we check this ›
Are you an author, or do you see a problem with this page? Request a review
Data sources
Bibliographic data: Semantic Scholar, OpenAlex, Crossref.
Contains information from the Semantic Scholar Academic Graph Datasets, made available under the ODC Attribution License (ODC-BY 1.0).
Semantic Scholar’s data is described in: Kinney, R., et al. (2023). The Semantic Scholar Open Data Platform. arXiv:2301.10140.
