

The DOI matches its Crossref record; 103 of the 105 references it cites were found in a registry or an index; none of the 81 sources its claims cite is checked for support yet.
Immunology of Wound Healing
Open accessAbstract
PURPOSE OF REVIEW: Chronic wounds are a tremendous burden on the healthcare system and lead to significant patient morbidity and mortality. Normal cutaneous wound healing occurs through an intricate and delicate interplay between the immune system, keratinocytes, and dermal cells. Each cell type contributes signals that drive the normal phases of wound healing: hemostasis, inflammation, proliferation, and remodeling. This paper reviews how various immunological cell types and signaling molecules influence the way wounds develop, persist, and heal. RECENT FINDINGS: Concurrent with the achievement of hemostasis, neutrophils are the first cells to migrate to the wound bed, brought in by pro-inflammatory signals including IL-8. Their apoptosis and engulfment by macrophages (efferocytosis) provides a key signal to the local immune milieu, including macrophages, to transition to an anti-inflammatory, pro-repair state, where angiogenesis occurs and granulation tissue is laid down. Myofibroblasts, activated through contractile forces and signaling molecules, then drive remodeling, where granulation tissue becomes scar. Unchecked inflammation at this stage can result in abnormal scar formation. SUMMARY: Although the derangement of immune signals at any stage can result in impaired wound healing, recent research has shown that the key transition point lies between the inflammatory and the proliferative phases. This review summarizes the events that facilitate this transition and discusses how this process can be disrupted, leading to chronic, non-healing wounds.
Overview
AI snapshot
Written from the paper’s full text.
TL;DR
This review summarizes immune mechanisms across hemostasis, inflammation, proliferation, and remodeling, arguing that the critical transition from the inflammatory to the proliferative phase often fails in chronic wounds. It highlights neutrophil apoptosis/efferocytosis and macrophage polarization as key drivers of repair.
Key findings
- Chronic wounds in the USA afflict approximately 6.5 million individuals and cost the healthcare system over 25 billion dollars annually; their mortality effect has been reported as comparable to cancer.
- Normal wound healing is divided into hemostasis (minutes to hours), inflammation (days 1–3), proliferation and repair (days 4–21), and remodeling (days 21–365); the key inflammatory-to-proliferative transition occurs around days 2–5 and often fails in chronic wounds.
- Neutrophils are early responders recruited by IL-8/CXCL8; their apoptosis and macrophage engulfment (efferocytosis) signal a shift to anti-inflammatory, pro-repair macrophages. Persistent neutrophils, NETs, proteases/MMPs, reactive oxygen species, and elevated CXCL8 contribute to chronic, non-healing wounds.
- Anti-inflammatory macrophages promote angiogenesis, granulation tissue, and re-epithelialization via VEGF, TGF-β, PDGF, EGF, KGF, and other signals; impaired pro- to anti-inflammatory macrophage transition—seen with iron overload, hyperglycemia, and hypoxia—stalls healing. Mature scars regain only 80% of initial tensile strength.
Methods
- Narrative review of the literature; no primary data, sample, or statistical analysis are reported.
- Synthesizes immune cell and signaling pathways across the four phases of wound healing, focusing on the inflammatory-to-proliferative transition and chronic wounds.
- Draws on cited animal models, in vitro studies, and human wound observations; no systematic search or meta-analysis is described.
Limitations
- The paper states no limitations.
- Evident from the text: it is a narrative review without systematic search, inclusion criteria, or quality appraisal.
- Evident from the text: many mechanistic conclusions rely on mouse models and in vitro findings, with limited direct human chronic wound data; no original experiments or quantitative synthesis are presented.
Model-written summary. Check it against the paper before relying on it.
Integrity signals
Registry
Cites
Statistics
Figures
Verification
Claims the paper makes
52 Not checked yet · 8 Own interpretation · 6 No basis given
In the paper
“In impaired models of wound healing, such as diabetes, where infection risk is higher, neutrophils are clearly required [28].”
§ Immunology of Wound Healing > Four Stages of Wound Healing > Inflammation
What the sources say
- Not checked yetcites [28] Wilgus TA, Roy S, McDaniel JC. Neutrophils and wound repair: positive actions and negative reactions. Adv Wound Care. 2013;2(7):379–88. https://doi.org/10.1089/wound.2012.0383 . source
boosteddirect- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: unclear — It is unclear whether the paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
- Rests on an assumption: Findings from mouse models of wound healing can be generalized to human wound healing and chronic wounds.
In the paper
“Their influx is mediated by a number of chemical signals, including IL-8, or CXCL8, as mentioned above, and neutrophils have over 30 different receptors that mitigate their migration and activation response [24].”
§ Immunology of Wound Healing > Four Stages of Wound Healing > Inflammation
What the sources say
- Not checked yetcites [24] Futosi K, Fodor S, Mocsai A. Neutrophil cell surface receptors and their intracellular signal transduction pathways. Int Immunopharmacol. 2013;17(3):638–50. https://doi.org/10.1016/j.intimp.2013.06.034 . source
plaindirect- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: unclear — It is unclear whether the paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
None of the sources cited for this claim have been checked yet.
In the paper
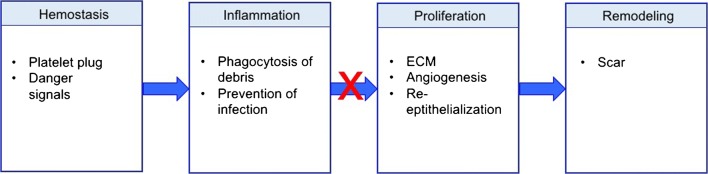
“normal wound healing can generally be broken down into four over-lapping but distinct steps (Fig. 1). These steps include hemostasis (minutes to hours after injury), inflammation (days 1–3), proliferation and repair (days 4–21), and lastly, wound remodeling (days 21–365) [8, 9].”
§ Immunology of Wound Healing > Introduction
What the sources say
- Not checked yetcites [8] Morton LM, Phillips TJ. Wound healing and treating wounds: differential diagnosis and evaluation of chronic wounds. J Am Acad Dermatol. 2016;74(4):589–605; quiz −6. https://doi.org/10.1016/j.jaad.2015.08.068 . source
- Not checked yetcites [9] Reinke JM, Sorg H. Wound repair and regeneration. Eur Surg Res. 2012;49(1):35–43. https://doi.org/10.1159/000339613 . source
plain- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
In the paper
“chronic wounds demonstrate significantly increased levels of the potent neutrophil chemoattractant, CXCL8 [58].”
§ Immunology of Wound Healing > Four Stages of Wound Healing > Inflammation
What the sources say
- Not checked yetcites [58] Fivenson DP, Faria DT, Nickoloff BJ, Poverini PJ, Kunkel S, Burdick M, et al. Chemokine and inflammatory cytokine changes during chronic wound healing. Wound Repair Regen. 1997;5(4):310–22. https://doi.org/10.1046/j.1524-475X.1997.50405.x . source
boostedcorrelational- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
The paper states this without a source or data behind it here, so there is nothing to check it against. The quote shows it is in the paper.
In the paper
“Platelet activation not only results in hemostasis, but also in the release of growth factors such as platelet-derived growth factor (PDGF) as well as immune mediators that are responsible for activation of the immune system and transition to the inflammatory phase of wound healing.”
§ Immunology of Wound Healing > Four Stages of Wound Healing > Hemostasis
plaindirect- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: unclear — It is unclear whether the paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
None of the sources cited for this claim have been checked yet.
In the paper
“mouse models of wound healing have shown that in non-aged, non-impaired models, neutrophil depletion does not negatively affect wound healing as profoundly as macrophage deletion [25–27].”
§ Immunology of Wound Healing > Four Stages of Wound Healing > Inflammation
What the sources say
- Not checked yetcites [25] Leibovich SJ, Ross R. The role of the macrophage in wound repair. A study with hydrocortisone and antimacrophage serum. Am J Pathol. 1975;78(1):71–100.
- Not checked yetcites [26] Pinhal-Enfield G, Ramanathan M, Hasko G, Vogel SN, Salzman AL, Boons GJ, et al. An angiogenic switch in macrophages involving synergy between Toll-like receptors 2, 4, 7, and 9 and adenosine A(2A) receptors. Am J Pathol. 2003;163(2):711–21. https://doi.org/10.1016/s0002-9440(10)63698-x . source
- Not checked yetcites [27] Simpson DM, Ross R. The neutrophilic leukocyte in wound repair a study with antineutrophil serum. J Clin Invest. 1972;51(8):2009–23. https://doi.org/10.1172/jci107007 . source
plaindirect- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: unclear — It is unclear whether the paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
- Rests on an assumption: Findings from mouse models of wound healing can be generalized to human wound healing and chronic wounds.
A conclusion the paper draws from its own results — it cites no other source for it, so there is none to check. The quote shows it is in the paper.
In the paper
“New research has illustrated that chronic wounds fail to shift from the inflammatory to the proliferative phase of wound healing”
§ Immunology of Wound Healing > Introduction
boosted- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
A conclusion the paper draws from its own results — it cites no other source for it, so there is none to check. The quote shows it is in the paper.
In the paper
“recent research has shown that the key transition point lies between the inflammatory and the proliferative phases.”
- Also stated in: § Conclusions · plain
“Recent research has shown that the key transition point in wound healing lies between the inflammatory and the proliferative phases.”
§ Immunology of Wound Healing > Abstract > Summary
plain- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: unclear — It is unclear why the paper says it holds.
- Also stated in: § Conclusions · plain
None of the sources cited for this claim have been checked yet.
In the paper
“the immune system has been found to play a substantial role due to its impact on several repair mechanisms [6, 7].”
§ Immunology of Wound Healing > Introduction
What the sources say
- Not checked yetcites [6] MA S, MJ N. The innate immune system in acute and chronic wounds. Adv Wound Care. 2016;5(2):65–78. https://doi.org/10.1089/wound.2014.0608 . source
- Not checked yetcites [7] Strbo N, Yin N, Stojadinovic O. Innate and adaptive immune responses in wound epithelialization. Adv Wound Care. 2014;3(7):492–501. https://doi.org/10.1089/wound.2012.0435 . source
plaindirect- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
The paper states this without a source or data behind it here, so there is nothing to check it against. The quote shows it is in the paper.
In the paper
“Myofibroblasts, activated through contractile forces and signaling molecules, then drive remodeling, where granulation tissue becomes scar.”
§ Immunology of Wound Healing > Abstract > Recent Findings
plaindirect- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: unclear — It is unclear why the paper says it holds.
- It may state two separate claims as one. 15
In the paper
“Concurrent with the achievement of hemostasis, neutrophils are the first cells to migrate to the wound bed, brought in by pro-inflammatory signals including IL-8.”
§ Immunology of Wound Healing > Abstract > Recent Findings
What the sources say
- Not checked yetcites [31] Baggiolini M, Loetscher P, Moser B. Interleukin-8 and the chemokine family. Int J Immunopharmacol. 1995;17(2):103–8. source
plaindirect- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: unclear — It is unclear whether the paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
None of the sources cited for this claim have been checked yet.
In the paper
“Neutrophils represent the most abundant inflammatory cells to infiltrate a new wound and function mainly to remove debris and prevent infection [22, 23].”
§ Immunology of Wound Healing > Four Stages of Wound Healing > Inflammation
What the sources say
- Not checked yetcites [22] Engelhardt E, Toksoy A, Goebeler M, Debus S, Brocker EB, Gillitzer R. Chemokines IL-8, GROalpha, MCP-1, IP-10, and Mig are sequentially and differentially expressed during phase-specific infiltration of leukocyte subsets in human wound healing. Am J Pathol. 1998;153(6):1849–60. source
- Not checked yetcites [23] de Oliveira S, Rosowski EE, Huttenlocher A. Neutrophil migration in infection and wound repair: going forward in reverse. Nat Rev Immunol. 2016;16(6):378–91. https://doi.org/10.1038/nri.2016.49 . source
plaindirect- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: unclear — It is unclear whether the paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
In the paper
“NETs have also been detected in excess in diabetic foot wounds and have been shown to delay healing, and inhibition of NETosis and NET function in mouse models of delayed wound healing improves outcomes [59•].”
§ Immunology of Wound Healing > Four Stages of Wound Healing > Inflammation
What the sources say
- Not checked yetcites [59•]
plaindirect- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
- Rests on an assumption: Findings from mouse models of wound healing can be generalized to human wound healing and chronic wounds.
None of the sources cited for this claim have been checked yet.
In the paper
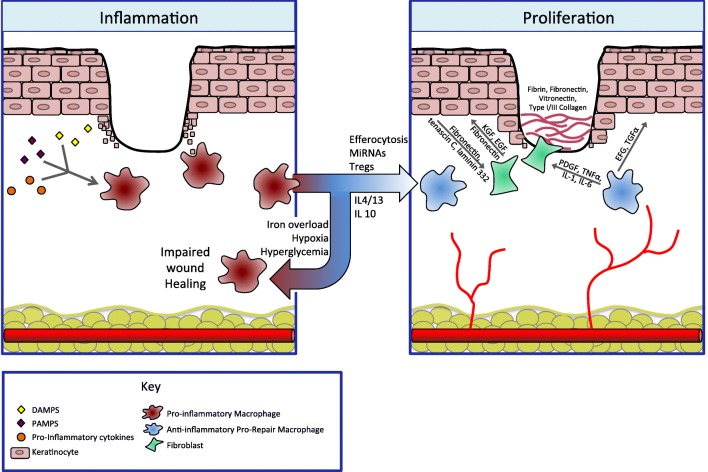
“Macrophages play a critical role in wound healing, and their roles in angiogenesis, fibroplasia, cell proliferation, and transition out of the inflammatory phase is clear (Fig. 2) [25–27, 60].”
§ Immunology of Wound Healing > Four Stages of Wound Healing > Inflammation
What the sources say
- Not checked yetcites [25] Leibovich SJ, Ross R. The role of the macrophage in wound repair. A study with hydrocortisone and antimacrophage serum. Am J Pathol. 1975;78(1):71–100.
- Not checked yetcites [26] Pinhal-Enfield G, Ramanathan M, Hasko G, Vogel SN, Salzman AL, Boons GJ, et al. An angiogenic switch in macrophages involving synergy between Toll-like receptors 2, 4, 7, and 9 and adenosine A(2A) receptors. Am J Pathol. 2003;163(2):711–21. https://doi.org/10.1016/s0002-9440(10)63698-x . source
- Not checked yetcites [27] Simpson DM, Ross R. The neutrophilic leukocyte in wound repair a study with antineutrophil serum. J Clin Invest. 1972;51(8):2009–23. https://doi.org/10.1172/jci107007 . source
- Not checked yetcites [60] Koh TJ, DiPietro LA. Inflammation and wound healing: the role of the macrophage. Expert Rev Mol Med. 2011;13:e23. https://doi.org/10.1017/s1462399411001943 . source
boosteddirect- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: unclear — It is unclear whether the paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
In the paper
“The inflammatory phase overlaps considerably with initial hemostasis, occurring during the first 72 h after tissue injury [16].”
§ Immunology of Wound Healing > Four Stages of Wound Healing > Inflammation
What the sources say
- Not checked yetcites [16] Eming SA, Martin P, Tomic-Canic M. Wound repair and regeneration: mechanisms, signaling, and translation. Sci Transl Med. 2014;6(265):265sr6. https://doi.org/10.1126/scitranslmed.3009337 . source
plaincorrelational- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: unclear — It is unclear whether the paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
In the paper
“After hemostasis is achieved, histamine released by the activated complement cascade causes capillary dilation and leakage, accelerating migration of inflammatory cells into the wound bed and full transition to the inflammatory phase of wound healing [15].”
§ Immunology of Wound Healing > Four Stages of Wound Healing > Hemostasis
What the sources say
- Not checked yetcites [15] Sinno H, Prakash S. Complements and the wound healing cascade: an updated review. Plast Surg Int. 2013;2013:146764–7. https://doi.org/10.1155/2013/146764 . source
plaindirect- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: unclear — It is unclear whether the paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
None of the sources cited for this claim have been checked yet.
In the paper
“neutrophil-derived proteases, such as elastase and matrix metalloproteinases (MMPs), can degrade healthy extracellular matrix (ECM), and increased levels of these proteases have been repeatedly detected in chronic wounds [52–56].”
§ Immunology of Wound Healing > Four Stages of Wound Healing > Inflammation
What the sources say
- Not checked yetcites [52] Briggaman RA, Schechter NM, Fraki J, Lazarus GS. Degradation of the epidermal-dermal junction by proteolytic enzymes from human skin and human polymorphonuclear leukocytes. J Exp Med. 1984;160(4):1027–42. source
- Not checked yetcites [53] Grinnell F, Zhu M. Fibronectin degradation in chronic wounds depends on the relative levels of elastase, alpha1-proteinase inhibitor, and alpha2-macroglobulin. J Invest Dermatol. 1996;106(2):335–41. source
- Not checked yetcites [54] Herrick S, Ashcroft G, Ireland G, Horan M, McCollum C, Ferguson M. Up-regulation of elastase in acute wounds of healthy aged humans and chronic venous leg ulcers are associated with matrix degradation. Lab Invest. 1997;77(3):281–8.
- Not checked yetcites [55] Nwomeh BC, Liang HX, Cohen IK, Yager DR. MMP-8 is the predominant collagenase in healing wounds and nonhealing ulcers. J Surg Res. 1999;81(2):189–95. https://doi.org/10.1006/jsre.1998.5495 . source
- Not checked yetcites [56] Pirila E, Korpi JT, Korkiamaki T, Jahkola T, Gutierrez-Fernandez A, Lopez-Otin C, et al. Collagenase-2 (MMP-8) and matrilysin-2 (MMP-26) expression in human wounds of different etiologies. Wound Repair Regen. 2007;15(1):47–57. https://doi.org/10.1111/j.1524-475X.2006.00184.x . source
plaindirect- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
None of the sources cited for this claim have been checked yet.
In the paper
“Platelet degranulation also leads to the release of inflammatory mediators such as interleukin (IL)-8, or CXCL8 (a potent neutrophil chemoattractant), in addition to IL-1α, IL-1β, IL-6, and tumor necrosis factor (TNF)-α, and activates the complement cascade [9, 14].”
§ Immunology of Wound Healing > Four Stages of Wound Healing > Hemostasis
What the sources say
plaindirect- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: unclear — It is unclear whether the paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
In the paper
“Dysregulation of any of these events can result in delayed wound healing and the potential to form chronic ulcers and/or excessive scarring [10••].”
§ Immunology of Wound Healing > Introduction
What the sources say
- Not checked yetcites [10••]
plaindirect- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
None of the sources cited for this claim have been checked yet.
In the paper
“Not only do anti-inflammatory, pro-repair macrophages produce VEGF, which promotes vessel sprouting, they also express two transmembrane proteins that have been shown to promote vascular anastomosis [80, 85, 86].”
§ Immunology of Wound Healing > Four Stages of Wound Healing > Proliferation
What the sources say
- Not checked yetcites [80] Brancato SK, Albina JE. Wound macrophages as key regulators of repair: origin, phenotype, and function. Am J Pathol. 2011;178(1):19–25. https://doi.org/10.1016/j.ajpath.2010.08.003 . source
- Not checked yetcites [85] Fantin A, Vieira JM, Gestri G, Denti L, Schwarz Q, Prykhozhij S, et al. Tissue macrophages act as cellular chaperones for vascular anastomosis downstream of VEGF-mediated endothelial tip cell induction. Blood. 2010;116(5):829–40. https://doi.org/10.1182/blood-2009-12-257832 . source
- Not checked yetcites [86] Affolter M, Zeller R, Caussinus E. Tissue remodelling through branching morphogenesis. Nat Rev Mol Cell Biol. 2009;10:831–42. https://doi.org/10.1038/nrm2797 . source
boosteddirect- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: unclear — It is unclear whether the paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
In the paper
“Wounds without IL-6 lack an appropriate inflammatory response and demonstrate stunted angiogenesis, collagen accumulation, and re-epithelialization [89].”
§ Immunology of Wound Healing > Four Stages of Wound Healing > Proliferation
What the sources say
- Not checked yetcites [89] Lin ZQ, Kondo T, Ishida Y, Takayasu T, Mukaida N. Essential involvement of IL-6 in the skin wound-healing process as evidenced by delayed wound healing in IL-6-deficient mice. J Leukoc Biol. 2003;73(6):713–21. source
plaindirect- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: unclear — It is unclear whether the paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
In the paper
“When the transition from a pro- to an anti-inflammatory macrophage phenotype is impaired, wound healing stalls in the inflammatory phase and a chronic wound results [10••].”
§ Immunology of Wound Healing > Four Stages of Wound Healing > Inflammation
What the sources say
- Not checked yetcites [10••]
plaindirect- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
The paper states this without a source or data behind it here, so there is nothing to check it against. The quote shows it is in the paper.
In the paper
“Additional signals, such as hyperglycemia in the setting of diabetes, hypoxia in the setting of arterial or venous insufficiency, or secondary infection likely also contribute to the persistence of pro-inflammatory macrophages.”
§ Immunology of Wound Healing > Four Stages of Wound Healing > Inflammation
hedgedconditional- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: unclear — It is unclear whether the paper’s conclusions depend on it.
- Based: unclear — It is unclear why the paper says it holds.
It may state two separate claims as one.
A conclusion the paper draws from its own results — it cites no other source for it, so there is none to check. The quote shows it is in the paper.
In the paper
“If wounds fail to transition from the inflammatory phase, pro-inflammatory macrophages persist and non-healing wounds develop.”
§ Immunology of Wound Healing > Conclusions
plaindirect- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
It may state two separate claims as one.
A conclusion the paper draws from its own results — it cites no other source for it, so there is none to check. The quote shows it is in the paper.
In the paper
“Numerous signals are responsible for the transition, most notably the apoptosis and phagocytosis of wound-bed resident neutrophils (efferocytosis).”
§ Immunology of Wound Healing > Conclusions
plaindirect- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: unclear — It is unclear why the paper says it holds.
It may state two separate claims as one.
The paper relies on this without support.
Findings from mouse models of wound healing can be generalized to human wound healing and chronic wounds.
“mouse models of wound healing have shown that in non-aged, non-impaired models, neutrophil depletion does not negatively affect wound healing as profoundly as macrophage deletion [25–27].”
“in a mouse model of iron overload, local wound macrophages persisted in a pro-inflammatory state with excess production of inducible nitric oxide synthase (iNOS), IL-12, and TNF-α, in addition to free radicals, leading to impaired wound healing [81].”
“inhibition of NETosis and NET function in mouse models of delayed wound healing improves outcomes [59•].”
Claims other papers make about this one
Each is checked against this paper’s own text: does it say what the citing paper says it does?
The source backs part of the claim, not all of it — or backs it for a different population, condition or comparison.
In the citing paper
“Immune regulators promote better surveillance and wound clearance in multiple tissues [75, 76].”
From Rejuvenation of three germ layers tissues by exchanging old blood plasma with saline-albumin (2020) · cites this paper as [75]
Experimental — accuracy not yet measuredIn the citing paper
“Indeed, these cells are known to be irreplaceable partners in a successful wound healing70.”
From Platelets induce increased estrogen production through NF-κB and TGF-β1 signaling pathways in endometriotic stromal cells (2020) · cites this paper as [70]
In the citing paper
“The absence or over-abundance of any of these cell types would derail the normal healing process, leading healing astray and causing pathological healing such as fibrosis70.”
From Platelets induce increased estrogen production through NF-κB and TGF-β1 signaling pathways in endometriotic stromal cells (2020) · cites this paper as [70]
Citations
Cites
Neutrophil Extracellular Traps Kill Bacteria
Brinkmann, V., Reichard, U., Goosmann, C., Fauler, B., Uhlemann, Y., Weiss, D. S., Weinrauch, Y., & Zychlinsky, A. (2004) · Science · doi:10.1126/science.1092385 · Cited by 10,268
Exploring the full spectrum of macrophage activation
Mosser, D. M., & Edwards, J. P. (2008) · Nature Reviews Immunology · doi:10.1038/nri2448 · Cited by 9,144
Pattern Recognition Receptors and Inflammation
Takeuchi, O., & Akira, S. (2010) · Cell · doi:10.1016/j.cell.2010.01.022 · Cited by 8,895
Mizgerd, J. P., Kubo, H., Kutkoski, G. J., Bhagwan, S. D., Scharffetter-Kochanek, K., Beaudet, A. L., & Doerschuk, C. M. (1997) · The Journal of Experimental Medicine · doi:10.1084/jem.186.8.1357 · Cited by 7,332
The chemokine system in diverse forms of macrophage activation and polarization
MANTOVANI, A., SICA, A., SOZZANI, S., ALLAVENA, P., VECCHI, A., & LOCATI, M. (2004) · Trends in Immunology · doi:10.1016/j.it.2004.09.015 · Cited by 6,534
Macrophage plasticity and polarization: in vivo veritas
Sica, A., & Mantovani, A. (2012) · Journal of Clinical Investigation · doi:10.1172/jci59643 · Cited by 6,335
MANTOVANI, A., SOZZANI, S., LOCATI, M., ALLAVENA, P., & SICA, A. (2002) · Trends in Immunology · doi:10.1016/s1471-4906(02)02302-5 · Cited by 5,528
Neutrophil recruitment and function in health and inflammation
Kolaczkowska, E., & Kubes, P. (2013) · Nature Reviews Immunology · doi:10.1038/nri3399 · Cited by 5,472
Monocyte and macrophage heterogeneity
Gordon, S., & Taylor, P. R. (2005) · Nature Reviews Immunology · doi:10.1038/nri1733 · Cited by 5,190
Wound repair and regeneration: Mechanisms, signaling, and translation
Eming, S. A., Martin, P., & Tomic-Canic, M. (2014) · Science Translational Medicine · doi:10.1126/scitranslmed.3009337 · Cited by 3,562
Cited by
Sorted by citations
Items 301–400 of 618
Fan, W., Lü, H., Shi, H., et al. (2024) · International Wound Journal · doi:10.1111/iwj.14913 · Cited by 11
Huang, L., Li, T., Geng, W., Xie, X., Wang, P., Deng, Y., Gao, Y., Bai, D., Tang, T. J., & Cheng, C. (2024) · Small · doi:10.1002/smll.202407046 · Cited by 11
Mahmoodi, M., Mirzababaie, S. A., Mokhtarzade, A., Roknabadi, A. T., Barikzehi, F., Mastori, M., Parsaeian, F., Kamaliyan, S. R., & Navabi, M. (2025) · International Journal of Biological Macromolecules · doi:10.1016/j.ijbiomac.2025.147220 · Cited by 12
Pourhashemi, E., Amini, A., Ahmadi, H., Ahrabi, B., Mostafavinia, A., Omidi, H., Asadi, R., Hajihosseintehrani, M., Rahmannia, M., Fridoni, M., et al. (2024) · Lasers in Medical Science · doi:10.1007/s10103-024-03974-8 · Cited by 10
“Disruption of the transition from inflammation to the proliferation stage, with persistent dominance of pro-inflammatory macrophages (M1 phenotype), can lead to non-healing wounds [10].”
Baglioni, E. A., Perego, F. R., Paolin, E., et al. (2024) · Frontiers in Medicine · doi:10.3389/fmed.2024.1417920 · Cited by 10
“Non-healing wounds have various consequences such as an increase in mortality, prolongation of hospitalizations, the need for further hospitalization and re-intervention, delay of adjuvant treatments for other pathologies, impairment of the aesthetic result, and psychosocial wellbeing (12).”
BackgroundChen, Y. Y., Murphy, E. J., Cao, Z. Q., Buckley, C., Cortese, Y. J., Chee, B. S., & Scheibel, T. (2024) · ACS Biomaterials Science & Engineering · doi:10.1021/acsbiomaterials.4c01605 · Cited by 10
Ali, A. M., Elkhouly, G. E., Orabi, A., Ismail, A., Barbosa, R. D. M., Riela, S., Viseras, C., & Abo‐zeid, Y. (2024) · BioNanoScience · doi:10.1007/s12668-024-01708-2 · Cited by 10
“In addition, wound is transitioned to the proliferative phase [111, 114] when M1 macrophages is polarized to the M2 type, where M2 macrophages is reported to produce pro-angiogenic factors e.g. VEGF that is essential to encourage capillaries to generate budding loops and branches that are required…”
Ezati, M., Hashemi, A., Zumberg, I., et al. (2025) · Macromolecular Bioscience · doi:10.1002/mabi.202400609 · Cited by 10
Immunomodulatory bioadhesive technologies
Lan, X., Johnston, E., Ning, T., Chen, G., Haglund, L., & Li, J. (2025) · Biomaterials · doi:10.1016/j.biomaterials.2025.123274 · Cited by 11
“Macrophages and myofibroblasts release various MMPs and catalyze the production of collagen, essential for local tissue integration [55,75].”
InfluentialJaiswal, P., Pandey, G., Kumar, S., Kolipaka, T., Misra, S. K., Kanaujiya, S., Rajinikanth, P. S., Srivastava, S., & Yadav, A. K. (2025) · Journal of Drug Delivery Science and Technology · doi:10.1016/j.jddst.2025.106872 · Cited by 10
Cheyne, C. D., Martens, A., & Spiegelaere, W. D. (2021) · Animals · doi:10.3390/ani11092728 · Cited by 11
“These pro-inflammatory immune cells are gradually replaced by pro-resolution M2-type macrophages, which resolve the initial inflammation and orchestrate the proliferation phase of wound healing [13,14].”
BackgroundSakthiganapathi, M., Yoganandam, G. P., & Gopal, V. (2022) · Avicenna Journal of Medical Biotechnology · doi:10.18502/ajmb.v15i1.11423 · Cited by 11
“Inflammation, proliferation, and remodeling are the three stages of wound healing 4 .”
BackgroundČoma, M., Manning, J. C., Kaltner, H., & Gál, P. (2023) · Expert Opinion on Therapeutic Targets · doi:10.1080/14728222.2023.2175318 · Cited by 10
“The main goal of the invading leukocytes is to eliminate pathogens, resolve inflammation, and remove necrotic cells/tissue [30].”
BackgroundPotential use of angiotensin receptor blockers in skin pathologies.
Hedayatyanfard, K., Khalili, A., Karim, H., Nooraei, S., Khosravi, E., Haddadi, N., Dehpour, A. R., & Bayat, G. (2023) · PubMed Central · doi:10.22038/ijbms.2023.66563.14606 · Cited by 10
“They found that angiotensin II and angiotensin (1-7) improve wound repair and increase keratinocyte and epidermal stem cell proliferation and the rate of epithelialization (8).”
BackgroundMethodInfluentialOintment of Ximenes americana promotes acceleration of wound healing in rats
Júnior, J. D. C. S. N., Estevão, L. R. D. M., Carbonel, A. A. F., et al. (2019) · Acta Cirúrgica Brasileira · doi:10.1590/s0102-865020190030000007 · Cited by 10
Porcine Small Intestinal Submucosa Mitral Valve Material Responses Support Acute Somatic Growth
Gonzalez, B. A., Issa, E. P., Mankame, O. V., Bustillos, J., Cuellar, A. V., Rodriguez, A. J., Scholl, F. G., Bibevski, S., Hernandez, L., Brehier, V., et al. (2019) · Tissue Engineering Part A · doi:10.1089/ten.tea.2019.0220 · Cited by 10
Senescence in a cell culture model for burn wounds
Kerschbaum, S., Wegrostek, C., Riegel, E., & Czerny, T. (2021) · Experimental and Molecular Pathology · doi:10.1016/j.yexmp.2021.104674 · Cited by 10
Protective Effect of Casticin on Experimental Skin Wound Healing of Rats
Sun, C., Yan, H.-M., Jiang, K., & Huang, L. (2022) · Journal of Surgical Research · doi:10.1016/j.jss.2021.12.007 · Cited by 11
Xu, J., Zimo, Y., Yuhan, D., Zhongyu, X., Kewei, Z., & Xiaolan, C. (2025) · Journal of Materials Science Materials in Medicine · doi:10.1007/s10856-025-06961-9 · Cited by 16
“The proliferative phase, a crucial stage commencing post-in fl ammation and lasting weeks, features fi broblast activation and collagen/ECM deposition to form granulation tissue that fi lls the wound bed [19].”
Recent advances in the application of functional hydrogels in skin wound healing
Bei, Z., & Zheng, J. (2024) · MedComm – Biomaterials and Applications · doi:10.1002/mba2.101 · Cited by 9
Hydrogel dressing composed of nanoAg@QAC promotes the healing of bacterial infected diabetic wounds
Zhou, Y., Huang, H., Yuan, Q. X., Ren, J., Wu, J., Zhao, X., Lin, Y.-C., Lin, Z., & Xu, L. (2024) · Biomaterials Advances · doi:10.1016/j.bioadv.2024.214143 · Cited by 9
Behara, M., & Goudy, S. L. (2023) · Frontiers in Physiology · doi:10.3389/fphys.2023.1148932 · Cited by 11
“Immediately following injury, the hemostasis and coagulation phase recruits platelets to the wound edge, leading to the formation of a hemostatic plug to stop bleeding (Ellis et al., 2018).”
BackgroundInfluentialYamane, T., Konno, R., Iwatsuki, K., et al. (2020) · Amino Acids · doi:10.1007/s00726-020-02831-6 · Cited by 9
Pernakov, M., Ermini, M. L., Sulaieva, O., et al. (2021) · Biomedicines · doi:10.3390/biomedicines9091215 · Cited by 9
“Initially, macrophages produce a broad range of proinflammatory cytokines and chemokines enhancing the inflammatory phase with PMN-leukocytes activation and recruitment [31].”
BackgroundBone Marrow-Derived Cells and Wound Age Estimation
Ishida, Y., Nosaka, M., & Kondo, T. (2022) · Frontiers in Medicine · doi:10.3389/fmed.2022.822572 · Cited by 9
“In the proliferative phase, macrophages release growth factors such as EGF and TGF-α to stimulate keratinocyte migration and proliferation (114).”
BackgroundPreparation and Application of Biomass-based Sprayable Hydrogels
Tan, Y., Cai, B., Li, X., & Wang, X. (2023) · Paper and Biomaterials · doi:10.26599/pbm.2023.9260006 · Cited by 9
Anitua, E., Zalduendo, M., Troya, M., et al. (2020) · Regenerative Medicine · doi:10.2217/rme-2020-0082 · Cited by 9
Caballero, M., Coll, S., & Navarrete, P. (2023) · Brazilian Journal of Otorhinolaryngology · doi:10.1016/j.bjorl.2023.101365 · Cited by 8
Zaidi, M. B., Khan, F., Jameel, F., Khan, I., Musharraf, S. G., & Salim, A. (2024) · Cell Biochemistry and Function · doi:10.1002/cbf.3946 · Cited by 8
Beirami, A. D., Akhtari, N., Noroozi, R., et al. (2024) · BMC Complementary Medicine and Therapies · doi:10.1186/s12906-024-04355-y · Cited by 8
“Wound healing can generally occur by four coinciding but discrete steps, including hemostasis, inflammation, proliferation, and ultimately, wound remodeling, which may be affected by various endogenous and exogenous factors [38–40].”
BackgroundSantoso, A. W., Amalia, E., Sari, K. I., Takarini, V., & Sufiawati, I. (2024) · Journal of Experimental Pharmacology · doi:10.2147/jep.s487373 · Cited by 8
“28 The inflammatory response is a natural and essential process that is highly coordinated and necessary for healing.”
BackgroundElshimy, R. M., El‐Shiekh, R. A., Okba, M. M., et al. (2024) · Inflammopharmacology · doi:10.1007/s10787-024-01591-z · Cited by 8
“After an injury, neutrophils are the first cells to enter the wound site and release pro-inflammatory mediators like TNF-α , IL-1β , and IL-6, which attract additional neutrophils with other immune cells and intensify the inflammatory process (Ellis et al. 2018).”
Coman, C.-G., Anisiei, A., Cibotaru, S., Ailincai, D., Pașca, S. A., Chabot, C., Gardikiotis, I., & Mititelu-Tarțău, L. (2024) · International Journal of Molecular Sciences · doi:10.3390/ijms252312709 · Cited by 8
“%) were purchased from Aldrich and used as received.”
Wang, S., Cheng, W., Wang, X., Wu, Z., & Su, J. (2025) · European journal of medical research · doi:10.1186/s40001-025-02667-4 · Cited by 11
“This process is contingent upon the severity of the injury to the organism and can vary in duration, ranging from weeks to years [40, 43].”
Du, S., Li, Y., Feng, Y., et al. (2025) · Chemical Engineering Journal · doi:10.1016/j.cej.2025.165816 · Cited by 8
Recent advances and biomedical applications of conductive hydrogels for wound repair
Wang, Y., Wang, Y., Wu, T. S., et al. (2025) · Journal of Materials Chemistry B · doi:10.1039/d5tb01130b · Cited by 8
Biomaterials strategy for promoting palatal wound healing
Tong, W., Ren, J., Yao, X., et al. (2025) · Frontiers in Bioengineering and Biotechnology · doi:10.3389/fbioe.2025.1646629 · Cited by 8
“Frontiers in Bioengineering and Biotechnology frontiersin.org macrophages), proin fl ammatory cytokines, proteases (MMPs, elastase), and reactive oxygen species (ROS), alongside reduced protease inhibitors (e.g., TIMPs) (Ellis et al., 2018).”
McGinnis, R. J., Song, B., Kim, H., Lorenzon, A., Shi, J., Zhao, L., Cho, C. S., Ganguly, A., & Xu, Z. (2025) · Cancers · doi:10.3390/cancers17233773 · Cited by 10
“The use of a higher pressure output may have also led to unintended collateral damage to surrounding tissue, which could impact the local immune response [38].”
Zhang, Y., Leng, K., Dong, M., Wu, J., Wang, Z., Zhu, Q., Gao, X., & Sun, Y. (2026) · Frontiers in Physiology · doi:10.3389/fphys.2026.1800001 · Cited by 11
“Models that fail to use aged animals (e.g., >18 months for mice) essentially model “ juvenile repair ” rather than the geriatric pathology of non-healing ulcers (Ellis et al., 2018).”
Blanchard, A. M., Staley, C. E., Shaw, L., et al. (2021) · Infection and Immunity · doi:10.1128/iai.00270-21 · Cited by 8
Bee products and diabetes mellitus
Maroof, K., & Gan, S. H. (2022) · Elsevier eBooks · doi:10.1016/b978-0-323-85400-9.00012-5 · Cited by 11
A Host-Directed Approach to the Detection of Infection in Hard-to-Heal Wounds
Burnet, M. W. M., Metcalf, D. G., Milo, S., Gamerith, C., Heinzle, A., Sigl, E., Eitel, K., Haalboom, M., & Bowler, P. G. (2022) · Diagnostics · doi:10.3390/diagnostics12102408 · Cited by 8
“Wound Healing: An Overview Wound healing is a complex, highly regulated process comprising four definite phases: homeostasis, inflammation, proliferation, and maturation [68].”
BackgroundInfluentialChallenges in cybersecurity: Lessons from biological defense systems
Schrom, E. C., Kinzig, A. P., Forrest, S., Graham, A. L., Levin, S. A., Bergstrom, C. T., Castillo‐Chávez, C., Collins, J. P., de Boer, R. J., Doupé, A., et al. (2023) · Mathematical Biosciences · doi:10.1016/j.mbs.2023.109024 · Cited by 8
Puri, S., Mandal, S. K., Jain, H., et al. (2024) · Journal of Food and Drug Analysis · doi:10.38212/2224-6614.3500 · Cited by 8
“If the anti-in fl ammatory and antioxidant functions are not active, it can lead to oxidative stress and persistent in fl ammation, slowing down the healing process and causing additional damage to the tissues [68].”
Biofabrication of thick vascularized neo-pedicle flaps for reconstructive surgery
Stephens, C. J., Spector, J. A., & Butcher, J. T. (2019) · Translational research · doi:10.1016/j.trsl.2019.05.003 · Cited by 8
Mateus, A. P., Mourad, M. M., & Power, D. M. (2020) · Developmental & Comparative Immunology · doi:10.1016/j.dci.2020.103989 · Cited by 8
Mechanisms of Collective Cell Migration in Wound Healing: Physiology and Disease
Mayya, C., Kharbhanda, S., Haque, A., & Bhatia, D. D. (2021) · Springer eBooks · doi:10.1007/978-981-16-2677-7_2 · Cited by 10
Metabolic regulation of type 2 immune response during tissue repair and regeneration
Ding, T., & Ge, S. (2022) · Journal of Leukocyte Biology · doi:10.1002/jlb.3mr0422-665r · Cited by 10
Elbatouti, G. A., Abdelhady, S. A., Yacout, D. M. M., Farrage, E. A., & Abdelwahab, I. A. (2023) · Journal of Pure and Applied Microbiology · doi:10.22207/jpam.17.2.01 · Cited by 10
Kinin B1 Receptor Signaling in Skin Homeostasis and Wound Healing.
Matus, C. E., Bhoola, K. D., & Figueroa, C. D. (2020) · PubMed Central · Cited by 8
Roosa, C., Muhamed, I., Young, A. T., et al. (2021) · Colloids and Surfaces B Biointerfaces · doi:10.1016/j.colsurfb.2021.111805 · Cited by 7
He, J., Fu, J., Wang, R., Liu, X., Yao, J., Xing, W., Wang, X., & He, Y. (2025) · Current Issues in Molecular Biology · doi:10.3390/cimb47070509 · Cited by 9
“However, adult wounds scar more, possibly because TGF-β 1 and TGF-β 2 dominate and TGF-β 3 is low [11].”
Vesicular drug delivery systems: A breakthrough in wound healing therapies
Lila, A. S. A., Mostafa, M., Katamesh, A. A., Ibrahim, M., Hassoun, S. M., Sayed, M. M. E., Subaiea, G. M., Abdallah, M. H., & Qelliny, M. R. (2025) · Colloids and Surfaces B Biointerfaces · doi:10.1016/j.colsurfb.2025.115046 · Cited by 8
Nuwayhid, R., Ngoc-Huyen, N., Notov, D., Langer, S., & Kurow, O. (2025) · Frontiers in Bioengineering and Biotechnology · doi:10.3389/fbioe.2025.1621566 · Cited by 8
“This also aligns with the physiological timeline of wound healing in vivo , where proliferation commences within 2 – 4 days (Landén et al., 2016; Ellis et al., 2018).”
Immunoglobulin G in Platelet‐Derived Wound Healing Factors
Seria, E., Tagliaferro, S. S., Cutajar, D., et al. (2021) · BioMed Research International · doi:10.1155/2021/4762657 · Cited by 7
“In combination with other local immune signals, this leads to the fundamental steps for the resolution of the inflammation [8].”
BackgroundLyu, X., Cui, F., Zhou, H., Cao, B., Zhang, X., Cai, M., Yang, S., Sun, B., & Li, G. (2023) · Biosensors and Bioelectronics · doi:10.1016/j.bios.2023.115111 · Cited by 7
Nano-Enabled Chronic Wound Healing Strategies: Burn and Diabetic Ulcer Wounds
Ngoepe, M. P., Battison, A., & Mufamadi, M. S. (2022) · Journal of Biomedical Nanotechnology · doi:10.1166/jbn.2022.3427 · Cited by 7
Ashames, A., Ijaz, M., Buabeid, M. A., Yasin, H. K. A., Yaseen, S., Bhandare, R. R., & Murtaza, G. (2024) · Molecules · doi:10.3390/molecules29030729 · Cited by 7
“Cutaneous wounds present a silent yet often overlooked burden on the healthcare systems and society, affecting millions of individuals annually [2].”
BackgroundMultifunctional nanocomposite hydrogels: an effective approach to promote diabetic wound healing
Hu, Y., Zhou, J., Gao, Y., et al. (2025) · Biomedical Materials · doi:10.1088/1748-605x/add06f · Cited by 7
“In the last maturation (remodeling) stage, collagen fibers reorganize to increase tissue strength [37, 38].”
Alginate-based bionanocomposites in wound dressings
Radoor, S., Karayil, J., Jayakumar, A., Radhakrishnan, E. K., Parameswaranpillai, J., & Siengchin, S. (2021) · Elsevier eBooks · doi:10.1016/b978-0-12-821280-6.00003-9 · Cited by 10
Synthesis of copper bearing borosilicate glass for soft tissue wound healing
Saghatchi, M., Abdollahi, S., Yekta, B. E., et al. (2022) · Ceramics International · doi:10.1016/j.ceramint.2022.09.304 · Cited by 7
Acute and Chronic Wound Management: Assessment, Therapy and Monitoring Strategies
Kabir, A., Sarkar, A., & Barui, A. (2023) · Springer eBooks · doi:10.1007/978-981-19-6008-6_6 · Cited by 8
Pro-regenerative Dialogue Between Macrophages and Mesenchymal Stem/Stromal Cells in Osteoarthritis
Bohaud, C., Contreras-López, R. A., Cruz, J. D. L., Terraza‐Aguirre, C., Wei, M., Djouad, F., & Jørgensen, C. (2021) · Frontiers in Cell and Developmental Biology · doi:10.3389/fcell.2021.718938 · Cited by 8
Nikolić, A., Milošević, I., Janković, A., Prokić, B., Nićković, E., Marković, D., Stevanović, M., Vukašinović‐Sekulić, M., Mišković‐Stanković, V., & Božinovski, T. L. (2025) · Gels · doi:10.3390/gels11050352 · Cited by 8
Zhou, C., Geng, Y., Zhang, C., Hsu, Y.-W., Ma, L., Li, M., Tang, Y., Guo, W., Li, M., & Wang, Y. (2025) · Burns & Trauma · doi:10.1093/burnst/tkaf049 · Cited by 6
“After an injury, blood vessels immediately constrict to reduce bleeding; subsequently,plateletsgatherandareactivatedatthewoundsite, forming a platelet plug, a process known as primary hemostasis [19].”
InfluentialApoptosis and Cell Clearance in Skin Wound Healing
Cleene, H. K. L. D., Keçeli, B. N., & Maschalidi, S. (2025) · Advances in experimental medicine and biology · doi:10.1007/978-3-031-92785-0_5 · Cited by 6
Mendonce, K. C., Palani, N., Monisha, P., Surya, P., & Rajadesingu, S. (2025) · Cells and Development · doi:10.1016/j.cdev.2025.204053 · Cited by 6
3D bioprinting of in vitro vascularized skin models and in vivo skin grafts
Zhang, S., Wan, Y., Niu, S., Zhou, H., Yang, H., Yin, J., Wu, Q., & Xu, H. (2026) · International Journal of Extreme Manufacturing · doi:10.1088/2631-7990/ae39b6 · Cited by 7
“Wound healing, which is a dynamic process involved with multiple cell types and growth factors, could be roughly divided into four main phases: hemostasis, inflammation, proliferation, and remodeling [7] .”
Stimuli‐responsive hydrogels: An intelligent tool for wound management
Zheng, D., Zhu, M., Liu, X., Zhang, C., Wu, D., Xie, T., Li, C., Zhao, P. Z., Chen, W., Fu, X., et al. (2026) · Interdisciplinary medicine · doi:10.1002/inmd.70104 · Cited by 8
Composite P(3HB-3HV)-CS Spheres for Enhanced Antibiotic Efficiency
Gherasim, O., Grumezescu, A. M., Ficai, A., et al. (2021) · Polymers · doi:10.3390/polym13060989 · Cited by 6
Nosrati, H., Tafti, M. F., Aghamollaei, H., Bonakdar, S., & Moghaddam, M. M. (2024) · Stem Cell Reviews and Reports · doi:10.1007/s12015-024-10767-7 · Cited by 6
“Mashinchian et al. (2014) fabricated biomimetic bacterial infections and secrete cytokines and growth factors that initiate the proliferation phase [103, 104].”
Fatima, N., Saleem, M., & Shahbaz, U. (2021) · Drug Research · doi:10.1055/a-1633-3010 · Cited by 6
“The bone marrow (BM) harbors a subset of cells capable of endothelial dif - ferentiation.”
BackgroundChen, Y., Chen, M., Wang, K., et al. (2024) · Journal of Biophotonics · doi:10.1002/jbio.202300429 · Cited by 6
Barbosa, J. S., de Moura, F. B. R., Ferreira, B. A., Martins, F. A., Muniz, E. H., Gomide, J. A. L., da Silva, C. V., Ribeiro, D. L., Araújo, F. D. A., & Tomiosso, T. C. (2021) · Advances in Research · doi:10.9734/air/2021/v22i130285 · Cited by 6
“the subsequent stages of healing (proliferative and remodeling phases) [15].”
BackgroundKim, J., Zhang, Z., Albadawi, H., et al. (2025) · Advanced Science · doi:10.1002/advs.202414642 · Cited by 5
Krishnaveni, K., Adityan, S., Murugasenapathi, N. K., & Palanisamy, T. (2025) · Sensors and Actuators B Chemical · doi:10.1016/j.snb.2025.137634 · Cited by 6
Fajardo, J. B., Vianna, M. H., Polo, A. B., et al. (2025) · International Journal of Biological Macromolecules · doi:10.1016/j.ijbiomac.2025.144960 · Cited by 5
Yuan, H., Li, B., Shao, X., Xi, Y., Cheng, S., Liu, A., & Zheng, B. (2025) · Nano Research · doi:10.26599/nr.2025.94907777 · Cited by 7
Alizadeh, M., Momeny, M., Khodadoust, E., Mahmoudi, S. M., Abolghasemi-Dehaghani, S., Zarrabi, M., Nouri, M., & Alizadeh, S. (2025) · ACS Applied Bio Materials · doi:10.1021/acsabm.5c01083 · Cited by 6
Roles of efferocytosis in wound repair: Process, cells, and signals
Sun, Y.-L., Guo, H.-Y., Bai, Y., Chen, J., & Li, Y.-H. (2025) · Genes and Diseases · doi:10.1016/j.gendis.2025.101937 · Cited by 8
“82 Notably, the mutual effect between apoptotic cells and macrophages results in the formation of apoptotic cell degradation products, and their metabolites, as well as other cytokines, prompt intracellular signaling cascades that in turn boost the switch from the M1 to M2 phenotype in cell…”
InfluentialDeep Eutectic Solvents in Chronic Wound Management: Current Developments and Future Prospects
Bastola, R., & Thapa, R. K. (2025) · International Journal of Nanomedicine · doi:10.2147/ijn.s572066 · Cited by 5
“42 This event is stimulated by tissue hypoxia and growth factors.”
Immunomodulatory role of decellularized extracellular matrix in skin wound healing
Savitri, C., Park, H. S., Kim, Y., Jang, Y.-J., Hyun, J., Lee, D., Kang, M., Park, K. M., Bhang, S. H., & Park, K. (2025) · Materials Today Bio · doi:10.1016/j.mtbio.2025.102672 · Cited by 7
Yuan, M., Liu, Y., Peng, X., Li, Z., & Lei, M. (2026) · Molecules · doi:10.3390/molecules31061024 · Cited by 9
“On the surface, wound healing is accompanied by a number of changes that are visible to the naked eye, and behind these visible changes are a series of complex processes involving various cells, growth factors, cytokines, and components of the ECM [99].”
Razani, S., Farhadpour, M., Hemmat, M. A., et al. (2024) · Heliyon · doi:10.1016/j.heliyon.2024.e32717 · Cited by 5
“These stages include homeostasis, inflammation, proliferation, repair, and finally, wound regeneration [90].”
BackgroundRahayu, P., Dermawan, D., Nailufar, F., Sulistyaningrum, E., & Tjandrawinata, R. R. (2024) · Biochimica et Biophysica Acta (BBA) - Proteins and Proteomics · doi:10.1016/j.bbapap.2024.141060 · Cited by 6
Sinha, A., Jain, P., & Ajazuddin, M. (2025) · Inflammopharmacology · doi:10.1007/s10787-025-01858-z · Cited by 5
“…interact with mechanical stresses to affect tissue regeneration and extracellular matrix production in the dermal and hypodermal layers (Ellis et al. 2018) VEGF receptors are composed of an intracellular portion that has a split tyrosine-kinase domain, an extracellular portion that…”
The dynamics of cell–extracellular matrix interactions, with implications for tissue engineering
Petreaca, M. L., & Martins‐Green, M. M. (2020) · Elsevier eBooks · doi:10.1016/b978-0-12-818422-6.00007-1 · Cited by 7
PAVLOV, S. B., Babenko, N., Kumetchko, M., Litvinova, O. B., & Valilshchykov, M. (2022) · Folia Medica · doi:10.3897/folmed.64.e61539 · Cited by 6
“Dysregulation can lead to delayed wound healing.[5] Wound healing usually goes through the phases of hemostasis, inflammation, proliferation, and remodelling.”
BackgroundAdvances in Nanocellulose for Wound Healing Applications
Patel, K. N., Shaikh, J., & Khan, T. A. (2022) · Springer eBooks · doi:10.1007/978-3-030-89621-8_42 · Cited by 5
Hydrogel-based Treatment Strategies to Accelerate Diabetic Foot Ulcer Healing
Mehta, S., Wadhwa, S., Nayak, S. R., & Kumar, R. (2023) · Current Diabetes Reviews · doi:10.2174/1573399819666230127150328 · Cited by 5
Engineered combinatorial cell device for wound healing and bone regeneration
Kadunc, L., Lainšček, D., Gašperšič, R., Sušjan, P., Kovačić, U., Butinar, M., Turk, B., Jerala, R., & Hafner‐Bratkovič, I. (2023) · Frontiers in Bioengineering and Biotechnology · doi:10.3389/fbioe.2023.1168330 · Cited by 6
“Epithelial to mesenchymal transition enhances keratinocyte migration and consequently reepithelization (Haensel and Dai, 2018), and immune cells that migrate to the wound site eliminate pathogens and secrete growth factors and cytokines (Ellis et al., 2018).”
BackgroundCassia Angustifolia Primed ASCs Accelerate Burn Wound Healing by Modulation of Inflammatory Response
Tasneem, S., Ghufran, H., Azam, M., et al. (2023) · Tissue Engineering and Regenerative Medicine · doi:10.1007/s13770-023-00594-1 · Cited by 5
“Therefore, during the inflammatory phase of wound healing, IL1b expresses concomitantly with TNFa but after progression to the proliferation phase, TNFa expression downregulates and indirectly supports the wound healing process [42, 44].”
The Potential of PIP3 in Enhancing Wound Healing
Blitsman, Y., Hollander, E., Benafsha, C., Yegodayev, K. M., Hadad, U., Goldbart, R., Traitel, T., Rudich, A., Elkabets, M., & Kost, J. (2024) · International Journal of Molecular Sciences · doi:10.3390/ijms25031780 · Cited by 5
Costa, V. D., Piovan, A., Filippini, R., & Brun, P. (2024) · Molecules · doi:10.3390/molecules29112472 · Cited by 5
“Moreover, at the steady state, C1-J, S1-J, and S2-J increased IL8 production in macrophages, inferring a chemoattractant activity able to sustain immune cell recruitment and wound healing [23].”
BackgroundNatural products for the treatment of hypertrophic scars: Preclinical and clinical studies
Zhang, Y., Liu, E., Gao, H., He, Q., Chen, A., Pang, Y., Zhang, X., Bai, S., Zeng, J., & Guo, J. (2024) · Heliyon · doi:10.1016/j.heliyon.2024.e37059 · Cited by 7
Benson, T. M., Markey, G. E., Hammer, J. A., Simerly, L., Dzieciątkowska, M., Jordan, K. R., Capocelli, K. E., Scullion, K., Crowe, L., Ryan, S. M., et al. (2024) · Mucosal Immunology · doi:10.1016/j.mucimm.2024.09.006 · Cited by 8
Seria, E., Galea, G., Borg, J., Schembri, K., Grech, G., Tagliaferro, S. S., & Felice, A. (2021) · BMC Molecular and Cell Biology · doi:10.1186/s12860-021-00366-6 · Cited by 5
“The expression of the genes encoding for IL-8 and transforming growth factor-α (TGFA), which are involved in the inflammatory phase [16] and the proliferative phase [17] of wound healing, were analysed to evaluate how the”
BackgroundChansamart, R., Sangvanich, P., & Thunyakitpisal, P. (2023) · The Open Dentistry Journal · doi:10.2174/18742106-v17-e230124-2022-75 · Cited by 5
Nakamura-García, A. K., Santos-Garfias, E. D. C., Alonso-Martínez, D. I., Garambullo-Peña, T. I., Covián-Nares, J. F., Gómez-Barroso, M., & Montoya-Pérez, R. (2022) · Revista Mexicana de Ingeniería Biomédica · doi:10.17488/rmib.43.1.2 · Cited by 5
“The wound healing process is impaired in chronic wounds, typically presenting a self-perpetuating inflammation state [7] with abundant neutrophil infiltration, which increases proteases and reactive oxygen species (ROS) levels that further damage the tissue [8], thus a frequent goal on wound management is to reduce in…”
BackgroundInnate immunity and wound repair: The platelet-rich fibrin advantage
Mohammadi, S. (2025) · World Journal of Biological Chemistry · doi:10.4331/wjbc.v16.i2.107195 · Cited by 5
“The wound microenvironment is a dynamic and complex milieu where a diverse array of immune cells and signaling molecules interact to modulate the repair process[22].”
Metadata
- Authors
- Ellis, S., Lin, E. J., & Tartar, D.
- Affiliations
- University of California, Davis (US)
- Corresponding author
- Tartar, Danielle
- ORCID
- Tartar, Danielle
- Venue
- Current Dermatology Reports
- Published
- 2018-09-28
- Volume
- 7
- Issue
- 4
- Pages
- 350-358
- ISSN
- 2162-4933 (ISSN-L)
- PMC
- PMC6244748
- OpenAlex
- W2892642834
- Semantic Scholar
- 2db5782e12aeaff45400ab4236b744f21a3178e0
- Cited by
- 625
- References
- 105
- Citations by year
- 2026: 65 · 2025: 114 · 2024: 109 · 2023: 90 · 2022: 96 · 2021: 86 · 2020: 44 · 2019: 21
- FWCI
- 4.74
- Type
- journal article
- Language
- en
- Open access
- hybrid
- doi.org
- Licence
- Locations
- Current Dermatology Reports (publishedVersion, cc-by)
- Europe PMC (PubMed Central) (publishedVersion, other-oa)
- PubMed Central (publishedVersion, cc-by)
- PubMed (publishedVersion)
- eScholarship (California Digital Library) (submittedVersion, cc-by)
- Topics
- Health Sciences › Medicine › Surgery › Wound Healing and Treatments
- Health Sciences › Medicine › Dermatology › Dermatologic Treatments and Research
- Health Sciences › Medicine › Hepatology › Liver physiology and pathology
- Keywords
- wound healing, chronic wounds, skin wound healing, neutrophils, efferocytosis, macrophages, interleukin-8, inflammation, angiogenesis, granulation tissue, myofibroblasts, scar formation, keratinocytes, dermal cells, immune signaling
About these checks
Registry, retraction, Cites and statistics results are computed, not judged, with one exception: a printed reference that no index lists is read once by a model before it counts as a citation error. Claims are extracted by a model and kept only when their quote appears verbatim in the text; each cited source is then checked, with a model’s help, for whether it says what the claim relies on. Those verdicts can be wrong — read the claim’s quote and the cited source before relying on one.
A language model drew the claims from the paper on 2026-10-10, under version 3 of the claim definition (model deepseek-v4.1-flash, prompt extract-v3).
A second model labelled each claim on 2026-10-10 (model jev-1.13-20260917, definition revision gold-guideline-v0.2).
Statistics and arithmetic are recomputed, not judged.
Confidence bands are shown only for fields calibrated on our annotated test set. None is calibrated yet, so no band is shown.
What counts as a claim ›How we measure confidence ›How we check this ›
Are you an author, or do you see a problem with this page? Request a review
