

Comparing group-based acceptance and commitment therapy (ACT) with enhanced usual care for adolescents with functional somatic syndromes: a study protocol for a randomised trial
Open accessThe DOI matches its Crossref record; 86 of the 89 references it cites were found in a registry or an index; 15 of the 62 sources its claims cite were checked for support.
Abstract
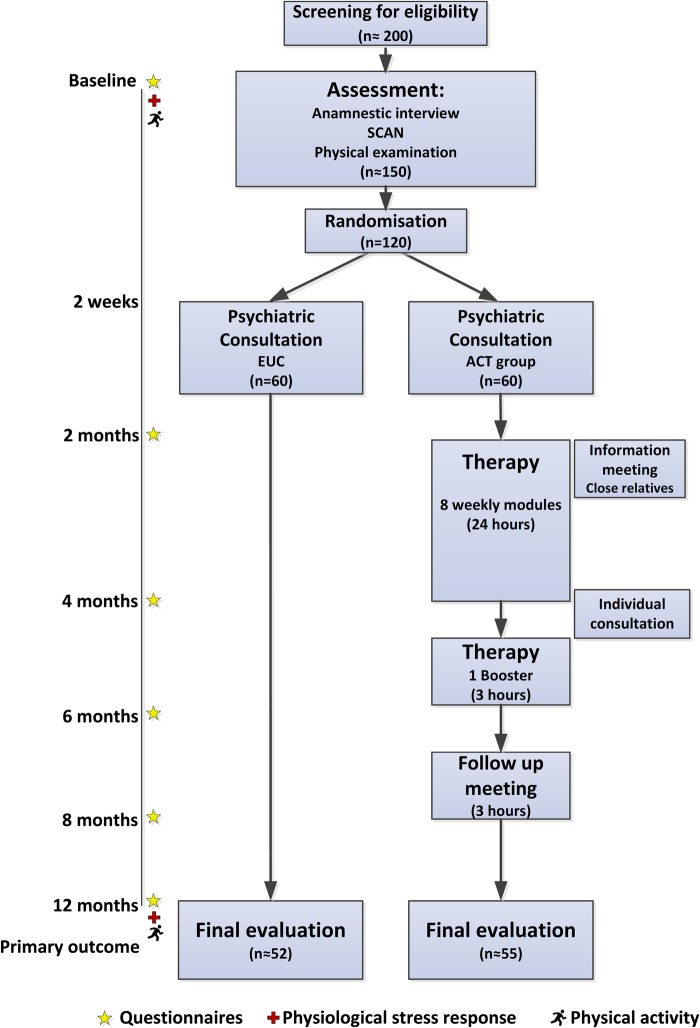
Introduction: Functional somatic syndromes (FSS) are common in adolescents, characterised by severe disability and reduced quality of life. Behavioural treatments such as acceptance and commitment therapy (ACT) has shown promising results in children and adolescents with FSS, but has focused on specific syndromes such as functional pain. The current study will compare the efficacy of group-based ACT with that of enhanced usual care (EUC) in adolescents with a range of FSS operationalised by the unifying construct of multiorgan bodily distress syndrome (BDS). Methods and analysis: A total of 120 adolescents aged 15-19 and diagnosed with multiorgan BDS, of at least 12 months duration, will be assessed and randomised to either: (1) EUC: a manualised consultation with a child and adolescent psychiatrist and individualised treatment plan or (2) manualised ACT-based group therapy plus EUC. The ACT programme consists of 9 modules (ie, 27 hours) and 1 follow-up meeting (3 hours). The primary outcome is physical health, assessed by an Short Form Health Survey (SF-36) aggregate score 12 months after randomisation. Secondary outcomes include selfreported symptom severity, symptom interference, depression and anxiety, illness worry, perceived stress and global improvement; as well as objective physical activity and bodily stress response measured by heart rate variability, hair cortisol and inflammatory biomarkers. Process measures are illness perception, illness-related behaviour and psychological flexibility. Ethics and dissemination: The study is conducted in accordance with Helsinki Declaration II. Approval has been obtained from the Science Ethics Committee of the Central Denmark Region and the Danish Data Protection. The results will be sought to be published according to the CONSORT statement in peer-reviewed journals. Discussion: This is one of the first larger randomised clinical trials evaluating the effect of a group-based intervention for adolescents with a range of severe FSS.
Overview
CoChat Summary
TL;DR
This is a study protocol for a single-site, non-blinded randomized controlled trial comparing manualized group-based ACT plus enhanced usual care with enhanced usual care alone for adolescents with multiorgan bodily distress syndrome (BDS). The trial plans to enroll 120 adolescents aged 15–19 and will assess physical health at 12 months as the primary outcome.
Key findings
- Not stated in the paper.
- The planned sample is 120 adolescents aged 15–19, randomized to EUC or ACT-based group therapy plus EUC.
- The ACT program consists of 9 modules (27 hours total) plus 1 follow-up meeting (3 hours).
- The primary outcome is physical health at 12 months, measured by an SF-36 aggregate score based on physical functioning, bodily pain, and vitality, with a score range of 15 to 65.
Methods
- Design: Single-site, non-blinded randomized controlled trial with two conditions: group-based ACT and enhanced usual care.
- Sample/data: Adolescents aged 15–19 with multiorgan BDS of at least 12 months’ duration, moderate-to-severe impairment, and Danish language/background criteria; 120 participants are planned.
- Analysis: Intention-to-treat analysis using random-effects model regression adjusted for prognostic baseline characteristics; missing data will be examined with a random-effects model on multiple imputed data.
Limitations
- The paper states there is no comparison with an evidence-based control treatment; the control is enhanced usual care rather than an active evidence-based psychotherapy.
- The paper states blinding is not possible for participants, therapists, and the clinician providing the standard psychiatric consultation.
- The paper states the study is in a specialized setting, which may limit generalizability to everyday clinical practice and other populations; it also says results cannot automatically be applied to younger adolescents.
- Evident from the text: this is a protocol, so the paper reports planned methods and outcomes rather than trial results.
Model-written summary. Check it against the paper before relying on it.
Integrity signals
Registry
Cites
Statistics
Figures

Verification
Claims the paper makes
9 Valid · 3 Not valid · 32 Not checked · 35 Own results and interpretations
Every source the paper cites for this claim was checked and supports it.
In the paper
“By reducing avoidance behaviour and symptom interference, ACT can increase functioning and enhance quality of life, through value-driven acceptance and exposure strategies.48”
§ Comparing group-based acceptance and commitment therapy (ACT) with enhanced usual care for adolescents with functional somatic syndromes: a study protocol for a randomised trial > Background Functional somatic syndromes (FSS), including chronic fatigue syndrome, juvenile fibromyalgia, functional gastrointestinal disorders and idiopathic pain syndromes, are well-known conditions in adolescents. FSS are diagnostic unities representing clusters of related functional somatic symptoms. Prevalence rates vary considerably due to differences in case definitions, assessment instruments and study populations.1–3 Studies attempting to cover the whole range of different functional somatic symptoms suggest that 5–10% of children and adolescents in the general population are substantially affected and likely to need care.4 5 Suffering from FSS during adolescence often has high personal and societal consequences. Adolescents have a higher risk of psychosocial problems such as social isolation, long-term school absence and reduced quality of life,6 and anxiety and depression are common comorbidities.7 8 A substantial proportion show continuity of functional symptoms into adulthood9–11 and are less likely to obtain a college education.9 Furthermore, adolescents diagnosed with FSS have higher overall healthcare costs due to increased use of medication and healthcare services.9 12 The aetiology of FSS remains unknown. Recent studies suggest a potential correlation between physiological stress and FSS, with physical inactivity as a potential covariate.13–16 It is proposed that a (patho)physiological response to prolonged or severe mental and/or physical stress in genetically susceptible individuals may trigger symptom development.17 High co-occurrence of different types of FSS, especially various pain syndromes, has been shown in children and adolescents.18–20 Children reporting multiple symptoms have an associated higher frequency of distress and impairment (eg, higher kindergarten/school absenteeism and consultations with physicians).21 Moreover, adult patients presenting with multiple symptoms from several organ systems have a poorer prognosis and a higher risk of chronification.22–24 Thus, an attempt to recognise the most severely affected patients with the highest illness burden may encompass sampling patients with the highest symptom load (ie, multiple symptoms from several organ systems). Recently, the empirically based unifying diagnostic category bodily distress syndrome (BDS) was introduced.25 The diagnosis describes specific symptom patterns and includes a multiorgan subtype and four single organ subtypes; in adult samples, it has been shown to capture a range of FSS including fibromyalgia, irritable bowel syndrome, non-cardiac chest pain and chronic fatigue syndrome.26 Multiorgan BDS comprising multiple symptoms from at least three specific symptom groups thus offers a diagnostic unity potentially including the most severely affected patients. Cognitive–behavioural therapy (CBT) has been shown to reduce symptoms and increase functioning in adults with FSS,27–30 whereas the evidence for treatment in adolescents is sparse. Family-based CBT and internet-delivered CBT have proven effective in young patients with specific FSS.31–36 However, the development of specifically tailored treatments for each FSS or symptom profile seems to be an inefficient strategy due to the costly nature of establishing separate clinics in each medical (sub)specialty, the fragmented care available and difficulty in handling multisymptomatic patients at those clinics.17 37 38 Recent studies suggest that adult patients with various FSS can feasibly receive the same treatment delivered in a group format, regardless of their main functional symptom.39 40 In adolescents, group treatment has been widely used and shown to be feasible in the treatment of psychiatric and non-psychiatric diseases.41 42 Group format offers several benefits including peer modelling, diminishment of stigma, increased motivation and higher acceptance of feedback from peers as opposed to professionals.43 Hence, a unified group-based treatment may be advantageous for adolescents with various FSS due to feasibility, accessibility of treatment and potential healthcare savings. Acceptance and commitment therapy (ACT), which derives from CBT, has shown promising results in children and adolescents with chronic functional pain.44 45 Evidence suggests that acceptance of pain is related to enhanced physical and emotional functioning, whereas attempts to control pain may lead to higher pain and disability.46 47 By reducing avoidance behaviour and symptom interference, ACT can increase functioning and enhance quality of life, through value-driven acceptance and exposure strategies.48 Symptom avoidance seems to be a general problem leading to disability and lower quality of life in patients with FSS.49 This provides a rationale for a therapeutic approach focused on reduction of avoidance behaviour and acceptance of somatic symptoms.
What the sources say
- Supportedcites [48] matched to “Acceptance and commitment therapy: model, processes and outcomes” (2006) source
The Acceptance section (p. 7) describes acceptance as an alternative to avoidance that increases values-based action, and Committed action (p. 9) includes exposure among ACT's behavior-change methods. Research on ACT (p. 12) links psychological flexibility with better quality-of-life outcomes, while Other studies (p. 19) reports improved functioning after ACT-based treatment. (LLM, conf=0.86)
plainstates a cause- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
- Supported
In the paper
“Acceptance and commitment therapy (ACT), which derives from CBT, has shown promising results in children and adolescents with chronic functional pain.44 45”
§ Comparing group-based acceptance and commitment therapy (ACT) with enhanced usual care for adolescents with functional somatic syndromes: a study protocol for a randomised trial > Background Functional somatic syndromes (FSS), including chronic fatigue syndrome, juvenile fibromyalgia, functional gastrointestinal disorders and idiopathic pain syndromes, are well-known conditions in adolescents. FSS are diagnostic unities representing clusters of related functional somatic symptoms. Prevalence rates vary considerably due to differences in case definitions, assessment instruments and study populations.1–3 Studies attempting to cover the whole range of different functional somatic symptoms suggest that 5–10% of children and adolescents in the general population are substantially affected and likely to need care.4 5 Suffering from FSS during adolescence often has high personal and societal consequences. Adolescents have a higher risk of psychosocial problems such as social isolation, long-term school absence and reduced quality of life,6 and anxiety and depression are common comorbidities.7 8 A substantial proportion show continuity of functional symptoms into adulthood9–11 and are less likely to obtain a college education.9 Furthermore, adolescents diagnosed with FSS have higher overall healthcare costs due to increased use of medication and healthcare services.9 12 The aetiology of FSS remains unknown. Recent studies suggest a potential correlation between physiological stress and FSS, with physical inactivity as a potential covariate.13–16 It is proposed that a (patho)physiological response to prolonged or severe mental and/or physical stress in genetically susceptible individuals may trigger symptom development.17 High co-occurrence of different types of FSS, especially various pain syndromes, has been shown in children and adolescents.18–20 Children reporting multiple symptoms have an associated higher frequency of distress and impairment (eg, higher kindergarten/school absenteeism and consultations with physicians).21 Moreover, adult patients presenting with multiple symptoms from several organ systems have a poorer prognosis and a higher risk of chronification.22–24 Thus, an attempt to recognise the most severely affected patients with the highest illness burden may encompass sampling patients with the highest symptom load (ie, multiple symptoms from several organ systems). Recently, the empirically based unifying diagnostic category bodily distress syndrome (BDS) was introduced.25 The diagnosis describes specific symptom patterns and includes a multiorgan subtype and four single organ subtypes; in adult samples, it has been shown to capture a range of FSS including fibromyalgia, irritable bowel syndrome, non-cardiac chest pain and chronic fatigue syndrome.26 Multiorgan BDS comprising multiple symptoms from at least three specific symptom groups thus offers a diagnostic unity potentially including the most severely affected patients. Cognitive–behavioural therapy (CBT) has been shown to reduce symptoms and increase functioning in adults with FSS,27–30 whereas the evidence for treatment in adolescents is sparse. Family-based CBT and internet-delivered CBT have proven effective in young patients with specific FSS.31–36 However, the development of specifically tailored treatments for each FSS or symptom profile seems to be an inefficient strategy due to the costly nature of establishing separate clinics in each medical (sub)specialty, the fragmented care available and difficulty in handling multisymptomatic patients at those clinics.17 37 38 Recent studies suggest that adult patients with various FSS can feasibly receive the same treatment delivered in a group format, regardless of their main functional symptom.39 40 In adolescents, group treatment has been widely used and shown to be feasible in the treatment of psychiatric and non-psychiatric diseases.41 42 Group format offers several benefits including peer modelling, diminishment of stigma, increased motivation and higher acceptance of feedback from peers as opposed to professionals.43 Hence, a unified group-based treatment may be advantageous for adolescents with various FSS due to feasibility, accessibility of treatment and potential healthcare savings. Acceptance and commitment therapy (ACT), which derives from CBT, has shown promising results in children and adolescents with chronic functional pain.44 45 Evidence suggests that acceptance of pain is related to enhanced physical and emotional functioning, whereas attempts to control pain may lead to higher pain and disability.46 47 By reducing avoidance behaviour and symptom interference, ACT can increase functioning and enhance quality of life, through value-driven acceptance and exposure strategies.48 Symptom avoidance seems to be a general problem leading to disability and lower quality of life in patients with FSS.49 This provides a rationale for a therapeutic approach focused on reduction of avoidance behaviour and acceptance of somatic symptoms.
What the sources say
- Not matchedcites 44 45
This doesn’t read as a citation we can look up.
plainstates a possible cause- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
- Not matched
In the paper
“Thorough assessment of all patients providing them with evidence-based understanding of their illness.”
- Also stated in: § Discussion · plain
“Furthermore, all patients are given a thorough assessment providing them with a positive and evidence-based understanding of their illness,88 89”
§ Comparing group-based acceptance and commitment therapy (ACT) with enhanced usual care for adolescents with functional somatic syndromes: a study protocol for a randomised trial > Abstract > Trial registration number
What the sources say
- Not matchedcites 88 89
This doesn’t read as a citation we can look up.
plain- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: unclear — It is unclear whether the paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
- Also stated in: § Discussion · plain
In the paper
“Recent studies suggest that adult patients with various FSS can feasibly receive the same treatment delivered in a group format, regardless of their main functional symptom.39 40”
§ Comparing group-based acceptance and commitment therapy (ACT) with enhanced usual care for adolescents with functional somatic syndromes: a study protocol for a randomised trial > Background Functional somatic syndromes (FSS), including chronic fatigue syndrome, juvenile fibromyalgia, functional gastrointestinal disorders and idiopathic pain syndromes, are well-known conditions in adolescents. FSS are diagnostic unities representing clusters of related functional somatic symptoms. Prevalence rates vary considerably due to differences in case definitions, assessment instruments and study populations.1–3 Studies attempting to cover the whole range of different functional somatic symptoms suggest that 5–10% of children and adolescents in the general population are substantially affected and likely to need care.4 5 Suffering from FSS during adolescence often has high personal and societal consequences. Adolescents have a higher risk of psychosocial problems such as social isolation, long-term school absence and reduced quality of life,6 and anxiety and depression are common comorbidities.7 8 A substantial proportion show continuity of functional symptoms into adulthood9–11 and are less likely to obtain a college education.9 Furthermore, adolescents diagnosed with FSS have higher overall healthcare costs due to increased use of medication and healthcare services.9 12 The aetiology of FSS remains unknown. Recent studies suggest a potential correlation between physiological stress and FSS, with physical inactivity as a potential covariate.13–16 It is proposed that a (patho)physiological response to prolonged or severe mental and/or physical stress in genetically susceptible individuals may trigger symptom development.17 High co-occurrence of different types of FSS, especially various pain syndromes, has been shown in children and adolescents.18–20 Children reporting multiple symptoms have an associated higher frequency of distress and impairment (eg, higher kindergarten/school absenteeism and consultations with physicians).21 Moreover, adult patients presenting with multiple symptoms from several organ systems have a poorer prognosis and a higher risk of chronification.22–24 Thus, an attempt to recognise the most severely affected patients with the highest illness burden may encompass sampling patients with the highest symptom load (ie, multiple symptoms from several organ systems). Recently, the empirically based unifying diagnostic category bodily distress syndrome (BDS) was introduced.25 The diagnosis describes specific symptom patterns and includes a multiorgan subtype and four single organ subtypes; in adult samples, it has been shown to capture a range of FSS including fibromyalgia, irritable bowel syndrome, non-cardiac chest pain and chronic fatigue syndrome.26 Multiorgan BDS comprising multiple symptoms from at least three specific symptom groups thus offers a diagnostic unity potentially including the most severely affected patients. Cognitive–behavioural therapy (CBT) has been shown to reduce symptoms and increase functioning in adults with FSS,27–30 whereas the evidence for treatment in adolescents is sparse. Family-based CBT and internet-delivered CBT have proven effective in young patients with specific FSS.31–36 However, the development of specifically tailored treatments for each FSS or symptom profile seems to be an inefficient strategy due to the costly nature of establishing separate clinics in each medical (sub)specialty, the fragmented care available and difficulty in handling multisymptomatic patients at those clinics.17 37 38 Recent studies suggest that adult patients with various FSS can feasibly receive the same treatment delivered in a group format, regardless of their main functional symptom.39 40 In adolescents, group treatment has been widely used and shown to be feasible in the treatment of psychiatric and non-psychiatric diseases.41 42 Group format offers several benefits including peer modelling, diminishment of stigma, increased motivation and higher acceptance of feedback from peers as opposed to professionals.43 Hence, a unified group-based treatment may be advantageous for adolescents with various FSS due to feasibility, accessibility of treatment and potential healthcare savings. Acceptance and commitment therapy (ACT), which derives from CBT, has shown promising results in children and adolescents with chronic functional pain.44 45 Evidence suggests that acceptance of pain is related to enhanced physical and emotional functioning, whereas attempts to control pain may lead to higher pain and disability.46 47 By reducing avoidance behaviour and symptom interference, ACT can increase functioning and enhance quality of life, through value-driven acceptance and exposure strategies.48 Symptom avoidance seems to be a general problem leading to disability and lower quality of life in patients with FSS.49 This provides a rationale for a therapeutic approach focused on reduction of avoidance behaviour and acceptance of somatic symptoms.
What the sources say
- Not matchedcites 39 40
This doesn’t read as a citation we can look up.
hedged- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
- Not matched
A statement the paper makes itself — it cites no source for it, so there is none to check. The quote shows it is in the paper.
In the paper
“whereas the evidence for treatment in adolescents is sparse.”
§ Comparing group-based acceptance and commitment therapy (ACT) with enhanced usual care for adolescents with functional somatic syndromes: a study protocol for a randomised trial > Background Functional somatic syndromes (FSS), including chronic fatigue syndrome, juvenile fibromyalgia, functional gastrointestinal disorders and idiopathic pain syndromes, are well-known conditions in adolescents. FSS are diagnostic unities representing clusters of related functional somatic symptoms. Prevalence rates vary considerably due to differences in case definitions, assessment instruments and study populations.1–3 Studies attempting to cover the whole range of different functional somatic symptoms suggest that 5–10% of children and adolescents in the general population are substantially affected and likely to need care.4 5 Suffering from FSS during adolescence often has high personal and societal consequences. Adolescents have a higher risk of psychosocial problems such as social isolation, long-term school absence and reduced quality of life,6 and anxiety and depression are common comorbidities.7 8 A substantial proportion show continuity of functional symptoms into adulthood9–11 and are less likely to obtain a college education.9 Furthermore, adolescents diagnosed with FSS have higher overall healthcare costs due to increased use of medication and healthcare services.9 12 The aetiology of FSS remains unknown. Recent studies suggest a potential correlation between physiological stress and FSS, with physical inactivity as a potential covariate.13–16 It is proposed that a (patho)physiological response to prolonged or severe mental and/or physical stress in genetically susceptible individuals may trigger symptom development.17 High co-occurrence of different types of FSS, especially various pain syndromes, has been shown in children and adolescents.18–20 Children reporting multiple symptoms have an associated higher frequency of distress and impairment (eg, higher kindergarten/school absenteeism and consultations with physicians).21 Moreover, adult patients presenting with multiple symptoms from several organ systems have a poorer prognosis and a higher risk of chronification.22–24 Thus, an attempt to recognise the most severely affected patients with the highest illness burden may encompass sampling patients with the highest symptom load (ie, multiple symptoms from several organ systems). Recently, the empirically based unifying diagnostic category bodily distress syndrome (BDS) was introduced.25 The diagnosis describes specific symptom patterns and includes a multiorgan subtype and four single organ subtypes; in adult samples, it has been shown to capture a range of FSS including fibromyalgia, irritable bowel syndrome, non-cardiac chest pain and chronic fatigue syndrome.26 Multiorgan BDS comprising multiple symptoms from at least three specific symptom groups thus offers a diagnostic unity potentially including the most severely affected patients. Cognitive–behavioural therapy (CBT) has been shown to reduce symptoms and increase functioning in adults with FSS,27–30 whereas the evidence for treatment in adolescents is sparse. Family-based CBT and internet-delivered CBT have proven effective in young patients with specific FSS.31–36 However, the development of specifically tailored treatments for each FSS or symptom profile seems to be an inefficient strategy due to the costly nature of establishing separate clinics in each medical (sub)specialty, the fragmented care available and difficulty in handling multisymptomatic patients at those clinics.17 37 38 Recent studies suggest that adult patients with various FSS can feasibly receive the same treatment delivered in a group format, regardless of their main functional symptom.39 40 In adolescents, group treatment has been widely used and shown to be feasible in the treatment of psychiatric and non-psychiatric diseases.41 42 Group format offers several benefits including peer modelling, diminishment of stigma, increased motivation and higher acceptance of feedback from peers as opposed to professionals.43 Hence, a unified group-based treatment may be advantageous for adolescents with various FSS due to feasibility, accessibility of treatment and potential healthcare savings. Acceptance and commitment therapy (ACT), which derives from CBT, has shown promising results in children and adolescents with chronic functional pain.44 45 Evidence suggests that acceptance of pain is related to enhanced physical and emotional functioning, whereas attempts to control pain may lead to higher pain and disability.46 47 By reducing avoidance behaviour and symptom interference, ACT can increase functioning and enhance quality of life, through value-driven acceptance and exposure strategies.48 Symptom avoidance seems to be a general problem leading to disability and lower quality of life in patients with FSS.49 This provides a rationale for a therapeutic approach focused on reduction of avoidance behaviour and acceptance of somatic symptoms.
plain- Asserted: passes — The authors put it forward as true.
- Checkable: passes — It can be checked against evidence.
- Load-bearing: passes — The paper’s conclusions depend on it.
- Based: passes — The paper gives a reason why it holds.
20 more claims
Create a free account to see all 79 claims and every source verdict.
- Probably not a substantial claim. 45
- It may state two separate claims as one. 21
Citations
Cites
A Global Measure of Perceived Stress
Cohen, S., Kamarck, T., & Mermelstein, R. (1983) · Journal of Health and Social Behavior · doi:10.2307/2136404 · Cited by 32,807
Guidelines for the process of cross-cultural adaptation of self-report measures
Beaton, D. E., Bombardier, C., Guillemin, F., & Ferraz, M. B. (2000) · Spine · doi:10.1097/00007632-200012150-00014 · Cited by 14,542 · cited 1×
“Three questionnaires (Limitation Index (LI),(52) Avoidance and Fusion Questionnaire in Youth (AFQ-Y8),(53) and Psychological Inflexibility in Pain Scale (PIPS-12)(54)) have been translated with reference to standard procedures with initial translation, synthesis of translations and back-translation.(55)”
MethodCONSORT 2010 Statement: updated guidelines for reporting parallel group randomised trials
the CONSORT Group, Schulz, K. F., Altman, D. G., & Moher, D. (2010) · BMC Medicine · doi:10.1186/1741-7015-8-18 · Cited by 13,371
Acceptance and commitment therapy: model, processes and outcomes
Hayes, S. C., Luoma, J. B., Bond, F. W., Masuda, A., & Lillis, J. (2006) · Behaviour Research and Therapy · doi:10.1016/j.brat.2005.06.006 · Cited by 6,587 · cited 1×
“47 By reducing avoidance behaviour and symptom interference, ACT can increase functioning and enhance quality of life, through value-driven acceptance and exposure strategies.(48) Symptom avoidance seems to be a general problem leading to disability and lower quality of life in patients with FSS.”
BackgroundCONSORT 2010 statement: updated guidelines for reporting parallel group randomized trials
Schulz, K. F., Altman, D. G., Moher, D., & for the CONSORT Group* (2010) · Annals of Internal Medicine · doi:10.7326/0003-4819-152-11-201006010-00232 · Cited by 3,824
THE McMASTER FAMILY ASSESSMENT DEVICE*
Epstein, N. B., Baldwin, L. M., & Bishop, D. S. (1983) · Journal of Marital and Family Therapy · doi:10.1111/j.1752-0606.1983.tb01497.x · Cited by 3,510
The Brief Illness Perception Questionnaire
Broadbent, E., Petrie, K. J., Main, J., & Weinman, J. (2006) · Journal of Psychosomatic Research · doi:10.1016/j.jpsychores.2005.10.020 · Cited by 3,431
SCAN: Schedules fonr Clinical Assessment in Neuropsychiatry
Wing, J. K. (1990) · Archives of General Psychiatry · doi:10.1001/archpsyc.1990.01810180089012 · Cited by 2,517
Review of the Psychometric Evidence of the Perceived Stress Scale
Lee, E.-H. (2012) · Asian Nursing Research · doi:10.1016/j.anr.2012.08.004 · Cited by 2,305
Psychometric properties of the credibility/expectancy questionnaire
Devilly, G. J., & Borkovec, T. D. (2000) · Journal of Behavior Therapy and Experimental Psychiatry · doi:10.1016/s0005-7916(00)00012-4 · Cited by 2,295 · cited 1×
“Credibility regarding treatment is assessed before the individual standard psychiatric consultation.(78) At end of treatment, that is, after module 9, the participants com-”
BackgroundGoodman, R., Ford, T., Richards, H., Gatward, R., & Meltzer, H. (2000) · Journal of Child Psychology and Psychiatry · doi:10.1111/j.1469-7610.2000.tb02345.x · Cited by 1,755
Confirmation of the dimensional structure of the scl-90: A study in construct validation
Derogatis, L. R., & Cleary, P. A. (1977) · Journal of Clinical Psychology · doi:10.1002/1097-4679(197710)33:4<981::aid-jclp2270330412>3.0.co;2-0 · Cited by 1,563
Fraley, R. C., Heffernan, M. E., Vicary, A. M., & Brumbaugh, C. C. (2011) · Psychological Assessment · doi:10.1037/a0022898 · Cited by 1,198
Pain in children and adolescents: a common experience
Perquin, C. W., Hazebroek-Kampschreur, A. A. J. M., Hunfeld, J. A. M., Bohnen, A. M., van Suijlekom-Smit, L. W. A., Passchier, J., & van der Wouden, J. C. (2000) · Pain · doi:10.1016/s0304-3959(00)00269-4 · Cited by 1,114
Russell, E., Koren, G., Rieder, M., & Van Uum, S. (2012) · Psychoneuroendocrinology · doi:10.1016/j.psyneuen.2011.09.009 · Cited by 1,063 · cited 1×
“It is measured from two strands of hair cut close to the scalp, since the proximal 1 cm segment of hair represents the cortisol level of the past month.(80) 3.”
BackgroundWhite, P., Goldsmith, K., Johnson, A., Potts, L., Walwyn, R., DeCesare, J., Baber, H., Burgess, M., Clark, L., Cox, D., et al. (2011) · The Lancet · doi:10.1016/s0140-6736(11)60096-2 · Cited by 897
Assessing the clinical significance of change scores recorded on subjective outcome measures
Hurst, H., & Bolton, J. (2004) · Journal of Manipulative and Physiological Therapeutics · doi:10.1016/j.jmpt.2003.11.003 · Cited by 702
Coping or acceptance? What to do about chronic pain
McCracken, L. M., & Eccleston, C. (2003) · Pain · doi:10.1016/s0304-3959(03)00202-1 · Cited by 591
Meeus, M., & Nijs, J. (2007) · Clinical Rheumatology · doi:10.1007/s10067-006-0433-9 · Cited by 541
Greco, L. A., Lambert, W., & Baer, R. A. (2008) · Psychological Assessment · doi:10.1037/1040-3590.20.2.93 · Cited by 514
Palermo, T. M., Eccleston, C., Lewandowski, A. S., de C. Williams, A. C., & Morley, S. (2010) · Pain · doi:10.1016/j.pain.2009.10.004 · Cited by 489
Epidemiology of Pediatric Functional Abdominal Pain Disorders: A Meta-Analysis
Korterink, J. J., Diederen, K., Benninga, M. A., & Tabbers, M. M. (2015) · PLOS ONE · doi:10.1371/journal.pone.0126982 · Cited by 481
Explaining medically unexplained symptoms-models and mechanisms
Rief, W., & Broadbent, E. (2007) · Clinical Psychology Review · doi:10.1016/j.cpr.2007.07.005 · Cited by 410
Wicksell, R. K., Melin, L., Lekander, M., & Olsson, G. L. (2009) · Pain · doi:10.1016/j.pain.2008.11.006 · Cited by 393
Self-citationThe Impact of Acceptance Versus Control Rationales on Pain Tolerance
Hayes, S. C., Bissett, R. T., Korn, Z., Zettle, R. D., Rosenfarb, I. S., Cooper, L. D., & Grundt, A. M. (1999) · The Psychological Record · doi:10.1007/bf03395305 · Cited by 388 · cited 1×
“Evidence suggests that acceptance of pain is related to enhanced physical and emotional functioning, whereas attempts to control pain may lead to higher pain and disability.(46) 47 By reducing avoidance behaviour and symptom interference, ACT can increase functioning and enhance quality of life, through value-driven a…”
BackgroundPsychological treatments for fibromyalgia: A meta-analysis
Glombiewski, J. A., Sawyer, A. T., Gutermann, J., Koenig, K., Rief, W., & Hofmann, S. G. (2010) · Pain · doi:10.1016/j.pain.2010.06.011 · Cited by 341
Fink, P., & Schröder, A. (2010) · Journal of Psychosomatic Research · doi:10.1016/j.jpsychores.2010.02.004 · Cited by 334 · cited 1×
“samples, it has been shown to capture a range of FSS including fibromyalgia, irritable bowel syndrome, noncardiac chest pain and chronic fatigue syndrome.(26) Multiorgan BDS comprising multiple symptoms from at least three specific symptom groups thus offers a diag-”
BackgroundSelf-citationRecurrent abdominal pain, headache and limb pains in children and adolescents
Øster, J. (1972) · PEDIATRICS · doi:10.1542/peds.50.3.429 · Cited by 332
Screening for somatization and hypochondriasis in primary care and neurological in-patients
Fink, P., Ewald, H., Jensen, J., Sørensen, L., Engberg, M., Holm, M., & Munk-Jørgensen, P. (1999) · Journal of Psychosomatic Research · doi:10.1016/s0022-3999(98)00092-0 · Cited by 314
Self-citationFink, P., Toft, T., Hansen, M. S., Ørnbøl, E., & Olesen, F. (2007) · Psychosomatic Medicine · doi:10.1097/psy.0b013e31802e46eb · Cited by 314 · cited 1×
“empirically based unifying diagnostic category bodily distress syndrome (BDS) was introduced.(25) The diagnosis describes specific symptom patterns and includes a mul-”
BackgroundSelf-citationHypothalamic-pituitary-adrenal axis dysfunction in chronic fatigue syndrome
Papadopoulos, A. S., & Cleare, A. J. (2012) · Nature Reviews Endocrinology · doi:10.1038/nrendo.2011.153 · Cited by 280 · cited 2×
“It is measured in various standardised situations (resting state, standing, slow breathing and valsalva) with the handheld device Vagus.16 71 79 2.”
BackgroundLevy, R. L., Langer, S. L., Walker, L. S., Romano, J. M., Christie, D. L., Youssef, N., DuPen, M. M., Feld, A. D., Ballard, S. A., Welsh, E. M., et al. (2010) · American Journal of Gastroenterology · doi:10.1038/ajg.2010.106 · Cited by 261
Robins, P. M., Smith, S. M., Glutting, J. J., & Bishop, C. T. (2005) · Journal of Pediatric Psychology · doi:10.1093/jpepsy/jsi063 · Cited by 254
Tests of Data Quality, Scaling Assumptions, and Reliability of the Danish SF-36
Bjorner, J. B., Damsgaard, M. T., Watt, T., & Groenvold, M. (1998) · Journal of Clinical Epidemiology · doi:10.1016/s0895-4356(98)00092-4 · Cited by 253
Kleinstäuber, M., Witthöft, M., & Hiller, W. (2011) · Clinical Psychology Review · doi:10.1016/j.cpr.2010.09.001 · Cited by 212
Nijhof, S. L., Bleijenberg, G., Uiterwaal, C. S., Kimpen, J. L., & van de Putte, E. M. (2012) · The Lancet · doi:10.1016/s0140-6736(12)60025-7 · Cited by 208
Calibration of ActiGraph GT3X, Actical and RT3 accelerometers in adolescents
Romanzini, M., Petroski, E. L., Ohara, D., Dourado, A. C., & Reichert, F. F. (2014) · European Journal of Sport Science · doi:10.1080/17461391.2012.732614 · Cited by 203 · cited 1×
“Physical activity Level of physical activity is assessed pretreatment and post-treatment by anthropometric measurements with an accelerometer (Actigraph wGT3X-BT).(72) The accelerometer is worn on the right hip 24 hours-a-day for seven consecutive days.”
MethodBoterhoven de Haan, K. L., Hafekost, J., Lawrence, D., Sawyer, M. G., & Zubrick, S. R. (2015) · Family Process · doi:10.1111/famp.12113 · Cited by 190
Psychological treatments for the management of irritable bowel syndrome
Zijdenbos, I. L., de Wit, N. J., van der Heijden, G. J., Rubin, G., & Quartero, A. O. (2009) · Cochrane Database of Systematic Reviews · doi:10.1002/14651858.cd006442.pub2 · Cited by 180
Wicksell, R. K., Lekander, M., Sorjonen, K., & Olsson, G. L. (2010) · European Journal of Pain · doi:10.1016/j.ejpain.2009.11.015 · Cited by 176
Self-citationMaes, M. H. J., Twisk, F., Kubera, M., & Ringel, K. (2011) · Journal of Affective Disorders · doi:10.1016/j.jad.2011.09.004 · Cited by 172
Medically unexplained symptoms in children and adolescents
Eminson, D. M. (2007) · Clinical Psychology Review · doi:10.1016/j.cpr.2007.07.007 · Cited by 172
Recurrent pain in children, socio-economic factors and accumulation in families
Grøholt, E.-K., Stigum, H., Nordhagen, R., & Köhler, L. (2003) · European Journal of Epidemiology · doi:10.1023/a:1025889912964 · Cited by 164
Adolescent Chronic Fatigue Syndrome: Prevalence, Incidence, and Morbidity
Nijhof, S. L., Maijer, K., Bleijenberg, G., Uiterwaal, C. S. P. M., Kimpen, J. L. L., & van de Putte, E. M. (2011) · Pediatrics · doi:10.1542/peds.2010-1147 · Cited by 162
Fjorback, L. O., Arendt, M., Ørnbøl, E., Walach, H., Rehfeld, E., Schröder, A., & Fink, P. (2013) · Journal of Psychosomatic Research · doi:10.1016/j.jpsychores.2012.09.006 · Cited by 144
Self-citationLong-Term Outcomes of Adolescents With Juvenile-Onset Fibromyalgia in Early Adulthood
Kashikar-Zuck, S., Cunningham, N., Sil, S., Bromberg, M. H., Lynch-Jordan, A. M., Strotman, D., Peugh, J., Noll, J., Ting, T. V., Powers, S. W., et al. (2014) · Pediatrics · doi:10.1542/peds.2013-2220 · Cited by 135
Chalder, T., Goldsmith, K. A., White, P. D., Sharpe, M., & Pickles, A. R. (2015) · The Lancet Psychiatry · doi:10.1016/s2215-0366(14)00069-8 · Cited by 134 · cited 1×
“The analytical strategy previously used in a large-scale trial will be used.(86)”
MethodPredicting Persistence of Functional Abdominal Pain From Childhood Into Young Adulthood
Horst, S., Shelby, G., Anderson, J., Acra, S., Polk, D. B., Saville, B. R., Garber, J., & Walker, L. S. (2014) · Clinical Gastroenterology and Hepatology · doi:10.1016/j.cgh.2014.03.034 · Cited by 133
Gauntlett-Gilbert, J., Connell, H., Clinch, J., & McCracken, L. M. (2013) · Journal of Pediatric Psychology · doi:10.1093/jpepsy/jss098 · Cited by 131
A new questionnaire to identify bodily distress in primary care: the 'BDS checklist
Budtz-Lilly, A., Fink, P., Ørnbøl, E., Vestergaard, M., Moth, G., Christensen, K. S., & Rosendal, M. (2015) · Journal of Psychosomatic Research · doi:10.1016/j.jpsychores.2015.03.006 · Cited by 129
(2005) · PubMed · Cited by 126
Tak, L., Riese, H., de Bock, G. D., Manoharan, A., Kok, I. C., & Rosmalen, J. (2009) · Biological Psychology · doi:10.1016/j.biopsycho.2009.05.002 · Cited by 124
Review of Group Interventions for Pediatric Chronic Conditions
Plante, W. A. (2001) · Journal of Pediatric Psychology · doi:10.1093/jpepsy/26.7.435 · Cited by 124 · cited 1×
“40 In adolescents, group treatment has been widely used and shown to be feasible in the treatment of psychiatric and nonpsychiatric diseases.(41) 42 Group format offers several benefits including peer modelling, diminishment of stigma, increased motivation and higher acceptance of feedback from peers as opposed to pro…”
MethodInsights in the use of health care services in chronic benign pain in childhood and adolescence
Perquin, C. W., Hunfeld, J. A. M., Hazebroek-Kampschreur, A. A. J. M., van Suijlekom-Smit, L. W. A., Passchier, J., Koes, B. W., & van der Wouden, J. C. (2001) · Pain · doi:10.1016/s0304-3959(01)00355-4 · Cited by 122
Customizing Treatment of Chronic Fatigue Syndrome and Fibromyalgia: The Role of Perpetuating Factors
Houdenhove, B. V., & Luyten, P. (2008) · Psychosomatics · doi:10.1176/appi.psy.49.6.470 · Cited by 122 · cited 3×
“Acceptance and commitment therapy (ACT), which derives from CBT, has shown promising results in children and adolescents with chronic functional pain.44 45 Evidence suggests that acceptance of pain is related to enhanced physical and emotional functioning, whereas attempts to control pain may lead to higher pain and d…”
BackgroundInfluentialExplanatory models of medically unexplained symptoms: a qualitative analysis of the literature.
van Ravenzwaaij, J., Hartman, T. O., van Ravesteijn, H., Eveleigh, R. M., van Rijswijk, E., & Lucassen, P. (2010) · PubMed Central · Cited by 121
Bodily distress syndrome: a new diagnosis for functional disorders in primary care?
Budtz-Lilly, A., Schröder, A., Rask, M. T., Fink, P., Vestergaard, M., & Rosendal, M. (2015) · BMC Family Practice · doi:10.1186/s12875-015-0393-8 · Cited by 115 · cited 1×
“daily life and symptom duration for a minimum of 12 months (table 1).(22) 26”
BackgroundSelf-citationChristensen, S. S., Frostholm, L., Ørnbøl, E., & Schröder, A. (2015) · Journal of Psychosomatic Research · doi:10.1016/j.jpsychores.2014.12.005 · Cited by 111 · cited 1×
“comparable study with adults, changes in illness perceptions partly mediated the effect of treatment on outcome.(76) Illness-related behaviour is measured by the Behavioural Responses to Illness Questionnaire (BRIQ)(67) (13 item, 5-point scale).”
MethodSPENCE, M., MOSS-MORRIS, R., & CHALDER, T. (2005) · Psychological Medicine · doi:10.1017/s0033291704003484 · Cited by 110 · cited 1×
“Specific illness-related behaviours have shown to be risk factors for development of FSS in adults.(67) Psychological flexibility is an area specifically targeted in ACT.”
BackgroundJuvenile fibromyalgia: current status of research and future developments
Kashikar-Zuck, S., & Ting, T. V. (2014) · Nature Reviews Rheumatology · doi:10.1038/nrrheum.2013.177 · Cited by 106
Neuroendocrine and Immunological Correlates of Chronic Stress in ‘Strictly Healthy’ Populations
Moriguchi Jeckel, C. M., Lopes, R. P., Berleze, M. C., Luz, C., Feix, L., Argimon, I. I. D. L., Stein, L. M., & Bauer, M. E. (2010) · Neuroimmunomodulation · doi:10.1159/000243080 · Cited by 106
Maes, M., Twisk, F. N. M., & Ringel, K. (2012) · Psychotherapy and Psychosomatics · doi:10.1159/000336803 · Cited by 97
Cognitive–behavioural group treatment for a range of functional somatic syndromes: Randomised trial
Schröder, A., Rehfeld, E., Ørnbøl, E., Sharpe, M., Licht, R. W., & Fink, P. (2012) · British Journal of Psychiatry · doi:10.1192/bjp.bp.111.098681 · Cited by 95 · cited 2×
“Furthermore, all patients are given a thorough assessment providing them with a positive and evidence-based understanding of their illness,(88) 89 and the treatment model is developed based on treatments with proven effect for both paediatric and adult patients with FSS and related disorders.(39) 40 44 Bias is minimis…”
BackgroundMethodSelf-citationAre adolescents with frequent pain symptoms more depressed?
Härmä, A.-M., Kaltiala-Heino, R., Rimpelä, M., & Rantanen, P. (2002) · Scandinavian Journal of Primary Health Care · doi:10.1080/pri.20.2.92.96 · Cited by 93 · cited 1×
“common comorbidities.(7) 8 A substantial proportion show continuity of functional symptoms into adulthood and are less likely to obtain a college education.”
Background(2007) · PubMed · Cited by 88
Rask, M. T., Ørnbøl, E., Rosendal, M., & Fink, P. (2017) · Psychosomatic Medicine · doi:10.1097/psy.0000000000000405 · Cited by 81
Self-citationSomatoform and related disorders
Garralda, M. E., & Rask, C. U. (2015) · Rutter's Child and Adolescent Psychiatry · doi:10.1002/9781118381953.ch72 · Cited by 81 · cited 1×
“Anticipated difficulties conducting the study include recruitment problems due to stringent inclusion and exclusion criteria as well as lack of knowledge of available service for adolescents and social prejudices in terms of receiving psychiatric diagnosis and psychological treatment for functional symptoms.(8)”
BackgroundSelf-citationVila, M., Kramer, T., Hickey, N., Dattani, M., Jefferis, H., Singh, M., & Garralda, M. E. (2009) · Journal of Pediatric Psychology · doi:10.1093/jpepsy/jsp005 · Cited by 67
Multiple somatic symptoms predict impaired health status in functional somatic syndromes
Creed, F. H., Tomenson, B., Chew-Graham, C., Macfarlane, G. J., Davies, I., Jackson, J., Littlewood, A., & McBeth, J. (2013) · International Journal of Behavioral Medicine · doi:10.1007/s12529-012-9257-y · Cited by 63
Effectiveness of groups for adolescents with Type 1 diabetes mellitus and their parents.
Kichler, J., Kaugars, A. S., Marik, P. K., Nabors, L., & Alemzadeh, R. (2013) · Families Systems & Health · doi:10.1037/a0033039 · Cited by 63
Husain, K., Browne, T., & Chalder, T. (2007) · Child and Adolescent Mental Health · doi:10.1111/j.1475-3588.2006.00419.x · Cited by 61
Steinhausen, H., & Winkler Metzke, C. (2007) · Journal of Child Psychology and Psychiatry · doi:10.1111/j.1469-7610.2006.01721.x · Cited by 60
Janssens, K. A. M., Oldehinkel, A. J., Verhulst, F. C., Hunfeld, J. A. M., Ormel, J., & Rosmalen, J. G. M. (2012) · Psychoneuroendocrinology · doi:10.1016/j.psyneuen.2011.06.016 · Cited by 56
Shevlin, M., & Elklit, A. (2008) · Nordic Journal of Psychiatry · doi:10.1080/08039480801983992 · Cited by 56 · cited 1×
“Potential predictors and moderators Relevant demographic data and potential important predictors for outcome, for example, predisposition to functional syndromes and number and kind of life events, are obtained as part of the diagnostic assessment.(70) Family functioning is assessed by the subscale on general function…”
MethodA brief diagnostic screening instrument for mental disturbances in general medical wards
Fink, P., Ørnbøl, E., Huyse, F. J., de Jonge, P., Lobo, A., Herzog, T., Slaets, J., Arolt, V., Cardoso, G., Rigatelli, M., et al. (2004) · Journal of Psychosomatic Research · doi:10.1016/s0022-3999(03)00374-x · Cited by 54
Self-citationUnexplained Physical Complaints
Garralda, M. E. (2011) · Pediatric Clinics of North America · doi:10.1016/j.pcl.2011.06.002 · Cited by 45 · cited 1×
“Studies attempting to cover the whole range of different functional somatic symptoms suggest that 5–10% of children and adolescents in the general population are substantially affected and likely to need care.(4) 5 Suffering from FSS during adolescence often has high personal and societal consequences.”
BackgroundSchröder, A., & Fink, P. (2011) · Psychiatric Clinics of North America · doi:10.1016/j.psc.2011.05.008 · Cited by 39 · cited 4×
“a range of FSS grouped under the unifying diagnosis of multiorgan BDS.(17) To do this, we will examine physical health and a range of other outcomes including level of”
BackgroundInfluentialSelf-citationFunctional Somatic Symptoms and Consultation Patterns in 5- to 7-Year-Olds
Rask, C. U., Ørnbøl, E., Fink, P. K., & Skovgaard, A. M. (2013) · Pediatrics · doi:10.1542/peds.2013-0159 · Cited by 39 · cited 1×
“Children reporting multiple symptoms have an associated higher frequency of distress and impairment (eg, higher kindergarten/school absenteeism and consultations with physicians).(21) Moreover, adult patients presenting with multiple symp-”
BackgroundSelf-citationEuteneuer, F., Schwarz, M., Hennings, A., Riemer, S., Stapf, T. M., Selberdinger, V. B., & Rief, W. (2011) · Psychiatry Research · doi:10.1016/j.psychres.2011.07.032 · Cited by 38
Schröder, A., Oernboel, E., Licht, R. W., Sharpe, M., & Fink, P. (2012) · Journal of Clinical Epidemiology · doi:10.1016/j.jclinepi.2011.03.012 · Cited by 38
Self-citationHolmström, L., Kemani, M. K., Kanstrup, M., & Wicksell, R. K. (2015) · Journal of Developmental & Behavioral Pediatrics · doi:10.1097/dbp.0000000000000191 · Cited by 37
Self-citationTak, L. M., Janssens, K. A. M., Dietrich, A., Slaets, J. P. J., & Rosmalen, J. G. M. (2010) · Psychotherapy and Psychosomatics · doi:10.1159/000296136 · Cited by 27
Medically unexplained symptom management
Schröder, A., Sharpe, M., & Fink, P. (2015) · The Lancet Psychiatry · doi:10.1016/s2215-0366(15)00233-3 · Cited by 27
Self-citationHeart rate variability in neurorehabilitation patients with severe acquired brain injury
Vistisen, S. T., Hansen, T. K., Jensen, J., Nielsen, J. F., & Fleischer, J. (2013) · Brain Injury · doi:10.3109/02699052.2013.860477 · Cited by 26
Assessment of Patients with Fibromyalgia Syndrome
Mease, P. J. (2008) · Journal of Musculoskeletal Pain · doi:10.1080/10582450801960347 · Cited by 20
Current state of management and organisation of care
Fink, P., Burton, C., De Bie, J., Söllner, W., & Fritzsche, K. (2011) · Medically Unexplained Symptoms, Somatisation and Bodily Distress · doi:10.1017/cbo9780511977862.005 · Cited by 14
Self-citation
Research works printed but not linked: 2
- Clarke GN , DeBar LL . Group cognitive-behavioral treatment for adolescent depression. In: Weisz J , Kazdin A, eds . Evidence-based psychotherapies for children and adolescents. 2nd edn. New York: The Guilford Press, 2010:111, 112, 121.
- Christensen, 2010, Measuring mental health by questionnaires in primary care—unidimensionality, responsiveness and compliance, Eur Psychiatr Rev, 3, 8
Cited by
Current status of acceptance and commitment therapy for chronic pain: A narrative review
Feliu Soler, A., Montesinos, F., Gutiérrez-Martínez, O., Scott, W., McCracken, L., & Luciano, J. (2018) · Journal of Pain Research · doi:10.2147/jpr.s144631 · Cited by 198
“72 Thus, only limited progress has been made in understanding which specific patient-level characteristics make someone with chronic pain a particularly good or poor candidate for ACT.”
InfluentialAcceptance and Commitment Therapy for Pediatric Chronic Pain: Theory and Application
Pielech, M., Vowles, K., & Wicksell, R. (2017) · Children · doi:10.3390/children4020010 · Cited by 99
“, [44]), cystic fibrosis [45], and anxiety disorders [46], as well as medical conditions that involve pain as a primary symptom [47].”
BackgroundSelf-citationFang, S., & Ding, D. (2020) · Journal of Contextual Behavioral Science · doi:10.1016/j.jcbs.2020.04.005 · Cited by 81
Kozlowska, K., Chudleigh, C., Savage, B., Hawkes, C., Scher, S., & Nunn, K. P. (2023) · Harvard Review of Psychiatry · doi:10.1097/hrp.0000000000000358 · Cited by 31
Frostholm, L., & Rask, C. U. (2019) · Clinical Psychology in Europe · doi:10.32872/cpe.v1i1.32217 · Cited by 18
“Recently, a study protocol describing the design of a large RCT comparing groupbased ACT with enhanced usual care for adolescents with various FSS was published (Kallesøe et al., 2016).”
BackgroundSelf-citation
Metadata
- Authors
- Kallesøe, K. H., Schröder, A., Wicksell, R. K., Fink, P., Ørnbøl, E., & Rask, C. U.
- Affiliations
- Aarhus University Hospital (DK)
- Karolinska Institutet (SE)
- Corresponding author
- Kallesøe, Karen Hansen
- ORCID
- Venue
- BMJ Open
- Publisher
- BMJ
- Published
- 2016-09
- Volume
- 6
- Issue
- 9
- Pages
- e012743
- ISSN
- 2044-6055 (ISSN-L)
- PMC
- PMC5030556
- OpenAlex
- W2519558121
- Cited by
- 23
- References
- 89
- Citations by year
- 2025: 2 · 2024: 4 · 2023: 2 · 2021: 4 · 2020: 3 · 2019: 3 · 2018: 2 · 2017: 2
- FWCI
- 2.07
- Type
- journal article
- Language
- en
- Open access
- gold
- doi.org
- Licence
- cc-by-nc
- Locations
- BMJ Open (publishedVersion, cc-by-nc)
- PubMed Central (publishedVersion, cc-by-nc)
- PubMed (publishedVersion)
- HighWire Press Open Archive (acceptedVersion)
- Funders
- TrygFonden
- Topics
- Health Sciences › Medicine › Psychiatry and Mental health › Psychosomatic Disorders and Their Treatments
- Social Sciences › Psychology › Clinical Psychology › Mindfulness and Compassion Interventions
- Health Sciences › Medicine › Psychiatry and Mental health › Fibromyalgia and Chronic Fatigue Syndrome Research
- Keywords
- functional somatic syndromes, acceptance and commitment therapy, group therapy, adolescents, enhanced usual care, physical health, heart rate variability, hair cortisol, inflammatory markers, psychological flexibility, illness perception, anxiety and depression, quality of life
- MeSH terms
- Adolescent, Adult, Anxiety, Depression, Female, Fibromyalgia, Gastrointestinal Diseases, Group Processes, Heart Rate, Humans, Hydrocortisone, Inflammation, Male, Pain, Quality of Life, Research Design, Stress, Physiological, Stress, Psychological, Syndrome, Fatigue Syndrome, Chronic, Young Adult, Pain Management, Acceptance and Commitment Therapy
About these checks
Registry, retraction, Cites and statistics results are computed, not judged, with one exception: a printed reference that no index lists is read once by a model before it counts as a citation error. Claims are extracted by a model and kept only when their quote appears verbatim in the text; each cited source is then checked, with a model’s help, for whether it says what the claim relies on. Those verdicts can be wrong — read the claim’s quote and the cited source before relying on one.
The claim verdicts this report counts are experimental: their accuracy is not yet measured.
A language model drew the claims from the paper on 2026-10-11, under version 3 of the claim definition (model deepseek-v4.1-flash, prompt extract-v3).
A second model labelled each claim on 2026-10-11 (model jev-1.13-20260917, definition revision gold-guideline-v0.2).
Cited sources are checked with a language model’s help (gpt-6-sol).
Statistics and arithmetic are recomputed, not judged.
Confidence bands are shown only for fields calibrated on our annotated test set. None is calibrated yet, so no band is shown.
What counts as a claim ›How we measure confidence ›How we check this ›
Are you an author, or do you see a problem with this page? Request a review
Data sources
Bibliographic data: Semantic Scholar, OpenAlex, Crossref.
Contains information from the Semantic Scholar Academic Graph Datasets, made available under the ODC Attribution License (ODC-BY 1.0).
Semantic Scholar’s data is described in: Kinney, R., et al. (2023). The Semantic Scholar Open Data Platform. arXiv:2301.10140.
